
Severe injuries resulting from traffic accidents and falls from heights are the most common reasons for admission to a trauma center.
Consequences of suicide attempts and crimes are significantly less common reasons for admission. In 2017, approximately 700 German hospitals reported about 35,000 seriously injured patients, 96% of whom were the result of blunt trauma (traffic accidents). Only about 4% were caused, for example, by a stab wound. Worldwide, 9% of deaths are attributable to accidents; among people under 45, trauma is the leading cause of death.
Local, regional, and national trauma centers all have the necessary expertise to care for patients with severe and critical injuries.
Trauma centers have a high level of emergency medical infrastructure and provide the highest level of care for the treatment of seriously and critically injured patients.
Thanks to a standardized emergency system and a high level of specialization, seriously injured patients in Germany have the best chances of survival.
The German Society for Trauma Surgery certifies these specialized hospitals.
The following departments operate within a trauma center:
- Orthopedics/Trauma Surgery
- Anesthesiology, as well as
- Visceral Surgery or
- General Surgery
In larger (supra-regional) centers, additional medical specialties are included, such as neurosurgery and vascular surgery.
Characteristic Features of Trauma Centers
Trauma centers ensure optimal care for patients with severe and critical injuries. They have at least one trauma room, also known as a resuscitation room. This is where initial treatment takes place.
The trauma room enables the following treatments:
- Maintaining or restoring vital functions (resuscitation)
- Ventilating the patient (if necessary)
- Stabilizing circulation as part of shock management
- Conducting initial imaging examinations (CT, X-ray, ultrasound)
- Performing life-saving emergency procedures
Since the workflows are standardized, the initial diagnosis and care are provided quickly.
This valuable time can mean the difference between life and death, as the patient receives life-saving surgery sooner.
Local, regional, and supraregional trauma centers are networked within the Trauma Network of the German Society for Trauma Surgery (DGU).
They differ in terms of:
- Number of triage room beds
- Equipment
- The specialist expertise available, and
- experience in treating complex injury patterns
Trauma centers are classified into the following categories:
Local trauma centers: They are responsible for providing comprehensive care for the most common individual injuries. Outside of metropolitan areas, they also provide initial care for critically injured patients when necessary.
Regional trauma centers: They specialize in the emergency and definitive care of severely injured patients. They have sufficient intensive care and surgical capacities.
Experts from a wide range of specialties are involved in treatment, and the equipment is of the highest standard.
Supraregional trauma centers: These are located at maximum-care hospitals and also specialize in the emergency care of critically injured patients.
Unlike regional trauma centers, they have more treatment stations in the trauma room. The physicians possess a higher level of specialized expertise in treating exceptionally complex and rare injuries.
 A trauma center can provide care for severely injured patients @ Adobe Contributor /AdobeStock
Certification by the German Society for Trauma Surgery
To ensure that the centers meet the requirements, they receive a certificate from the DGU. The criteria for this quality assurance are documented in the “DGU White Paper on Care for Severely Injured Patients.”
The requirements include:
- Facilities
- Personnel
- Professional and equipment-related criteria
The guidelines require a uniform approach to the care of critically injured patients in terms of personnel and organization. Treatment procedures are also standardized.
Trauma centers must be equipped with a trauma resuscitation room. There are additional criteria for the transfer of critically injured patients in the early phase.
The physicians are specially qualified and commit to participating in additional training programs such as ATLS or DSTC courses.
What are ATLS and DSTC courses?
The ATLS (Advanced Trauma Life Support) program is an international training course in which doctors learn standardized initial care for trauma patients.
They practice emergency scenarios in realistic simulations. Doctors learn to assess the patient’s condition quickly and accurately and to treat injuries and complications.
The DSTC (Definitive Surgical Trauma Care) concept describes the diagnostic and therapeutic measures following triage in the trauma room.
 Motorcycle accidents usually result in serious injuries @ AS Photo Family /AdobeStock
In specialized continuing education courses, doctors typically learn emergency surgical techniques using body donors or models, such as:
- Abdominal hemostasis
- Emergency thoracotomy and
- Retroperitoneal packing
These exercises enable them to perform life-saving procedures—even in the case of less common surgeries—safely, in a standardized manner, and with confidence.
What types of injuries are treated at a trauma center?
Trauma centers treat injuries:
- resulting from traffic accidents (car, motorcycle, bicycle, pedestrian)
- from falls from heights
- following suicide attempts, and
- following violent crimes (such as stab and gunshot wounds)
These blunt and penetrating trauma mechanisms can sometimes result in life-threatening injuries to:
- limbs
- Internal organs
- the head, as well as
- the chest (thorax) and abdomen
- Typical injury patterns include:
- Lung contusions
- Spinal fractures and spinal cord contusions
- Open fractures
- Traumatic brain injuries (skull fractures and cerebral hemorrhages)
- Internal bleeding
Polytrauma, which frequently occurs following a traffic accident, is characterized by injuries to multiple parts of the body. At least one of these injuries is life-threatening. Burns are also common as trauma emergencies.
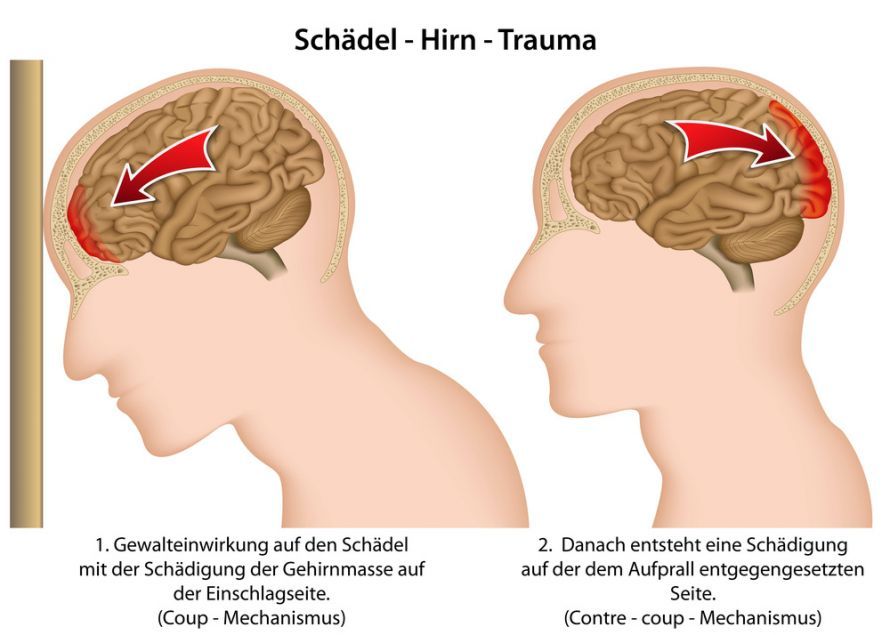
Traumatic brain injury often occurs after traffic accidents @ bilderzwerg /AdobeStock
Primary care comes before the trauma center
The severity of the injury and the measures taken in the first hour determine the patient’s prognosis.
Doctors must apply emergency measures in a highly targeted manner. Even at the scene of the accident, the emergency physician decides on further treatment.
Primary care at the scene of the accident includes stopping bleeding and treating chest injuries. Even in cases of severe traumatic brain injury, stabilizing vital functions is the top priority. This is because it’s also crucial to prevent secondary damage.
Furthermore, doctors ensure that breathing and circulation are maintained. A damaged brain cell is significantly more sensitive to oxygen deprivation than a healthy one. That is why rapid treatment of shock is the top priority.
The following points are particularly important as part of primary care:
- Keep the airways clear
- Ensure an adequate oxygen supply
- Stabilizing circulation
- Restoring acid-base balance
- Stabilizing fractures with splints
- Immobilize the spine to prevent further injury
Trauma Center: Every Minute Counts
Providing high-quality medical care quickly is the top priority in emergency medicine. It determines the chances of survival for accident victims.
After initial care at the scene of the accident, further surgical treatment takes place at a trauma center. This is because the specialists there are able to treat all injuries professionally and quickly.
Trauma centers therefore have helipads that emergency teams can land at around the clock.

About the medical author
Prof. Karl-Heinz Frosch
Medical Editor · Director of the Clinic and Polyclinic for Trauma, Hand and ReconstructiveSurgery · Hamburg
More about the medical author →Sources
- Clausen JD., Winkelmann M., Mommsen P. (2019) Modernes Traumamanagement. In: Engelhardt M., Raschke M. (eds) Orthopädie und Unfallchirurgie. Springer Reference Medizin. Springer, Berlin
- Deutsche Gesellschaft für Unfallchirurgie (2012) Weißbuch Schwerverletztenversorgung, 2. Aufl. Orthopädie und Unfallchirurgie, Supplement 1. http://www.traumanetzwerk-dgu.de/fileadmin/user_upload/traumanetzwerk-dgu.de/docs/20_07_2012_Weissbuch_DGU_Schwerverletztenversorgung_2.erweiterte_Auflage_01.pdf
- Deutsche Gesellschaft für Unfallchirurgie et al. (2016) Polytrauma / Schwerverletzten-Behandlung. S3-Leitlinie. AWMF-Register-Nr. 012-019. https://www.awmf.org/uploads/tx_szleitlinien/012-019l_S3_Polytrauma_Schwerverletzten-Behandlung_2017-08.pdf
- Deutsche Gesellschaft für Unfallchirurgie (2018) Jahresbericht 2018 - TraumaRegister DGU für den Zeitraum 2017. http://www.traumaregister-dgu.de/fileadmin/user_upload/traumaregister-dgu.de/docs/Downloads/TR-DGU-Jahresbericht_2018.pdf
- TraumaNetzwerk DGU. TraumaZentrum. http://www.traumanetzwerk-dgu.de/de/auditierung_zertifizierung/traumazentrum.html