
Aortic valve insufficiency, or aortic insufficiency for short, is a heart valve disorder characterized by incomplete closure of the aortic valve. The aortic valve (valva aortae) is one of the four heart valves. It is located in the aorta, directly at the junction with the left ventricle, which is why, anatomically speaking, it is also referred to as one of the heart’s two semilunar valves. Semilunar valves are the heart valves between the ventricles and the outgoing blood vessels. In the systemic circulation, this is the aorta, which is why the semilunar valve located there is called the aortic valve. The second semilunar valve in the body is located in the right heart, at the exit to the pulmonary circulation, and is therefore called the pulmonary valve.
The aortic valve ensures that no blood flows back from the aorta into the left side of the heart during the heart’s relaxation phase (diastole). However, in aortic valve insufficiency, the aortic valve no longer closes properly, resulting in blood flowing back from the aorta into the heart.
Below you will find further information as well as a selection of specialists for the treatment of aortic valve insufficiency.
What causes aortic valve regurgitation?
Aortic valve insufficiency can be congenital or acquired, although the congenital form is very rare. Since the heart develops very early in pregnancy, congenital aortic insufficiency often develops before the eighth week of pregnancy.
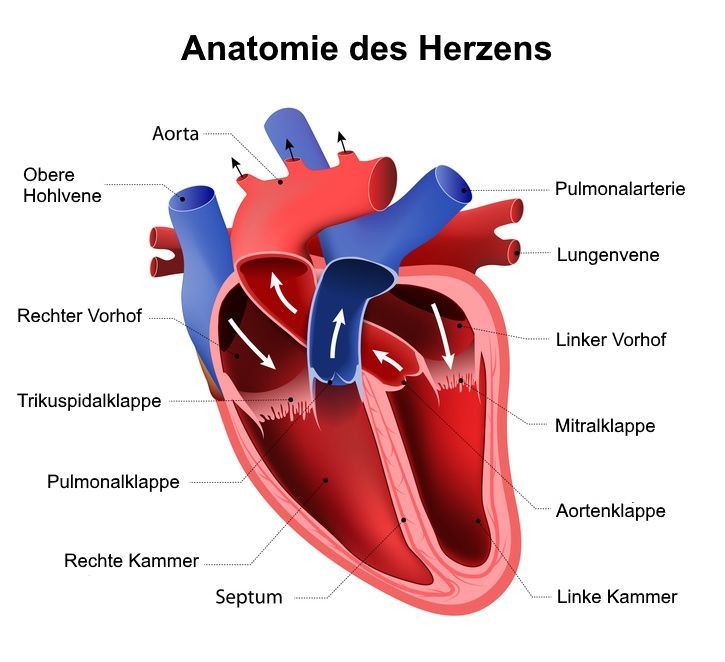
In addition to genetic factors, drug and alcohol use, as well as infection with the rubella virus, can contribute to the development of a heart valve defect. However, aortic valve insufficiency can just as easily result from a bacterial infection of the heart, known as endocarditis. The bacteria infect the aortic valve and damage its structure, preventing it from closing properly. However, this form of valve defect has become rare in Europe, as bacterial infections are now treated early with antibiotics.
Rheumatic valve defects also result from an infection. In the case of rheumatic fever, however, unlike bacterial endocarditis, this is a late rather than a direct consequence of the disease. If an infection with certain bacteria (usually streptococci) is present, the body produces antibodies against these pathogens. The surface structure of the bacteria resembles that of certain structures in the body, so the antibodies produced also attack these structures and cause inflammation. If these inflammatory processes occur in the area of the heart, the heart valves can be irreversibly damaged.
In a similar way, other conditions can cause aortic valve insufficiency, such as Marfan syndrome or Ehlers-Danlos syndrome. Furthermore, aortic valve insufficiency can result from excessive stretching of the valve components. However, this phenomenon is most commonly seen in people over the age of 60, or in cases of aortic dilation resulting from an aneurysm. As the aorta expands, the aortic valve is pulled apart and thus loses its functionality.
What are the symptoms of aortic valve insufficiency?
Milder forms of valve insufficiency are compensated for by the body and therefore go unnoticed by patients. In severe cases, shortness of breath (dyspnea) is the primary symptom. Depending on the severity, the volume of regurgitation can be as high as two-thirds of the ejection volume. This means that two-thirds of the blood that the left ventricle pumps into the aorta flows back during the heart’s diastolic phase. This backflow of blood is missing from the circulatory system and also places a strain on the left side of the heart.

The result is an enlargement of the left side of the heart, known as hypertrophy. Over decades, this cardiac hypertrophy leads to dysfunction of the heart muscle, causing left heart failure to gradually develop. The heart can no longer pump the volume of blood the body needs. This manifests as:
- shortness of breath during exertion and, later, even at rest,
- nocturnal coughing fits,
- fluid buildup in the lungs (pulmonary edema).
How is aortic valve insufficiency diagnosed?
If a heart valve defect is suspected, the doctor listens to the patient’s chest with a stethoscope. They can identify aortic valve regurgitation by a sound caused by the backflow of blood into the left ventricle. This Austin-Flint murmur is particularly audible over the apex of the heart.
Other important indicators of aortic valve regurgitation include a low diastolic blood pressure and a high blood pressure amplitude. Blood pressure amplitude is the difference between the systolic (upper) and diastolic blood pressure readings. Due to the backflow of blood during the heart’s relaxation phase (diastole), the diastolic blood pressure is low. Systolic blood pressure, on the other hand, is normal, resulting in an unusually large amplitude. The high blood pressure amplitude also leads to the characteristic Musset sign, a pulse-synchronous nodding of the patient’s head.
However, diagnostic testing is required to confirm the diagnosis. An ultrasound examination of the heart, known as echocardiography, can determine how much blood is flowing back into the ventricle. A cardiac catheterization, an electrocardiogram (ECG), or a chest X-ray can also be helpful in establishing the diagnosis.
How is aortic valve insufficiency treated?
In the early stages, the valve defect is treated with medication. ACE inhibitors, calcium channel blockers, and nitrates can relieve the strain on the heart by lowering blood pressure. If the patient suffers from shortness of breath and/or is at risk of cardiac decompensation, an artificial heart valve should be implanted. A distinction is made between mechanical heart valves and biological prostheses.
In some cases, aortic valve reconstruction may also be attempted. In this procedure, the surgeon restores the shape and function of the patient’s aortic valve without the need for foreign materials.
What is the prognosis for aortic valve insufficiency?
Overall, the prognosis for aortic valve insufficiency is generally good. Early surgery improves the prognosis and life expectancy of patients. However, to prevent blood clots from blocking blood vessels, patients with a mechanical heart valve must take anticoagulants for the rest of their lives.
Share this article

Sources
- Deutsche Herzstiftung e. V.
- Vogelgesang A et al., Diagnose und Therapie der Aortenklappenstenose. Der Internist 2018; 12: https://doi.org/10.1007/s00108-018-0519-x
- flexikon.doccheck.com/de/Herzklappenersatz





