
Miniphlebectomy is a minimally invasive procedure that allows for the targeted removal of small, short-segment varicose veins in the superficial venous system.
Find out here who the treatment is suitable for, how it is carried out and what you should bear in mind afterwards.
Background information on the venous system: How varicose veins develop
The heart pumps oxygen-rich blood through the arteries to all the organs and tissues of the body. Once the oxygen has been delivered, the deoxygenated venous blood flows back to the heart via the veins and on to the lungs. There, it is re-oxygenated, and the cycle begins again.
There are two venous systems in the legs: a deep system, which runs between the muscles, and a superficial system in the subcutaneous fatty tissue. Both are connected to one another via connecting veins, known as perforating veins. The superficial vessels drain venous blood from the skin and subcutaneous tissue into the deep system. To ensure that blood flows against gravity towards the heart, venous valves – acting like small one-way valves – prevent it from flowing backwards.
If these valves no longer close properly, some of the venous blood pools in the legs. The vessel walls give way, the veins dilate and become increasingly twisted or knotted. This is how varicose veins, medically known as varices, develop. They often shimmer bluish through the skin and are easily visible to the naked eye. Depending on the vessel affected, specialists distinguish between, amongst other things, dilations of the large trunk veins, lateral branch varices and, as the finest form, spider veins.
If such a venous disorder remains untreated, it can progress over time. Possible consequences include itchy eczema, phlebitis and blood clots, permanently swollen legs, poorly healing open sores on the lower leg, and varicose vein haemorrhages.
What is a mini-surgical phlebectomy (mini-phlebectomy)?
The term ‘phlebectomy’ is derived from the Greek words for ‘vein’ (phleb-) and ‘removal’ (-ectomy). In this procedure, a specialist or vein surgeon removes dilated superficial veins using fine, hook-shaped instruments, hence the name ‘hook method’. As only tiny incisions in the skin are required, the procedure is classified as a minimally invasive operation and is also referred to as a mini-surgical phlebectomy.
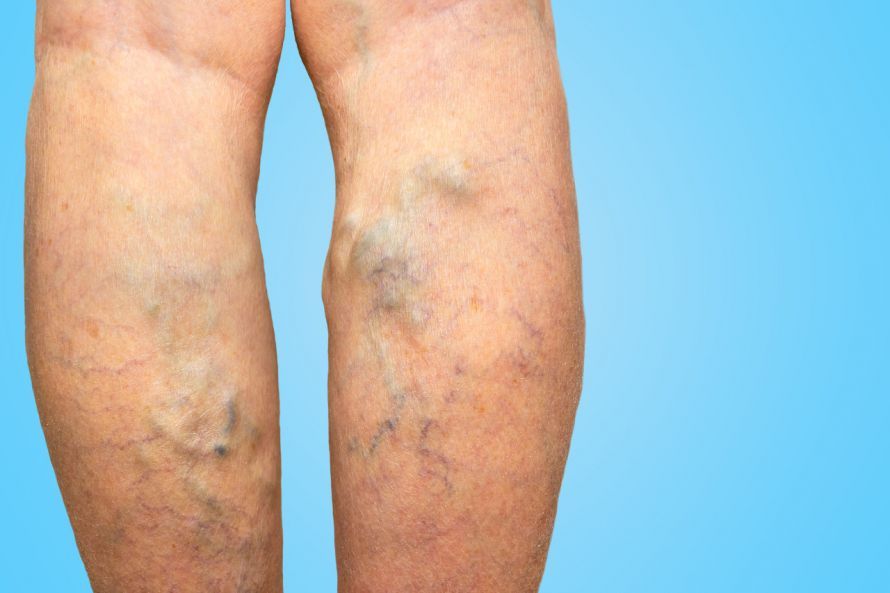
Through the small incisions, the surgeon gains access to the diseased vessel (varicose vein). Using the hook-shaped instrument, they grasp it so that it can be pulled out piece by piece. The diseased sections are thus permanently removed, and the healthy veins then take over the task of draining venous blood. The method is particularly suitable for lateral branch varicose veins, i.e. the dilated branches of the large main veins in the leg.
The surgical procedure was developed in the 1950s by the Swiss dermatologist Robert Muller. It is therefore also known as Muller’s phlebectomy. Today, the hook method is an established part of venous surgery. It meets both medical and aesthetic requirements, as only very small scars usually remain once healing is complete. The procedure can be carried out on an outpatient basis and does not require general anaesthesia, placing minimal strain on the body.
When is miniphlebectomy used?
The hook method is suitable exclusively for varicose veins that lie superficially in the subcutaneous tissue (spider veins). Typical areas of application include side-branch varicose veins and short-segment dilations of the two major veins in the leg: the great saphenous vein on the inner side of the leg and the small saphenous vein at the back of the lower leg. Leaky connecting veins between the superficial and deep venous systems (perforating varicosities) and isolated venous dilations in the subcutaneous tissue (phlebectasias) can also sometimes be treated in this way. The method may also be suitable for reticular varicose veins, i.e. fine, web-like veins just beneath the skin. For the very finest capillaries, however, other procedures such as sclerotherapy are usually considered.
The hook method is often combined with other procedures, such as closing off the affected trunk vein using laser therapy or radiofrequency waves. The most suitable approach in each individual case depends on the course of the affected vessels and on where the venous valves are no longer closing properly.
This treatment is not suitable in cases of acute deep vein thrombosis, severe systemic diseases or skin inflammation in the treatment area. Varicose veins that have developed as a result of a previous deep vein thrombosis are only treated surgically in exceptional cases, as they may serve as an important collateral circulation. Conversely, complications may make treatment more urgent. This applies, for example, to thrombophlebitis (vein inflammation), i.e. the inflammation of a superficial vein with clot formation, which spreads towards the deep venous system.
What preparations are necessary for a phlebectomy?
The first step is a detailed consultation at a practice or clinic specialising in vascular surgery, phlebology or dermatology. During this consultation, you will discuss your symptoms, any pre-existing conditions and medications, the planned procedure and any potential risks.
The key part of the diagnostic process is a specialised ultrasound scan of the leg veins, known as duplex sonography. This shows where the venous valves are leaking and the direction in which the blood is flowing. This enables the vein specialist to determine whether the ‘hook’ method is suitable and whether there are any reasons against it.
Some medicines affect blood clotting, including blood-thinning agents and the painkiller acetylsalicylic acid (ASA). Your doctor will determine whether and for how long you should stop taking such medicines before the procedure. Please never stop taking prescribed medication on your own initiative. You should also discuss during the preliminary consultation whether you should avoid alcohol or your usual sleeping tablets beforehand. If you smoke, you should significantly reduce your intake several weeks beforehand if possible, as nicotine impairs blood circulation and can hinder wound healing.
On the day of the treatment, the doctor will mark the varicose veins to be removed on your skin whilst you are standing, as the veins are most clearly visible in this position. If necessary, any hair in the treatment area will be removed. The skin is then thoroughly disinfected and covered with a sterile drape.
How does mini-surgical phlebectomy work?
First, the treatment area is numbed with a local anaesthetic. Tumescent anaesthesia is often used for this, whereby a larger volume of diluted anaesthetic solution is injected into the tissue beneath the skin. In some clinics, analgosedation is also available on request. This involves administering a calming and pain-relieving medication via an intravenous line, whilst you remain responsive.
The doctor then makes tiny incisions in the skin along the markings, known as puncture incisions. Each puncture is only a few millimetres in size and serves as an access point for the microsurgical instruments. Using a fine hook or a small haemostatic clamp (mosquito clamp), the doctor extracts the varicose vein from beneath the skin and removes it in sections.
The small wounds usually do not need to be stitched. They are treated with adhesive strips, skin glue or a plaster, over which a compression bandage is applied. Depending on the extent of the procedure, the operation usually takes between 30 and 60 minutes. After a short rest, you will usually be allowed to go home. If you have had analgosedation, you should arrange to be picked up and must not drive yourself on the same day.
What should you bear in mind after a miniphlebectomy?
After the procedure, you will initially wear a pressure dressing, and later usually medical compression stockings. Your doctor will determine how long this is necessary; it is often around two weeks. These are often colloquially referred to as ‘thrombosis stockings’. However, medical compression garments generally exert significantly greater pressure than the white stockings used for thrombosis prevention in hospital. The external pressure reduces post-operative bleeding and swelling, prevents blood clots and supports the healing process.
Exercise is just as important. Regular walking activates the calf muscle pump and reduces the risk of thrombosis. However, you should avoid standing or sitting for long periods, as well as heat from saunas, sunbathing or hot baths, during the first few weeks.
The dressing is changed approximately every two to four days. To reduce pain, standard medication recommended by your doctor is usually sufficient. A follow-up appointment takes place around two weeks after the operation.
What are the benefits, complications and risks associated with miniphlebectomy?
Compared with open surgery, the hook method offers several advantages. As it is carried out on an outpatient basis under local anaesthetic, there are none of the risks associated with general anaesthesia. Recovery time is short; many patients are able to resume their daily routines largely as normal after just a few days. Thanks to the tiny incisions, scarring is usually minimal. Furthermore, the removal of the affected veins often helps to reduce pain, such as a feeling of tightness or heavy legs.
Overall, the method is regarded as a gentle treatment with low risk. Nevertheless, as with any medical procedure, side effects may occur.
Common side effects
The most common side effects of the operation include short-lived conditions such as
- bruising,
- swelling,
- wound healing complications,
- a feeling of tightness or pressure,
- skin nerve damage causing numbness or pain,
- skin rash, sneezing, itching, watery eyes, vomiting or dizziness as overreactions to the anaesthetic.
Rare serious complications
Serious complications are very rare. These include wound infection, which in extreme cases can progress to septicaemia. Thrombosis – that is, a blood clot in a blood vessel in the leg – is also possible. If such a clot breaks loose and is carried by the bloodstream into the lungs, it causes an embolism. In addition, prolonged swelling of the leg due to lymphatic congestion or permanent nerve damage may occur. A life-threatening allergic reaction to the anaesthetic is extremely rare.
Your doctor will carefully weigh up these risks against the expected benefits beforehand. The treatment will only be recommended if the benefits clearly outweigh the risks for you.
Frequently Asked Questions (FAQ)
Is a phlebectomy painful?
Thanks to local anaesthesia, most patients feel no more than a slight pressure or tugging sensation during the treatment. The injection of the anaesthetic may be briefly uncomfortable. Afterwards, mild pain or a feeling of tightness is normal for a few days and can usually be easily relieved.
How gentle is the hook method compared to other procedures?
Compared to traditional vein stripping, in which an entire trunk vein is removed via larger incisions, the hook method is significantly less invasive. It does not require a general anaesthetic, causes only tiny wounds and allows for a rapid return to everyday life. However, it is only suitable for certain, superficial sections of the veins and does not always replace treatment for a diseased trunk vein.
Does every varicose vein need to be surgically removed?
No, not every varicose vein requires treatment. In mild cases where there are no symptoms, regular exercise and, if necessary, compression therapy may be sufficient. If symptoms or complications arise, there are other options available alongside the hook method, such as sclerotherapy or catheter procedures using laser or radiofrequency energy. A thorough ultrasound examination will determine which method is most appropriate.
What is the risk of complications?
The hook method is one of the procedures in vascular medicine with a low risk of complications. The most common side effects are bruising, swelling and temporary changes in skin sensation. Serious complications such as infections or thrombosis are very rare. Your personal risk depends, amongst other things, on the extent of the treatment and any pre-existing conditions, and can be discussed during the preliminary consultation.
Will there be any scars left after the treatment?
No operation heals completely without leaving any scars. As the incisions are only a few millimetres long and usually do not require stitches, they are generally barely visible once they have healed. Protect the fresh scars from strong sunlight during the first few months to prevent them from darkening.
Can varicose veins return after treatment?
The sections of vein that have been removed will not return. However, as a predisposition to weak vein walls is often hereditary, new varicose veins may form elsewhere over the years. Regular exercise, a healthy body weight and follow-up appointments at the specialist’s surgery help to detect any changes at an early stage.


