
Lacrimal duct surgery is an important procedure in ophthalmology used to treat narrowed or blocked lacrimal ducts. Lacrimal duct stenosis, in particular, leads to impaired drainage of tears. At the eye clinic, dacryocystorhinostomy is frequently performed to create a new connection between the lacrimal sac and the nasal cavity.
This surgery can be performed using traditional methods or via endoscopic and endonasal techniques. The goal is to restore the natural drainage pathway and reduce symptoms such as watery eyes. The procedure is often performed under general anesthesia and may be assisted by a tube. Modern techniques allow for minimally invasive treatment. The ophthalmologist determines the appropriate method on a case-by-case basis.
Anatomical Background
The lacrimal gland in the eye continuously produces tear fluid. This fluid is necessary to
- keep the surface of the eye constantly moist and
- to flush foreign bodies out of the eye.
Excess fluid normally collects on the lower eyelid. From there, it drains through the tear ducts to the nose.
The tear duct system begins at the so-called “lacrimal puncta.” These are two small openings in the upper and lower eyelids. Through these openings, the fluid enters a small canal (“canaliculus lacrimalis”). The canal empties into the lacrimal sac between the inner corner of the eye and the nose. The lacrimal sac then leads into the nasolacrimal duct. This duct runs through the bony structures surrounding the nose.
The tear fluid thus ultimately reaches the nasal cavity.
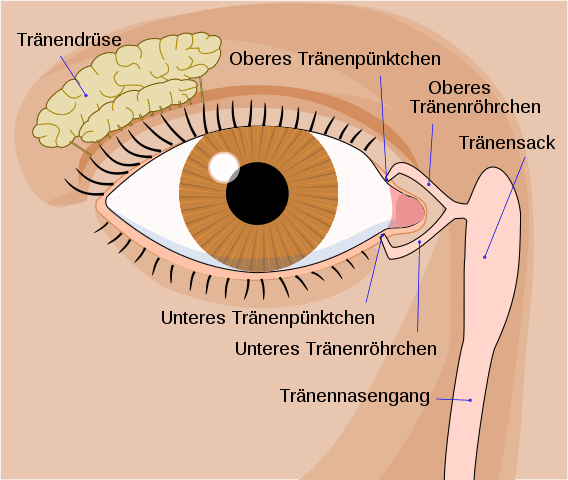
Blinking spreads tear fluid evenly across the front of the eye, keeping it moist and healthy. At the same time, the eyelids push fluid into the lacrimal puncta, through which it enters the lacrimal canal.
If the tear ducts are blocked or narrowed (lacrimal duct stenosis), the fluid cannot drain properly. As a result, it can only spill over the eyelids. This makes those affected look as if they are constantly crying.
In addition, vision is impaired. Patients feel as though they are “looking through an aquarium.” This is particularly noticeable when reading.
Tears that remain in the lacrimal sac for an extended period can also lead to a secondary infection.
Indications for Lacrimal Duct Surgery
The most common symptom of a tear duct dysfunction is excessive tearing. This can result from
- mucus buildup,
- eye irritation, and
- painful swelling at the inner corner of the eye
.
A more detailed examination reveals the location of the blockage and its cause. This blockage usually must be removed through surgery.
If a tear duct dysfunction remains untreated, an infection may develop as a result. This, in turn, can sometimes lead to
- an abscess,
- cellulitis (a soft-tissue infection), or
- a fistula (an abnormal tear duct leading from the lacrimal sac into the skin).
In the case of an abscess or cellulitis, topical and systemic antibiotic treatment is necessary. This clears up the infection.
Once this is achieved, lacrimal duct surgery is necessary. The goal of this surgery is to
- eliminate the excess tearing associated with the dysfunction of the tear duct and
- prevent recurrent infection.
All other cases of tear duct dysfunction also require tear duct surgery.
The surgical method depends on the exact diagnosis.
Procedure for Lacrimal Duct Surgery
All lacrimal duct surgeries are performed under general anesthesia. A lacrimal duct surgery can be performed either externally using the Toti procedure or minimally invasively via endoscopy.
A Toti procedure is necessary in cases of a long-segment narrowing of the tear duct between the lacrimal sac and the nose. This procedure is also called dacryocystorhinostomy (DCR). In this type of surgery, the dysfunction of the tear duct is surgically bypassed by creating a new pathway to the nose through which tear fluid is drained.
This tear duct surgery is
- performed via a skin incision (with a success rate of 90 to 95 percent) or
- a laser procedure without an incision (with a success rate of 75 percent)
.
For an endoscopic DCR, the surgeon must be proficient in nasal endoscopy. Sometimes it is necessary to correct abnormalities of the nasal septum or the turbinates. In these cases, this is the only way to gain access.
After the procedure, a thin, soft silicone tube is placed for three months. The tube ensures that the surgical bypass remains open and functional during the postoperative healing phase.
If the tear ducts are narrowed but not completely blocked, this is referred to as relative lacrimal duct stenosis. In such cases, the tear ducts can be probed and dilated using balloon dilation. The tear ducts are thus mechanically widened again. After the procedure, a silicone tube remains in place for three months to maintain the tear duct opening.
The tubes keep the enlarged lacrimal punctum open during the healing phase. This increases the likelihood that this structure will remain permanently enlarged and functional.
Lacrimal Duct Surgery in Children
In children with a tear duct dysfunction, the cause is often an incompletely developed nasolacrimal duct. Up to 7 percent of children are affected by this problem. In some children, the tear duct opens spontaneously during the first year of life.
If this does not happen and the symptoms persist, a brief tear duct surgery is necessary. For this procedure, a fine metal probe is inserted through
- the key parts of the tear duct (lacrimal puncta, canaliculus, lacrimal sac) and
- the junction of the nasolacrimal duct with the nose (known as Hasner’s valve)
.
In severe or recurrent cases, or in children whose treatment has been delayed, probing is performed in conjunction with silicone intubation. The treatment of lacrimal duct stenosis via probing or silicone intubation has an extremely high success rate.
These lacrimal duct surgeries are also performed under general anesthesia.
After lacrimal duct surgery
Pain after lacrimal duct surgery is usually minimal, and no bandage is required. Patients apply an antibiotic ointment before bedtime for 7 to 10 days.
If an incision was made, whether the sutures need to be removed depends on the type of suture material used. If self-absorbing sutures were used, this is not necessary.
The silicone tube remains in place for about 3 months. In most cases, it takes only 30 seconds to remove this tube on an outpatient basis while the patient is seated in the examination room.
Risks and Complications of Lacrimal Duct Surgery
Bleeding and infections, both potential risks of lacrimal duct surgery, are very rare. Minor bruising and swelling at the surgical site are to be expected for one to two weeks.
Occasionally, scar tissue may form later on, which could potentially block the newly created tear duct. In this case, repeat surgical intervention is recommended.
Most patients experience reduced tear production after the surgery. Pain, if any, is very mild after the procedure.
Additional Information on Lacrimal System Surgery
Lacrimal surgery is a subspecialty of ophthalmology. It focuses on disorders of the eyelids and the tear duct.
In the 1970s and 1980s, most disorders of the eyelids and lacrimal gland fell within the scope of general ophthalmologists. Today, the situation is somewhat different. Disorders of the eyelids and lacrimal gland are very common. Minor disorders account for a significant portion of the workload in general ophthalmology.
Sometimes, disorders of the eyelids and lacrimal glands can be treated without surgery. If these measures prove ineffective, patients are increasingly referred to specialists in lacrimal duct surgery.
Lacrimal system surgery remains part of the training curriculum for board-certified ophthalmologists. General ophthalmologists typically perform less complex surgeries, such as corrections for entropion and ectropion.
Ophthalmologists specializing in lacrimal duct surgery have often completed additional advanced training. Some work exclusively in this subspecialty.
Surgical Repertoire of the Lacrimal System Surgeon
The surgical repertoire of the lacrimal duct surgeon includes
- correction of eyelid malpositions (e.g., entropion, ectropion, ptosis, eyelid retraction due to thyroid dysfunction)
- surgery for ingrown eyelashes
- removal of tumors on the eyelids and surrounding tissue
- reconstruction of this tissue following tumor removal
Lacrimal surgeons are also consulted for
- excessive tearing caused by an eyelid malposition or
- a malfunction of the tear duct
.
Interdisciplinary Treatment Approaches
Some lacrimal surgeons also perform aesthetic or cosmetic procedures. They work on the eyelids and the periorbital tissue—that is, the tissue surrounding the eye. Possible procedures include
- visually rejuvenating the periocular tissue
- a change in the shape of the eyebrows
- correction of minor eyelid irregularities
These surgical procedures do not normally fall within the scope of treatment for an ENT specialist. Many of the techniques used in aesthetic surgery are similar to those used in lacrimal surgery.
Lacrimal surgeons often work closely with experts in related disciplines, such as
- dermatology,
- oncology,
- ENT, and
- plastic surgery.
However, lacrimal duct surgery is strictly the domain of the oculoplastic surgeon—that is, the ophthalmologist. He or she is and remains the primary point of contact for the treatment of a watery eye.
Conclusion
The conclusion is that lacrimal duct surgery, particularly DCR, is an established procedure in ophthalmology that is frequently performed in collaboration with ENT specialists. In cases of lacrimal duct obstruction or blockage, the Toti procedure creates an artificial connection to restore tear drainage. This procedure utilizes modern endoscopic techniques, in which an endoscope is inserted through the nose. This minimally invasive procedure allows for gentle treatment without an external incision.
During the surgery, the nasal mucosa is carefully incised to remove narrowings and create a permanent opening between the lacrimal sac and the nasal cavity. The lacrimal duct surgery is performed through the nose, during which the mucous membrane is sutured and a small tube may be inserted to keep the tear ducts open. In some cases, lacrimal duct intubation is also performed, during which a fine tube is inserted. In rare cases, this tube may need to be knotted or readjusted.
After the procedure, blurred vision may occur temporarily, particularly in the area of the inner corner of the eye or on the eyelid. Follow-up care with eye drops and regular flushing of the tear duct are important for the healing process. The ophthalmologist examines the area around the eyeball and the conjunctival sac to detect complications early on.
The overall success rate is high, with complete stabilization often occurring within 6–12 months. The surgery can provide early relief, particularly for congenital problems in children, such as those caused by a membrane or narrowed tear ducts. Surgical intervention is also necessary for rare causes, such as a tumor.
Overall, lacrimal duct surgery is an effective surgical method for treating disorders of the lacrimal ducts. Modern techniques, such as endoscopic procedures, significantly improve outcomes. Supportive measures, such as nasal packing, help stabilize the healing process and ensure long-term success.
FAQ
What is lacrimal duct surgery?
Lacrimal duct surgery is a surgical procedure to treat a blockage of the tear drainage ducts. The goal is to restore the flow of tears.
When is surgery necessary?
Surgery is necessary in cases of lacrimal duct stenosis or recurrent inflammation. Surgery is also recommended in cases of permanent blockage of the tear ducts.
How is the surgery performed?
In a dacryocystorhinostomy, an opening is created between the lacrimal sac and the nasal cavity. This can be performed endoscopically or using traditional surgical techniques.
What are the risks?
Possible risks include bleeding, postoperative bleeding, or infection. Careful postoperative care with eye drops is important.
What is the recovery like?
Swelling may occur after the surgery. A silicone tube keeps the tear duct open until healing is complete.

About the medical author
Prof. Dr. Dr. Ludwig Heindl
Medical Editor · Cologne

