
Positional vertigo is one of the most common causes of sudden dizziness. Benign positional vertigo is particularly common among older adults between the ages of 40 and 70. It is typically characterized by brief episodes of dizziness triggered by certain head movements or when lying down.
Benign paroxysmal positional vertigo is caused by the detachment of small otoliths in the inner ear. These tiny crystals enter the semicircular canals of the inner ear, where they irritate the vestibular system. This results in rotational vertigo, nystagmus, nausea, and sometimes vomiting.
Treatment usually involves special repositioning maneuvers designed to remove the crystals from the semicircular canals. Benign paroxysmal positional vertigo is the most common benign form of vertigo and is easily treatable in most cases.
Definition: What is positional vertigo?
People with positional vertigo experience recurring episodes of dizziness. These episodes occur whenever the person changes position—for example, when lying down, turning their head, or tilting their head up or down.
Positional vertigo is triggered only by rapid changes in position. Patients do not experience vertigo while sitting, lying down, or walking.
A particularly characteristic feature is that the dizziness occurs with a short delay after the movement. The dizzy spell lasts an average of 30 seconds to a maximum of 2 minutes.
It is a harmless condition, but one that can significantly impair daily life and quality of life. This makes it all the more important for those affected to learn to live with the symptoms. Acute episodes of dizziness can be significantly alleviated through specific maneuvers.
Typical Symptoms of Positional Vertigo
In most cases, it manifests as episodic rotational vertigo that can last from a few seconds up to a maximum of two minutes.
Like other forms of dizziness, positional vertigo is often accompanied by symptoms such as
- nausea and vomiting,
- sleep disturbances caused by movements in bed
. Older patients, in particular, also face an increased risk of falling.
Untreated positional vertigo can also lead to avoidance behavior. This, in turn, has a negative effect on posture. Last but not least, untreated patients are more likely to experience depressive moods.
What causes positional vertigo?
The inner ear contains small crystals—known as otoliths (ear stones)—that amplify the effects of gravity on the sensory cells. Under certain circumstances, they can detach from their original location and migrate into the fluid-filled semicircular canals.
When the head moves, the following happens: The otoliths move along with it and send signals to the brain. However, the brain cannot reconcile this incoming information with that from other organs—such as the eyes. This leads to feelings of dizziness and balance disorders.
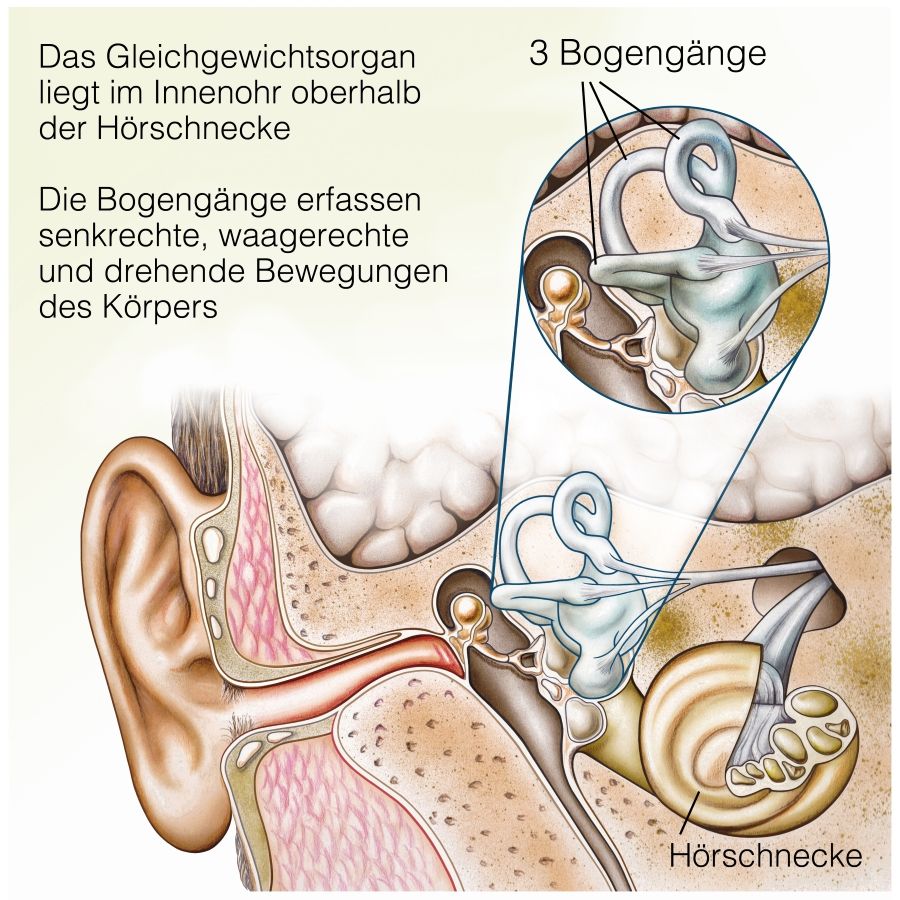
The detachment of the otoliths is a completely natural aging process. Positional vertigo therefore most commonly occurs in older adults between the ages of 60 and 80. Women are affected more frequently than men.
Furthermore, the following factors contribute to the development of benign paroxysmal positional vertigo:
- Traumatic brain injury/head injuries
- Inflammation of the inner ear
- Inflammation of the vestibular system
- Surgery on the cerebellum
- Migraine
- Meniere's disease
Examination & Diagnosis: What Does the Doctor Do?
If you experience recurring episodes of dizziness, it is advisable to see an ear, nose, and throat (ENT) specialist. Your primary care physician can also be your first point of contact. If necessary, they will refer you to an ENT specialist or a neurologist.
The examination begins with a detailed discussion between the doctor and the patient, known as the medical history. This discussion alone can provide the doctor with important clues about the cause of the dizziness.
The doctor then performs a hearing test and also examines the balance and hearing systems. This allows them to rule out certain conditions—such as sudden hearing loss.
If he suspects positional vertigo, he can confirm this, for example, using the Dix-Hallpike maneuver. He asks the patient to sit upright on the examination table, turn their head 45 degrees to the side, and then lie down.
In cases of benign paroxysmal positional vertigo, the patient will then experience a vertigo attack. This is often accompanied by involuntary, rapid eye movements (nystagmus). The vertigo subsides within a maximum of two minutes.
How is positional vertigo treated?
Medication or surgery are not options for treating benign paroxysmal positional vertigo. Instead, the patient learns techniques to help prevent vertigo or effectively relieve acute vertigo attacks.
The doctor may also instruct the patient to perform so-called repositioning maneuvers. Two maneuvers have been developed for this purpose: the Epley maneuver and the Brandt-Daroff maneuver. These maneuvers help move the crystals from the semicircular canals back into the correct organ (the utricle).
There are a few guidelines to follow when performing these maneuvers. Therefore, patients should receive thorough instruction in these exercises from their ENT doctor or a physical therapist. Special positioning training sessions are available for this purpose.
These maneuvers are very easy for laypeople to perform, and in approximately 80% of cases, patients are completely symptom-free after the first treatment. With positional vertigo, the goal is not to get used to the symptoms, but rather to eliminate the underlying cause through these exercises.
Course and Prognosis
The prognosis for positional vertigo is good, provided the patient is willing to undergo treatment. The patient must consistently perform the exercises prescribed by the doctor. Benign paroxysmal positional vertigo can thus resolve completely.
In many cases, however, it recurs in episodes. The patient can then effectively alleviate or shorten the vertigo attacks using the recovery maneuvers they have learned in advance.
Conclusion
Although positional vertigo is generally harmless, those affected should not simply ignore the symptoms. They should always consult a specialist to rule out other conditions.
FAQ
What is positional vertigo?
Positional vertigo is a benign form of vertigo affecting the vestibular system. Benign paroxysmal positional vertigo (BPPV), also known as BPLS or vertigo, is caused by the detachment of small stones or crystal-like structures in the inner ear. These structures enter the semicircular canals and trigger episodic bouts of vertigo.
What are the symptoms of positional vertigo?
Typical symptoms of positional vertigo include sudden onset of rotational vertigo, a sensation of dizziness, nystagmus, as well as nausea and vomiting. These symptoms often occur when turning over in bed, sitting up, or moving the head. Eye movements or nystagmus may also be observed.
What causes benign paroxysmal positional vertigo?
Benign paroxysmal positional vertigo is caused by otoliths that detach from the sensory cells. These crystals move within the semicircular canals of the inner ear and irritate the vestibular system. Causes of positional vertigo can include age, bed rest, or certain head movements.
How is positional vertigo treated?
Treatment usually involves special repositioning maneuvers or liberation maneuvers. During these maneuvers, the head is often moved at a 45-degree angle to guide the otoliths back out of the semicircular canals. In addition, repositioning exercises or, in rare cases, medication or anti-vertigo drugs may be used.
When should you see a doctor for positional vertigo?
If episodes of dizziness, nausea, or vertigo persist for an extended period, or if other forms of dizziness—such as Meniere’s disease—are suspected, a medical diagnosis and treatment should be sought. A medical evaluation is particularly advisable in cases of frequent symptoms or uncertainty regarding the nature of the symptoms.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →










