
The eye condition known as keratoconus refers to the thinning and cone-shaped distortion of the cornea. The condition usually begins in one eye. However, both eyes are typically affected. Keratoconus can progress either in episodes or gradually. Across Germany, approximately one in every 2,000 people is affected—with men being affected twice as often as women.
Here you will find all the important information as well as a selection of keratoconus specialists and centers.
Keratoconus: Definition and Prevalence
The condition usually affects the central part of the cornea. It causes the cornea to become cone-shaped and thin.
Keratoconus usually affects both eyes. However, it is extremely rare for it to occur simultaneously and with comparable severity in both eyes. If the condition is detected early, it can be managed with timely treatment. The goal is then to prevent the corneal deformation and thinning from progressing too rapidly.

Keratoconus is defined as a cone-shaped deformation of the cornea
Those affected usually suffer from nearsightedness, which becomes increasingly severe over time as the distortion worsens. However, the resulting nearsightedness and irregular astigmatism usually cannot be fully corrected and can only be managed with visual aids (such as glasses). The reason for this is the cone-shaped protrusion of the cornea.
Keratoconus is relatively rare. In Germany alone, “only” about 0.5 percent of the population is affected. However, the percentages vary depending on the region and the different examination methods used.
In addition, twice as many men are affected by the condition as women. Keratoconus usually develops between the ages of 20 and 30. In rare cases, however, it can also occur as early as childhood or later, for example between the ages of 40 and 50.
Causes of the Condition
Despite numerous studies, the exact causes of keratoconus—or the factors that trigger or contribute to it—remain unknown. The condition often occurs in association with hereditary disorders such as Down syndrome.
It is also more common in people who suffer from
- allergies,
- asthma,
- soft-tissue rheumatism,
- atopic dermatitis (an inflammatory skin condition characterized by eczema), and
- dry eyes
.
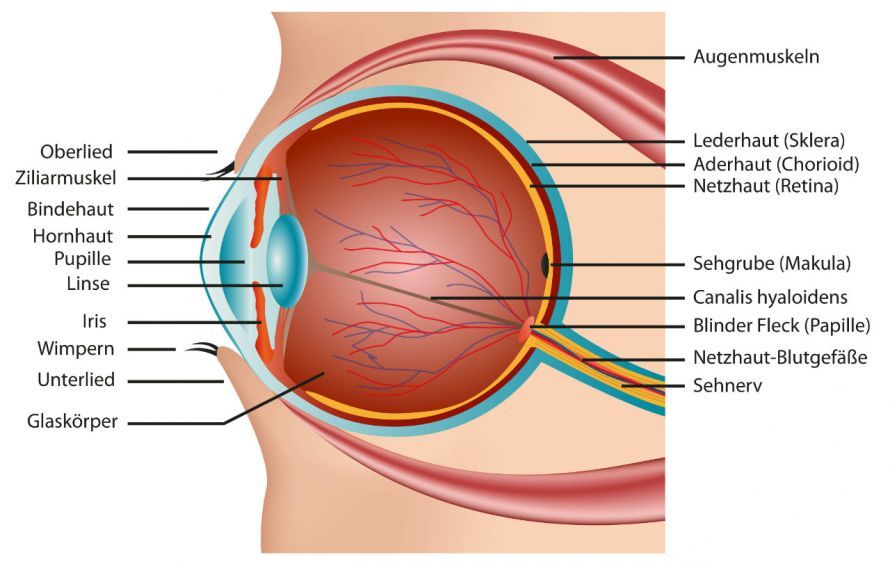
According to various theories, a metabolic disorder in those affected is the trigger. However, a hereditary disease could also be a possibility.
Furthermore, various long-term studies on keratoconus have observed a deviation in the chemical composition of the cornea. Individual observations, however, have shown that even the natural curvature of the sclera (the white part of the eye) in an affected eye often deviated only minimally from the norm.
An infection or a weakening of the collagen present in the cornea could also contribute to the development of keratoconus. However, these hypotheses have not yet been substantiated by further studies.
In rare cases, the progression of the disease can lead to tears in the posterior cornea. When this happens, aqueous humor—the fluid from the anterior chamber of the eye—can penetrate the cornea. The result is acute keratoconus, which can be painful and often requires immediate treatment (such as surgery). Otherwise, vision deteriorates rapidly and drastically (blurred vision).
Acute keratoconus is the only form of the disease in which the eye can cause pain and noticeable discomfort. The mere deformation and thinning of the cornea manifests only through the loss of vision.
Symptoms of Keratoconus
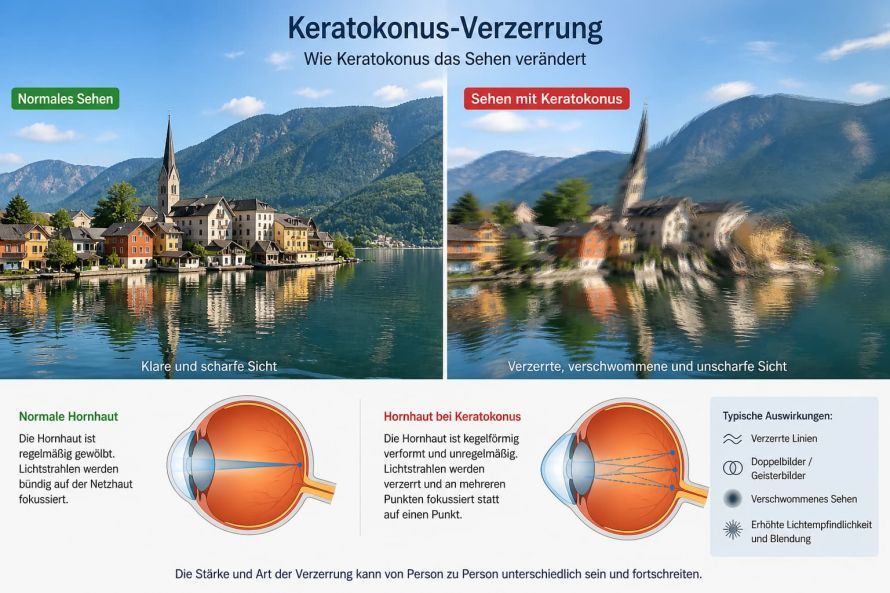
In the early stages of the disease, symptoms appear only gradually, and the patient’s vision deteriorates slowly. The patient sees double or perceives shadows on objects. The increasing irregularity of the corneal surface leads to distorted vision. Star-shaped rays appear to emanate from light sources, and streaks appear around letters.
Under sufficient lighting, semicircular or circular greenish-brown to yellowish-brown lines appear, which doctors refer to as
- keratoconus lines,
- Fleischer’s rings, or
- Kayser-Fleischer corneal ring
.
Other symptoms include:
- impaired night and twilight vision
- persistent redness of the eyes
- increased sensitivity to light
- severely strained, exhausted facial muscles
- Contact lenses frequently slip out of place or fall out
Diagnosis of keratoconus
Keratoconus is usually diagnosed during a routine eye exam or as soon as nearsightedness becomes noticeable. Therefore, the first signs of keratoconus are frequent changes in eyeglass prescriptions with drastic changes in the axis. In the early stages, the condition is often in a so-called “forme fruste” phase, in which changes to the cornea are detectable only through specialized diagnostic tests. Visual acuity also fluctuates significantly.
Added to this is the increasing curvature of the cornea, which initially often affects only one eye. Since keratoconus is a relatively rare condition, the early signs are usually not recognized. Many ophthalmologists are familiar with keratoconus only in theory. A referral to an ophthalmologist specializing in corneal diseases may therefore be advisable. If in doubt, patients who suspect they may have keratoconus should consult another ophthalmologist.
Keratoconus can be diagnosed using various methods. The most well-known are
- a close examination of the cornea with a skiascope (keratoconus is characterized by the typical “fish-mouth effect”),
- a slit lamp (to determine the thickness and number of corneal layers),
- a keratograph (to assess the surface structure of the cornea), and
- optical coherence tomography (OCT).
The latter produces a cross-sectional image of the anterior segment of the eye. This includes, among other things, the corneal thickness and the detailed topography of the surface. This allows the typical deformation and thinning to be identified.
Progression and Treatment of Keratoconus
Today, doctors can treat keratoconus in two different ways. The goal is to correct the refractive error caused by keratoconus.
Vision Aids to Compensate for Refractive Errors
In the early stages of keratoconus, symptoms are still mild. At this stage, the deformation and thinning of the cornea can still be corrected with glasses. In advanced keratoconus, however, the changes to the cornea are usually too severe.
In such cases, the refractive error can—and usually must—be corrected with rigid gas-permeable contact lenses or with special lenses (known as keratoconus lenses).
About 80 percent of patients with keratoconus are able to manage long-term with rigid gas-permeable contact lenses. In some cases, however, these must be combined with an additional visual aid (such as glasses). Only then can adequate correction of the refractive error be achieved.

Corneal Cross-Linking
On the other hand, timely treatment is intended to prevent the disease from progressing further. In the best-case scenario, further deformation and thinning of the cornea are largely halted.
This is possible, for example, with a cross-linking treatment (also known as cross-linking or collagen cross-linking). Cross-linking prevents the progression of keratoconus but is recommended by experts only in stages I and II. Cross-linking stiffens the soft corneal tissue. During the procedure, riboflavin (vitamin B2) is applied to the cornea and then exposed to UVA light to cross-link the collagen fibers.
To date, however, cross-linking is the only treatment method that can halt the progression of keratoconus for several years.
Various studies suggest that keratoconus could be permanently halted with timely corneal cross-linking. However, there is currently a lack of supporting long-term study data.
Circular Keratotomy
Circular keratotomy (CKT) is another procedure used in an attempt to largely halt the progression of keratoconus. In this procedure, an incision approximately 7 mm wide is made around the optical axis of the cornea. The incision is then closed with a double-layered suture.
This tightens the cornea and corrects the cone. However, for this procedure to be performed, the cornea must be at least 400 µm thick and stable enough in the area of the incision. Furthermore, CKT is also only suitable for stages I and II of keratoconus.
To date, the actual effectiveness of CKT has not been proven.
Ring Segments
Another option is the implantation of ring segments (also known as intrastromal corneal ring segments). These small plastic rings are inserted into the cornea and can partially flatten the cone-shaped deformation, which may improve visual acuity.
Corneal Transplant
If keratoconus is far advanced and corrective lenses can no longer adequately correct the refractive error, the cornea should generally be replaced with a graft (keratoplasty). The transplant is performed at an eye clinic specializing in transplants. H
In rare cases, the patient’s cornea is stabilized using various methods; more often, however, it is replaced with a donor cornea.
Often, the cornea is simply excised. Only a minimal rim remains; the excised piece of cornea is replaced with healthy donor tissue and sutured in place with a fine double suture.
The costs are generally covered by health insurance. This coverage is contingent on the patient’s vision being impaired to such an extent that it seriously affects their quality of life.
Daily Life and Prognosis
Keratoconus can have a significant impact on daily life, whether treated or left untreated. In patients with keratoconus, visual acuity in one eye often fluctuates greatly. This can only be partially counteracted using various visual aids.
In any case, however, keratoconus affects the patient’s ability to concentrate due to constantly fluctuating visual acuity. This can result in difficulties with vision, thinking, and concentration, as well as headaches and migraine-like pain attacks.
Another problem is the comfort of the lenses, which do not necessarily sit comfortably in the eye and can lead to
- increased tearing,
- irritation, and
- redness of the eyes
. Furthermore, in many cases, keratoconus can significantly impair a person’s ability to drive a motor vehicle. However, the treating ophthalmologist must determine whether this applies in each individual case.
Lack of Prognosis
Another burden for those affected by this condition is the lack of predictions regarding the course of the disease. Neither the exact causes of keratoconus nor the influence of external factors are yet fully understood.
Therefore, it is difficult to say
- how quickly and how drastically keratoconus will progress,
- which treatment is the right one, and
- how the person affected should manage the condition.
Often, seemingly simple questions—such as whether it’s okay to play sports or whether rubbing the eye is harmful—cannot be answered.
For some patients, for example, a corneal transplant is necessary after just a few weeks or months. Others, however, manage with glasses or appropriate keratoconus contact lenses for decades or for the rest of their lives.
The only prognosis that applies to most patients is that keratoconus usually comes to a natural halt—not one forced by treatment—between the ages of 40 and 50.
Lack of Financial Assistance
Contact lenses and frequently replaced eyeglasses, however, represent a daily financial burden. Both types of vision aids must be replaced more often than average and adjusted to new prescription values. Often, multiple pairs of contact lenses or eyeglasses are even necessary to compensate for constant fluctuations in visual acuity.
The costs for the necessary vision aids—especially for suitable contact lenses—are quite high. They are covered only partially, if at all, by public health insurance plans. Most supplemental insurance plans, however, no longer cover keratoconus if it was diagnosed before the policy began.
Those affected are therefore often left entirely on their own to bear the immense costs of treatment.
Prevention of the Disease
According to all current studies and findings, it is not currently possible to prevent this disease.
Even though targeted prevention is not possible, treating keratoconus also involves avoiding anything that could put additional strain on the eye and the cornea. A very common and typical example is rubbing the eyes. This is often linked to prolonged computer use and the resulting dryness of the eyes. For this reason, doctors advise those affected, in particular, to avoid working on a computer.
Likewise, spending time in dusty and smoky rooms, as well as in rooms with air conditioning, should be avoided.
Anyone affected by keratoconus should definitely drink plenty of fluids and spend a lot of time outdoors. Some experts, however, are skeptical about the constant wearing of contact lenses. Many studies claim—though this has not yet been proven—that this could also put long-term strain on the cornea. However, opinions on this matter remain divided.
FAQ
What is keratoconus?
A progressive corneal disease in which the cornea thins and bulges outward in a cone-shaped manner, progressively impairing vision.
What are the symptoms?
Blurred vision, increased sensitivity to light, and frequently changing prescription strengths are typical early signs.
What treatments are available?
In the early stages, cross-linking halts the progression of the disease. Rigid gas-permeable contact lenses correct the refractive error; in advanced cases, a corneal transplant is necessary.
4. Can it be prevented? Specific prevention is not possible. However, rubbing the eyes should be avoided, as it exerts pressure on the cornea and can contribute to the development of the disease.
Share this article
