
The retina is essential for vision. Diseases affecting this part of the eye can significantly impair vision and, in the worst cases, lead to blindness. Among the most important retinal diseases are circulatory disorders, diabetic retinopathy, macular degeneration, retinitis pigmentosa, and retinal detachment.
What is the retina?
The inner layer of the eye (retina, from the Latin rete, “net”) surrounds the eyeball along with the middle layer (iris, ciliary body, and choroid) and the outer layer (sclera and cornea).
 The retina is the transparent, light-sensitive tissue at the back of the eye @ Kristof /AdobeStock
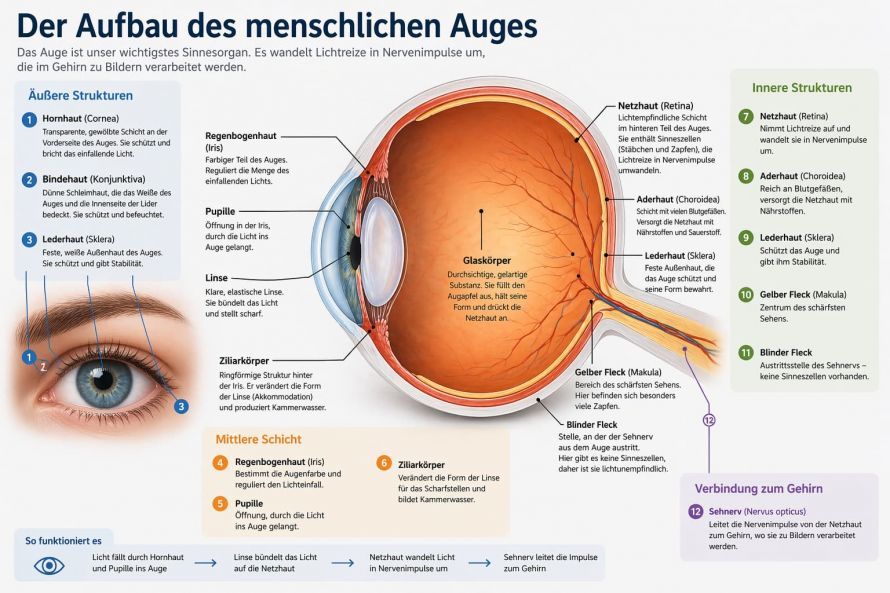
After light enters the eye through the pupil, it passes through the transparent vitreous humor and strikes the retina. There, the incoming light is captured by photoreceptors. These sensory cells transmit the stimuli via intermediate cells until they reach the brain as nerve impulses. A single nerve cell does not function in isolation but interacts with many other cells. At the center of the macula is the area of sharpest vision, also known as the fovea. This area of sharpest vision is crucial for reading, facial recognition, and discerning fine contrasts. As a result, this area is particularly sensitive to damage.
Structure and Function of the Retina
The retina lines the inside of the eyeball. It lies directly on top of the choroid, which is responsible for supplying the retina with nutrients. Light entering the retina stimulates the sensory cells, which transmit these signals to the relevant regions of the brain.
The retina contains various types of nerve cells, which can be divided into three categories:
- Photoreceptors convert incoming light into nerve impulses
- Interneurons process these impulses within the retina
- Ganglion cells transmit the impulses outside the retina
 Photoreceptor cells
There are two types of photoreceptor cells:
- Rods
- The cones
The eye has 120 million rods, which are responsible for distinguishing between light and dark. About 6 million cones enable color vision.
There are three types of cones that respond to different wavelengths of light. These three wavelength ranges of light appear to us as red, green, and blue.
The rods are located around the fovea to ensure optimal color perception.
The light-dark-sensitive cones are clustered in the peripheral area. For this reason, it is easier to distinguish between light and dark out of the corner of the eye, but colors are not perceived as well. Color vision also diminishes in low-light conditions. The photoreceptor cells regenerate regularly.
- Yellow Spot (Macula)
Located in the rear portion of the retina, opposite the pupil, is the “yellow spot” (macula), which is about 3 mm in size. The pigments embedded here can filter high-energy UV light and protect the retina from harmful effects.
At the center of the macula lies the fovea (fovea centralis). This is the area of the eye that enables the sharpest vision (e.g., for reading). The rest of the retina, on the other hand, is responsible for the peripheral visual field—that is, for “peripheral vision.”
- Optic disc
The optic disc is slightly offset from the macula. It is the point where the nerve fibers of the retina converge to form the optic nerve. Together with the blood vessels, they exit the eyeball through all layers of the eye’s outer membrane. There are no photoreceptors at this point to capture incoming light. Therefore, it is literally a “blind spot.”
Causes and Risk Factors
Retinal diseases can be congenital, age-related, metabolic, vascular, or caused by traction forces within the eye.
Some forms develop gradually, while others occur suddenly. Common causes include circulatory disorders, age-related changes in the macula, or complications resulting from poorly controlled metabolic conditions.
Risk factors include, in particular, diabetes, high blood pressure, atherosclerosis, inflammatory processes, genetic predisposition, and advancing age. Changes in the vitreous humor also play a role. Vitreous detachment is not uncommon in older adults and can exert traction on the retina. In severe cases, this traction can cause the retina to detach or lead to retinal tears. Similarly, blood vessels—such as a diseased artery, narrowed veins, or a blockage in the supplying vessels—can impair blood flow to the retina.
Types of Retinal Diseases
Diabetic Retinopathy as a Complication of Diabetes Mellitus
A particularly well-known retinal disease is diabetic retinopathy. It develops as a result of elevated blood sugar levels over an extended period. This damages the small blood vessels in the retina, leading to leaks, bleeding, and reduced blood flow. In the early stages of retinopathy, these changes may occur without noticeable symptoms. Later on, those affected may notice spots, distortions, or blurred vision.
Diabetic retinopathy is a serious complication for many people with diabetes. People with diabetes should therefore undergo regular checkups. In advanced stages, macular edema may also develop—that is, fluid accumulation in the macula. This primarily affects central visual acuity. Without appropriate treatment, retinopathy can progress and, in extreme cases, lead to blindness.
Retinitis Pigmentosa
Retinal Detachment
Retinal detachment is an acute and serious condition. In this condition, the retina separates from the underlying choroid. As a result, the tissue is no longer adequately supplied with nutrients. Photoreceptors are damaged and may die. Warning signs include flashes of light, floaters, shadows, or a curtain-like obstruction in the field of vision. Some patients also report sudden distorted or blurred vision.
A vitreous detachment can cause a retinal tear, which can lead to retinal detachment. Injuries, traction forces, complications from diabetes, or pre-existing damage to the retina can also play a role. Prompt action is crucial in these cases. Anyone who notices such warning signs should see an ophthalmologist immediately. This is because an untreated retinal detachment can lead to permanent blindness.
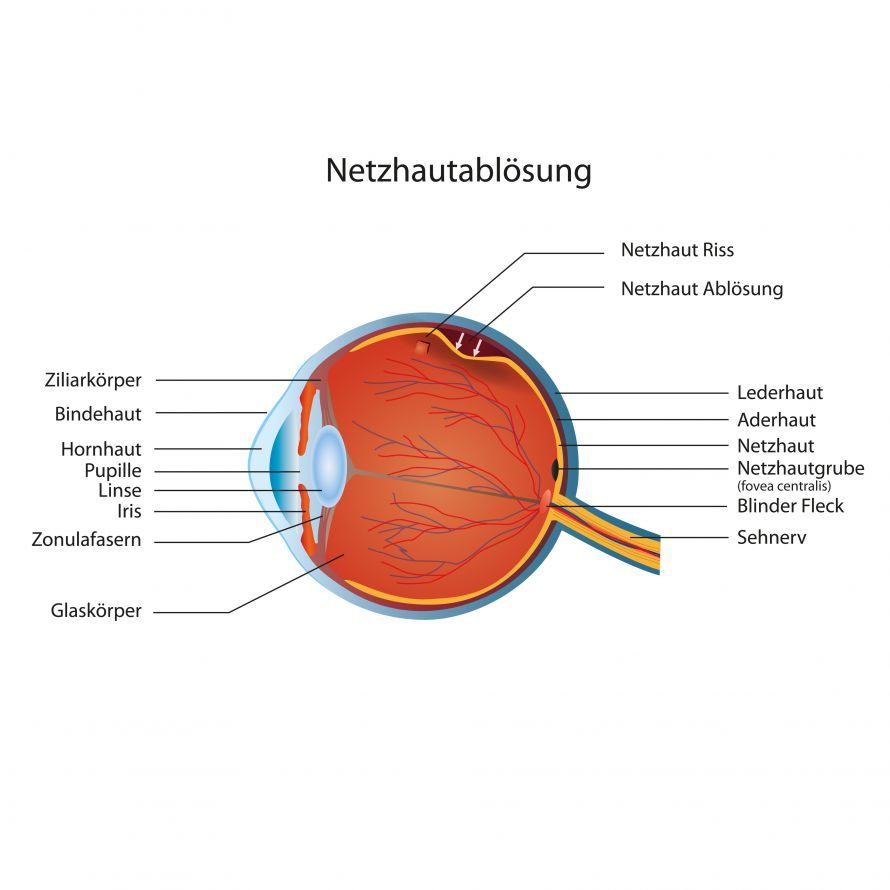 In retinal detachment, the retina no longer receives enough oxygen and nutrients from the choroid @ bilderzwerg /AdobeStock
Macular Degeneration and Other Changes
Another common retinal condition is age-related macular degeneration. AMD affects the macula—the very area responsible for sharp vision. It is the most common cause of central vision loss, particularly in older adults. With macular degeneration, the brain processes central visual information less effectively, while the peripheral visual field often remains intact at first.
In addition to AMD, there are other conditions such as a hole in the macula, inflammatory processes, or other retinal changes. These, too, can significantly impair central vision and should be evaluated by an ophthalmologist.
Diagnosis of a Retinal Disease by an Ophthalmologist
Diagnosis begins with a detailed medical history. The doctor asks about symptoms, previous medical conditions, and risk factors. Precisely because many changes are initially painless, an examination of the fundus is particularly important. Ophthalmologists assess whether there is bleeding, fluid accumulation, vascular changes, or retinal tears.
Basic diagnostic procedures include a visual acuity test, examination of the pupil, slit-lamp examination, and assessment of the interior of the eye following pupil dilation. This allows for the detection of many types of retinal damage, early-stage retinal damage, and changes in the retina. Modern imaging techniques are also used, such as optical coherence tomography to visualize the macula, vascular examinations, and photographic documentation. This allows for a precise assessment of the disease’s progression, activity, and need for treatment.
Treatment of Symptoms
Treatment depends on the cause, extent, and stage of the condition. For vascular diseases, the initial focus is on stabilizing the underlying conditions. Blood pressure, blood sugar, and vascular risk factors should be consistently managed. In diabetic retinopathy in particular, success depends largely on how well metabolic control is maintained.
Depending on the findings, various treatment options may be considered. These include intravitreal injections, laser therapy, or surgical procedures. In cases of retinal detachment, rapid surgery is usually necessary to reattach the retina. For macular edema or wet AMD, intravitreal injections can help reduce fluid buildup and stabilize visual function.
Individualized treatment is always important, as not every change requires the same intervention right away.
Course
The course and prognosis depend heavily on the specific cause. Some retinal diseases develop slowly and remain compensated for a long time, while others have an acute course. The timing of the diagnosis is often crucial, as it allows damage to be either reversed or at least limited.
In cases of circulatory disorders and diabetic retinopathy, the course of the disease can stabilize if the underlying condition is well controlled; genetic conditions such as retinitis pigmentosa, on the other hand, may continue to progress despite treatment.
In the case of retinal detachment, the sooner it is treated, the better the prognosis. If the central macula is also affected, the risk of permanent vision loss increases.
If left untreated, severe cases can lead to blindness. The same applies to macular degeneration: when detected early, the progression can be slowed in many cases. In patients, accompanying symptoms such as vascular changes, deposits, or areas of pallor can provide indications of progressive damage.
Specialists
The diagnosis and treatment of retinal diseases should be entrusted to experienced specialists. The first point of contact is usually an ophthalmologist, especially if shadows, flashes, distortions, or black spots suddenly appear.
For complex diagnoses, surgical procedures, or advanced conditions, a referral to a specialized eye clinic may be advisable. Specialized centers are particularly important in cases of complicated disease progression, suspected macular degeneration, retinopathy, genetic disorders, or following acute retinal changes.
Anyone looking for a specialist should look for experience in retinal diagnostics, modern imaging, and surgical expertise. Good specialists to consult are ophthalmologists who focus on the retina, retinal surgery, and macular diseases. Close and long-term care is especially crucial for patients with chronic conditions.
Frequently Asked Questions
What symptoms indicate retinal diseases?
Typical signs include shadows, floaters, distortions, sudden vision loss, or flashes of light. Such symptoms should always be evaluated by an ophthalmologist as soon as possible.
Is a retinal detachment an emergency?
Yes, a retinal detachment is an emergency because blood flow to the retina deteriorates rapidly. Without prompt treatment, permanent damage can occur.
Can diabetes damage the retina?
Yes, diabetic retinopathy in particular demonstrates that chronically elevated blood sugar levels can damage the small blood vessels of the retina. Regular checkups are therefore especially important.
What is the difference between macular degeneration and diabetic retinopathy?
Macular degeneration primarily affects the central retina in older adults, whereas diabetic retinopathy is a consequence of metabolic changes associated with diabetes. Both conditions can impair central vision, but they develop through different mechanisms.
When should you see an ophthalmologist?
If you experience sudden flashes of light, shadows, distortions, or a noticeable decline in vision, you should always see a specialist promptly. People with diabetes or vascular diseases should also have their eyes checked regularly.
Share this article


