
Idiopathic scoliosis is the most common form of scoliosis and refers to a three-dimensional curvature of the spine of unknown cause. Idiopathic scoliosis occurs particularly in children and adolescents during growth and can worsen significantly depending on the Cobb angle.
Clinical and radiological examinations of the spine are crucial for diagnosis, as the severity of the curvature, the rotation of the vertebral bodies, and any lateral deviation must be assessed. The goal of treatment is to prevent progression and to preserve the function of the spine in the long term.
What is scoliosis?
Idiopathic scoliosis is a form of scoliosis. Scoliosis is an abnormal curvature of the spine that is always accompanied by a twisting of the spine. The word “scoliosis” comes from Ancient Greek and means “curvature” in English.
In scoliosis, the spine deviates laterally from its natural longitudinal axis. In most cases, this lateral curvature of the spine consists of several opposing curves.
To maintain physical balance, the body attempts to counteract this. This inevitably leads to
- twisting,
- friction, and
- deformities
of individual vertebrae, since the muscles alone can no longer compensate for the misalignment.
The spinal deformity associated with scoliosis begins to develop as early as childhood or adolescence. Further curvatures occur particularly during periods of rapid growth, such as puberty.
As far as possible, the classification of the individual types of scoliosis is based on
- their cause,
- the time of their onset,
- the location and nature of the curvature,
- the respective degree of the curvature angle, and
- the extent of remaining flexibility (mobility) of the various curves.
When referring to the so-called curvature pattern, medical professionals classify
- C-shaped scoliosis,
- S-shaped scoliosis, and
- double-S scoliosis.
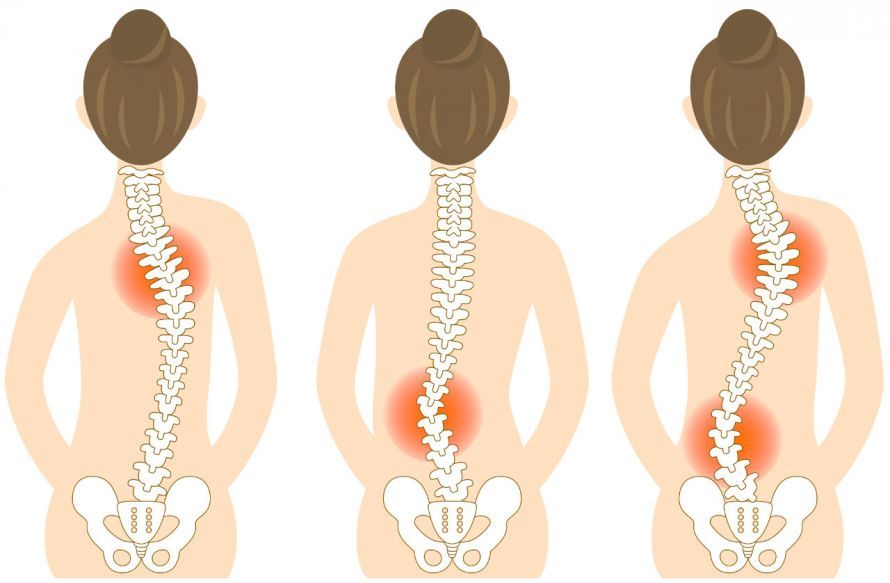
Illustration of various forms of scoliosis © sumaki | AdobeStock
The main causes of congenital scoliosis are malformed vertebral bodies and segments of the vertebral column. Neuromuscular disorders that impair signal transmission for muscle function can also trigger scoliosis. In addition, untreated leg length discrepancies are sometimes the cause of scoliosis. The latter can also influence the progression of the condition.
As part of the diagnostic process, physicians attempt to identify the cause of the individual case. Clinical and radiological examination methods are used for this purpose. If no cause for the scoliosis can be identified, the physician refers to it as idiopathic scoliosis. The term “idiopathy,” which, like “scoliosis,” originates from Ancient Greek, means “self-inflicted” in English. Idiopathic scoliosis is therefore a distinct medical condition with no known underlying cause.
The Three Forms of Idiopathic Scoliosis
Depending on when idiopathic scoliosis (IS) develops, medical professionals distinguish three forms:
- Infantile idiopathic scoliosis (IIS): Onset by age 3
- Juvenile idiopathic scoliosis (JIS): Onset between the ages of 4 and 10
- Adolescent idiopathic scoliosis (AIS): Onset at age 11 or older
The peak incidence of idiopathic scoliosis occurs between the ages of 10 and 12. Infantile and juvenile scoliosis are also grouped together under the term “early-onset scoliosis.”
Scoliosis diagnosed only in adulthood may be previously undetected but persistent idiopathic adolescent scoliosis. However, it could also be degenerative adult scoliosis (de novo scoliosis). This form of scoliosis is caused by degenerative changes in the spine or vertebral bodies.
What are the typical symptoms of idiopathic scoliosis?
Idiopathic scoliosis presents with the same symptoms as conventional scoliosis. These are recognizable at first glance:
- a crooked back
- pelvic asymmetry
- uneven shoulder heights
- protruding shoulder blade
- head held at an angle
- Asymmetrical waistline or nipple line
These symptoms do not necessarily occur simultaneously, nor do they all have to be present.
In the early stages, idiopathic scoliosis often causes no pain and goes unnoticed. Once the body has finished growing, the malformed spine leads to further deformities or degenerative changes over time. Patients may then complain of
- stiffness and pain in the upper and lower back, as well as
- restricted movement.
Patients find it increasingly difficult to maintain a straight posture. In advanced cases, prolonged standing and walking become difficult, and patients’ functionality is significantly impaired.
In cases of severe spinal curvature, the rib cage may become deformed or narrowed. This can lead to functional impairments of the heart and lungs. Furthermore, in severe scoliosis, the lower ribs and the iliac crest may come into painful contact with one another.
Idiopathic Scoliosis—Three-Dimensional Curvature of the Spine, Its Diagnosis, and Treatment
Examination and Diagnosis of Idiopathic Scoliosis
Idiopathic scoliosis does not necessarily cause symptoms if it is not very pronounced. The diagnosis is often made incidentally, i.e., during examinations conducted for other reasons.
If idiopathic scoliosis is suspected, the doctor examines the patient’s back while the patient is standing. The doctor also checks the legs for differences in length. Leg length discrepancies are assessed both while lying down and while standing.
Another important diagnostic tool is the Adams forward-bending test: The patient remains facing away from the doctor and bends forward while standing. Irregularities in the alignment of the spine and the ribs extending from it become more apparent during this test.
An X-ray examination of the spine in the frontal and lateral planes confirms the diagnosis.
Full-spine X-rays also allow for the assessment of the patient’s so-called skeletal maturity by depicting the iliac crests. The different types of curvature are analyzed as follows:
- Primary curvature: the most pronounced spinal deviation
- Secondary curvature: corrective deviation above and below the primary curvature
- Neutral vertebra: change in the direction of the curvature = inflection point of the curvature
The following are also assessed:
- the balance of the spine in both planes,
- the rotation of the spine in the frontal plane, and
- the shape of the spine in the lateral plane.
When evaluating the X-ray, the doctor uses the Cobb angle to measure the degree of spinal curvature. The Cobb angle ranges from 10° for mild deviations to 30°—and occasionally higher—for severe curvatures.
It is noteworthy that the higher the Cobb angle, the more it affects girls and women. Female patients are about seven times more likely to have a Cobb angle of 30°.
What treatments are available for idiopathic scoliosis?
Mild cases of idiopathic scoliosis with a Cobb angle below 10° do not yet require treatment. However, it is advisable to have a diagnosed case of scoliosis monitored regularly. Orthopedic surgeons—preferably specialists in spinal curvature—are the appropriate professionals to consult for scoliosis treatment.
For scoliosis of up to 20°, a medical checkup every 6 months is sufficient. X-rays may also be taken if necessary.
For scoliosis ranging from 20° to 30° and above, the doctor will continue to schedule regular checkups. The doctor may also recommend wearing a brace. The more consistently the brace is worn, the more effective it will be!
Surgical correction offers good prospects for success in cases of severe idiopathic scoliosis.
In this procedure, the spinal surgeon fuses the affected sections of the spine.
This means that the affected vertebrae are repositioned and then fused. As a result, the spine is straightened. The downside, however, is that the fused vertebrae are no longer mobile. Patients must therefore expect somewhat limited mobility. For this reason, the guiding principle is: Always as short as possible and only as long as necessary.
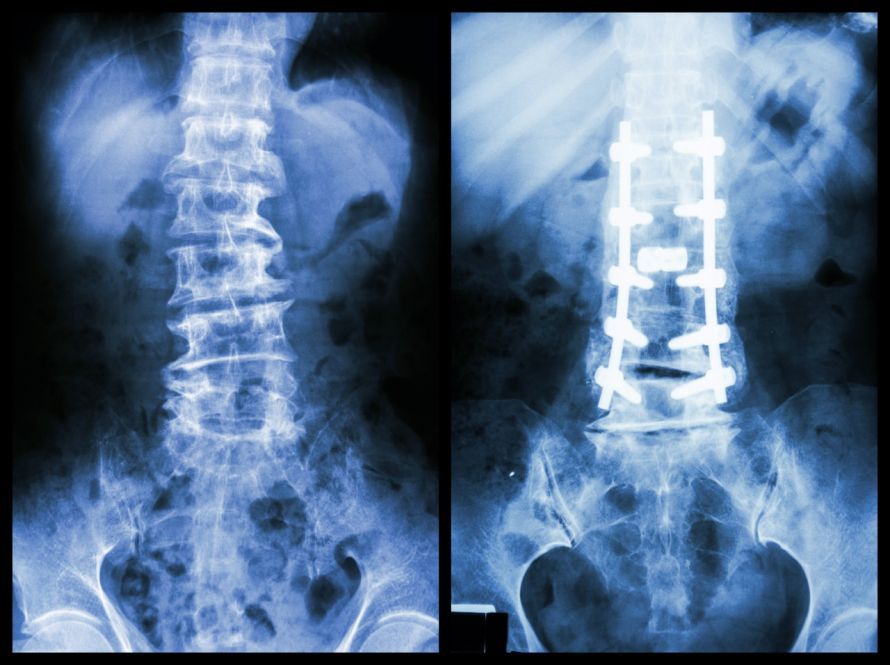
So-called dynamic scoliosis correction is used for children with severe scoliosis (40–60°). In this procedure, the surgeon implants so-called growth rods that can adapt to the child’s growth. The chosen surgeon should have a special focus on and experience in the field of scoliosis surgery. It is best to look for a specialist in scoliosis surgery. Severe idiopathic scoliosis can also take a psychological toll on many patients. Psychotherapy as a complementary treatment provides support and helps patients cope with the condition going forward.
Prognosis for Idiopathic Scoliosis
Excellent results can be achieved today with both conservative and surgical treatments. Functional ability, education, and professional life are rarely significantly impaired.
Building strong muscles is important for achieving good outcomes with scoliosis and following scoliosis treatment. Strong muscles are essential for an efficient musculoskeletal system. The following can help:
- physical therapy,
- sufficient exercise, and
- gyms,
to prevent adverse developments and symptoms as one ages.
Conclusion
Idiopathic scoliosis manifests as spinal curvatures of varying severity. Initially, it often causes no symptoms and is usually discovered incidentally. Later symptoms are characterized in particular by lower back pain, as well as pain when standing or walking for extended periods.
Modern medicine offers helpful treatment options for patients. Specialized therapies enable those affected by idiopathic scoliosis to maintain a rewarding quality of life, even in the long term.
Early detection of idiopathic scoliosis is crucial, as a spinal curvature of at least 10 degrees (10°) is considered to require treatment; diagnosis is typically made through X-ray examination of the entire spine in two planes. The severity of the scoliosis—characterized by lateral curvature of the spine, rotation of the vertebral bodies, and possible involvement of the pelvis and lumbar spine—significantly determines the prognosis and whether conservative treatment is sufficient or whether surgical intervention by a spinal surgeon is necessary.
Particularly in adolescent scoliosis, as well as in scoliosis in children and adolescents, remaining growth potential, the duration of orthotic wear, and consistent bracing therapy based on approaches such as the Katharina Schroth method play a central role in preventing the curvature from worsening. Scoliosis is defined as a three-dimensional axial deviation of the spine, the severity of which can range from less than 20° to over 40° or 50°, with the progression of scoliosis being influenced by individual factors and the course of a person’s life.
If scoliosis is diagnosed, regular checkups with an orthopedist are important, as signs of idiopathic scoliosis—such as a rib hump or lumbar bulge—may appear when bending forward, and early scoliosis treatment significantly improves quality of life in the long term.
FAQs on Idiopathic Scoliosis
What is idiopathic scoliosis?
Idiopathic scoliosis refers to a lateral, three-dimensional curvature of the spine for which no clear cause can be identified. It frequently occurs in childhood and adolescence and is diagnosed by process of elimination.
How is idiopathic scoliosis diagnosed?
The diagnosis is made clinically and radiologically using an X-ray of the entire spine in two planes. The key factor is the measurement of the Cobb angle; a curvature of at least 10 degrees is classified as scoliosis.
What treatment options are available?
Treatment for idiopathic scoliosis depends on the severity, remaining growth potential, and degree of curvature. Options include conservative therapies such as the Katharina Schroth method, bracing, or surgical intervention by a spinal surgeon.
When is a brace necessary?
Brace therapy is usually recommended for children and adolescents with a curvature between 20° and 40 degrees, provided they are still growing. The goal is to prevent the curvature from worsening.
When is surgery necessary?
Surgical treatment is generally considered for idiopathic scoliosis with a Cobb angle of more than 40 to 50 degrees, particularly in cases of progressive curvature or functional limitations of the spine.
Share this article
Sources
- https://www.aerzteblatt.de/archiv/die-idiopathische-skoliose-7f072395-663d-4c74-b940-f462cc114d2a
- https://www.amboss.com/de/wissen/Idiopathische_Skoliose/
- https://wirbeldoc.de/idiopathische-skoliose/
- https://de.wikipedia.org/wiki/Skoliose
- https://koller-spine.de/idiopathische-skoliose/













