
A gastric bypass is a procedure used in bariatric surgery, also known as obesity surgery. According to WHO criteria, obesity is defined as a BMI of 30 or higher. Gastric bypass surgery is used to reduce weight in cases of extreme obesity.
Gastric bypass is a form of bariatric surgery and is performed when non-surgical treatments have been exhausted and certain criteria are met. By bypassing a portion of the small intestine, the absorption and passage of food change significantly, which is why close medical monitoring is essential.
In addition to the surgery itself, structured nutritional counseling plays a central role, as digestive juices and nutrient absorption change after gastric bypass surgery. Alternative procedures, such as the gastric balloon, may be considered in select cases but do not replace surgery in cases of severe obesity.
Here you will find further information as well as a list of selected specialists and centers.
When is gastric bypass surgery performed?
Extreme obesity (adiposity permagna) or morbid obesity (BMI over 40) can lead to health complications. Many patients have already tried unsuccessfully to lose weight on multiple occasions.
This often leads to comorbidities or serious impairments of general health. In such cases, gastric bypass surgery may be an option.
The choice of procedure is always determined on a case-by-case basis and depends on the following criteria:
- The presence or risk of a serious comorbid condition or symptom with a body mass index of 35 or higher
- Completion of conservative therapy: A gastric bypass is a treatment option in bariatric surgery after all conservative measures have been exhausted.
- Motivation and cooperation on the part of the patient: The success of the surgery depends directly on the patient’s motivation and cooperation. Any reasonable doubt regarding this therefore constitutes a direct exclusion criterion.
- Appropriate age: Gastric bypass surgery is generally performed between the ages of 18 and 65.
In addition, doctors advise against such a procedure in the presence of the following factors:
- poor general health
- Presence of a malignant disease (malignant tumor)
- Addiction
- unstable mental illness
- untreated eating disorder
- High blood pressure
- Various physical and mental health conditions
- Severe liver disease
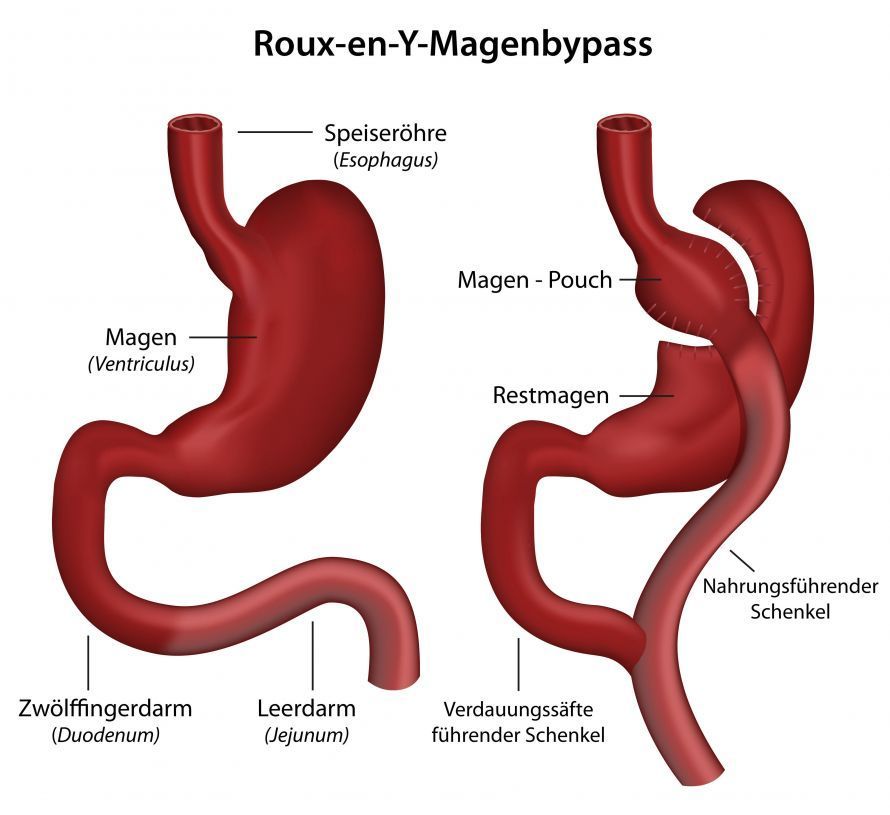
The Surgical Procedure for a Roux-en-Y Gastric Bypass
Nearly 99 percent of gastric bypass surgeries are performed laparoscopically (minimally invasively). This requires only small incisions through which the surgeon inserts tiny instruments. The wounds heal faster than with major open surgery and leave only very small scars.
Laparoscopic gastric bypass surgery is performed under general anesthesia and takes about 60 to 90 minutes.
The standardized “Roux-en-Y” technique is performed as follows:
- The surgeon makes several incisions, each about two centimeters long, in the abdominal wall. A camera with a light source and the necessary instruments are inserted through these incisions. By introducing a gas (usually CO2) into the abdominal cavity, the abdominal wall lifts slightly. This gives the surgeon a clear view and better access to the organs.
-
Using a stapler, the surgeon divides the stomach into a small functional section and a larger section that will be rendered non-functional.
- The subsequent incision through the small intestine creates two free ends, forming a Y-shaped branch of the small intestine. This method was developed by the Swiss physician César Roux and is medically referred to as a Roux-en-Y gastric bypass.
- The lower free loop of the small intestine is pulled upward and sutured to the outlet of the small residual stomach.
- The surgeon guides the upper end—which is connected to the bypassed portion of the stomach—through an artificially created opening, typically about 100 centimeters further down into the small intestine.
Surgeons distinguish between two types of gastric bypasses:
- the proximal gastric bypass and
- the distal gastric bypass.
The distinguishing factor is the length of the remaining small intestine available for digestion. This refers to the section of the small intestine between the point where it connects to the lower remnant of the stomach and the junction with the large intestine.
The standard procedure is the proximal gastric bypass, which involves a section of the small intestine approximately 2.5 meters long. The more extreme distal gastric bypass, which leaves only about one meter of small intestine, is used less frequently.
After the procedure
After the Roux-en-Y procedure, close monitoring is required, which is why the patient is initially admitted to the intensive care unit.
As early as the first day after the procedure, the patient should move around to prevent pneumonia and dangerous blood clots. To support this, the patient receives a blood-thinning medication (heparin) daily.
On the second day after surgery, an initial check of the results is performed. The goal is to identify any potential weak spots or narrowings. This is done using an X-ray examination with a barium swallow (swallowing a contrast agent).
If there are no complications or medical concerns, and provided the patient’s recovery is progressing well, they may be discharged from the hospital after just 4 to 5 days.
A sick leave certificate is issued for a total of 4 weeks.
Gastric Bypass Surgery: Benefits, Risks, and Gradual Dietary Reintroduction
Benefits
A key benefit of gastric bypass surgery is that it not only enables significant and sustained weight loss but also improves metabolic conditions. Many patients experience more stable blood sugar levels, reduced joint pain, and noticeable relief for the cardiovascular system soon after the procedure. To ensure the body’s long-term nutritional needs are met, patients learn to specifically supplement their diet with vitamins and minerals, which is an important part of postoperative care.
Furthermore, due to the specific procedure involved in gastric bypass surgery, the operation combines two mechanisms of action: a significant restriction of food intake and altered calorie absorption in the intestines. The residual stomach remaining after surgery allows patients to feel full much more quickly, which supports weight loss and makes relapse more difficult. This effect has a positive impact on numerous comorbidities—from diabetes to high blood pressure.
Added to this is a structural advantage for many patients: Since the gastric bypass is among the most thoroughly researched bariatric procedures, patients benefit from a high success rate and the surgeons’ many years of experience. Furthermore, the procedure is covered by insurance under certain conditions, which makes it more accessible to severely obese individuals. This is a blessing, as the gastric bypass is currently one of the preferred procedures in modern bariatric surgery and is considered highly effective.
Risks and Complications
A gastric bypass is a major procedure. It carries an increased risk of complications, primarily due to obesity and associated medical conditions.
A detailed screening is conducted prior to surgery to assess individual risk.
Nevertheless, as with any abdominal surgery, complications can occur, such as:
- Adhesions in the abdominal cavity
- Infections
- Blood clots or
- Bleeding and postoperative bleeding
Risks specific to gastric bypass surgery include:
- Suture breakdown
- Narrowing
- Injury to adjacent structures such as the esophagus, liver, spleen, or stomach
- Allergic reactions
- Gastric perforation
- Inadequate connection between the operated organ segments
Through the bypass, doctors completely or partially bypass several organs, such as:
- the residual stomach
- duodenum
- Upper small intestine
This creates the risk of what is known as early dumping syndrome. In this condition, the chyme passes too quickly from the stomach into the small intestine.
Dumping involves a sudden release of undigested, osmotically active chyme into the small intestine. There, it leads to fluid loss as fluid flows out of the surrounding intestinal tissue.
This results in what is known as volume depletion, which manifests as follows:
- Nausea and vomiting
- Sweating
- Drop in blood pressure
- Rapid heartbeat, as well as
- Feeling of fullness
What can you do to manage dumping syndrome?
In addition to early dumping, which occurs about 30 minutes after a meal, late dumping is also possible, in which large amounts of glucose are transported too quickly. The following symptoms usually appear about 1 to 3 hours after eating:
- low blood sugar
- cold sweats
- feeling weak
- dizziness
- changes in heart rate
If you experience dumping syndrome after bypass surgery, talk to your doctor. He or she will examine you thoroughly to rule out other causes and provide you with important advice on how to prevent dumping in the future. If necessary, your doctor may prescribe medication to help alleviate your symptoms.
The best way to prevent dumping syndrome is through a modified diet, such as one rich in fiber and protein. Avoid simple carbohydrates and sugar. Experience has shown that some patients also can no longer tolerate dairy products.
However, it’s not just about the foods you eat—it’s also about the quantity and eating slowly. Do not consume drinks and meals at the same time; instead, space them out a bit.
In addition, the following long-term complications may arise as a result of surgery:
- Alcohol intolerance
- Gallstones and kidney stones
- Inflammation of the peritoneum (peritonitis)
- Deficiency syndromes such as iron and vitamin B12 deficiency
Slow reintroduction of food after the bypass
In the first 48 hours after surgery, the focus is on allowing the sutures to heal. Therefore, the patient may only consume non-carbonated water or other clear liquids during this time.
This is followed by a gradual and gentle reintroduction of food over several weeks, divided into four phases:
- First phase (during the first two weeks) with low-fat milk and dairy products, yogurt, or light vegetable soups.
- Second phase (followed by two to three weeks) consisting of pureed foods with low fat and sugar content.
- Third phase (if Phase 2 is well tolerated): high-protein foods with low amounts of sugar and fat.
- Fourth phase (if Phase 3 is well tolerated): primarily protein-rich foods with a gradual transition from soft to solid foods. The patient should avoid foods high in sugar and fat.

This takes place as part of outpatient or inpatient rehabilitation. Here, patients learn to adjust their diet to prevent nutritional deficiencies.
The gastric bypass specifically reduces the absorption of fats and carbohydrates. Because the length of the intestine is shortened, deficiency symptoms may now occur due to nutrients being excreted prematurely. To prevent this, patients must consume sufficient protein.
The so-called intrinsic factor, produced by the stomach lining, is necessary for the absorption of vitamin B12. This is no longer possible after a gastric bypass. Patients must therefore take vitamin B12 supplements for the rest of their lives.
After surgery, the following levels should be monitored regularly:
- Iron
- Vitamin B12, and
- Folic acid
If necessary, the patient may need to take supplements for these nutrients.
Omega-Loop Bypass and Possible Physical Changes After Surgery
The Omega-Loop Bypass
Another procedure is the mini-gastric bypass, in which only the remaining gastric pouch is connected to the small intestine. It is a variation of the Roux-en-Y method and is also known as the Omega-Loop bypass.
This type of gastric bypass is particularly beneficial for patients who require significant weight loss but do not have complex gastric malformations. The surgical procedure is typically performed by experienced specialists in general and visceral surgery, as the anatomical changes must be made with precision and safety.
In certain cases, a gastric bypass may be considered for patients with a BMI of 35 or higher, particularly if they already have comorbidities. Health insurance coverage is often granted following a case-by-case review by the insurance provider, once conservative treatment options have been exhausted and the gastric bypass is recognized as a medically necessary form of therapy.
Procedure
In an omega-loop gastric bypass, surgeons surgically transform the stomach into a long, narrow tube. In the process, they remove large portions of the stomach as well as sections of the adjacent small intestine.
This significantly reduces the stomach’s volume. The patient can consume less food and absorb fewer nutrients from the digested food in the intestines.
Consequently, hormonal balance changes. Patients experience less hunger and therefore consume less food. The feeling of fullness also sets in relatively quickly. Bariatric surgery also appears to have a positive effect on diabetes.
Complications of the Loop Procedure
Due to the altered digestive physiology (shortened gastric and intestinal transit time), deficiency symptoms may occur. The patient may no longer be able to absorb important nutrients, such as vitamins (vitamin B12), in sufficient quantities.
In addition, an Omega-Loop bypass can lead to an imbalance in fluid levels in the intestines. The patient then suffers more frequently from constipation or prolonged diarrhea. Swallowing difficulties, peritonitis, osteoporosis, and hair loss may also occur.
Another complication is the reflux of bile into the residual stomach. The long-term consequences of such reflux have not yet been thoroughly studied. Observations suggest that bile acids can trigger gastric cancer approximately 10 to 15 years after reflux begins.
For this reason, doctors advise patients with reflux to undergo another surgery. Instead of the Omega-Loop variant, they receive a Roux-en-Y bypass.
Precisely because the remaining stomach is significantly reduced in size during the surgery, patients must ensure a consistent intake of vitamins and minerals for the rest of their lives following gastric bypass surgery. A gastric bypass for obesity not only alters digestion but also places significant demands on the body and often on the mind as well, which is why regular checkups and close follow-up care are essential. If physical or mental health conditions are present, doctors will discuss additional support early on to prevent long-term complications and ensure the success of the procedure.
Cosmetic Effects After Surgery
Due to the significant weight loss that occurs within a short time after any of the surgical methods, the skin cannot retract quickly enough. As a result, it sags in various areas of the body. This can lead, among other things, to an abdominal apron and sagging breasts.
In many cases, plastic surgery can help. Until then, good skin care is very important, especially for larger skin folds. You can also find contact information for plastic surgery experts on our website.
At the end of such a phase of significant weight loss, it’s also worth openly addressing any physical or mental health conditions, as they can influence the healing process. Although a gastric bypass surgery takes a relatively short time, the entire procedure remains a major, life-changing intervention. Because gastric bypass surgery is currently one of the most effective procedures for people with obesity, it is often used when other options have been exhausted. This makes long-term support that addresses both physical and emotional aspects all the more important.
Costs of Gastric Bypass Surgery and Specialists
Costs of gastric bypass surgery:
Statutory health insurance plans do not automatically cover the costs of this type of surgery. However, if the relevant criteria are met, the claim will be approved.
These criteria include a BMI of at least 40 or a BMI between 35 and 40, as well as an additional comorbid condition, such as type 2 diabetes.
Ultimately, the decision on whether to cover the costs depends on whether gastric bypass surgery is clearly medically necessary. The effectiveness of gastric bypass surgery is well-documented scientifically, particularly in cases of severe obesity and associated comorbidities. Because the procedure involves rerouting parts of the stomach and small intestine, it is a complex treatment subject to clear medical criteria. Only when these criteria are met will statutory health insurance plans cover the costs in many cases.
Whether the surgery is recognized as a standard benefit by statutory health insurance therefore depends heavily on the individual case. Patients should seek thorough advice in advance regarding the potential costs and the documentation required. Since gastric bypass surgery is currently one of the most effective surgical procedures for long-term weight loss, it is considered whenever conservative measures have been exhausted. Careful medical and administrative preparation makes the process significantly easier.
Which doctors perform gastric bypass surgery?
Specialists in bariatric surgery are board-certified surgeons in visceral surgery who focus on the surgical treatment of patients with obesity.
Experts in gastric surgery may also focus their practice on gastric bypass procedures.
Alternative surgical methods include, for example, a gastric band or a sleeve gastrectomy.
Since a gastric bypass is currently one of the most effective bariatric procedures, the surgery should be performed exclusively by experienced surgeons. In specialized centers—which are often certified according to the guidelines of the German Society for General and Visceral Surgery—a thorough assessment is conducted to determine whether a gastric bypass is appropriate or if alternative methods would be more suitable. Here, the doctor also discusses the situations in which a gastric bypass is not suitable—such as in cases of certain pre-existing conditions or insufficient willingness to comply with treatment.
Before a gastric bypass is performed, a thorough diagnostic evaluation and consultation always take place. Although gastric bypass surgery is an established and safe procedure, it requires lifelong follow-up care and a stable foundation of health. At these specialized facilities, patients receive a comprehensive evaluation and learn which surgical approach is truly best for them.
FAQs About Gastric Bypass
How does gastric bypass surgery aid in weight loss, and why does it help so many patients so significantly?
Gastric bypass surgery leads to significant and sustained weight loss by utilizing the small remaining stomach and bypassing a segment of the small intestine. At the same time, hormonal balance changes, which reduces appetite and has a positive effect on metabolism.
Does a gastric bypass also help with diabetes mellitus or sleep apnea?
Many patients experience a significant improvement in metabolic conditions after the procedure: Type 2 diabetes can go into remission, and symptoms of sleep apnea often subside as well. These effects are among the most important medical benefits of the surgery.
At what BMI is a gastric bypass recommended, and are there situations in which the procedure is not suitable?
Generally, surgery is performed for a BMI of 40 or higher, or a BMI of 35 or higher with comorbidities. The procedure is not suitable for patients with untreated eating disorders, severe mental health conditions, or certain internal medical risks. In such cases, the disadvantages outweigh the potential benefits and risks of surgery.
What role do benefits and risks play in the decision to undergo a surgical procedure such as gastric bypass surgery?
As obesity continues to rise in Germany, many people are opting for bariatric surgery. Before the surgery, the benefits and risks are carefully weighed—from the prospect of a healthier weight to the possible complications of the procedure.
What should you know before deciding on a gastric bypass—especially considering that a gastric bypass permanently alters part of the digestive process?
The surgery reduces the stomach to a small pouch and reroutes a section of the intestine. This makes lifelong follow-up care, vitamin supplementation, and a sustained change in diet essential. This ensures that the gastric bypass is effective without causing long-term nutritional deficiencies.

About the medical author
Dr. med. Markus von der Groeben
Medical Author
Dr. med. Markus von der Groeben – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
More about the medical author →












