
Polymyalgia rheumatica or giant cell arteritis?
The names date back to a time when very little was known about these conditions. The name (poly = many, myalgia = muscle pain, rheumatica = flowing) contributes to considerable confusion. Although the patient experiences pain in the muscles,
the muscle tissue itself is not pathologically altered. Instead, the condition involves inflammation of an artery that runs through the muscle.
Inflammation of an artery is called arteritis. The condition is referred to as giant cell arteritis when
- the inflammation can be confirmed by a tissue biopsy and
- giant cells are identified in the sample.
The term “polymyalgia rheumatica” is used when
- the inflammation cannot be detected in a tissue sample or
- no suitable site for a tissue sample (biopsy) can be found.
There is disagreement among medical professionals as to whether these are two distinct diseases or whether giant cell arteritis represents a particularly advanced form of polymyalgia rheumatica.
The treatment is essentially the same, although higher doses of medication are used for giant cell arteritis.
Other names for this condition include
- temporal arteritis,
- capitis arteritis, or
- cranial arteritis.
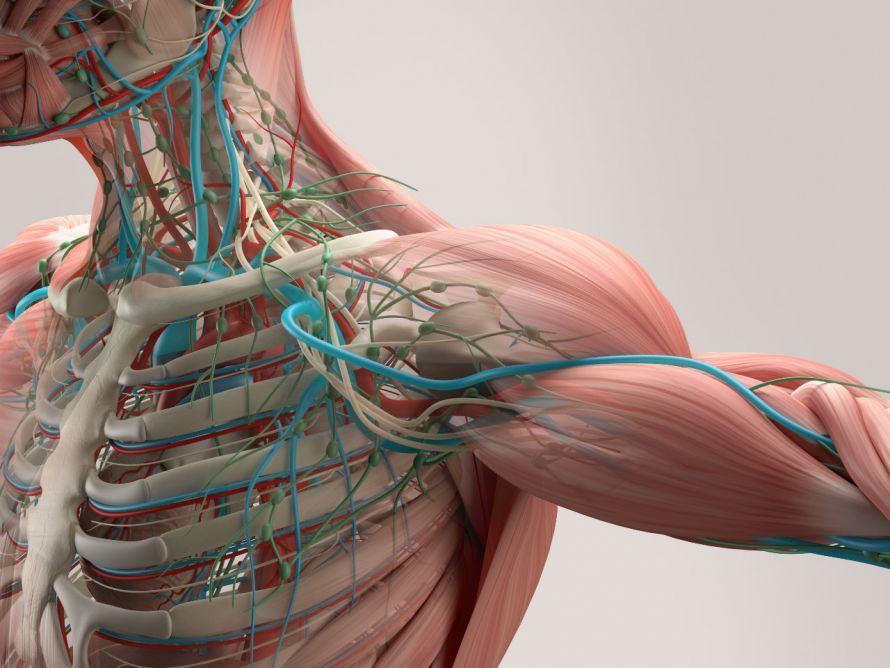
Arteries (red) run through the muscle tissue © Anatomy Insider | AdobeStock
What happens when an artery becomes inflamed?
During the inflammatory process, inflammatory cells (white blood cells—leukocytes) migrate into the artery wall. Giant cells form. The artery wall becomes thicker and stiffer, causing the artery to narrow progressively.
This process develops segmentally. This means that some sections (segments) are severely affected by the narrowing, while others remain unaffected. Therefore, when taking a tissue sample, a sufficiently long section must be removed.
Due to the narrowing of the blood vessels, the affected organs are no longer supplied with sufficient blood. In the event of a complete occlusion, these organs may even die. This process can affect any organ or region of the body.
In some areas, this can lead to medical emergencies:
- Occlusion of the ophthalmic artery: The patient goes blind within a few minutes.
- Occlusion of the coronary arteries: A heart attack occurs.
- Occlusion of the cerebral artery: A stroke is imminent.
Polymyalgia rheumatica is therefore a painful and, in some cases, life-threatening condition. Only timely diagnosis and immediate treatment can avert the impending damage and lead to rapid relief from the severe pain.
To date, no specific cause or trigger has been identified. A certain genetic predisposition is suspected. However, it is not a hereditary disease in the strict sense of the term.
Symptoms of polymyalgia rheumatica
Within a few days to two weeks, extremely severe pain occurs, primarily in the
- the neck,
- the shoulders,
- the upper arms
. Furthermore, this pain may also occur in the area
- the hips,
- the thighs, and
- the lumbar spine
. Initially, the pain is usually present on both sides. It is a constant pain at rest that may vary slightly depending on the time of day. Thus, it occurs even without strain or movement of the affected body parts.
After several weeks, the pain may take on a wave-like pattern and shift location. In addition, the patient complains of
- fatigue,
- fatigue,
- lack of motivation,
- loss of appetite with weight loss,
- and increased sweating.
A physical examination by a doctor often reveals no specific abnormalities. However, it should definitely be performed, as other conditions can present with similar symptoms.
In some cases, swollen joints may be present.
Symptoms such as
- headaches,
- jaw pain,
- dizziness, or
- brief, temporary visual disturbances and loss of consciousness (blackouts)
can be early signs of the serious complications described above. The condition is often accompanied by severe depression. However, this can usually be effectively treated with the right therapy.

Headaches and dizziness may occur when the cerebral artery is affected © goodluz | AdobeStock
Who develops polymyalgia rheumatica or giant cell arteritis?
It primarily affects older adults. The median age of onset is 70 years. The number of new cases increases with age; it is seven times higher among 90-year-olds than among 60-year-olds.
Since this is a disease of older age, the pain is often not associated with inflammation. At this age, joints and the spine already show signs of wear and tear, so pain in these areas is not unusual.
Important indicators for patients are therefore
- the sudden onset of severe pain and
- a severe general feeling of illness,
- and occasionally a fever.
Diagnosis of Polymyalgia Rheumatica and Giant Cell Arteritis
The erythrocyte sedimentation rate (ESR) is moderately to markedly elevated in polymyalgia rheumatica. C-reactive protein (CRP) levels also rise. These values can be used to assess the course of the disease. However, ESR and CRP are nonspecific markers of inflammation; that is, they rise in almost any type of inflammation, such as a common flu or other inflammatory conditions.
In addition, there may be an increase in blood platelets (thrombocytes) and a shift in blood proteins.
X-rays typically reveal findings consistent with the patient’s age. These include age-related wear and tear of the spine or joints, but no signs of inflammation.
The diagnosis of polymyalgia rheumatica is made through
- a discussion with the doctor,
- a physical examination to rule out other conditions, and
- laboratory tests
.
Giant cell arteritis, on the other hand, is diagnosed only by taking a biopsy of a blood vessel and examining it under a microscope.
However, this is only feasible if a suitable site on the body can be found. This site must be carefully selected. Both the biopsy and the microscopic examination must be performed by an experienced specialist.
If thickened arteries can be felt in the temporal region, a biopsy of the vessels should be performed. If giant cell arteritis is present, the necessary medications must be administered at higher doses.
Treatment of Polymyalgia Rheumatica and Giant Cell Arteritis
Corticosteroids are essential! A prompt response to corticosteroids is typical. In medical terminology, corticosteroids are also called glucocorticoids or, for short, corticoids. With an adequate dosage, symptoms resolve within a few hours to a few days.
Laboratory markers of inflammation (ESR and CRP) also return to normal. For CRP, this occurs within a few days; for ESR, it may take a little longer.
The dose must be increased further if
- the pain persists despite this treatment or
- laboratory tests still show signs of inflammation.
The patient must now expect years of treatment. It is therefore important for them to discuss the consequences of corticosteroid therapy with their doctor. In particular, there is a risk of osteoporosis. The high initial dose must be reduced only gradually.
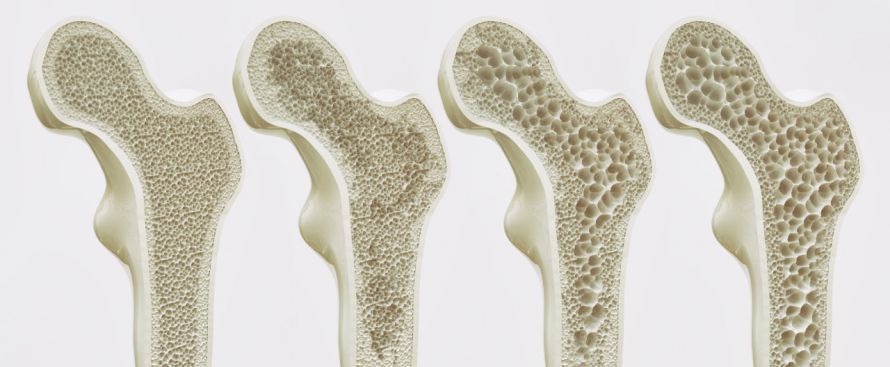
If the dose is reduced too quickly, the pain will return and/or the BKS/CRP levels will rise again. The dose must then be increased until the patient is symptom-free and the lab values are within the normal range.
Before any dose reduction, the physician should be consulted and the BKS level should be measured. In cases of ocular involvement, the “emergency brake” must be applied immediately, as failure to do so carries the risk of irreversible blindness. In this case, the initial dose must be set particularly high.
If a high dose of corticosteroids is required or if a low dose cannot be achieved within 6 to 9 months, additional therapy with methotrexate or azathioprine may be considered. These therapies should be administered by an experienced specialist.
Conventional anti-rheumatic and pain medications can, at best, alleviate the pain. In doing so, they mask the progressive inflammation of the blood vessels and do not constitute an appropriate treatment.
Prognosis for Polymyalgia Rheumatica and Giant Cell Arteritis
The disease usually lasts 3 to 4 years. However, cases lasting 10 years or longer have also been reported.
The necessary medications do not cure the disease but only suppress it. Even with successful treatment, it is not certain that the disease has truly disappeared.
Discontinuing treatment too quickly can lead to a relapse or even blindness. An attempt to taper off the medication—that is, slowly reducing all medications—should not be made until at least 2 years have passed.
FAQ: The 8 Most Important Questions About Polymyalgia Rheumatica
What are the typical symptoms of polymyalgia rheumatica?
The main symptom of the disease is bilateral pain in the shoulder and pelvic girdle muscles, which often occurs overnight. In addition, people with polymyalgia rheumatica suffer from severe morning stiffness that lasts longer than 45 minutes. The muscle pain experienced when getting dressed or getting out of bed is often so severe that mobility is significantly restricted. In addition, general symptoms such as fever, night sweats, fatigue, weight loss, and anemia often occur. These symptoms of polymyalgia rheumatica can significantly reduce quality of life.
How is polymyalgia rheumatica diagnosed?
The diagnosis of polymyalgia rheumatica is primarily a diagnosis of exclusion, as there is no single definitive laboratory test. The physician bases the diagnosis on clinical symptoms and laboratory values (elevated ESR and CRP). To confirm the diagnosis, the 2012 provisional classification criteria for polymyalgia rheumatica—published in medical journals such as *Ann Rheum Dis*—are often used. It is important to rule out other conditions, such as rheumatoid arthritis, by testing for rheumatoid factors and ANCA. A prompt response to a trial dose of prednisone supports the diagnosis.
What is the relationship to giant cell arteritis?
About 15 to 20 percent of patients with PMR also have giant cell arteritis (temporal arteritis). This vasculitis affects the large arteries, particularly the temporal arteries in the head. Warning signs include new-onset headaches, pain when chewing (masticatory claudication), and visual disturbances. Since untreated cranial arteritis can lead to blindness, every PMR patient must be actively screened for it. Conversely, up to 50 percent of patients with giant cell arteritis have symptoms of PMR.
What is the treatment for polymyalgia rheumatica?
The treatment of choice is glucocorticoids (cortisone). Treatment usually begins with an initial dose of 15 to 25 mg of prednisone (or equivalents such as methylprednisolone). Since symptoms often disappear quickly, the dose can be gradually reduced (tapering). The goal is to achieve a maintenance dose that is as low as possible (low-dose) to minimize side effects such as osteoporosis. In complicated cases or with frequent relapses, methotrexate or, less commonly, azathioprine is used as a steroid-sparing medication.
Are there new treatments for PMR?
In addition to standard therapy with corticosteroids and methotrexate, biologics are increasingly being researched. Studies discussed in publications such as the Canadian Medical Association Journal and Ann Rheum Dis show that interleukin-6 inhibitors like tocilizumab or sarilumab can be effective in treatment-resistant PMR. These medications specifically target the inflammatory process and often allow for a more rapid reduction in corticosteroid dosage. Experts such as Buttgereit have contributed to guidelines from the German Society for Rheumatology that evaluate these options.
What do the lab results indicate?
In acute polymyalgia rheumatica, inflammatory markers in the blood are almost always significantly elevated. The erythrocyte sedimentation rate (ESR) is often markedly accelerated (lightning-fast). C-reactive protein (CRP) is also elevated. These values are used not only for diagnosis but also to monitor the course of the disease. If the ESR and CRP decrease during treatment, this suggests the treatment is working. A renewed increase may indicate a relapse.
How long does the disease last?
Polymyalgia rheumatica is usually self-limiting but has a chronic course lasting one to three years, and sometimes longer. The proportion of patients who still require treatment after two years is relatively high. Reducing medication too quickly often leads to relapses. Therefore, close monitoring by a rheumatologist is important to adjust the dosage based on disease activity and maintain symptom-free status.
What differential diagnoses should be considered?
Before diagnosing PMR, other causes of muscle pain and inflammation must be ruled out. These include infections, neoplastic diseases (paraneoplasia), thyroid disorders, myositis, fibromyalgia, and other forms of arthritis, particularly late-onset rheumatoid arthritis (RA). Polymyositis or drug-induced myopathies can also cause similar symptoms.
Share this article
Sources
- S2e-Leitlinie „Behandlung der Polymyalgia rheumatica“ (AWMF-Register-Nr. 060-006), Stand 22.04.2025: register.awmf.org/de/leitlinien/detail/060-006






