
ERCP stands for endoscopic retrograde cholangiopancreatography and is a specialized procedure in gastroenterology. ERCP allows the bile ducts, common bile duct, and pancreatic duct to be visualized using an endoscope and contrast dye under X-ray guidance. Papillotomy is an additional procedure in which the papilla in the duodenum is surgically incised to improve bile flow.
An ERCP with papillotomy is often performed in cases of gallstones in the common bile duct or in cases of strictures. The procedure is performed endoscopically through the stomach into the duodenum up to the papilla of Vater. This is where the common bile duct and the pancreatic duct open into the duodenum. ERCP performed at the hospital serves both diagnostic and therapeutic purposes, such as stone removal or stent placement.
What are ERCP and papillotomy?
Endoscopic retrograde cholangiopancreatography (ERCP) is an endoscopic procedure in which the bile ducts and pancreatic ducts are visualized via an access point through the mouth. This means that no incisions are necessary, as the endoscope can be advanced directly to the bile ducts via existing access routes.
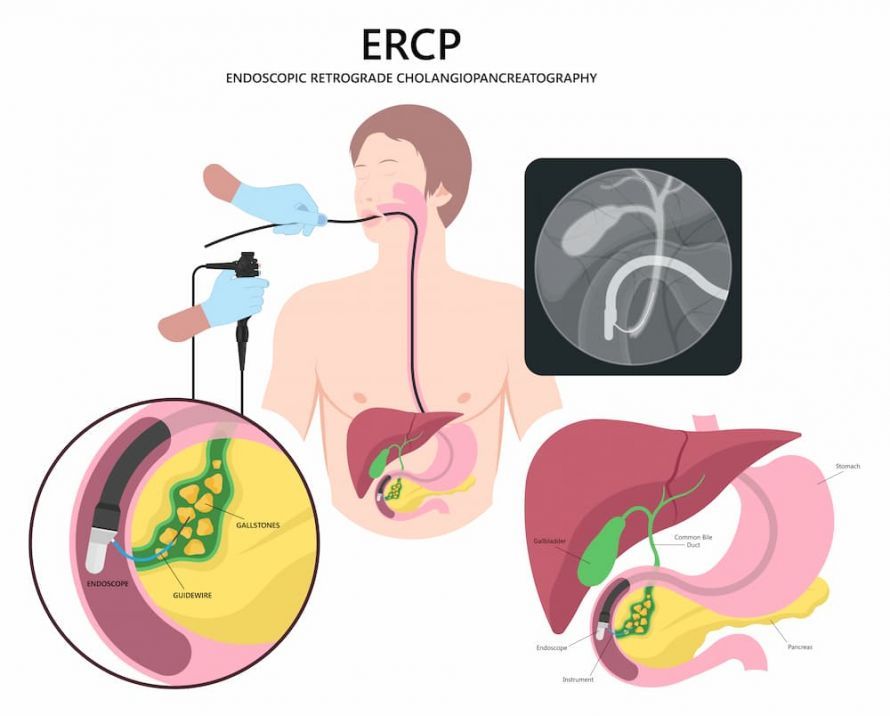 During an ERCP, the doctor examines the bile ducts and the pancreas @ Pepermpron /AdobeStock
ERCP plays a central role in the diagnosis of diseases affecting the bile and pancreatic ducts. Purely diagnostic ERCP is no longer common, except in rare cases. Only the detection of primary sclerosing cholangitis—which cannot be diagnosed by other means—occasionally still justifies its diagnostic use.
For therapeutic purposes, a papillotomy—the opening of the sphincter at the common junction of the pancreatic and bile ducts into the duodenum (papilla, papilla of Vater, major duodenal papilla)—is generally required.
What are the indications and contraindications for ERCP and papillotomy?
The typical leading symptom that often leads to an ERCP is yellowing of the sclera and skin (jaundice, icterus) as a sign of impaired bile flow. In addition, the urine becomes darker, the stool lighter in color, and increased itching becomes noticeable.
Typically, ultrasound is used to confirm obstruction of the bile ducts, and laboratory tests are performed to rule out liver tissue damage and increased breakdown of red blood cells. Typical obstructions include gallstones or tumors. A blockage of pancreatic juice, for example, in the context of chronic pancreatitis, can lead to severe pain.
ERCP and papillotomy cannot be performed if the procedure poses a greater risk to the patient than the underlying bile duct or pancreatic disease being treated. This would be the case, for example, with an acute heart attack or severe blood clotting disorders.
How are ERCP and papillotomy performed?
ERCP is performed under anesthesia. The procedure itself usually takes between 30 and 60 minutes.
An endoscope with a side-viewing lens is advanced to the papilla, and the ducts are selectively probed with a thin wire depending on the clinical indication. After confirming via fluoroscopy that the wire is in the desired duct, contrast dye is injected into the duct. At this point, it is usually clear whether a stone or a narrowing is the cause of the symptoms.
Using a papillotome—a plastic catheter with a short cutting wire—a controlled incision of a few millimeters, known as a papillotomy, can then be made by applying high-frequency current to generate heat.
After papillotomy, there is sufficient space to use baskets or balloon catheters to extract stones or to insert plastic stents or expandable metal stents to bridge the narrowing.
Patient Preparation and Follow-Up for ERCP and Papillotomy
The stomach must be empty for the ERCP procedure, so the patient must fast on the day of the examination. Recent blood tests must have been performed to confirm normal blood clotting and rule out other risks. Medications that significantly impair consciousness (sedation) are administered for the procedure. Typically, the patient is unaware of the procedure.
Following ERCP and papillotomy, inpatient monitoring is recommended so that immediate action can be taken in the event of any complications that may arise. For example, if the patient experiences pain, pain medication can be administered promptly. The patient must not eat anything at first, because food in the stomach stimulates the pancreas—which may have been irritated by the procedure—and increases the risk of acute pancreatitis. Drinking water or unsweetened tea is not considered problematic.
If there are no symptoms the following day and the blood test results show no cause for concern, a gradual return to a normal diet may begin.
If the patient is discharged on the day of the procedure, their limited ability to drive after sedation must be taken into account. The patient must not drive a car for 24 hours. If stones were successfully removed, no follow-up care is necessary; if a tumor was the cause, further measures regarding the underlying condition may need to be arranged.
What complications and risks can occur during an ERCP and papillotomy?
The main side effect of ERCP is acute pancreatitis, which occurs in approximately 5% of procedures. The risk is higher if the physician lacks experience, if anatomical conditions are particularly challenging, or if very specific medical conditions are present.
Furthermore, the risk is generally slightly higher for female patients than for male patients.
What are the prospects for recovery after ERCP and papillotomy?
ERCP, papillotomy, gallstone extraction, and stent placement are successful in well over 90% of cases when performed by experienced practitioners.
Once stones have been removed from the bile duct, removal of the gallbladder (cholecystectomy) is usually required to prevent further stones from migrating from the gallbladder into the duct, even though these stones can pass more easily on their own into the small intestine following papillotomy.
If a stricture caused by a malignant tumor has been treated, radical surgery is unavoidable for a cure. Unfortunately, due to the advanced stage of the tumor, the patient’s age, or comorbidities, such surgery is often no longer possible, and bile drainage serves as a palliative measure to maintain quality of life.
If the flow of the pancreatic duct is restored in cases of painful chronic pancreatitis through ERCP, papillotomy, stone extraction, or stents, approximately two-thirds of patients can expect their pain to cease or be largely alleviated.
FAQ
What exactly does ERCP stand for?
ERCP stands for endoscopic retrograde cholangiopancreatography. During the procedure, an endoscope is advanced into the duodenum, and contrast dye is injected through the papilla into the bile ducts or the pancreatic duct. Using fluoroscopy and X-rays, abnormalities such as stones or strictures become visible. ERCP is thus a combination of endoscopy and radiologically guided imaging.
When is a papillotomy performed?
A papillotomy is often performed as part of an ERCP when the bile duct is obstructed by gallstones. By incising the papilla—a procedure also known as transduodenal papillotomy or EPT—the opening can be widened. This facilitates stone extraction during an ERCP and improves bile flow. A papillotomy may also be beneficial in cases of sphincter of Oddi dysfunction.
How is stone extraction performed during an ERCP?
After visualizing the bile ducts, a papillotomy is performed if necessary. The stones are then extracted from the common bile duct using special instruments, such as baskets or balloon catheters. In some cases, lithotripsy is also used to break up larger stones. The stone is then extracted via the endoscope.
What are the risks of ERCP?
Like any endoscopic procedure, ERCP carries risks. Possible complications include inflammation—particularly pancreatitis—bleeding, or infection. In rare cases, upper abdominal pain or injury to the bile ducts may occur. For this reason, ERCP is performed only when clearly indicated.
When are stents used?
Stents are small tubes that are inserted into the bile duct or the pancreatic duct. They are used for drainage in cases of narrowing, tumors, or inflammatory swelling. The goal is to ensure the flow of bile or pancreatic juice and to normalize elevated liver enzyme levels. An ERCP with papillotomy can thus bring about a lasting improvement in symptoms.
About the medical author
PD Dr. med. Uwe Seitz
Medical writer







