
Percutaneous nephrolithotomy is an established procedure for treating kidney stones and is primarily used for larger stone loads. PCNL, also known as percutaneous nephrolitholapaxy or PNL, is one of the most important procedures in urology for the treatment of urolithiasis. During this procedure, a puncture is made in the kidney through the skin to directly access and remove stones.
PCNL offers a high success rate in achieving stone-free status, particularly for kidney stones larger than 2 cm. Compared to ESWL (extracorporeal shock wave lithotripsy), percutaneous nephrolithotomy is often more effective. The indication depends on the size, location, and composition of the kidney stones. Modern techniques, such as tubeless procedures, reduce the postoperative burden and promote recovery.
Indications for PCNL
PCNL is a minimally invasive treatment similar to ESWL and (flexible) ureterorenoscopy. ESWL breaks up kidney stones using shock waves. The patient then passes the fragments through the urinary tract. This procedure is the treatment of choice for most kidney stones.
Indications for PCNL arise when ESWL reaches its limits.
It is an option for patients:
- Who do not respond to ESWL treatment
- For whom ESWL has a low chance of success from the outset
The following factors play a role:
- The size of the kidney stone (PCNL is used for kidney stones with a diameter of >2 cm or for stones that have broken off)
- The composition of the kidney stone
- Problems with the urinary tract or
- An unfavorable location of the kidney stone
 A kidney stone in size comparison @ New Africa /AdobeStock
Percutaneous nephrolithotomy is not suitable in the following cases:
- Pregnancy
- Untreatable coagulation disorders
- Untreated acute urinary tract infection
Performing PCNL
Percutaneous nephrolithotomy is usually performed under general anesthesia while the patient is lying on their stomach. However, it can also be performed with the patient in a semi-recumbent position.
- Renal puncture
Prior to PCNL, retrograde placement of a balloon ureteral catheter is recommended. Doctors use this catheter to inject a contrast agent to dilate and visualize the renal pelvis and calyces, which simplifies the renal puncture.
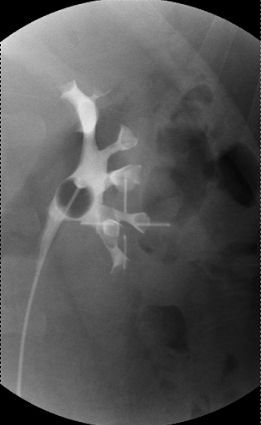
Contrast imaging of the renal pelvis and calyces using a balloon ureteral catheter blocked in the renal pelvis
The puncture itself is performed using a puncture guide that is rigidly connected to the ultrasound probe. This serves as a guide for the puncture needle.
Access to the renal calyceal system is usually gained through the lower calyx group. This puncture carries the lowest risk. The lower pole of the kidney has the lowest density of blood vessels, so the risk of bleeding is lowest here. In contrast, puncturing a middle or upper renal calyx can more easily lead to injury to neighboring organs.

If doctors are unable to reach the calyx containing the stone, they can alternatively puncture another group of calyces or a calyceal diverticulum. Using a puncture needle, doctors insert a guidewire into the renal calyx system, which they use to dilate (bougie) the puncture channel.
There are various options for dilating a narrow section to a diameter of 6 to 10 millimeters:
- Telescopic rods that gradually increase in thickness and are used one after another
- Plastic rods, which doctors gradually replace with thicker ones
- Balloons that are inflated to widen the narrow section
Doctors then insert the working shaft into the dilated channel. This allows for safe access to the renal pelvis and calyx system. The surgeon can then inspect the renal pelvis and calyx system while continuously flushing the system.
- Breaking Up the Kidney Stone
Various lithotripsy probes are available for breaking up the stone. In addition to ultrasonic drilling probes with continuous suction, pneumatic or laser-based probes are primarily used today.
Ultrasonic drilling probes are suitable for rigid nephroscopes. The reason is the rapid fragmentation and simultaneous suction of large stone masses. For flexible nephroscopes or mini-PCNL, Holmium:YAG laser lithotripsy is primarily used.
The Holmium:YAG (Holmium:Yttrium-Aluminum-Garnet) laser is suitable for fragmenting stones of all compositions. Physicians then remove any remaining fragments using forceps or a retrieval basket.
- Verification of Results and Alternatives
At the conclusion of the PCNL, endoscopic and radiological examinations are performed to confirm that the kidney is free of stones. If stones remain, a second-look PCNL, ESWL, or URS is required as a follow-up procedure.
For large stone masses, a combination treatment involving PCNL and flexible URS may also be planned from the outset.
After the procedure, doctors typically insert a balloon nephrostomy tube through the access channel. This allows for safe urine drainage and hemostasis through compression of the puncture site. In addition to flexible nephroscopes, there is another technical innovation: mini-PCNL. This technique uses instruments designed to provide access to the renal pelvis with less tissue trauma. Mini-PCNL is not so much an alternative to PCNL as it is an alternative to ESWL. It is suitable for the treatment of lower calyx stones.
Results of the Procedure
The success rate of percutaneous stone removal depends on:
- Stone size
- Stone location, and
- Anatomical conditions
In general, PCNLs achieve stone-free rates of > 90%.
Physicians prefer to use PCNL for stones in the lower calyx group. A study by the Lower Pole Study Group shows the following results for lower calyx stones with a mean size of 14 mm:
- After PCNL, a stone-free rate of 95%
- After ESWL treatment, stone-free rate of 37%
Further studies demonstrate that percutaneous stone removal can also yield good results in the following conditions:
- Horseshoe kidneys
- Transplanted kidneys
- Malrotated kidneys
- Pelvic kidneys
- obese patients
PCNL in children
ESWL achieves excellent results in children and is used in most cases. However, PCNL is preferred in the following cases:
- ESWL-refractory stones
- Large stone masses or
- Anatomical anomalies
For pediatric patients, mini-nephroscopes should be used. In these cases, the success rate for achieving a stone-free state is up to 100%.
Possible Complications of PCNL
The most common complications during PCNL are venous bleeds. These are usually asymptomatic but can lead to termination of the procedure due to impaired visibility.
The vast majority of postoperative complications following a PCNL—such as prolonged bleeding, urinary tract infections, or fever—can be managed conservatively.
If severe venous bleeding occurs that does not stop spontaneously, doctors clamp the nephrostomy tube. If this also fails to stop the bleeding, the cause is usually arterial bleeding. Doctors can occlude these after making the appropriate diagnosis. Open surgery is therefore rarely necessary. Large-scale studies have shown that only 10–15% of bleeding episodes require a blood transfusion.
Injuries to adjacent organs such as the intestines, spleen, liver, or lungs are rare but particularly serious. Puncturing an upper renal calyx via an access route above the ribs is especially risky. This can lead to injury to the thoracic organs. In our opinion, puncture under combined ultrasound- and fluoroscopy-guided control is a crucial measure for reducing such complications.
By using ultrasound as a guide, physicians can identify and protect adjacent organs such as the intestines, liver, spleen, and lungs. We therefore view radiologically guided renal puncture—which is particularly widespread in North America—with skepticism.
The entire procedure (preoperative ultrasound, procedural planning, puncture, stone removal, and postoperative follow-up) should remain under the urologist’s control. The renal puncture is the most delicate part of the procedure. The success of the operation depends on it. Therefore, the surgeon should perform this procedure personally, as he or she is best able to assess the optimal access route.
Conclusion
Percutaneous nephrolithotomy is considered a well-established procedure for the treatment of kidney stones and is used in particular for large kidney stones in the renal pelvis. As a method for removing kidney stones, minimally invasive PCNL—or minimally invasive percutaneous nephrolitholapaxy—enables effective stone treatment, in which lithotripsy is often performed pneumatically and general anesthesia is usually required.
Compared to extracorporeal shock wave lithotripsy, this procedure is particularly suitable for kidney stones larger than 10 mm, although modern variants such as tubeless PCNL can shorten the hospital stay.
A nephrostomy tube may be temporarily inserted after percutaneous nephrolithotomy to ensure urine drainage, although risks and complications must be assessed on a case-by-case basis.
FAQ
What is percutaneous nephrolithotomy (PCNL)?
Percutaneous nephrolithotomy is a minimally invasive procedure for removing kidney stones. During PCNL, access to the kidney is created via a puncture to directly碎石 and remove them. The procedure is also known as percutaneous nephrolitholapaxy or PNL.
When is a PCNL performed?
It is primarily indicated for large kidney stones over 2 cm, complex urolithiasis, or when ESWL (extracorporeal shock wave lithotripsy) is not sufficiently effective. Stones in the renal pelvis or stones in the kidney that are difficult to access may also require treatment via PCNL.
How is the procedure performed?
Percutaneous nephrolithotomy is usually performed under general anesthesia and often with the patient in the prone position. After puncture, a working channel is created through which flexible instruments are inserted. Lithotripsy is performed pneumatically or using other methods to remove the stones and restore urine flow.
What are the potential risks and complications?
Risks and complications include bleeding, infection, injury to adjacent structures, or temporary urinary drainage via a nephrostomy. These complications are regularly analyzed in scientific publications such as *Eur Urol* or *World J Urol*. However, most complications can be effectively treated.
How long does recovery take after a PNL?
The hospital stay is usually only a few days. Modern procedures such as tubeless PCNL or minimally invasive PCNL can shorten the recovery time. Postoperatively, the patient is checked to ensure the kidney is stone-free, and further treatment for kidney stones is planned if any residual stones are present.
About the medical author
Prof. Dr. med. Thomas Knoll
Medical writer






