
Radical cystectomy is a well-established surgical procedure for treating bladder cancer and advanced bladder carcinoma. This surgical procedure involves the complete removal of the bladder and, in many cases, the surrounding affected tissue. An urinary diversion is then created so that urine can continue to be drained from the body.
Depending on the situation, a neobladder, a stoma, or other methods of urinary diversion may be considered. The surgery is performed in specialized urological centers and is often combined with lymph node removal. In men, the prostate and adjacent structures are often removed as part of a radical cystectomy. The goal of treatment is the complete removal of the tumor and the prevention of further spread. The choice of urinary diversion method has a significant impact on the patient’s future quality of life.
When is a radical cystectomy performed?
In about 70% of bladder cancer patients, the initial diagnosis is made at an early stage of the tumor. A thorough evaluation is then conducted. If it is determined that the tumor has not yet infiltrated the bladder muscle, patients often receive radiation therapy and/or chemotherapy as an initial treatment. In some cases, a simple cystectomy may be an option instead of a radical cystectomy.
For a radical cystectomy, the timing of the surgery is crucial:
- all other treatment options for bladder cancer must have been exhausted, but
- the cancer must not yet have metastasized to other organs.
To be on the safe side, the surrounding organs and nearby lymph nodes are therefore removed along with the bladder.
The following clinical presentations indicate the need for a radical cystectomy:
- Muscle-invasive bladder cancer: In this case, the tumor has already infiltrated the muscle layer of the bladder wall and possibly surrounding tissue, but has not yet spread to more distant tissues.
- Superficial bladder carcinomas with an aggressive growth pattern: This is a non-muscle-invasive bladder cancer that, however, exhibits rapid and uncontrollable growth.
- Minimally invasive, hard-to-reach superficial bladder carcinomas: A transurethral resection (endoscopic resection via the urethra, also known as TURB) cannot control this form of cancer.
- As a palliative measure: If an inoperable bladder cancer leads to increased pain, bleeding, and other symptoms that impair quality of life, a radical cystectomy is also indicated.
- Lack of bladder capacity: Bladder atrophy can severely limit bladder capacity. This leads to persistent urge incontinence, which significantly reduces the quality of life for those affected.
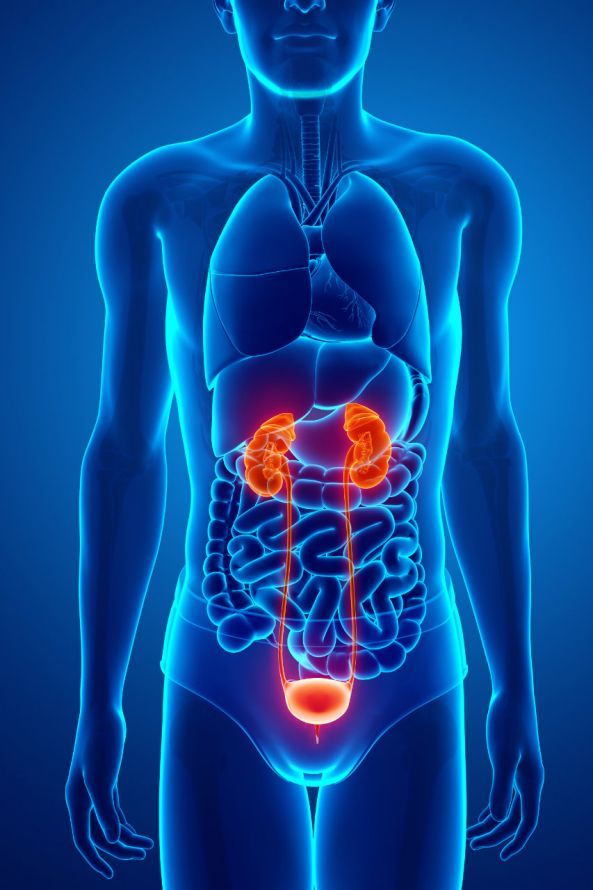
The location of the bladder, which is connected to the kidneys via the ureters © pixdesign123 | AdobeStock
The Procedure for a Radical Cystectomy
The surgery requires hospitalization. This means you will be assigned a bed in the hospital and will remain in the hospital for a few days after the surgery.
An informational consultation will also take place beforehand. During this consultation, your treating physician will explain the surgical technique to be used as well as any potential risks. You will also receive detailed information about alternatives to urinary diversion prior to the surgery. The patient is usually in a supine position and under general anesthesia during the surgery.
For a radical cystectomy, the surgeon makes an incision in the lower abdomen from the pubic bone to the navel. First, the surgeon removes the bladder and the lymph nodes, as these may contain metastases.
As part of a radical cystectomy, the surgeon also removes—depending on the patient’s gender—
- the prostate or
- the ovaries, fallopian tubes, and usually the uterus, as well as
- additional surrounding tissue (safety margin).
In this state, the body can no longer drain the urine produced by the kidneys. For this reason, the surgeon creates an artificial urinary diversion or bladder so that urine can still be drained after the surgery. The procedure takes between three and five hours.
Alternatives to Open Surgery
As an alternative to the conventional surgical method, a minimally invasive surgical technique may be an option in certain circumstances. The procedure is performed as part of a laparoscopy using an assistive surgical robot (Da Vinci). Surgical instruments, including a video camera, are inserted through tiny incisions in the abdominal wall.
This robot-assisted, minimally invasive bladder removal is considered a major challenge with a high degree of difficulty. Nevertheless, the advantages of this method outweigh those of open abdominal surgery:
- Blood loss is significantly lower,
- surgical wounds heal much faster,
- complications occur less frequently, and
- scarring is minimal.
However, not every hospital is equipped for this procedure or offers this relatively costly surgical technique. You should discuss with your doctor in advance whether Da Vinci surgery is an option for you.
Urinary Diversion
Depending on the findings and the course of the surgery, different forms of urinary diversion may be considered following a radical cystectomy. Of course, your preferences or aversions regarding specific forms of urinary diversion will also be taken into account.
There are three options for artificial urinary diversion:
- Wet or incontinent urinary diversion: With this method, urine flows directly from the abdominal cavity into a pouch that is not visible to others. This form of urinary diversion is particularly recommended if the disease has significantly impaired the patient’s overall condition.
- Dry urinary diversion: The surgeon removes a section of the small intestine—and sometimes a piece of the large intestine as well—and uses it to construct a replacement bladder. This new bladder is medically referred to as a “neobladder.” Prerequisites for this procedure include intact ureters, good overall health, and a healthy intestine.
- Dry urinary diversion through the skin: In cutaneous urinary diversion (through the skin), the surgeon also constructs a urine reservoir in the abdomen using sections of the intestine. This urine reservoir, known as a pouch, extends to the area around the navel. A valve of sorts is inserted there to allow urine to drain. When the pouch fills up and presses against the artificial opening, you can empty it using a disposable catheter. This type of “umbilical urinary bladder” is called a continent or dry urostomy, since you can control the emptying yourself.
When using a neobladder, the patient can use the restroom as usual without any problems. The only issue is that the patient cannot feel when the neobladder is full. You must therefore get into the habit of emptying the bladder at regular intervals (every 3 to 4 hours) in the restroom. Soon, the absence of a bladder will no longer be a problem in everyday life.
Urine does not flow out on its own when you urinate. You must therefore use your abdominal muscles to push. If you still have difficulty emptying your bladder, you can drain the urine using a catheter. You will also learn how this works and how to insert the catheter following your surgery.
Follow-up Care After a Radical Cystectomy
Follow-up care takes place either at the hospital where the surgery was performed or with a private urologist who has the appropriate experience.
Conclusion on radical cystectomy
A radical cystectomy initially presents a major psychological challenge for those affected. Thanks to state-of-the-art technology, however, patients today can lead an almost normal life again with either a neobladder or a urinary diversion.
FAQ
What is a radical cystectomy?
A radical cystectomy is the surgical removal of the bladder and is considered an important treatment method for invasive bladder cancer and bladder carcinoma. During this procedure, surrounding tissue and lymph nodes are often removed along with the bladder. The goal is to completely remove the tumor and prevent the further spread of cancer cells.
Which organs are removed during a radical cystectomy?
In men, a radical cystectomy also involves the removal of the prostate and seminal vesicles. In women, depending on the extent of the tumor, the uterus, ovaries, or part of the vagina may be removed. The complete removal of the bladder is always performed in accordance with oncological criteria and the patient’s individual situation.
What options are available for urinary diversion after bladder removal?
After bladder removal, various methods of urinary diversion are available. Continent urinary diversion can be achieved using an orthotopic neobladder created from a section of the small intestine. Alternatively, an ileal conduit with a stoma or other forms of diversion may be considered. Urine is drained via the ureters and intestinal tissue, allowing urine to continue to be safely excreted.
How is the surgery performed?
The surgery is performed under general anesthesia and involves removal of the bladder, a lymphadenectomy, and the creation of a urinary diversion. During the procedure, the ureters, lymph nodes, and, if necessary, other affected structures are carefully examined. After the surgery, catheters, drains, and intensive postoperative care support wound healing and recovery.
What does follow-up care after a radical cystectomy involve?
Follow-up care includes regular monitoring of kidney function, the urinary diversion, and any possible changes in the tissue. In addition, continence, urination, the integrity of the neobladder, and the function of the stoma are assessed. Structured follow-up care helps detect complications early and maintain quality of life in the long term.

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
More about the medical author →Sources
- https://www.krebsinformationsdienst.de/ (Deutsches Krebsforschungszentrum)
- https://www.urologielehrbuch.de/
- https://www.aerzteblatt.de/








