
Thrombectomy is an interventional procedure in which a blood clot is mechanically removed from an occluded blood vessel. This procedure can be life-saving, particularly in cases of ischemic stroke—the most common type of stroke—since a thrombus blocks blood flow to the brain. Using a thin catheter, often inserted through the femoral artery, clots can be removed with the aid of a stent retriever or by suction. This method is now considered a key acute therapy in modern stroke treatment and is performed in specialized neuroradiology centers. Studies show that patients with occlusions of large and medium-sized cerebral arteries benefit significantly from mechanical thrombectomy—especially when it is performed within a narrowly defined time window after the onset of symptoms.
Why does blood clot?
Any type of injury to blood vessels triggers the blood clotting process. The blood clumps together and forms small clots. These clots attach to the inside of the damaged vessel and seal it off. Blood clotting is therefore essential for wound healing.
What exactly is a thrombosis?
Sometimes, blood clumps together without any injury. This can lead to further problems.
Initially, a tiny blood clot forms. In most cases, the body can dissolve it. If it is unable to do so, the blood clot may continue to grow. If it becomes large enough, it can block the entire blood vessel.
If this happens in a vein, this blockage is called a thrombosis; in arteries, it is called a thrombotic occlusion.
Why does thrombosis occur?
Ultimately, there are three main causes of thrombosis:
- Changes in the vessel wall, particularly injuries, irregularities, calcium deposits, or narrowings.
- Changes in blood composition, for example, in cases of blood cancer (leukemia) or congenital disorders associated with an increased risk of blood clotting.
- Changes in the flow and flow properties of the blood. These are caused by turbulence in the area of narrowings or during prolonged immobility (air travel, long car rides), as well as after surgery requiring bed rest.
These three factors are also known as Virchow’s triad. Virchow was a German pathologist who conducted extensive research on both normal and pathological blood clotting.
Other examples from everyday clinical practice associated with clot formation:
- Infusion tubes or pacemaker leads in blood vessels can also cause clots to form.
- Prolonged inactivity—for example, from sitting for too long in a cramped position, being bedridden, or suffering from paralysis—can contribute to thrombosis. This is why you should always wear compression stockings after surgery or during a long flight.
- Certain heart conditions also increase the risk of blood clots.
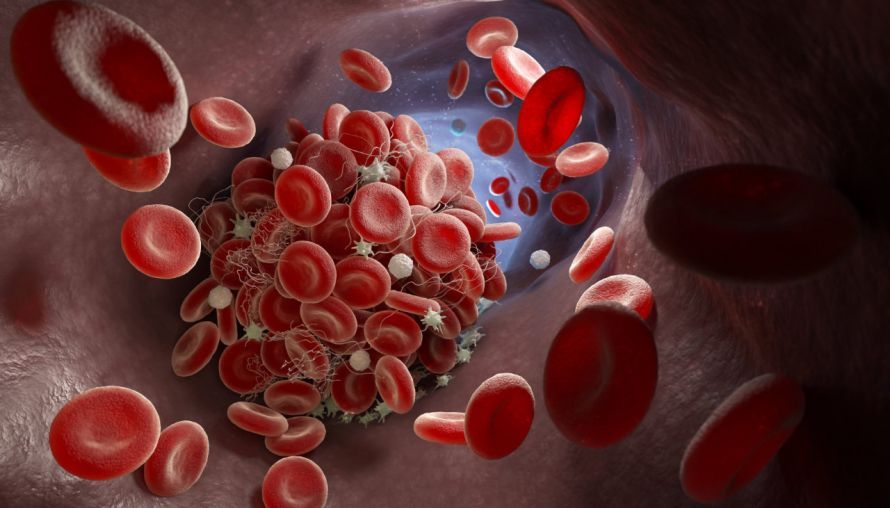
In thrombosis, the blood clumps together and forms a blood clot that can block a blood vessel © Tatiana Shepeleva | AdobeStock
Other risk factors include
- certain medications (such as the “birth control pill” or hormone replacement therapy),
- being overweight,
- smoking,
- pregnancy,
- cancers, and
- dehydration.
What symptoms occur with thrombosis?
Depending on where a blood clot is located, it can cause various problems. Some of these can even be life-threatening, such as blood clots in
- a cerebral artery: stroke,
- a coronary artery: heart attack,
- the lungs: pulmonary embolism,
- the legs: intermittent claudication—which is not life-threatening but is accompanied by severe pain.
If a thrombosis is detected early enough, it can usually be dissolved by administering special medications. If that is not possible, a thrombectomy—that is, the surgical removal of the thrombus—can be life-saving.
When should a thrombectomy be performed?
A thrombectomy is primarily considered as an emergency treatment for a severe stroke or heart attack. These situations are life-threatening for the patient and must be treated quickly. This means that the blocked vessels must be reopened as quickly as possible to prevent brain or heart tissue from dying.
During a thrombectomy, the thrombus—that is, the blood clot—is mechanically removed from the blood vessel.
This is particularly the case with very large blood clots measuring about one centimeter or longer. Thrombectomy is used particularly frequently in cases of stroke, especially in younger patients or in particularly severe cases. Rapid restoration of the necessary blood flow can prevent severe disabilities and death.
However, whether a thrombectomy is likely to be successful must be assessed on a case-by-case basis. The timing of treatment, for example, is crucial: The procedure must be performed within a few hours of a heart attack or stroke to prevent permanent damage. In addition, the area of the brain or heart that has already been damaged must not be too large.
In some cases, thrombectomy may also be used to treat a blocked leg vein.
How exactly is thrombectomy performed?
During a thrombectomy, a very thin catheter is inserted into the affected blood vessel through the groin or the arm. The doctor then uses the catheter to pierce the blood clot. An inflatable balloon is located at the tip of the catheter. As the catheter is withdrawn, this balloon can be inflated, thereby pulling the clot along with it.
This allows blood to flow freely again and supplies the affected areas of the body with oxygen.
Thrombectomy is usually performed under general anesthesia, though in some cases local anesthesia is used.
The procedure is routine in some medical specialties. Vascular surgeons, in particular, perform it very frequently on the arteries of the arms and legs.
In the arteries supplying the brain, however, this procedure is considered an emergency measure. It is performed only in specialized hospitals (mostly university hospitals).
A prerequisite for successful treatment is that specialists in
- high-quality imaging techniques and
- performing the surgery
are available around the clock. This method has become increasingly established in recent years, particularly in the treatment of stroke. As a result, many patients can be referred to specialized hospitals and departments of neuroradiology where a thrombectomy can be performed.
What are the risks associated with thrombectomy?
There are hardly any serious risks associated with thrombectomy. In rare cases, a blood vessel may be injured or a clot may be dislodged into the body. However, the consequences are barely noticeable to patients and can usually be resolved immediately.
However, if blood leaks into the surrounding brain tissue through a damaged blood vessel, there is a risk of additional damage.
Of course, there are also certain risks associated with the anesthesia and the procedure itself; however, in cases of life-threatening vascular occlusions, the medical benefits always outweigh the risks.
What does follow-up care involve after a thrombectomy?
After a successful thrombectomy, the symptoms of a heart attack or stroke often disappear very quickly.
Nevertheless, further treatment of the resulting complications is necessary. The administration of specific medications should reduce the risk of new clot formation as much as possible.
Doctors determine which forms of therapy, medications, and follow-up treatments are necessary on a case-by-case basis.
FAQs on Thrombectomy
What is a thrombectomy, and when is it used to treat a stroke?
Thrombectomy is the mechanical removal of a blood clot from a blocked blood vessel. It is primarily performed in cases of ischemic stroke, when a blood clot blocks blood flow to the brain. Patients with occlusions of the large and medium-sized cerebral arteries benefit in particular, because the blood clot in the brain can be removed quickly, preventing severe damage to brain tissue. Studies show that thrombectomy significantly improves stroke treatment—even within the extended time window of up to 24 hours after symptom onset.
How is mechanical thrombectomy performed, and through which catheter access is it carried out?
During mechanical thrombectomy, the physician inserts a thin catheter into the vascular system via the femoral artery or through the arm. Depending on the location and size of the clot, it is mechanically removed, often using a stent retriever or by suctioning the thrombus out with the catheter. The goal is to clear the vascular occlusion, restore blood flow, and quickly supply the brain with oxygen. The procedure is performed in specialized centers for neuroradiology or neurology and requires precise diagnostic imaging.
How does thrombectomy differ from pharmacological thrombolysis?
Thrombolysis dissolves a clot using medication, while thrombectomy mechanically removes the blood clot. Often, both procedures are combined because drug-based treatments can reach smaller clots, while large blood clots frequently block the artery and must be removed mechanically. The German Stroke Society and the German Society of Neurology recommend thrombectomy especially when the artery is completely blocked or when thrombolysis is insufficient.
What are the risks, and how safe is thrombectomy?
Thrombectomy is considered a safe procedure for the acute treatment of ischemic stroke. In rare cases, the catheter may damage the vessel wall or dislodge part of the clot. Even more rarely, changes in the vessel wall or bleeding into the brain tissue may occur. Nevertheless, in cases of severe stroke, the benefits clearly outweigh the risks, as thrombectomy can prevent brain damage and is a central component of modern stroke units.
Who decides whether to perform a thrombectomy?
The decision is made by specialized neuroradiologists or neurologists based on diagnostic imaging such as CT or MRI. Depending on the location and size of the clot, the time elapsed since the onset of symptoms, and the patient’s neurological status, a determination is made as to whether thrombectomy can be performed. Patients with severe symptoms, in particular, benefit when the clot is quickly removed mechanically.
What does follow-up care involve after a thrombectomy?
After a successful thrombectomy, neurological symptoms often resolve quickly. In the stroke unit, patients are monitored to ensure that blood flow remains stable and that no new clot forms. For secondary prevention, blood-thinning medications are used to prevent the arteries from becoming blocked again. Subsequently—depending on any remaining limitations—rehabilitation therapy is provided to support the restoration of function.
Can a thrombectomy also be used for other types of vascular occlusions?
Yes. In addition to stroke treatment, thrombectomy is also used for heart attacks, arterial occlusions in the legs, and, rarely, for venous thrombi. Especially when a blood vessel is completely blocked and blood flow must be restored urgently, mechanical removal of the clot can be life-saving.

About the medical author
Prof. Dr. med. Susanne Regus
Medical Author
Prof. Dr. med. Susanne Regus – medical author: expert articles, professional insights and medical expertise in the Leading Medicine Guide.
More about the medical author →Sources
- Kompaktwissen Gefäßchirurgie: Differenzierte Diagnostik und Therapie, Bernd Luther (Hrsg.), Springer, 2. Aufl. 2010.
- Operative und interventionelle Gefäßmedizin, Eike Sebastian Debus & Walter Gross-Fengels (Hrsg.), Springer, 2012.















