Diabetic retinopathy carries a risk of blindness. High blood sugar levels increase the risk of developing the condition and influence its severity.
For people with type 1 diabetes, the average time until retinopathy develops is five to ten years after the onset of diabetes. People with type 2 diabetes are already at risk at the time of diagnosis, as structural damage may already be present due to years of latent disease.
After 20 years, the risk of diabetic retinopathy among people with diabetes is about 90 percent. Overall, more than 30 percent of people with diabetes in Germany suffer from this complication.
Diabetic retinopathy develops without symptoms, so the patient is initially unaware of the condition.
Only when the retinopathy has affected the macula does a deterioration in vision become noticeable. In some cases, the deterioration in vision is also associated with vascular bleeding.
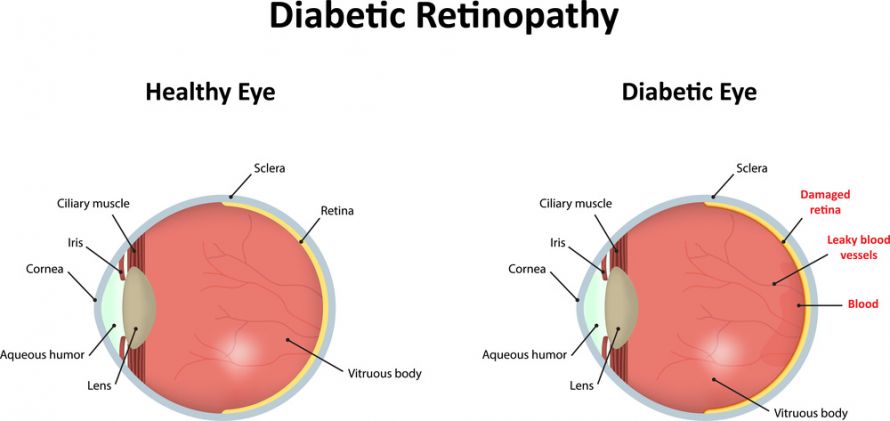 Comparison of a healthy eye and an eye with diabetic retinopathy @ joshya /AdobeStock
Experts distinguish between several forms of diabetic retinopathy. Fundamentally, they differentiate between nonproliferative and proliferative retinopathy. The difference lies in the fact that, in the proliferative form, the changes are limited to the retina. In the nonproliferative form, however, damage to the retina progresses. The transitions are gradual and typically follow a linear pattern. In all stages, swelling usually occurs in the area of the photoreceptor cells—a condition known as macular edema.
The nonproliferative form comprises four subgroups.
- Mild nonproliferative diabetic retinopathy
In diabetic retinopathy, at least one microaneurysm is present in the eye. Microaneurysms are small bulges in the damaged walls of capillaries. In the mild form of the disease, there is only a single microaneurysm.
- Moderate nonproliferative diabetic retinopathy
At this stage, there are already multiple microaneurysms with hemorrhages and lipid deposits in the blood vessels. In addition, isolated nerve fiber infarcts are already present.
- Severe nonproliferative diabetic retinopathy
In addition to the retinal changes already mentioned, a change in the vascular structure is evident here. It takes on a string-of-pearls appearance. There is a reduction in blood supply. The number of nerve fiber infarcts is significantly higher.
- Proliferative diabetic retinopathy
In the most severe stage of diabetic retinopathy, new blood vessels form in the retina. As the condition progresses, very thin-walled new blood vessels develop in the retina. Experts refer to this as severe proliferative diabetic retinopathy.
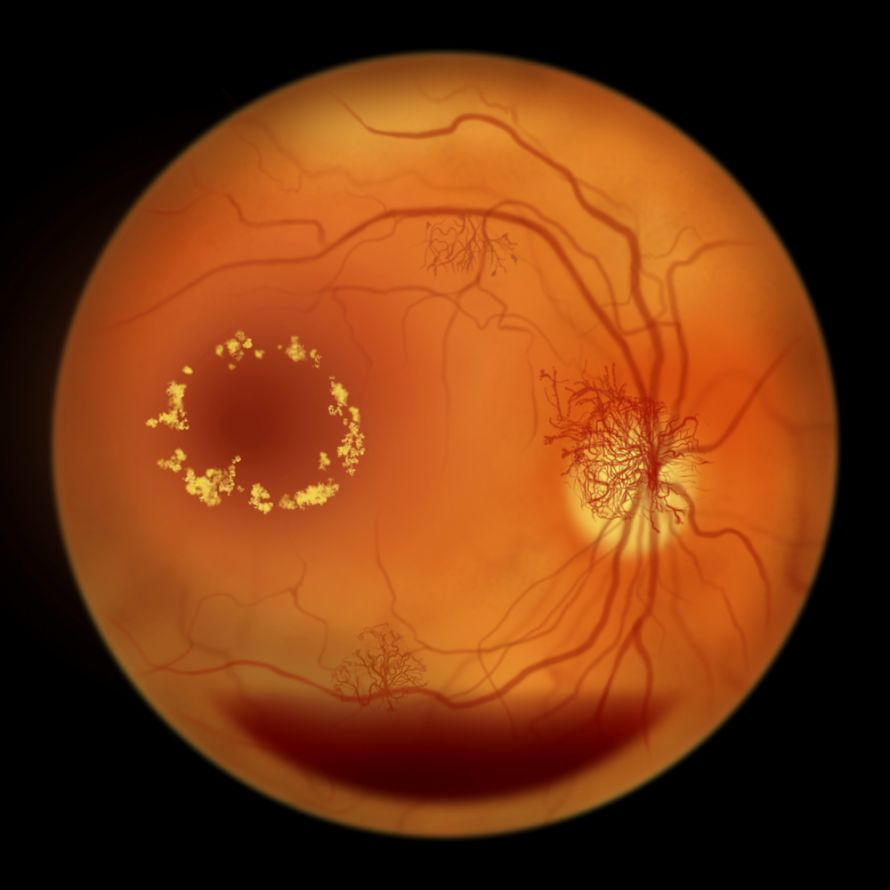 Eye with diabetic retinopathy after ophthalmoscopy @ Dr_Microbe /AdobeStock
The risk factors include those associated with diabetes.
High blood sugar levels and high blood pressure can lead to the formation of blood clots in the blood vessels. They also interfere with the proper delivery of oxygen to the retina. Due to a disturbance in lipid metabolism (hyperlipidemia), patients with type 2 diabetes have an increased risk of vision loss.
The following factors increase the risk of diabetic retinopathy:
- High blood pressure
- High blood sugar levels
- Tobacco use
- Sudden drops in blood sugar levels
- High cholesterol
- Hormonal fluctuations (especially during puberty)
- Hyperlipidemia
A diagnosis is made during an eye exam. Ophthalmologists can detect dangerous changes in the retina through a routine procedure.
During an ophthalmoscopy, the ophthalmologist first administers eye drops to dilate the pupils. The doctor then illuminates the eyes with an ophthalmoscope and magnifies the back of the eye with a magnifying lens.
To examine larger areas, indirect ophthalmoscopy is used. In this method, the ophthalmologist holds the ophthalmoscope at a greater distance. With lower magnification, this allows the doctor to examine wider areas of the fundus.
Diabetes patients must absolutely undergo regular examinations of the back of the eye. Only specialists have the necessary measuring equipment.
The ophthalmologist is able to detect and treat a predisposition to diabetic retinopathy at an early stage—even if the patient has no symptoms yet.
If the patient manages their diabetes responsibly, they can protect their retina. Diabetologists use blood glucose records to develop long-term treatment plans. The goal is to normalize blood glucose levels over time.
Therefore, patients should keep a record of their blood sugar levels and have them analyzed regularly by a specialist. Thorough preventive care can minimize fluctuations in blood sugar. This can delay damage to the retina.
Treating established diabetic retinopathy is challenging. Therefore, careful prevention of the disease is very important.
Nevertheless, treatment options are available. In cases of severe nonproliferative or proliferative diabetic retinopathy, ophthalmologists perform laser treatment (argon laser photocoagulation) on the retina.
This improves the oxygen supply to the affected area. The disease cannot progress, and blindness is therefore prevented.
In all other cases, however, it is not possible to halt the disease. Especially if doctors detect changes in the retina too late, laser treatment is no longer likely to be successful.
Therefore, if you have diabetes, you should see an ophthalmologist as soon as possible and have your fundus examined at least once a year.
The conclusion regarding diabetic retinopathy is that this form of the condition is a serious disease of the retina that develops gradually and often goes unnoticed for a long time. Nonproliferative retinopathy represents an early stage of the disease, while proliferative retinopathy is associated with the formation of new blood vessels and an increased risk of bleeding. As diabetic retinopathy progresses, it can lead to diabetic maculopathy, which particularly impairs central visual acuity.
An early eye exam and an examination of the fundus are crucial for detecting changes in the retinal blood vessels and the fundus in a timely manner. The earlier retinopathy is detected, the better the chances of preventing damage to the retina. Controlling HbA1c levels plays a particularly important role in patients with type 2 diabetes. The progression of diabetic retinopathy and maculopathy can be significantly slowed by maintaining good blood glucose control.
Modern procedures, such as laser treatment of the retina, are a central component of the treatment of retinal complications associated with diabetes. In advanced cases, particularly with proliferative diabetic retinopathy, bleeding into the retina or even into the vitreous body may occur. Damage to the central retina resulting in permanent vision loss is also possible. The impact on vision is therefore significant and, in the worst-case scenario, can lead to blindness.
In addition to diagnosis and treatment, the prevention and management of retinal complications also play an important role. Regular checkups at an eye clinic and collaboration with initiatives for the early detection of diabetic changes are advisable. Other eye diseases, such as glaucoma, may also occur and damage the optic nerves. Overall, signs of diabetes should be taken seriously, as damage to the central retina can result in permanent vision loss and permanently impair sharp vision.
What is diabetic retinopathy?
Diabetic retinopathy is a disease of the retina caused by diabetes. It involves damage to the blood vessels of the retina, which can lead to bleeding, deposits, and swelling. Without treatment, this eye disease can, in the worst-case scenario, lead to blindness.
What are the typical symptoms of diabetic retinopathy?
In the early stages, there are often no symptoms. As the disease progresses, vision may be impaired, leading to blurred vision, bleeding, or macular edema. Visual acuity, in particular, can decrease significantly.
How is diabetic retinopathy diagnosed?
The diagnosis is made through an ophthalmological examination of the back of the eye. This examination identifies changes in the retina, microaneurysms, and bleeding. Imaging techniques may also be used to supplement the diagnosis.
How is diabetic retinopathy treated?
Treatment depends on the stage of the disease. Laser treatment of the retina is often used to stabilize damaged blood vessels. In advanced cases, a vitrectomy may be necessary.
Can diabetic retinopathy be prevented?
Good blood sugar control is the most important factor in prevention. Regular checkups with an ophthalmologist help detect changes early on. A healthy lifestyle can also reduce the risk.



