
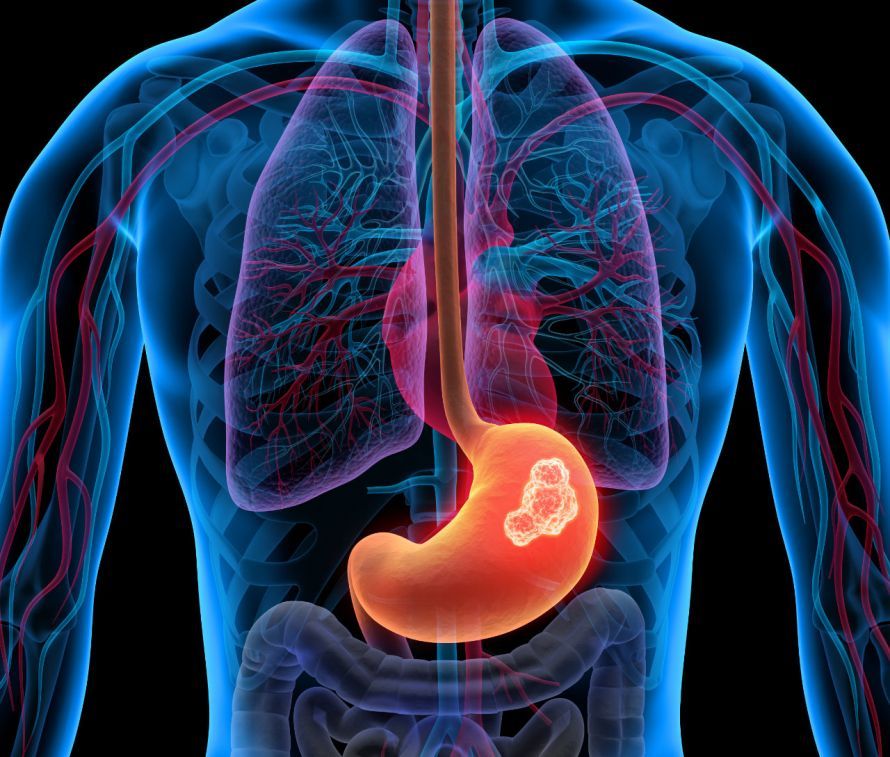
A gastrectomy is a surgical procedure to partially or completely remove the stomach. This procedure is primarily performed to treat a tumor, gastric cancer, or other serious stomach conditions. Depending on the findings, a total gastrectomy or a partial removal of the stomach may be necessary. The goal of the surgery is to completely remove the tumor and prevent it from spreading further.
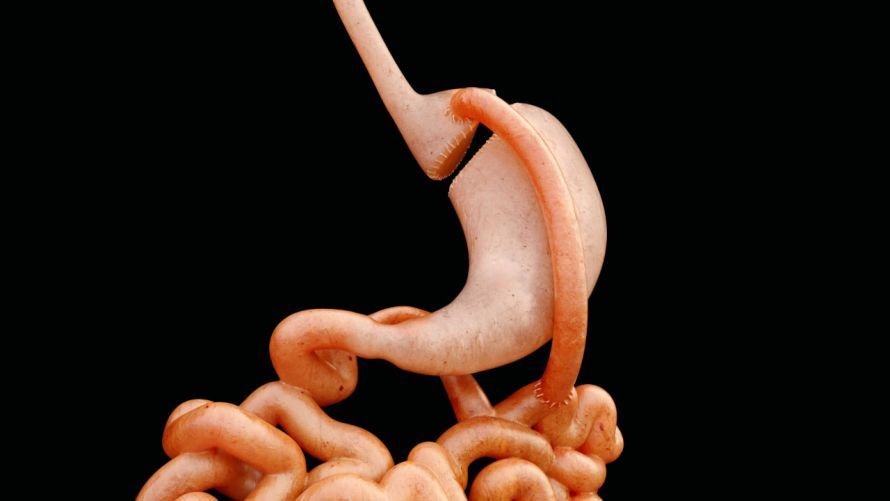
After gastric resection, the esophagus and small intestine are connected via an anastomosis. Gastrectomy can be performed as open surgery or laparoscopically. Modern techniques enable safe surgical treatment that is individually tailored to the patient’s condition. Careful postoperative care supports digestion and long-term quality of life.
What is a gastrectomy?
A gastrectomy is the total—or complete—removal of the stomach. This should be distinguished from a (subtotal) gastrectomy, in which only part of the stomach is removed. Today, total gastrectomy is performed almost exclusively for malignant stomach tumors (stomach cancer).
When exactly is a gastrectomy necessary?
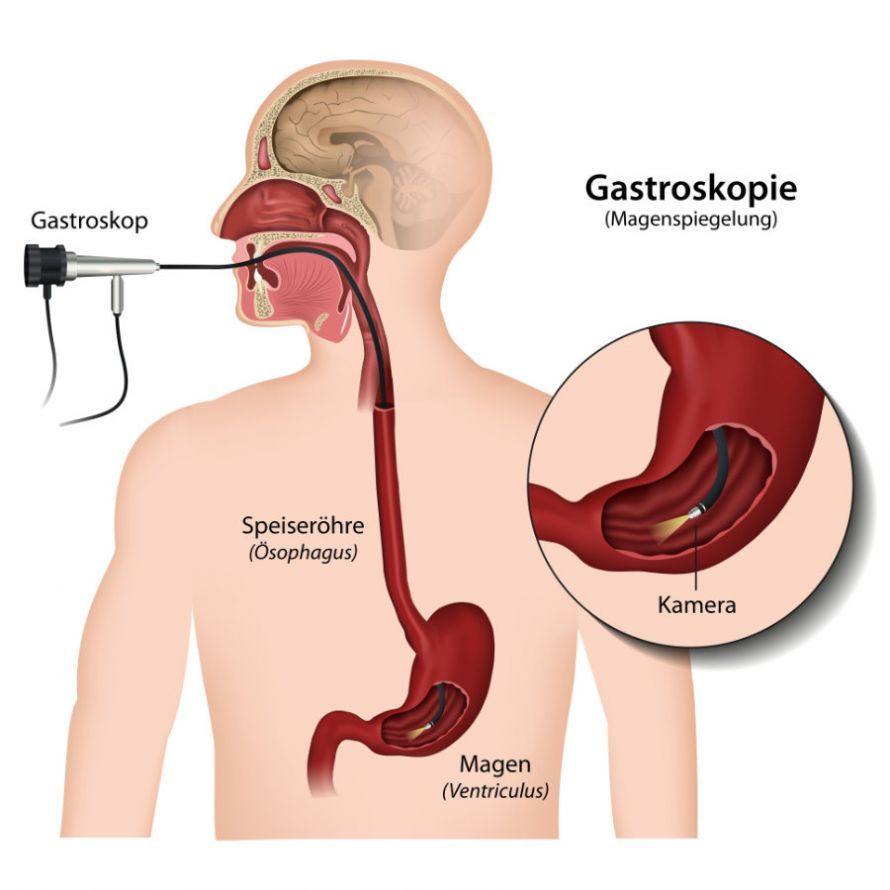
It is not necessary to remove the stomach entirely or partially in all cases of gastric carcinoma. Under certain conditions, tumor removal is possible via minimally invasive gastroscopy. For this to be possible, the gastric tumor must
- be confined to the mucosa or the outermost layer of the underlying tissue (submucosa) and
- be classified as a so-called “low-risk tumor” based on its biological activity. This means that it must have a slow growth rate and must not yet be very large.
In all other cases, gastric surgery is the only possible chance for a cure for this disease.
How can one determine whether a gastrectomy is necessary?
Before a treatment decision is made, tumor staging is first required. This involves assessing the local spread and, if applicable, metastasis (= spread throughout the body) of the carcinoma. Based on this, the tumor can be classified into a stage.
This is initially done via gastroscopy, during which the stomach is examined and the local extent of the carcinoma can be visualized. In addition, tissue samples can be taken. If the results indicate that the tumor is a so-called “low-risk tumor,” it can be removed during the gastroscopy. Ideally, no further surgeries will be necessary afterward. However, this is only possible in the very early stages of the tumor.
Other imaging techniques, such as ultrasound and computed tomography, provide additional information.
Depending on the findings from these examinations, several treatment options are available:
For “low-risk tumors” in the early stages, removal of the tumor via gastroscopy may be possible.
Primary surgery is indicated if
- the carcinoma is confined to the muscular layer of the stomach and
- there are no indications of affected lymph nodes.
Neoadjuvant therapy—that is, radio-chemotherapy prior to surgery—is indicated if
- the carcinoma has reached the outer layer of the stomach (serosa) and/or
- metastases are already present in the lymph nodes. This means that the tumor has already spread throughout the body.
Palliative therapy is indicated for
- very large tumors that cannot be surgically removed, as well as
- numerous distant metastases throughout the body and abdominal cavity (peritoneal carcinomatosis)
What exactly does “palliative” mean?
Gastric tumors that have already spread to other neighboring organs and have grown very large are medically incurable. In addition, tumors that have formed distant metastases are often no longer curable. Metastases can develop, for example, in the liver or the abdominal cavity. Nevertheless, such tumors can be treated to prolong life and improve quality of life. This is referred to as palliative therapy.
In these cases, drug therapy is usually indicated to slow the growth of cancer cells and treat pain. However, surgery is performed only in cases where the tumor obstructs the pylorus. The purpose of this surgery is to improve quality of life by maintaining the passage of food, not to remove the tumor tissue.
How are stomach tumors classified based on the results of the biopsy?
Based on the tumor’s location and the degree of tumor cell differentiation (Laurén classification), physicians determine whether
- a complete removal of the stomach, i.e., a gastrectomy, or
- a so-called subtotal gastrectomy, in which the upper part of the stomach is left in place,
offers the best chances of recovery.
For the so-called intestinal type according to Laurén, a safety margin of 5 cm superior to the tumor is sufficient. This means that when the tumor is removed, the tissue within a 5-cm radius around the tumor is also removed.
For tumors in the lower third of the stomach, a residual stomach can therefore be left in place. For tumors located higher up in the stomach, a total gastrectomy is necessary.
A complete gastrectomy is
- in the diffuse type according to Laurén and
- the so-called mixed type
.
What is the difference between open and minimally invasive surgery?
In principle, surgery for stomach cancer can be performed either open or via laparoscopy (abdominal endoscopy).
However, the equivalence of laparoscopic gastric resection—also known as minimally invasive surgery—to the open procedure has not yet been established. For this reason, most hospitals perform surgery for gastric cancer using the open technique.
If the minimally invasive approach is chosen nonetheless, care must be taken to ensure that the surgery is performed with the same degree of radicality.
What exactly happens during an open gastrectomy?
Tumor metastases in the abdominal cavity (peritoneal carcinomatosis) must first be ruled out via laparoscopy. Otherwise, surgical cure of the gastric tumor would not be possible, and the procedure would have to be canceled.
During the operation, the abdominal cavity is either opened transversely or accessed via a longitudinal incision. Next, the duodenum is transected just beyond the pylorus, and all lymph nodes are identified and removed. The extent of lymph node removal is critical to the patient’s prognosis. Therefore, the utmost attention is paid to lymph node removal (lymphadenectomy).
The lymph nodes around the liver, pancreas, spleen, and abdominal aorta are particularly important. They must be carefully identified and removed. During this dissection, the capsule of the pancreas is also removed.
Removal of the spleen itself is now recommended only for very extensive tumors. This may be particularly appropriate for tumors located along the greater curvature of the stomach and in the area of the gastric inlet. After transection of the left gastric artery, the dissection continues along the abdominal aorta and the diaphragmatic branches to the diaphragmatic hiatus. In this manner, the short gastric arteries, which connect to the splenic artery, are also transected.
The stomach is now suspended solely from the esophagus and is detached at this point. After transection of the esophagus, followed by a frozen-section histological examination to confirm the absence of tumor at the resection margin, intestinal continuity is restored.
How can intestinal continuity be restored?
The intestine must remain functional despite the (partial) removal of the stomach. This is referred to as intestinal continuity. There are two basic options for achieving this:
- Roux-en-Y reconstruction: Reconstruction that bypasses the duodenum; this is likely the most common form of reconstruction.
- Longmire reconstruction: Reconstruction that incorporates the duodenal passage.
There are no significant differences in quality of life between the two different reconstruction methods. Further modifications in restoring esophagogastric continuity include various forms of artificial stomach creation, the value of which is assessed differently.
What are the complications and risks associated with total gastrectomy?
Modern hemostasis procedures and dissection techniques are now highly advanced. Therefore, a blood transfusion during or after surgery is not necessarily required. Nevertheless, bleeding may occur during the operation—for example, in the event of injury to large blood vessels—or after the operation. In such cases, a second operation is often necessary to locate the source of the bleeding and stop it.
However, the most feared complication following a gastrectomy is what is known as anastomotic insufficiency. This refers to a leak in the suture at the junction between the esophagus and the small intestine. Treatment for this leak (also known medically as anastomotic leakage) can often be managed conservatively, but sometimes it necessitates repeat surgery.
Other possible complications include
- peritonitis,
- pneumonia, and
- a buildup of fluid between the lung and the pleura, known as a pleural effusion.
What are the dietary recommendations after a gastrectomy?
With all reconstructive procedures, the patient can no longer consume large amounts of food at one time after surgery. Instead, they must eat smaller portions several times a day.
The only nutrient that can no longer be absorbed after a total gastrectomy is vitamin B12. Regular supplementation via injection every 8–12 weeks is required. If diarrhea occurs, supplemental pancreatic enzymes may be beneficial.
Many patients continue to lose weight for about half a year after a total gastrectomy. After that, the body adjusts to the new situation. During this time, weight loss can be counteracted with so-called liquid nutritional solutions. These solutions provide easily digestible, high-calorie nutrition without placing a significant burden on the digestive tract. However, the amount consumed must be limited; excessive intake can lead to nausea, vomiting, and diarrhea.
What is the prognosis after stomach cancer surgery?
Overall, the 5-year survival rates for gastric cancer depend heavily on the stage of the disease.
For example, the chance of cure for a carcinoma confined to the stomach lining is well over 90%.
In contrast, for advanced gastric cancer, the 5-year survival rate ranges between 30 and 40%. Of particular importance here is the ratio of the number of lymph nodes removed to the number of affected lymph nodes.
What does follow-up care look like after surgery for gastric cancer?
Close-monitored tumor follow-up is not recommended for gastric cancer, as treatment options are very limited once metastases occur. For this reason, so-called symptom-oriented follow-up is preferred.
Nevertheless, regular blood tests and ultrasound examinations should be performed. Regular visits to the primary care physician can also provide timely relief for nutritional disorders, which are not uncommon in the early period following gastrectomy. In some cases, targeted supplementation of nutrients and vitamins is necessary and can restore quality of life.
Conclusion
Gastrectomy is an established procedure for treating stomach diseases and is performed either as a partial removal of the stomach or as a complete removal of the stomach. The exact indication depends on the location and extent of the disease in the stomach. Depending on the findings, a partial resection or, in the most extensive form, a total gastrectomy is performed. The goal of surgical removal is to completely remove the tumor and minimize the risk of residual cancer cells remaining in the body.
During the operation, affected structures are resected, supplemented by a lymphadenectomy if necessary, and reconnected via an anastomosis. After transection of the stomach, duodenum, or esophagus, the small intestine is reconnected, often using a jejunal loop and various looping techniques. In certain situations, a Billroth II resection may be performed, in which a section is blindly closed off. The reconstruction may additionally include a foot-point anastomosis and a drainage loop.
The surgery can be performed open via an upper abdominal laparotomy or laparotomy, or laparoscopically through small incisions. During the procedure, surgeons pay close attention to the blood supply to important structures such as the gastric artery, celiac trunk, pancreas, and pancreatic head. Anatomical areas such as the omental bursa, lesser omentum, antrum, and the region of the esophagogastric junction are also taken into account. In the case of a partial resection, a portion of the stomach may be preserved under certain circumstances.
Risks and complications include bleeding, infections, and potential complications such as anastomotic leakage. Additional surgical risks relate to digestion, as the stomach’s reservoir function is limited or lost following resection. Early dumping syndrome and late dumping syndrome are among the known consequences of a gastrectomy. In addition, the loss of the gastric mucosa, mucus, and intrinsic factor may necessitate lifelong supplementation of certain nutrients.
FAQ
What is a gastrectomy?
A gastrectomy is a surgical procedure in which the stomach is partially or completely removed. A total gastrectomy involves the complete removal of the stomach, while a partial gastrectomy removes only a portion of the stomach. This surgical procedure is primarily performed to treat a tumor or gastric carcinoma.
When is a gastrectomy performed?
A gastrectomy is performed for malignant conditions such as gastric cancer, as well as for certain benign conditions. The indication depends on the size, location, and extent of the tumor. The goal is surgical removal with an adequate safety margin.
How is the surgery performed?
During a gastrectomy, the stomach, affected lymph nodes, and, if necessary, adjacent structures are resected. After transection of the esophagus, duodenum, or jejunum, the passage of food is restored via an anastomosis. Depending on the findings, the surgery may be performed as open surgery via an upper abdominal laparotomy or laparoscopically through small incisions.
What are the risks and complications?
Risks and complications include bleeding, infections, anastomotic leakage, and digestive disorders. Other possible complications include early dumping syndrome, late dumping syndrome, or vitamin B12 deficiency due to the lack of intrinsic factor. Careful postoperative care reduces surgical risks and supports recovery.
How does life change after a gastrectomy?
After a complete gastrectomy, the small intestine partially takes over the function of food passage. The stomach’s reservoir function is lost, which is why eating several small meals throughout the day is usually recommended. Regular checkups, vitamin B12 supplementation, and an adjusted diet help maintain quality of life in the long term.

















