
Hepatitis refers to inflammation of the liver.
In Germany alone, an estimated two million people suffer from chronic liver disease. Cirrhosis (scarring of the liver) is one of the four leading causes of death among adults aged 30 to 50. In addition to alcohol, the main causes of chronic liver disease are viral hepatitis B and C.
In Germany, 30 to 40% of viral hepatitis cases are caused by the hepatitis B virus. About 0.5% of the German population are carriers of the hepatitis B virus, meaning they are infectious. Several thousand new hepatitis B infections occur in Germany each year.
According to WHO estimates, 300 to 420 million people worldwide are infected with chronic hepatitis B. Approximately one million people die each year as a result of this disease.
The Liver
Weighing about 1,500 g, the liver is the largest internal organ in the human body. It is located in the upper right abdomen and is surrounded by a connective-tissue capsule.
The liver is the body’s central metabolic organ. Its functions include breaking down toxins before they enter the systemic circulation. Toxins enter the body through the intestines. Nutrients that reach the liver via the intestines are also processed there.
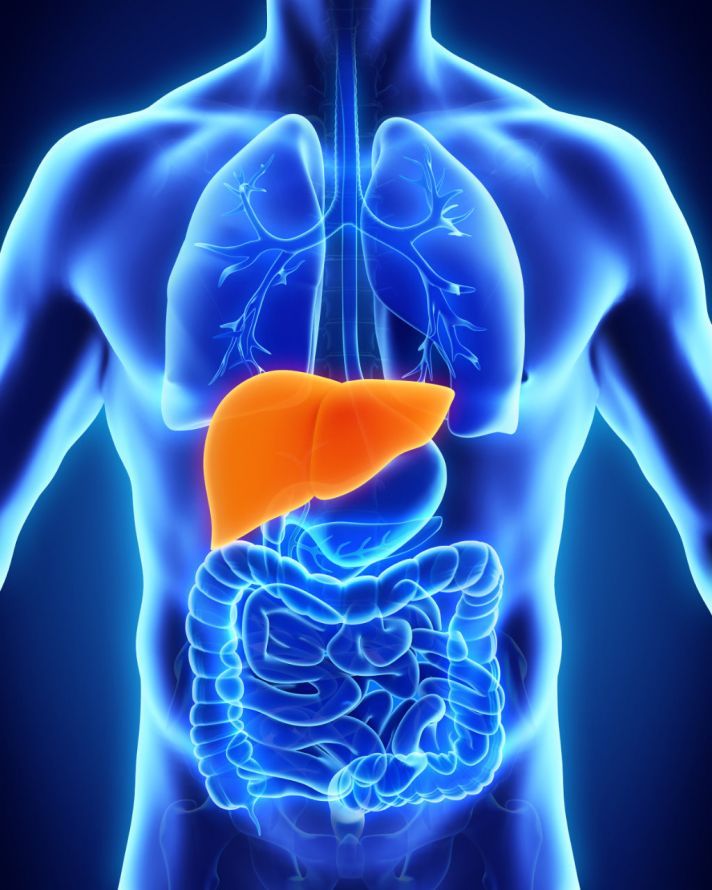
In addition, the liver produces important proteins that are necessary, for example, for blood clotting and the body’s defense against infections. Another important function is the production of bile, which is transported to the duodenum via a specialized duct system. Bile helps eliminate breakdown products of red blood cells and facilitates the digestion of fats. Various toxins are also excreted from the body along with the bile.
The liver itself has no nerve fibers capable of transmitting pain. However, if the liver swells or becomes scarred due to inflammatory processes, pain can result from tension in the connective tissue capsule.
Definition: What is viral hepatitis B?
Hepatitis B infection is an infection of the liver caused by the hepatitis B virus (HBV). In most patients (over 90%), the body is able to clear the infection on its own following an acute phase. It is not uncommon for affected patients to be completely unaware of the viral infection.
However, in less than 10% of infected patients, the body’s immune system is unable to successfully fight off the virus. If the disease persists for more than six months, it is referred to as chronic hepatitis B.
The clinical course of chronic hepatitis B depends
- on the viral load in the body and
- the strength of the patient’s immune response.
In chronic hepatitis B, there are forms of the disease in which
- only a small number of viruses are produced (low-replicative form of chronic hepatitis B) and
- others in which a very large number of viruses are produced (high-replicative form).
In low-replicative chronic hepatitis B, the disease does not typically progress rapidly. In most cases, patients have normal liver function test results. In these patients, the HBs antigen can be detected, but the HBe antigen is generally not detectable in the blood.
In high-replicative chronic hepatitis B, more than 100,000 viral copies per mL of blood can be detected (this corresponds to approximately 20,000 IU/mL). In addition to the HBs antigen, the HBe antigen may be detectable. However, in many patients (approximately 50%) with a highly replicative form of chronic hepatitis B, the HBe antigen is not detectable.
Blood tests can be used to determine which form of chronic hepatitis B a particular patient has. The doctor can use
- the antigens and antibodies present in the blood,
- the amount of virus in the blood (viral load),
- transaminase levels, and
- a histological examination of the liver tissue
to form an accurate picture of their patient’s infection.
Pathogenesis of Hepatitis B
In a chronic infection, the hepatitis viruses continuously infect new liver cells. The infected liver cells die and are replaced by new liver cells.
As a sign of inflammation, white blood cells migrate into the liver tissue. They ensure that infected and dead liver cells are destroyed and cleared away. However, they are generally unable to eliminate the virus itself. The dead liver cells may later be replaced by connective tissue (= scar tissue).
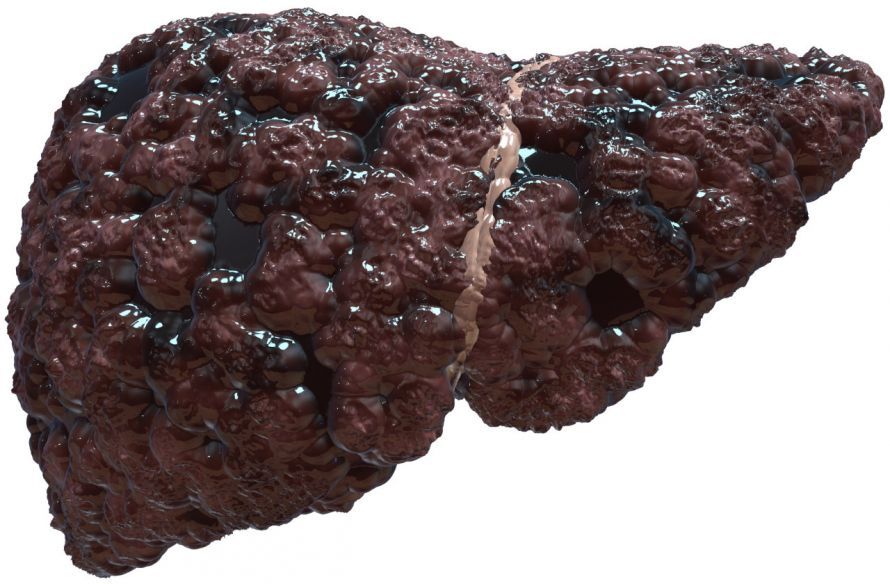
If the liver undergoes changes involving connective tissue, the condition is referred to as liver fibrosis in the early stages and, later, as liver cirrhosis. Connective tissue can be broken down again, at least partially—if chronic hepatitis B is successfully treated.
Infection with the hepatitis B virus
The hepatitis B virus is most commonly transmitted through infected blood, sexually, or during childbirth. The hepatitis B virus is much more contagious than, for example, the AIDS virus (HIV) or the hepatitis C virus.
The hepatitis B virus is transmitted only from person to person.
Sexual transmission
Unlike the hepatitis C virus, sexual transmission of the hepatitis B virus is common. Patients in whom the virus can be detected in the blood should use condoms to protect their partners.
However, transmission may also occur through saliva and other bodily fluids. Therefore, it is important for sexual partners to be vaccinated.
Transmission through blood
The hepatitis B virus can be transmitted through blood or blood products. The modern tests used today to screen blood are highly sensitive. As a result, the risk is now very low.
In addition, the virus can also be transmitted through contaminated syringes or needles. Risk factors for infection with the hepatitis B virus therefore include the use of
- drugs,
- tattoos, or
- body piercings.
The hepatitis B virus can also be transmitted through
- open wounds,
- razor blades, or
- toothbrushes
is possible.
Infection of Newborns
The risk of a newborn becoming infected by an infected mother is highest during or shortly after birth. The risk of viral transmission during delivery ranges from
- 10% (low-replicating chronic hepatitis B) and
- nearly 100% (high-replicative chronic hepatitis B).
Therefore, the newborn must always receive active and passive immunoprophylaxis immediately after birth. The newborn is therefore given both a vaccination and immunoglobulin at the same time.
Whether a hepatitis B infection can be transmitted through breastfeeding remains a matter of debate. There appears to be a correlation between the likelihood of viral transmission during breastfeeding and the mother’s viral load.
Complications of Hepatitis B
Liver Cirrhosis
Patients with chronic hepatitis B have a significantly increased risk of developing liver cirrhosis in the following decades. The risk of developing liver cirrhosis depends, among other things, on disease activity and duration of the disease.
Factors that can further accelerate the development of liver cirrhosis include additional chronic liver diseases, e.g.,
- other hepatitis viruses (e.g., a concurrent infection with the hepatitis C virus) or
- substances that damage the liver. Alcohol is the primary culprit here.
Liver cirrhosis is diagnosed when a large portion of the liver tissue has been replaced by connective tissue. This destroys the normal structure of the liver tissue.
Blood Flow
This leads to changes in blood flow that can result in high blood pressure in the portal vein. The portal vein is the vein connecting the intestines to the liver. A backup of blood can lead to the formation of dilated veins (varices) in the esophagus and stomach.
If these vessels rupture, severe gastrointestinal bleeding can occur. The risk of bleeding is exacerbated by the fact that the blood’s ability to clot is impaired by the disease. This is due to reduced protein synthesis in the liver and a decrease in the number of blood platelets (thrombocytes).
Partly due to high blood pressure upstream of the liver, fluid may also accumulate in the abdominal cavity (ascites).
Toxins and Metabolism
As liver cirrhosis progresses, the liver no longer functions properly. It is sometimes unable to break down the toxins that enter the bloodstream from the gastrointestinal tract. As a result, these toxins enter the systemic circulation, where they can lead to increased fatigue and difficulty concentrating. This condition is also known as hepatic encephalopathy (encephalon = brain).
Due to reduced protein production, there is also a deficiency in substances needed for the body’s immune defense. The result is an increased susceptibility to infections.
Further Complications
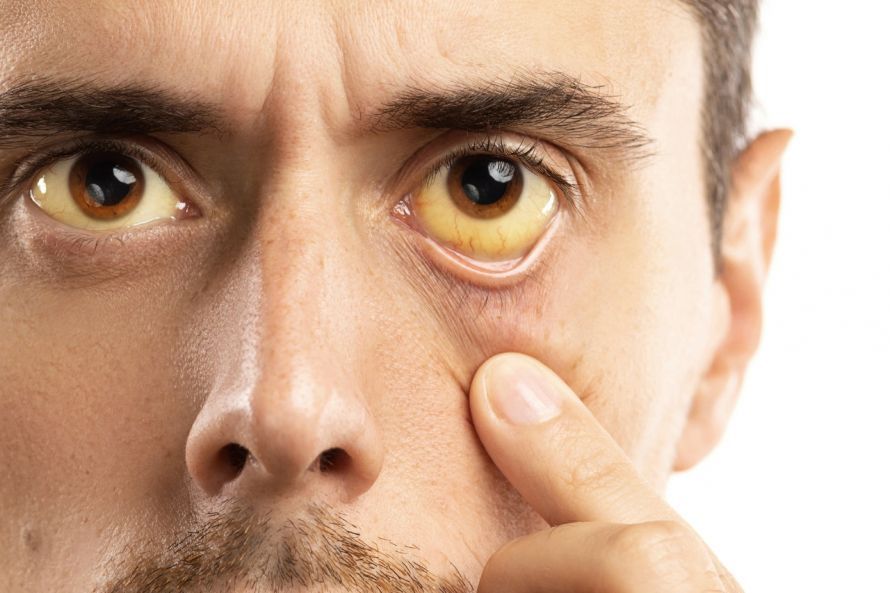
In severe liver disease, the backup of bile often causes yellowing of the eyes and skin (jaundice). This is often accompanied by itching. At the same time, the urine may become dark in color.
After a long course of the disease, chronic hepatitis B also increases the risk of developing liver cancer (hepatocellular carcinoma). Patients with a high viral load (HBV-DNA) are at particularly high risk. In most patients, hepatocellular carcinoma develops on the basis of liver cirrhosis.
Even for patients with a low-replicative form of chronic hepatitis B, the risk of developing hepatocellular carcinoma is elevated. Therefore, regular ultrasound and blood tests are necessary for these patients as well.
In some cases, chronic hepatitis B progresses to such a severe stage that a liver transplant may be necessary.
Hepatitis D
Hepatitis D is another viral disease of the liver. It is caused by the hepatitis D virus. Only patients who also have hepatitis B are at risk for hepatitis D. This is because the hepatitis D virus requires certain proteins from the hepatitis B virus to replicate. Without these proteins, the virus cannot replicate.
The hepatitis D virus can cause more severe liver inflammation than a chronic infection with the hepatitis B virus alone.
The hepatitis D virus is found primarily in southern regions (Mediterranean countries, South America, Africa). If you have chronic hepatitis B, you should consult your doctor to find out how you can protect yourself against the hepatitis D virus. In general, you should avoid traveling to areas with a high incidence of hepatitis D virus infections whenever possible.
Symptoms of Hepatitis B
The incubation period—that is, the time between infection and the onset of the first symptoms—ranges from six weeks to four months. Some patients may now experience
- flu-like symptoms,
- joint pain, and
- fatigue.
Only some patients develop the “typical” symptoms of severe liver disease, such as
- jaundice (icterus) with pale stools and brown urine, as well as
- upper abdominal discomfort.
About two-thirds of patients with acute hepatitis B experience few or no symptoms.
The symptoms of chronic hepatitis B are usually even less pronounced. Some patients experience increased fatigue or discomfort in the upper right abdomen. Many patients are unaware they have the disease.
Diagnosis of Hepatitis B
Blood tests as part of hepatitis B diagnosis
The diagnosis of hepatitis B is based on the testing for various antigens and antibodies. The most important tests are the detection of anti-HBc antibodies and the HBs antigen.
If the HBsAg test is positive, further tests should be conducted to determine the activity of the hepatitis. These include, on the one hand, testing for HBeAg and anti-HBe, and on the other hand, directly measuring the amount of viral DNA in the blood (viral load).
Liver function tests (GPT, GOT) provide limited information about the inflammatory activity of hepatitis. The activity of the disease and the connective tissue reaction in the liver can only be reliably assessed through a liver biopsy.
Non-invasive procedures, such as elastography, allow for an indirect assessment of the stage of fibrosis.
Patients with chronic hepatitis B are at higher risk of developing liver cancer. Therefore, alpha-fetoprotein (AFP), a tumor marker for hepatocellular carcinoma, should be measured every six months, and the liver should be examined by ultrasound.
Liver Biopsy (Liver Puncture) and Hepatitis B
A liver puncture is necessary to obtain important information about the severity of the disease prior to treatment. This includes, for example, the proportion of connective tissue fibers and the level of inflammatory activity in the liver.
During a liver puncture, a small tissue sample is removed under local anesthesia. This sample is examined microscopically (histologically). To assess the success of treatment, a follow-up liver biopsy may be advisable after treatment is completed.
Non-invasive methods (laboratory parameters, elastography) can predict the presence of liver cirrhosis with a high degree of certainty even without a liver biopsy.

Treatment of Chronic Hepatitis B
Treatment with Antiviral Drugs
In recent years, numerous substances that can directly inhibit viral replication (antiviral drugs) have been tested. Treatment for chronic hepatitis B generally does not result in the complete elimination of the virus from the body. In some patients, a highly replicative form of the disease can be permanently converted into a low-replicative form.
However, the majority of patients require long-term—and in some cases, lifelong—treatment to prevent the disease from progressing. For this reason, it is particularly important to carefully discuss the need for treatment and treatment goals with your doctor after diagnosis.
Treatment is generally always necessary
- in cases of severe liver inflammation and elevated liver enzyme levels,
- significant connective tissue reactions in the liver, and
- a high HBV DNA concentration (viral load) in the blood.
Viral replication and the activity of chronic hepatitis B can be inhibited with the following medications:
- Lamivudine,
- telbivudine,
- entecavir,
- adefovir or tenofovir.
These substances are classified as nucleoside or nucleotide analogs.
When is treatment with nucleos(t)ide analogs administered?
In general, all patients with chronic hepatitis B can be treated with these substances. Patients for whom interferon therapy does not offer sufficient chances of long-term success also respond to this treatment.
In addition, patients
- in whom treatment with interferon alfa has not been successful, or
- who cannot receive interferon alfa due to another underlying condition (e.g., immunodeficiency, post-transplant, HIV infection, etc.)
can be treated with nucleos(t)ide analogs.
Lamivudine, telbivudine, entecavir, adefovir, and tenofovir are taken as tablets. The dosage is as follows:
- Lamivudine: 100 mg per day,
- Adefovir: 10 mg per day,
- Entecavir: 0.5–1.0 mg per day,
- Telbivudine: 600 mg per day,
- Tenofovir: 245 mg per day.
Side Effects of Nucleos(t)ide Analogs
Unlike interferon therapy, side effects are very rare with nucleos(t)ide analog therapy.
Possible side effects include
- headaches,
- fever,
- skin rash,
- a general feeling of being unwell,
- gastrointestinal symptoms,
- insomnia,
- cough, and
- in some cases, pancreatitis.

A general feeling of being unwell is one of the side effects of treatment with nucleos(t)ide analogs © Justlight | AdobeStock
During treatment with adefovir and tenofovir, kidney function should be monitored regularly.
When using lamivudine, resistance to the drugs develops more frequently and more rapidly compared to other medications.
Fortunately,
- lamivudine- and telbivudine-resistant hepatitis B viruses respond to adefovir or tenofovir, and conversely,
- Adefovir-resistant viruses respond to lamivudine, telbivudine, and entecavir.
Tenofovir-resistant viruses have not yet been observed clinically.
If resistance develops, it is essential to take two suitable (non-“cross-resistant”) medications together (combination therapy).
Patients who do not respond adequately to the medication can be given a suitable second drug at an early stage. This helps prevent the development of resistance.
Therapy with (pegylated) interferon alfa
Interferon alfa is a protein produced naturally by the body, including by white blood cells. This occurs particularly when the body needs to defend itself against infectious agents.
The interferon alfa used to treat chronic hepatitis is produced biotechnologically. Interferon alfa must be injected into the subcutaneous fatty tissue. Newer interferons have a longer duration of action and need to be injected only once a week (so-called pegylated interferons).
How is treatment administered?
Currently, the long-acting pegylated interferons are administered at a dosage of
- 180 µg/week (Peg-Interferon alfa-2a) or
- 50–100 µg/week (Peg-Interferon alfa-2b)
. In Germany, Peg-Interferon alfa-2a is approved for the treatment of chronic hepatitis B.
Treatment with pegylated interferon should last 48 weeks. The response rate to pegylated interferon therapy for chronic hepatitis B is 30–35% of patients. These figures apply to patients in whom the HBe antigen has been detected.
In other patients, such as those infected with a variant of the hepatitis B virus (the so-called HBeAg-negative mutant), the sustained response rate to pegylated interferon therapy is 20%.
The goal of therapy is to inhibit viral replication. Thus, highly replicative chronic hepatitis B is converted into low-replicative chronic hepatitis B.
In the best-case scenario (which is rare), the HBs antigen may no longer be detectable after treatment with pegylated interferon, which is equivalent to a cure.
Side Effects of Pegylated Interferon alfa
Side effects of interferon alfa are common at the start of treatment and generally subside significantly as treatment progresses.
The most common side effects are flu-like symptoms
- such as fever, headache, joint and muscle pain,
- fatigue,
- loss of appetite, and weight loss.
Occasionally, thyroid dysfunction may also occur. Some patients experience temporary hair loss during therapy. Mood changes, including depression, may also occur.
Also important are changes in blood counts, which primarily affect white blood cells. Pegylated interferons have the same range of side effects as standard interferons.

Combination Therapies
Initial studies on combination therapy with pegylated interferons plus nucleos(t)ide analogs (e.g., lamivudine) yielded disappointing results. These treatments failed to improve sustained virologic response rates.
The combination of two antiviral drugs (e.g., lamivudine plus adefovir) is no more effective than either drug alone. However, it may be useful to prevent the development of resistance in at-risk patients (e.g., before and after liver transplantation).
Once resistance has developed, combination therapy is essential.
Diet for Hepatitis B
As long as liver function is not impaired, the patient does not need to follow a special diet. If liver function is impaired, the patient should consume less protein (meat, dairy products) and salt. Your doctor, possibly in consultation with a nutritionist, should discuss this with you. It is important that you avoid alcohol.
Hepatitis B Vaccination
Vaccination against hepatitis B is available. For several years now, it has been one of the vaccinations recommended by the Standing Committee on Vaccination (STIKO) for
- infants,
- toddlers, and
- adolescents between the ages of 11 and 15.
For these age groups, the costs are covered by health insurance plans.
Other groups of people who should get vaccinated against hepatitis B include
- people at particular risk of infection due to their occupation (medical and dental professionals, police officers, first responders),
- dialysis patients,
- all patients with other chronic liver diseases (e.g., chronic hepatitis C),
- people in close contact with patients with chronic hepatitis B, and
- newborns of infected mothers.
Three doses of the vaccine are required for adequate protection. Afterward, over 90% of vaccinated individuals are protected against infection.
For more information on hepatitis B, please visit the website of Deutsche Leberhilfe e.V.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →







