
Rheumatoid arthritis, also known as chronic polyarthritis, is often equated with rheumatism. While polyarthritis is the most significant, it is not the only inflammatory rheumatic disease. The small joints of the hands and feet, as well as the large joints of the upper and lower extremities, can be affected. Rheumatoid arthritis most commonly occurs in women between the ages of 20 and 40.
Here you will find further information as well as a selection of specialists and centers for polyarthritis.
Definition and Prevalence of Rheumatoid Arthritis
This condition, known in German as polyarthritis, is the most common inflammatory joint disease.
The term “chronic polyarthritis” captures the most important characteristics of the disease:
- "chronic" refers to the long duration of the disease,
- “arthritis” means joint inflammation, and
- “poly” indicates that multiple joints are affected.
Internationally, polyarthritis is also known as rheumatoid arthritis. It is therefore a synonym for polyarthritis.
Rheumatoid arthritis is a chronic, inflammatory systemic disease. It originates in
- the synovial membrane,
- the tendon sheaths, and
- bursae
and leads to damage to the joints, tendons, and bones. The small joints of the hands and feet are just as vulnerable as the large joints of the upper and lower extremities. Severe disabilities can result in the final stage of this chronic disease.
The video shows the progression of the disease in the hip joint:
Worldwide, about 0.5 to 1 percent of all people suffer from rheumatoid arthritis. In Germany, there are an estimated 800,000 people with the disease, with women being affected about three times more often than men. The condition can occur at any age, but most commonly between the ages of 30 and 50.
The development of rheumatoid arthritis is an immunological process. It involves uncontrolled activity of the immune system, leading to chronic inflammation.
A genetically determined difference in the immune system’s responsiveness is likely a factor in rheumatoid arthritis.
Causes of Chronic Polyarthritis
Research has made significant progress in recent years toward understanding rheumatoid arthritis. Nevertheless, the cause of the disease remains unclear.
One possible explanation is a malfunction of the immune system: in this scenario, immune system cells attack the body’s own tissues (e.g., joint cartilage). For this reason, polyarthritis is classified as an autoimmune disease.
Infectious agents (viruses or bacteria) may also play a role at the onset of the disease. To date, there is no definitive evidence regarding this. It is also likely that a genetic predisposition is required, which, when combined with exposure to certain infectious agents, leads to the onset of the disease. This predisposition also influences the severity of polyarthritis.
Inflammatory tissue hormones (known as cytokines) also play an important role.
Research findings from recent years have opened up new possibilities for treating rheumatoid arthritis. They also offer hope for a better prognosis, even though the cause of the disease remains unknown.
Development of Chronic Polyarthritis
At the center of the disease process is the inflamed synovial membrane (pannus). The inflammatory growths of the synovial membrane overgrow the articular cartilage.
The persistent joint inflammation produces signaling molecules and enzymes that further damage the cartilage and accelerate wear and tear. The pannus can also grow into the bone and attack the cartilage from the edge of the joint.
The pannus and joint effusion are followed by painful movement disorders accompanied by muscle atrophy.
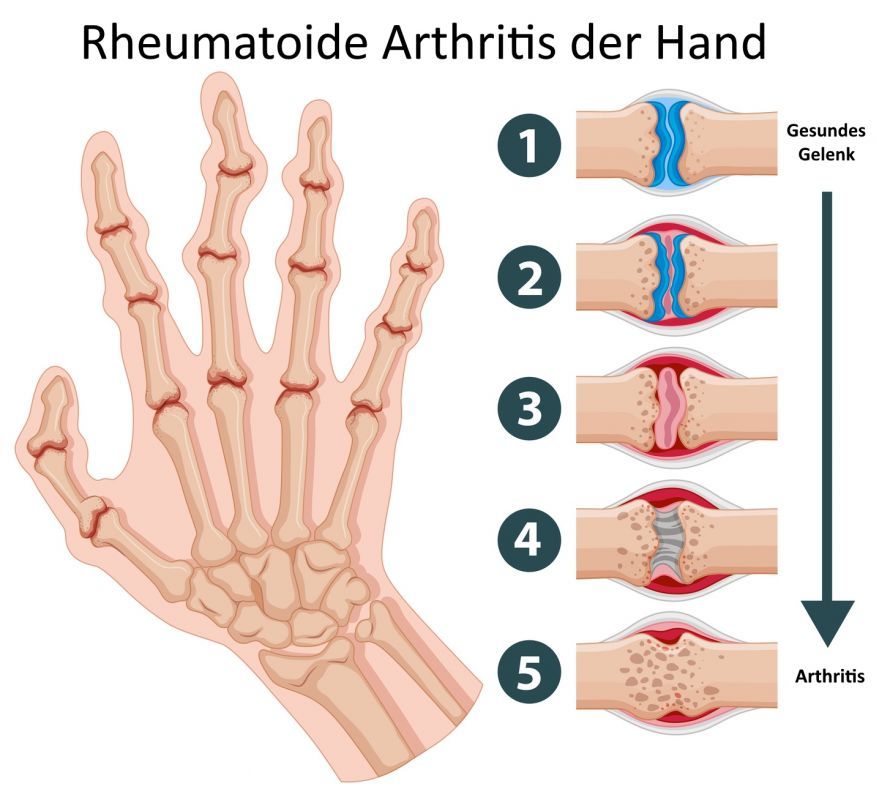
In later stages, the joint capsule becomes scarred, leading to increasing restriction of movement. Other courses of the disease involve progressive destruction of the cartilage and bone, sometimes resulting in severe joint deformities (mutilation).
The end result is a contracted, destroyed joint with
- severe deformation of the joint-forming bone segments,
- instability, or
- connective tissue stiffness.
The cartilage damage leads to secondary osteoarthritis. It can mask the clinical picture and, in advanced cases, even dominate it.
Pathways of joint destruction in rheumatoid arthritis (according to Mohr):
- Cartilage destruction via the synovial fluid
- Proliferating synovial tissue (pannus tissue, red) overgrows the cartilage and invades it, causing destruction
- Proliferating synovial tissue pushes its way between the cartilage and the bone
- Proliferating pannus tissue invades the bone marrow
- From the medullary cavity, pannus tissue spreads back to the cartilage
Acute symptoms of rheumatoid arthritis
Rheumatoid arthritis develops gradually or proceeds in flare-ups, with periods of apparent inactivity in between.
The early stage is characterized by
- symmetrical, spongy joint swelling (especially in the middle and distal joints of the fingers and toes)
- morning stiffness,
- warmth in the joints or swollen areas,
- and pain.
However, atypical cases involving acute involvement of large joints also occur. Rheumatoid nodules may develop on the extensor sides of the extremities.
The course of the disease is extremely varied. It ranges from occasional, flare-up-like joint symptoms to progressive joint disease and destruction.
A distinctive feature is the involvement of the synovial atlantoaxial joints. This can lead to displacement of the atlas relative to the cervical spine and result in damage to the spinal cord. This results in sensory and motor disturbances of varying severity.
In late stages, characteristic deformities develop. These include
- ulnar deviation of the long fingers,
- a prominent olecranon,
- swan-neck deformity and buttonhole deformity of the long fingers, as well as
- functional deficits due to tendon ruptures.
Progression of Rheumatoid Arthritis
Pain, swelling, and limited mobility are most pronounced in the morning. The stiffness upon waking is referred to as morning stiffness. Depending on the activity of the disease, this morning stiffness can last for several hours.
In addition to this typical onset of rheumatoid arthritis, occasionally only a few large joints are inflamed at first—often the shoulder joints in older adults.
Over the course of weeks or months, more and more joints may become affected. In addition to the joints, the tendon sheaths become inflamed and swollen (e.g., the extensor tendons on the back of the hand). The spine—usually the cervical spine—and bursae may also be affected, with bursae frequently involved at the elbow.
General symptoms such as
- fatigue,
- weakness,
- fever,
- night sweats, and
- possible weight loss
indicate that the entire body is involved in the inflammatory process.
A characteristic feature is the formation of so-called rheumatoid nodules in up to 20 percent of cases, particularly around the elbows and fingers.
The disease often progresses in flare-ups, meaning that for a period of time, certain joints become particularly painful. This is accompanied by a pronounced sense of illness.
Overall, the course of rheumatoid arthritis varies greatly. In about 10 percent of patients, the disease is expected to go into spontaneous remission (without treatment).
The defining characteristic of this disease is the attack by inflammatory cells and substanceson the joint cartilage and bone. If the inflammation goes unchecked, these joint structures are progressively broken down, and the joints are destroyed. The video illustrates the progression of joint damage.
In addition, in severe cases, other organs may be affected, such as
- the eyes,
- the heart and pericardium,
- the lungs and pleura,
- nerves, and
- blood vessels.
Diagnosis of Chronic Polyarthritis
An accurate diagnosis at an early stage is important for all rheumatic diseases. This allows the doctor to initiate effective treatment to prevent long-term damage.
Rheumatoid arthritis is diagnosed
- based on the symptoms of the disease and
- a rheumatological examination
. The doctor relies on recognized criteria. For example, the American College of Rheumatology (ACR) has established criteria. These help identify previously unexplained inflammation in multiple joints as rheumatoid arthritis. These include:
- morning joint stiffness,
- joint inflammation in three or more joint regions,
- inflammation of the finger joints,
- symmetrical involvement,
- rheumatoid nodules, rheumatoid factors, and
- typical X-ray changes.
Laboratory tests can identify rheumatoid factors and markers of inflammation. Rheumatoid factors are also found in other diseases, in which case they have no diagnostic significance. They therefore do not prove the presence of rheumatoid arthritis, but merely suggest it.
Laboratory findings are often nonspecific in the early stages. However, there is a persistent increase in inflammatory markers. Rheumatoid factors can be detected in 80 percent of cases. The CCP level is a much more accurate diagnostic indicator.
X-rays are necessary at the onset of the disease and throughout its course to assess the extent of bone damage.
Additional information about the soft tissues surrounding the joints is obtained via ultrasound, e.g.,
- joint effusion and
- inflammatorily thickened synovial membrane.
More complex imaging diagnostic procedures are used for specific clinical questions. These include, for example, magnetic resonance imaging (MRI) in cases of inflammation-related involvement of the cervical spine.
Treatment for Rheumatoid Arthritis
If the cause were known, the disease could be effectively treated or even cured with targeted causal therapy. Unfortunately, the cause of polyarthritis remains unclear to this day.
As a result, a wide range of therapeutic measures is often required. These aim to alleviate pain and reduce disease activity, as well as improve the prognosis.
The rheumatologist tailors the individual treatment measures to the patient’s specific clinical situation. Subsequently, the rheumatologist monitors the effectiveness of the treatment in collaboration with the patient’s primary care physician.
Drug Therapy for Chronic Polyarthritis
A range of medications is available for the treatment of chronic polyarthritis. There are various drug classes and a large number of medications with different profiles of efficacy and side effects. Therefore, special expertise is required when tailoring drug therapy.
The most important aspect is the use of so-called disease-modifying antirheumatic drugs (DMARDs). These can prevent the progression of the disease. Through the combined use of various disease-modifying antirheumatic drugs (so-called “combination therapy”) and the development of new medications, it is becoming possible for an increasing number of patients to halt the progression of the disease and improve their quality of life.
When it comes to drug therapy, physicians distinguish between basic therapy and symptomatic therapy:
Basic therapy has undergone a veritable revolution in recent years. New basic therapies, known as biologics, directly intervene at various points in the inflammatory process of the synovial membrane. But effective blocking agents (antibodies) can now also be used at other points in the inflammatory process. They can be deployed, for example, against interleukin-1 or against activated inflammatory cells.
The goal of this new biologic therapy is to achieve remission of the disease—that is, to bring the inflammation to a resting state. Cytostatic drugs such as methotrexate or azathioprine are also used.
For symptomatic treatment, nonsteroidal anti-inflammatory drugs (NSAIDs) such as ibuprofen and diclofenac, as well as corticosteroid preparations, are available. With all of these medications, attention must be paid to potential side effects. A well-known example is the consequences of long-term corticosteroid therapy.
Overview of Medication Therapy:
- Rheumatic pain relievers (so-called nonsteroidal anti-inflammatory drugs): help with inflammatory pain
- Cortisone: acts quickly on the inflammatory response (but is problematic in the long term due to side effects)
- Basic rheumatism medications: provide long-term relief from inflammation and joint damage
- Local therapeutic measures: cortisone injections into joints, chemical or nuclear medicine synovial sclerosis (ablation treatment of the inflamed synovial membrane)
Nutrition for Chronic Polyarthritis
Symptoms can also be alleviated through an appropriate diet. For example, a diet rich in calcium and vitamin D can help prevent osteoporosis (bone loss). Unfortunately, dietary changes cannot fundamentally alter the course of the disease.

Physical Therapy for Rheumatoid Arthritis
Physical therapy continues to play a significant role alongside medication.
It is important to ensure proper positioning and splinting of the affected limb at an early stage. This helps prevent contractures and joint deformities.
Physical therapy and occupational therapy for mobilization and muscle care play an equally important role. Heat treatments (compresses, baths, mud therapy) are primarily used intermittently and as part of a spa regimen. During a flare-up, patients generally tolerate cold therapy better.
Malalignments and contractures can be functionally treated with appropriate splints.
Surgical Treatments for Chronic Polyarthritis
Early surgical removal of the synovial membrane (synovialectomy), combined with removal of the inflammatory pannus, can improve the clinical picture and also slow further destruction of the affected joint.
Alternatively, or in combination with radiosynoviorthesis, the proliferation of synovial tissue can be inhibited using a radionuclide.
In addition to synovialectomy, a number of surgical reconstructive procedures may be considered:
- tendon replacement procedures,
- joint reconstructions,
- capsular tightening, and
- nerve releases
can improve the condition of destroyed joints, either individually or in combination. In some cases, they may also counteract the progression of joint destruction.
Joint replacement surgery is among the most successful surgical interventions for patients with rheumatic diseases. Artificial joints are now available for nearly all joints. The decision to perform the procedure is based primarily on the patient’s pain levels, but also on
- progressive destruction and
- functional deficits.
Patients with rheumatic diseases often suffer from damage to multiple joints, so a step-by-step treatment plan must be developed at a specialized clinic. This plan should exhaust all possibilities of conservative and surgical therapy.
An overview of important measures for chronic polyarthritis
- Physical therapy: to maintain joint function, muscle strength, and mobility
- Physical therapy: for pain relief, e.g., cold therapy, electrotherapy
- Occupational therapy: how to relieve pressure on my joints, how much weight I can put on them, and what assistive devices are available?
Additional measures include:
- Orthopedic therapy: orthotics, crutches, splints, surgical interventions (e.g., joint replacements)
- Psychological therapy: to help manage illness and pain
- Social and medical measures: job retention, retraining, rehabilitation
- Education and information play a key role in the success of therapy
Guidance on Coping with the Disease
Rheumatoid arthritis is a chronic condition. In addition to causing changes in the body’s joints and organs, it also takes a toll on one’s emotional well-being. Coping with daily pain and functional limitations, and having to give up activities that were once taken for granted, is not easy to handle.
Adjustments to daily life are necessary, both in terms of one’s professional and family situations. It is essential to seek help from others in order to cope with the disease in everyday life.
Patient education programs and information from
- books,
- information sheets, and
- the Internet
can help you adjust to your new life situation.
FAQ
What causes polyarthritis?
The exact causes are not yet fully understood. Possible factors under discussion include an immune system malfunction, genetic factors, environmental influences, and infectious agents, which together may trigger the onset of the disease.
How is polyarthritis diagnosed?
The diagnosis is based on typical symptoms, a rheumatological examination, blood test results (e.g., rheumatoid factors), and an X-ray to assess bone damage; ultrasound examinations of the soft tissues may also be used.
What medications help with polyarthritis?
In addition to traditional medications such as antirheumatic drugs and cortisone, modern biologics are used—biotechnologically produced active ingredients with targeted anti-inflammatory effects that directly intervene in the inflammatory process.
Can polyarthritis also affect young people?
Yes—one specific form is juvenile idiopathic arthritis, which occurs more frequently in children and adolescents and, like the adult form, can lead to permanent joint damage.
Share this article
About the medical author
Prof. Dr. med. Wolfgang Rüther
Medical Author
Prof. Dr. med. Wolfgang Ruether – author: Explore expert medical articles in the Leading Medicine Guide.
View full expert profile →






