
Expert Interviews
Prof. Dr. El Hindy in an Expert Interview on Intervertebral Disc Prostheses

Alexandra Pfitzmann ·
Prof. Dr. med. Nicolai El Hindy is Chief of the Department of Neurosurgery and Spinal Surgery at St. Marien Hospital Lünen and is one of Germany’s leading specialists in modern, high-precision spinal surgery. As a board-certified neurosurgeon with additional certification in specialized neurosurgical intensive care medicine, he combines extensive scientific expertise with innovative technology and many years of clinical experience. Prof. El Hindy places a special emphasis on robot-assisted spinal surgery.
Using the state-of-the-art ExcelsiusGPS® system, he is one of the pioneers of this minimally invasive procedure in Germany. This makes surgeries even more precise, safer, and gentler on patients. Prof. Dr. El Hindy is also setting new standards in the field of intervertebral disc replacement, a procedure that preserves mobility and quality of life. In addition to his specialization in spinal disorders, he also treats complex brain pathologies such as tumors, vascular malformations, and spontaneous hemorrhages—always with a patient-centered, individually tailored approach.
His commitment extends far beyond the operating room: Prof. Dr. El Hindy is an internationally sought-after speaker, trains colleagues worldwide in robot-assisted surgery, and actively supports the next generation of medical professionals through research projects and fellowships. He is a member of renowned professional societies such as the German Society for Neurosurgery and the German Spine Society, and he also contributes his expertise to international networks. At St. Marien Hospital Lünen, a hospital grounded in Christian values, Prof. Dr. El Hindy shapes the clinic’s culture by combining cutting-edge medicine, social responsibility, and a compassionate approach.
Here, patients benefit from interdisciplinary, high-quality care and the innovative spirit of a physician who consistently combines medical excellence with personal attention.
To preserve the spine’s natural mobility despite disc degeneration, a disc prosthesis can be implanted—the editorial team of the Leading Medicine Guide spoke with Prof. Dr. El Hindy about this.
Disc replacement is a modern procedure in spinal surgery that offers patients with severe disc damage an important alternative to traditional spinal fusion surgery. The goal of this innovative technique is to preserve the spine’s natural mobility, alleviate pain, and improve quality of life in the long term. The use of an artificial disc replaces the function of the worn-out or damaged disc, allowing patients to regain mobility more quickly and reducing the long-term risk of secondary damage to adjacent segments of the spine. Especially in carefully selected patients, intervertebral disc replacement offers an effective way to restore the spine to the best possible functional and anatomical condition.
Typical indications include chronic back pain resulting from isolated disc damage—either in the lumbar or cervical spine—while the stability of the surrounding spinal structures remains intact.
“Intervertebral disc prostheses can essentially be divided into two categories: those for the cervical spine and those for the lumbar spine. This distinction is important because both regions have different requirements for mobility—the cervical region, in particular, naturally has a high degree of mobility. Such a prosthesis is more suitable for patients whose degeneration has not yet progressed too far. After all, degeneration always entails a restriction of mobility. The body then often begins to stiffen on its own—for example, by forming bone spurs. Once this process has progressed too far, it is difficult or even impossible to restore mobility with a prosthesis. Generally speaking, prosthetics are geared more toward patients who are still mobile and active. These are often athletic people or those with a very active daily life—whether professionally or personally. There’s simply more to it than just the intervertebral disc itself—it also involves muscles, ligaments, and the entire system. And that’s exactly what often works particularly well for these patients,” explains Prof. Dr. El Hindy at the start of our conversation, adding regarding diagnostics:
“Imaging for patients with signs of wear and tear generally follows a standardized procedure. First, an MRI is usually performed—this is the most important method for even being able to assess which pathology underlies the symptoms. In addition, so-called functional imaging is used, which is quite common for degenerative conditions. During this process, the patient performs specific movements, such as tilting the head forward and backward in the cervical spine region or bending and extending in the lumbar spine region. These movements are captured in a lateral X-ray to determine whether there is still sufficient mobility in the area that may require surgery. Such images also provide clues as to whether a disc prosthesis is a viable option—or not. One exclusion criterion, for example, is spinal instability. This can be identified in the functional X-rays. If the vertebral bodies move during flexion and extension but remain stable on top of one another, this is generally a good sign. However, if one vertebra slips over another—for example, if the third lumbar vertebra slides significantly beyond the fourth during forward bending—this indicates instability. In such a case, a prosthesis would not be suitable.”
The long-term prognosis following a disc replacement procedure differs from that of traditional spinal fusion (spondylodesis) in several key respects. Fundamentally, the goal of intervertebral disc replacement is to preserve the mobility of the affected segment of the spine, whereas spondylodesis aims for complete fusion of the corresponding spinal segment.
“The central idea behind the use of a disc prosthesis is the preservation of mobility. This is precisely what distinguishes it from fusion surgery: the affected segment remains mobile. Studies and clinical experience show that this preservation of mobility leads to fewer problems in the adjacent segments of the spine over the long term—so-called adjacent-segment problems occur less frequently. Thus, mobility is not only preserved in the affected segment itself, but the adjacent areas are also spared, as they do not have to bear as much compensatory load. Of course, natural wear and tear continues to progress over the course of a person’s life—it cannot be completely stopped. However, a prosthesis interferes less with the spine’s biomechanical system than a fusion. Fusion surgeries are nevertheless unavoidable in some cases. They are often viewed negatively, but many patients—for example, after a single fusion—do not notice any significant difference in their daily lives. Problems usually arise only with very extensive fusions, such as those extending from the thoracic spine to the pelvis. However, these are rather rare exceptions. “In many cases, good long-term results can be achieved with a prosthesis—while maintaining a natural sense of movement,” explains Prof. Dr. El Hindy. 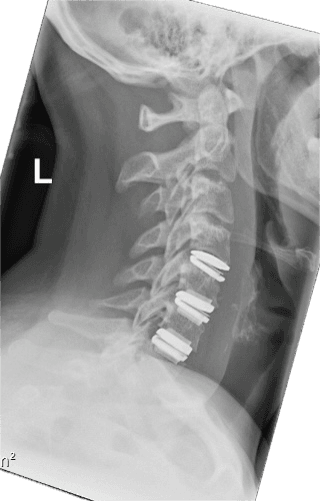
Modern intervertebral disc prostheses are highly sophisticated implants specifically designed to mimic the natural function and mobility of the human intervertebral disc as closely as possible. Both the choice of materials and the technical design play a decisive role in durability, biocompatibility, and mobility.
Prof. Dr. Hindy comments: “Intervertebral disc prostheses are made of materials that have proven themselves for decades in endoprosthetics—for example, in knee or hip joints.” The prosthesis typically consists of two titanium plates that are anchored at the top and bottom of the vertebral body. Titanium is particularly well-suited because it is readily accepted by the bone and integrates stably. Between the titanium plates lies a movable core made of polyethylene. This core functions similarly to a ball-and-socket joint and allows for the natural mobility of the spinal segment. The technique is well-established: the prosthesis models currently in use have been in clinical practice for about 30 years. During this time, extensive long-term studies have been conducted, confirming good outcomes. Durability tests also simulate several decades of use—as a rule, the implants are designed to last at least 40 years. In practice, it is evident that this durability is not merely theoretical. There are patients who have been living with such a prosthesis for 30 years—with consistently good function and preserved mobility in the corresponding segment. The intervertebral disc prosthesis is thus not only a modern but also a proven implant.”
Technically speaking, intervertebral disc prostheses are designed to allow movement in multiple directions: flexion and extension, lateral flexion, and rotation. This multidirectional mobility is crucial for maintaining the natural dynamics of the spine and preventing excessive strain on adjacent segments. Some prosthesis models are also designed to absorb shock in order to better mimic the natural distribution of pressure on the spine. 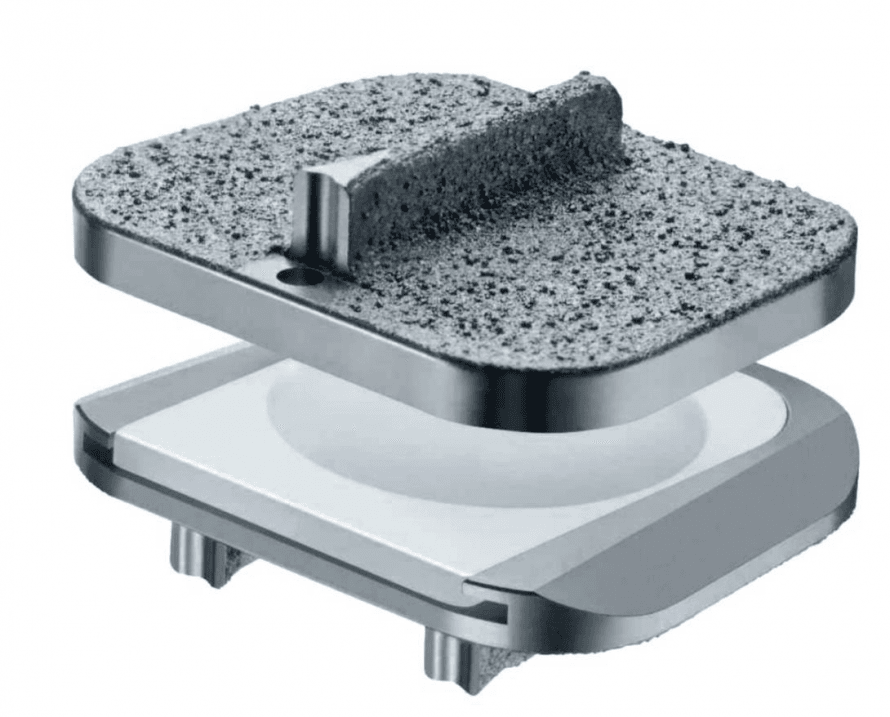
Although artificial disc replacement is a promising alternative to traditional spinal fusion (spondylodesis), it—like any surgical procedure on the spine—is associated with certain risks and potential complications.
General risks associated with intervertebral disc replacement include infections at the surgical site, bleeding, impaired wound healing, and injury to adjacent structures such as nerve roots, blood vessels, or the meninges. Thrombosis and embolism are also among the general perioperative risks. Specific complications related to the intervertebral disc prosthesis itself primarily concern the positioning and function of the implant. If the prosthesis is not placed precisely, it can lead to improper loading of the spine, misalignment, or unnatural movement patterns. As a result, pain may persist or even worsen. However, the use of modern techniques can significantly reduce many of these risks. These include minimally invasive surgical procedures that preserve the surrounding tissue as much as possible and enable a faster recovery. The high level of expertise of the treating physician is extremely important in this regard.
“During surgery to implant a disc prosthesis—especially in the cervical spine—the surgical approach is, in principle, identical to that of a traditional fusion procedure, which is still considered the gold standard in Germany. Nevertheless, prosthesis implantation differs significantly in its technical execution: It requires more experience and precision, as the goal is not only to remove the herniated disc causing pain but also to preserve the segment’s mobility. With prostheses in particular, the implant’s size and position must be exactly right. For example, if an implant that is too tall is used, it can lead to hyperextension of the posterior facet joints, which can result in new symptoms such as neck pain. Such problems occur less frequently with fusion procedures, since mobility is eliminated in those cases anyway. Selecting the appropriate implant is also crucial. There are many different models on the market that vary in height, width, mechanism, and material—some contain nickel, for example, which could be problematic for patients with allergies. For women, implants with a minimum height of 6 mm are often too tall. Stability also plays a role: Some prostheses require special anchoring techniques, such as keels that are driven into the bone and provide good primary stability from the outset. The prostheses must therefore be individually tailored to the patient’s anatomy and needs. This requires a wide selection of implants and extensive surgical experience. A prosthesis is not simply a “off-the-shelf” solution, but is carefully planned and selected. The actual surgery—for example, to place a prosthesis in a segment of the cervical spine—takes about an hour on average. However, success depends not only on the duration but also on precise preparation and execution down to the finest detail,” emphasizes Prof. Dr. El Hindy, adding:
“Patients who receive a disc prosthesis can usually return home relatively quickly. With surgery on the cervical spine, the greatest risk is postoperative bleeding, which could potentially constrict the trachea. Therefore, patients remain in the hospital for at least one night for observation. After this period, the risk of such complications has decreased significantly. From a medical standpoint, most patients could be discharged as early as the following day—as is common practice in some other countries. In Germany, however, economic factors mean that patients usually stay for three nights, because a shorter hospital stay would result in financial losses for the hospital. This regulation has not yet been changed as part of the hospital reform—which focuses more on the fundamental question of which hospitals are still permitted to perform certain procedures, rather than on the billing of hospital stays.”
Surgery on the lumbar spine is somewhat more complex. It usually takes about two hours and is performed through an incision in the abdomen. Accordingly, the average hospital stay is four to five days.
“Even though the incisions are small—about two centimeters in the neck area, five centimeters for a single-level procedure in the lumbar region, and seven to eight centimeters for a two-level procedure—the term ‘minimally invasive’ here refers primarily to the gentle approach: Instead of having to detach the muscles from the bone, as is done in procedures performed from the back, the anterior approach makes use of natural anatomical layers. The tissues are simply pushed aside. This spares the muscles and makes the procedure significantly more comfortable for the patient overall—especially with regard to postoperative mobility, for which functioning muscles are crucial. This anterior approach is by no means new, but it is becoming increasingly rare for surgeons to master it. This approach is technically challenging, particularly for surgeries on the lumbar spine, which is why vascular surgeons are often involved in other countries. In Germany, the spine team usually performs this procedure themselves. Of course, every patient is thoroughly informed about the procedure in advance—including potential risks, such as injuries to the trachea, esophagus, or the recurrent laryngeal nerve in the neck area. In abdominal surgery, the ureters, bladder, and other organs are located nearby. Such risks are extremely rare, but they are always discussed. Long-term studies show that these approaches are, on the whole, very safe,” explains Prof. Dr. El Hindy.
After surgery with a disc prosthesis, patience is required at first—even though patients usually feel well again relatively quickly in their daily lives. It is crucial that the prosthesis first fuses firmly with the bone. This process takes about three months. During this time, the spine must be protected to allow for a stable bond between the bone and the implant.
Prof. Dr. El Hindy recommends: “In the first four to six weeks after surgery, patients should largely avoid physical strain. Light walks, changing positions (sitting, lying down, standing), and basic isometric exercises (i.e., holding positions without major movements) are permitted—and are also offered as part of supervised physical therapy. However, exercising on machines or engaging in intense training is strictly prohibited during this phase. Rehabilitation typically does not begin immediately after surgery, but rather three months later—once the prosthesis has become firmly integrated. At that point, patients can begin targeted strength-building and mobility training to regain full functionality. A follow-up examination is also scheduled after about three months. During this checkup, the doctor verifies that the prosthesis is correctly positioned, has integrated well, and has not shifted. Only when this checkup shows no abnormalities are patients considered “cleared” for all activities. For people who are physically active, the required rest period varies depending on the sport. For sports involving sudden changes in movement or high impact—such as tennis, soccer, golf, or weightlifting—one should wait three to six months before resuming the activity. After that, a return to the previous level of activity is generally possible without any problems—many former patients resume their sports without restriction.”
Unlike in a fusion procedure (spondylodesis), in which two vertebral bodies are permanently fused together and lose their mobility, the dynamic function of the segment is largely preserved with the implantation of an intervertebral disc prosthesis. This mobility has a decisive influence on the distribution of stress throughout the entire spine.
The health of the intervertebral discs depends on various factors, with genetic predisposition playing a major role, particularly in the lumbar spine. Especially in younger patients with lower back problems, no clear trigger can often be identified, suggesting that predisposition is a major cause.
“In the cervical spine, on the other hand, signs of wear and tear caused by occupational stress are more common. People who frequently work with their heads tilted back—such as painters, electricians, or auto mechanics—are particularly susceptible to disc damage. Intensive competitive sports at a young age can also put strain on the discs in the lumbar spine. To protect the intervertebral discs, it is important to move in a back-friendly manner in everyday life. This means, for example, always bending at the knees when lifting loads and avoiding twisting motions while under load, as these are particularly harmful to the intervertebral discs. It is equally important to strengthen the core muscles—that is, the abdominal and back muscles—since strong muscles support the spine and can thus prevent or delay the onset of discomfort. Regular exercise and targeted training, such as back training or other strengthening exercises, are helpful in this regard. In addition, you should avoid sitting for long periods, change your position more frequently, and generally stay active rather than taking it easy. For the cervical spine, however, muscle training is only of limited help, as there are fewer postural muscles in this area. That’s why it’s especially important to reduce overhead strain and ensure ergonomic working conditions. “While not everything can be controlled, conscious movement, good posture, and targeted training can significantly reduce the strain on the intervertebral discs and thus minimize the likelihood of problems or surgeries,” advises the spine specialist.
At St. Marien Hospital in Lünen, approximately 100 intervertebral disc prostheses are implanted in the cervical spine and about 50 in the lumbar spine each year. The number of surgeries has even increased recently, partly because the Lünen and Werne locations were consolidated.
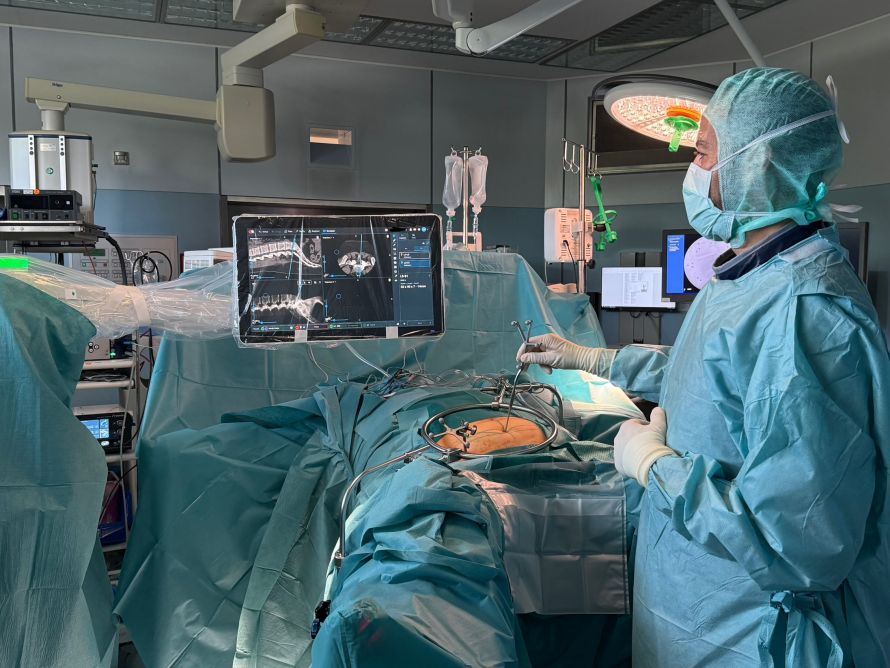
“Especially when implanting a prosthesis in the lumbar spine, it is important that the prosthesis be placed very precisely in the center, because unlike spinal fusion—where a small deviation of a few millimeters is not as critical—the prosthesis must fit exactly to function optimally. To ensure this precise placement, St. Marien-Hospital uses robotic navigation, which enables three-dimensional orientation and thus perfectly displays the midline. This technology was introduced there about a year and a half ago and is unique, as not many hospitals use the robot for this type of spinal surgery. Another advantage of robot-assisted navigation is the reduction in X-ray radiation exposure for patients and the surgical team, as the procedure can be performed more precisely and with less radiation exposure. In the future, artificial intelligence will likely play a key role in helping to better determine which patient is suitable for which type of surgery—prosthesis or fusion. Factors such as smoking, osteoporosis, or the patient’s social situation play a role in this. AI could thus assist in selecting the appropriate treatment, while the technical execution of the surgeries becomes more precise and faster thanks to robots and navigation systems. Overall, the combination of robotics and AI offers great potential for improving treatment in spinal surgery, even though the technical use of AI in the operating room itself has been limited so far. “The rapid development of robotics in hospitals is fascinating and demonstrates how modern technologies can be put to good use in many medical specialties, even though the significance of robots and AI varies depending on the medical field,” said Prof. Dr. El Hindy at the conclusion of our conversation.
Thank you very much, Prof. Dr. El Hindy, for this fascinating insight into the use of artificial disc replacement!
Share this article
About the medical author
Alexandra Pfitzmann
Editor
Alexandra Pfitzmann – medical author: expert knowledge, professional articles and medical insights in the Leading Medicine Guide.
More about the medical author →Expert Interviews
Read next
- Expert interview
Cardiogeriatrics: Significance and benefits in the context of hospital reform
Sep 21, 2026
Cardiogeriatrics: Significance and benefits in the context of hospital reform
Read more - Expert interview
Expert Interview with Professor Dr. Amadeus Hornemann, MPH
Sep 18, 2026
Prof. Amadeus Hornemann on Precision Medicine in Gynecology: Modern Surgery, New Techniques, Better Quality of Life
Read more - Expert interview
Expert Interview with Professor Dr. Konstantinos Anagnostakos
Sep 15, 2026
Prof. Anagnostakos on Painful Knee Replacements
Read more
