
Fundoplication is a well-established procedure in anti-reflux surgery that is primarily used in patients with severe reflux disease. The goal of the surgery is to permanently prevent the backflow of acidic stomach contents into the esophagus and thereby reliably relieve symptoms such as heartburn or coughing. Before the procedure, specialized surgeons use various tests to determine whether surgery is appropriate and which technique—such as the Nissen or Toupet procedure—is best suited. While medication is sufficient in many cases, younger patients with persistent symptoms in particular benefit from surgical treatment. Thanks to the minimally invasive, laparoscopic surgical technique, the procedure is now relatively gentle and offers high success rates.
What is a fundoplication?
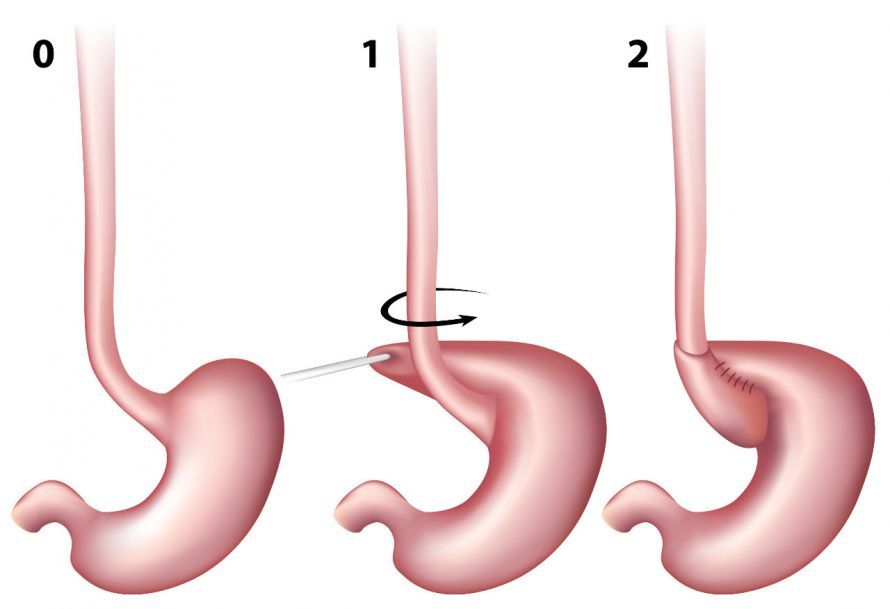
Fundoplication is a surgical procedure used to treat gastroesophageal reflux disease (GERD). During the procedure, the upper part of the stomach—known as the fundus—is wrapped around the lower part of the esophagus like a cuff and secured in place. This strengthens the sphincter at the entrance to the stomach, preventing the backflow of stomach contents into the esophagus.
The term is derived from Latin: “fundus” refers to the upper part of the stomach, while “plicatio” means “folding” or “doubling.” This “folding” creates a fundus cuff that stabilizes the lower esophagus and effectively prevents reflux.
Fundoplication for Reflux & Heartburn—When Is It Helpful?
Fundoplication is a procedure that is now predominantly performed laparoscopically and is used primarily in patients with gastroesophageal reflux disease (GERD). A typical symptom is heartburn, which is caused by the reflux of acidic stomach acid into the esophagus. In this process, stomach contents enter the esophagus and cause a burning pain in the upper abdomen or behind the breastbone.
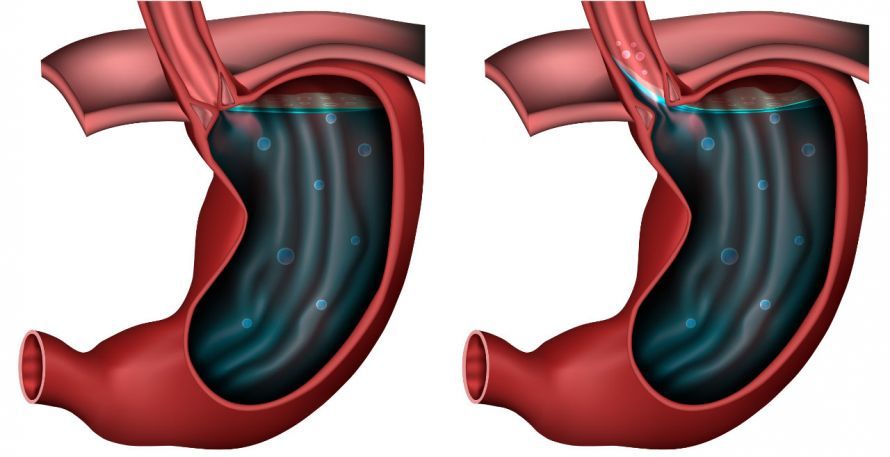
In most cases, medication—such as proton pump inhibitors (PPIs like pantoprazole or omeprazole)—is sufficient as an initial treatment. These medications reduce acid production in the stomach, thereby alleviating symptoms.
Fundoplication may be considered if
- symptoms persist despite consistent medication,
- reflux occurs as far as the mouth or even into the airways,
- complications such as chronic bronchitis or lung disease develop,
- or patients—especially younger ones—desire a permanent cure without having to take medication continuously.
In such cases, specialized surgeons carefully evaluate the indications. Fundoplication can then be a successful treatment that permanently prevents reflux and brings about a noticeable improvement in quality of life.
History of Fundoplication: From Nissen to the Present
Fundoplication was first described in 1956 by the surgeon Rudolf Nissen. For this reason, the original technique is also known as the Nissen fundoplication or Nissen full cuff, as the gastric fundus is wrapped completely around the lower esophagus in a 360-degree cuff. This surgical technique is still considered the gold standard of antireflux surgery today.
In the decades that followed, the procedure underwent continuous refinement. Instead of open surgery involving a large abdominal incision, fundoplication is now predominantly performed laparoscopically—that is, using a minimally invasive approach. This technique reduces the risk of complications, speeds up recovery, and results in a shorter hospital stay.
In addition to the classic Nissen fundoplication, other variants have emerged, such as the Toupet fundoplication (partial sleeve with a 270° wrap) or specialized adaptations for patients with additional conditions such as achalasia or a hiatal hernia. The choice of procedure depends on the patient’s individual situation and is determined as part of the visceral surgical evaluation.
As a result, fundoplication has evolved from a pioneering procedure into an established standard procedure that is routinely performed in specialized centers for modern visceral surgery.
Fundoplication: Necessary Tests Before the Procedure
Gastroscopy Before a Fundoplication
Functional Diagnostics of the Esophagus: Manometry & pH Monitoring
Another key component of determining the indication is functional testing. This includes manometry, which measures pressure in the esophagus and at the entrance to the stomach. It shows how strongly the muscles are contracting and whether food is being transported normally into the stomach.
This is supplemented by pH monitoring, a measurement of acid levels in the distal esophagus over at least 24 hours. This allows for a precise determination of how frequently and intensely acid reflux occurs. These results are crucial for determining the need for surgery and selecting the appropriate surgical technique.
X-ray Examination Before and After Fundoplication
- before surgery, to help determine the choice of procedure,
- after surgery, to assess the outcome and rule out possible complications such as improper positioning of the cuff.
Surgical Technique: The Fundoplication Procedure
Minimally Invasive Approach: Laparoscopic Fundoplication
Today, fundoplication is performed almost exclusively laparoscopically. Surgeons insert a camera and instruments through 4 to 5 small incisions in the upper abdomen. This procedure is particularly gentle, reduces pain, and allows for a quick postoperative recovery.
Open Surgical Technique
Only in exceptional cases—such as in patients who have undergone multiple surgeries or in cases of complications—is fundoplication still performed as open surgery via an abdominal incision.
Formation of the Fundus Sleeve
The core of the procedure is the formation of a fundus cuff: The upper portions of the gastric fundus are wrapped around the lower esophagus and carefully sutured. This creates a kind of valve mechanism that reinforces the sphincter and prevents the reflux of stomach contents into the esophagus. The suturing technique secures the individual sections in such a way that a stable but not overly tight cuff is formed—this prevents complications such as dysphagia.
Variations: Nissen vs. Toupet Fundoplication
- In Nissen fundoplication, a full Nissen cuff (360°) is placed around the entrance to the stomach. This technique, developed by surgeon Rudolf Nissen, is considered the standard procedure and provides high reflux control.
- Toupet fundoplication involves a partial sleeve (270°), in which the anterior and posterior walls of the stomach are secured to the anterior and posterior walls of the esophagus. This procedure causes fewer swallowing problems and often results in less bloating.
- Studies show that both procedures have a high success rate. The choice of procedure depends on the individual findings and is determined by the clinic or the experienced surgeon.
Additional Steps: Hiatoplasty & Suturing Technique
Fundoplication is often combined with hiatoplasty. In this procedure, the diaphragmatic crura at the point where the esophagus passes through the diaphragm are sutured closer together to achieve additional stabilization. This step is particularly important for patients with a diaphragmatic hernia.
Life After Fundoplication: Symptoms & Daily Life
In most cases, a successful fundoplication results in significant relief from symptoms: typical symptoms such as heartburn or acid reflux often disappear immediately after the procedure. Regular medication is also generally no longer necessary.
After laparoscopic fundoplication, patients usually remain hospitalized for 2 to 5 days to monitor wound healing and the early postoperative phase. During this time, the surgical incisions are checked, and patients are informed about the altered anatomy of the stomach entrance.
To ensure the long-term success of the surgery, adjustments to daily life are necessary—especially regarding eating habits:
Recommended Behaviors After Fundoplication
- Chew food thoroughly
- Eat slowly and opt for small portions
- Swallow as little air as possible (e.g., when drinking or speaking)
Things to avoid in the first few weeks
- Carbonated beverages
- Foods that cause excessive gas (e.g., legumes, onions)
- Eating too quickly or eating large meals
Since air has a harder time escaping after surgery, belching and vomiting are limited, especially in the early stages. This problem is usually less pronounced after a Toupet fundoplication (partial sleeve) than after a Nissen fundoplication (full sleeve).
Tolerance to different foods varies from person to person and must be tested by each patient individually. Those who follow the recommended guidelines generally benefit from a lasting improvement in quality of life: Many foods and beverages that previously caused discomfort—such as coffee, red wine, orange juice, or fried meat—can be enjoyed again after surgery.
Risks & Possible Complications After Fundoplication
General Risks of Surgery
As with any surgical procedure, fundoplication also carries general risks. These include injury to adjacent organs such as the spleen, liver, or intestines, which can lead to internal bleeding. Thrombosis and wound infections are also among the general risks of surgery. Thanks to modern laparoscopic surgery, such problems occur only rarely.
Specific Complications Following Fundoplication
A feared but very rare complication is injury to the esophagus during the procedure. It must be identified immediately and securely sutured; otherwise, there is a risk of infection in the mediastinum, which can be life-threatening. In isolated cases, the cuff may loosen later or migrate into the chest cavity, particularly after severe coughing or repeated vomiting.
Side Effects & Functional Symptoms
In addition to serious complications, some patients report functional problems in their daily lives:
- Dysphagia (difficulty swallowing) if the cuff is too tight
- A feeling of fullness and pressure in the upper abdomen
- Increased flatulence or reduced flatulence symptoms, depending on the technique
- Occasional diarrhea
These side effects can usually be effectively managed by adjusting eating habits or taking medication for a short period.
Long-Term Prognosis & Complication Rate
In randomized studies, the complication rate among experienced surgeons is well below 5%. In approximately 89 percent of patients, long-term control of reflux is achieved, making fundoplication a successful treatment for reflux disease. Only a small number of patients experience a recurrence of symptoms, which is why the surgery is considered a procedure with a high success rate.
More on Fundoplication & Specialized Surgeons
Fundoplication is a well-established anti-reflux surgical procedure that has been in use for decades and is now performed in specialized centers for visceral surgery. Depending on the patient’s condition, surgeons choose between different techniques:
- the Nissen fundoplication with a complete 360° sleeve and
- the Toupet fundoplication with a partial sleeve (270°).
Studies show that both procedures have comparable efficacy. In some situations, however, one technique is deliberately chosen over the other (e.g., Nissen versus Toupet), such as when there is an increased risk of dysphagia. The correct indication and choice of procedure depend on the individual findings, the portion of the esophagus included in the sleeve, and the surgeon’s experience.
The surgery requires a high degree of precision: the gastric fundus is wrapped around the esophagus in such a way as to create a stable sleeve. In doing so, surgeons pay particular attention to suturing the structures to ensure that the filling of the stomach after eating does not lead to a feeling of excessive pressure.
Young patients in particular often benefit from the surgery, as they can expect lasting relief without the need for constant medication. Most patients who have already undergone the procedure also experience a significant improvement in their quality of life. Although serious complications are rare, the procedure should only be performed by experienced surgeons at specialized clinics.
For patients suffering from persistent heartburn and reflux symptoms, fundoplication thus offers an effective and long-term successful treatment option.
FAQ – Frequently Asked Questions About Fundoplication
What is fundoplication?
Fundoplication is a surgical procedure for treating reflux disease in which the upper part of the stomach (the gastric fundus) is wrapped around the esophagus like a cuff and sutured in place. This strengthens the sphincter at the entrance to the stomach, preventing stomach contents from flowing back into the esophagus.
When is fundoplication an option?
Surgery is considered when medication does not adequately relieve symptoms or when symptoms recur despite treatment. Younger patients in particular often benefit because this allows them to achieve long-term improvement without having to take medication constantly.
What is the difference between Nissen and Toupet fundoplication?
How do Nissen and Toupet fundoplication differ?
In the Nissen technique, the upper portion of the stomach is wrapped completely (360°) around the esophagus—a so-called full sleeve. This procedure offers very reliable control of reflux symptoms but can, in rare cases, make swallowing difficult.
The Toupet method, on the other hand, wraps only about three-quarters (270°) of the esophagus and is therefore considered less invasive. It usually results in fewer swallowing problems and reduces the tendency toward bloating. Specialized physicians decide which technique to use based on the initial findings.
What are the possible consequences or risks following a fundoplication?
As with any surgery, there are general risks such as bleeding or infection. Specific symptoms after the procedure may include a feeling of pressure in the upper abdomen, difficulty swallowing, or reduced belching. Serious complications are rare, and overall, the surgery is considered a very safe procedure with good long-term outcomes.
What are the long-term outcomes after fundoplication?
According to clinical studies, fundoplication achieves lasting symptom relief and reliable reflux control in approximately 89 percent of patients. Many patients who have already undergone the procedure report a significant improvement in their quality of life, as they can once again eat foods that were previously intolerable without experiencing any symptoms.














