
The Norwood procedure is a surgical technique used to treat newborns with congenital hypoplastic left heart syndrome. It is a three-stage surgical procedure, the first stage of which is performed within the first few days of life. The second stage follows several months later, and the third stage of the Norwood procedure is usually performed between the ages of one and a half and three years.
Below you will find more information about this surgical procedure as well as specialists in Norwood surgery.
Definition: What is a Norwood procedure?
The Norwood procedure is used to save newborns with HLHS.
Anatomical Background
Hypoplastic left heart syndrome (abbreviated HLHS) is a rare but serious heart malformation. It accounts for about 1.6% of all congenital heart defects. Children born with this heart defect will die during the neonatal period unless immediate intervention is performed. HLHS is genetically caused.
In HLHS, the left side of the heart—that is, the left atrium and the left ventricle—is underdeveloped. The first section of the aorta is also underdeveloped or completely nonfunctional. The ascending aorta, up to and including the aortic arch, is most commonly affected. In addition, the two heart valves of the left side of the heart are underdeveloped:
- the mitral valve between the left atrium and the left ventricle, and
- the aortic valve between the left ventricle and the aorta
These valves are severely narrowed or completely blocked and underdeveloped.
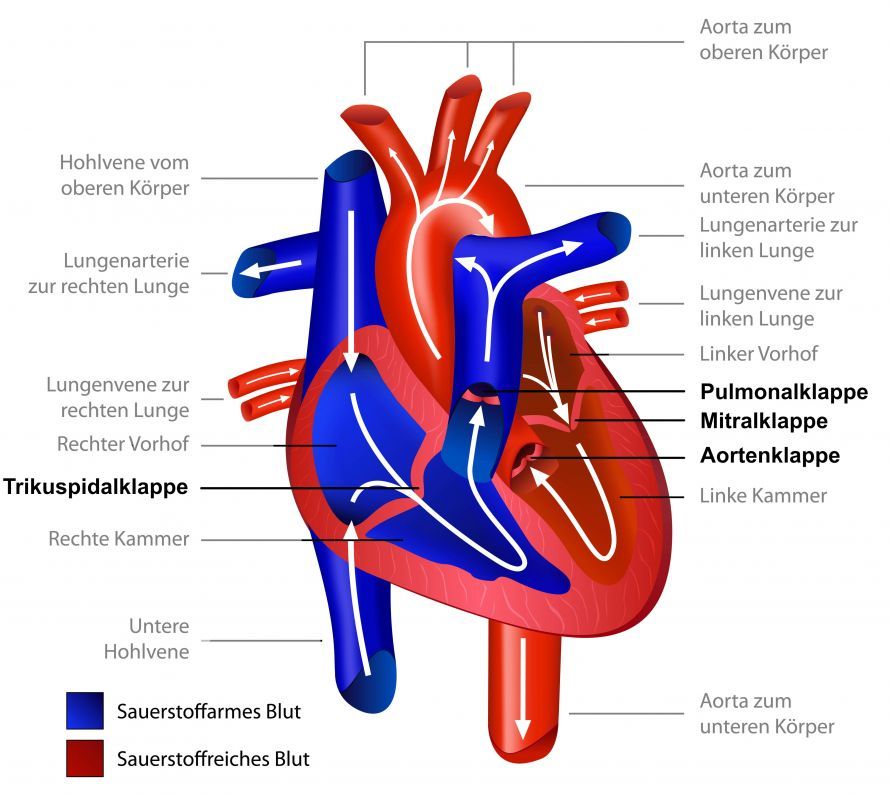
The anatomy of a healthy heart © bilderzwerg | AdobeStock
The Norwood Procedure
In principle, the Norwood procedure involves converting the heart to a single-chamber system. Since the left side of the heart cannot perform its function, the right side must take over its duties.
The right ventricle then supplies the body with oxygen-rich blood from the pulmonary circulation. In a normally developed heart, this is the role of the left side of the heart.
This surgery was developed in the early 1990s by William Norwood. The first patients treated in this way have already reached the age of about 30.
The Norwood procedure is not a single operation but a three-stage surgical process:
- The first stage is performed in the first few days of life.
- The second stage follows several months later, and
- the third stage of the Norwood procedure is usually performed between the ages of one and a half and three years.
The first two stages of the Norwood procedure are performed on a stopped heart. This means the heart must be stopped. The body’s oxygen supply is then maintained using a heart-lung machine.
Children with HLHS in their first days of life
Normally, the pulmonary circulation and the systemic circulation in humans are separate. They converge in the heart, from where oxygen-rich blood from the lungs is pumped into the body.
Unborn babies cannot yet breathe on their own while in the mother’s womb. For this reason, the systemic and pulmonary circulatory systems remain connected during the first hours or days after birth. The connection between the two circulatory systems is maintained by
- by the vascular connection between the pulmonary artery and the aorta, called the ductus arteriosus Botalli, as well as
- the opening (foramen ovale) in the septum between the left and right atria
.
After birth, the body gradually breaks down these shunts. In newborns with healthy hearts, this is important for supplying oxygen to the systemic circulation.
For children with HLHS, however, the gradual separation of the pulmonary circulation from the systemic circulation is life-threatening. The underdeveloped side of the left heart cannot generate the necessary pumping capacity.
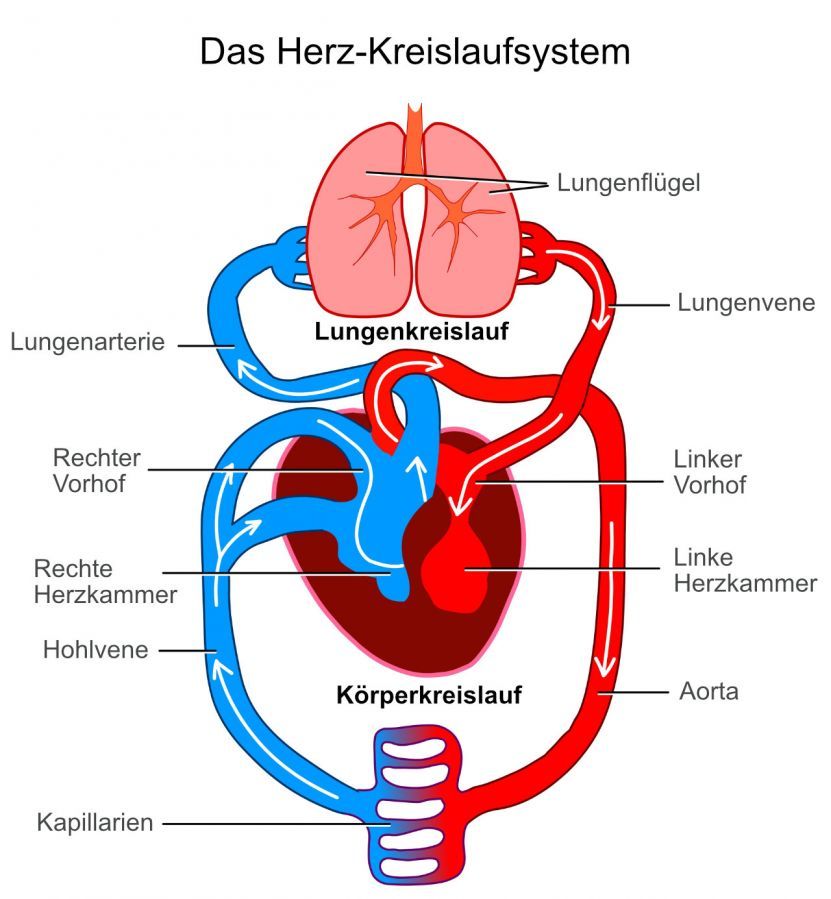
The human cardiovascular system with a healthy heart © LuckySoul | AdobeStock
First stage of the Norwood procedure in newborns
The first procedure as part of the Norwood operation is therefore necessary within the first few days of life. The cardiac surgeon then creates an artificial connection between the pulmonary and systemic circulatory systems.
The surgeon operates on a stopped heart. First, he reconstructs the underdeveloped section of the aorta, including the aortic arch. In addition, he creates an artificial connection between the aorta and the pulmonary artery (arteria pulmonalis).
The heart surgeon closes off the natural connection between the two circulatory systems that is still present at birth. Furthermore, he removes the septum between the two atria.
The right ventricle now takes over the pumping function for both the pulmonary and systemic circulations.
However, the oxygen-rich blood from the lungs still mixes with the “used,” carbon dioxide-rich blood from the entire body. As a result, due to the suboptimal supply of oxygen, these children tend to develop a purplish-blue discoloration
- of the skin,
- lips, and
- the mucous membranes (cyanosis).
Second stage of the Norwood procedure a few months later
In the second stage of the Norwood procedure, the cardiac surgeon relieves the pressure on the right ventricle.
The second stage of the Norwood procedure is also performed by the cardiac surgeon on an open, non-beating heart. The surgeon transects the superior vena cava and connects it directly to the pulmonary artery (known as a Hemi-Fontan or Glenn anastomosis).
He removes the connection between the aorta and the pulmonary artery that was implanted in the first stage.
He then inserts a patch into the right ventricle. This prevents oxygen-poor blood from the lower body from flowing uncontrollably into the lungs.
The surgery relieves some of the strain on the right ventricle. However, oxygen-poor blood still mixes with oxygen-rich blood from the lungs via the inferior vena cava. As a result, oxygen supply is still not optimal.
Third stage of the Norwood procedure at 1.5 to 3 years of age
The final procedure ensures a complete separation between oxygen-rich and oxygen-poor blood.
In some specialized hospitals, cardiac surgeons perform the third and final stage of the Norwood procedure without using a heart-lung machine.
The surgeon now also connects the inferior vena cava to the pulmonary artery. As a result, the deoxygenated, carbon dioxide-rich blood can no longer mix with the oxygen-rich blood.
The difference from a normal heart is that the right ventricle takes over the function of the left ventricle. It pumps oxygen-rich blood from the lungs directly into the aorta. The oxygen-poor blood from the upper and lower body flows directly into the pulmonary arteries without pressure. In a healthy heart, blood is pumped from the right ventricle to the lungs. After the Norwood procedure, no pumping is necessary.
Prognosis after the Norwood procedure
It is not yet possible to make a reliable statement about the life expectancy of those affected. The surgical procedure has only been in use for just under 30 years.
However, experience has shown that patients can lead a (nearly) normal life. Participating in recreational sports without engaging in high-intensity physical activity is possible. There is strong evidence to suggest that patients have a normal life expectancy.

