
The most common diseases of the sclera include inflammatory conditions, particularly scleritis and episcleritis. While episcleritis is usually milder, scleritis is a serious inflammation that can be associated with more severe symptoms and complications.
Both conditions are often associated with general inflammatory processes and underlying systemic diseases.
Below you will find further information as well as a selection of specialists in scleral diseases.
Definition
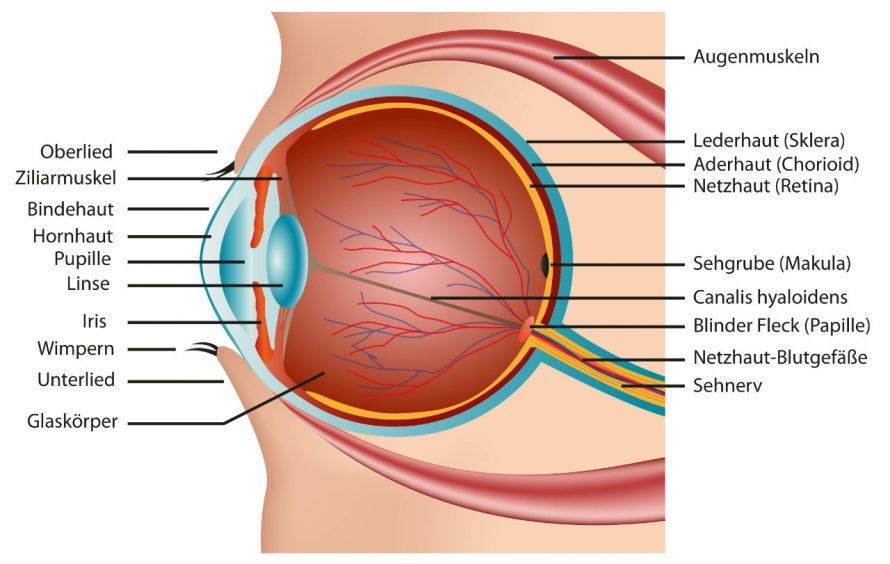
The sclera is part of the outer layer of the eye and covers about 80% of the eyeball. It consists of firm connective tissue and provides the eye with stability. At the same time, it protects deeper structures from mechanical stress. The external eye muscles attach to it, thereby enabling the eye to move within the eye socket.
The thickness of the sclera varies between 0.4 and 1.2 millimeters depending on the region. It is particularly thick in the posterior region of the eyeball, where the optic nerve exits. At the front, the sclera transitions into the cornea, which plays a central role in the refraction of light. This anatomical proximity also explains why inflammatory processes affecting the outer layer of the eye must be carefully evaluated.
Causes and Risk Factors
Inflammation is the predominant feature of scleral diseases. These primarily include scleritis, a deeper form of inflammation, and episcleritis, a superficial form. These changes rarely occur exclusively at the local level. They often develop in connection with systemic diseases that eventually affect the sclera as well.
The most important causes include autoimmune diseases and chronic inflammatory processes. These include, for example, rheumatism, gout, collagenoses, or vasculitis. Infections can also be involved, such as syphilis, herpes zoster, or Lyme disease.
Identifying the underlying cause is particularly important in cases of scleritis, as treatment depends largely on it.
In the case of episcleritis, the specific cause often remains unclear. Although it sometimes occurs in conjunction with underlying conditions, it is frequently observed without a clearly identifiable trigger. Typically, it can recur at longer intervals.
In addition to inflammatory causes, the sclera can also be affected by injuries, such as those resulting from accidents. A yellowish discoloration of the sclera can also occur as part of jaundice (icterus), without there necessarily being a primary inflammation.
Symptoms
The symptoms differ significantly between episcleritis and scleritis.
Scleritis
Scleritis can manifest as a localized condition—that is, confined to the sclera—or as a diffuse condition, meaning it is widespread. This inflammation often leads to complications and has a chronic course. The average age of those affected is 52 years.
The specific cause is usually difficult to determine. However, scleritis often occurs in association with chronic inflammation associated with certain diseases or infections.
Most commonly, the site of inflammation is located in the anterior portion of the outer layer of the eye. Only five percent of cases involve a posterior location in the sclera.
The primary treatment for this condition involves managing the underlying disease, usually with anti-inflammatory medications.
Complications may arise from
- recurrence of the condition (high recurrence rate) and
- destruction of the sclera (necrosis).
Episkleritis
Episkleritis is an inflammation of the episclera, a structure located between the sclera and the conjunctiva. It can be
- be diffuse,
- be limited to specific sectors, or
- nodular
in the sclera of the eye.
The causes of this disease of the outer layer of the eye are usually unclear. It most often occurs in association with other underlying conditions or inflammatory processes. Patients are typically between the ages of 40 and 60.
Episkleritis affects the sclera repeatedly at periodic intervals, although the intervals between episodes can be very long. Unlike scleritis, complications are rare.
Diagnosis
Diagnosis begins with a thorough ophthalmological examination. In ophthalmology, the key distinction is whether the condition is superficial episcleritis or deeper-seated scleritis.
The description of the symptoms alone provides important clues. Mild irritation and localized redness tend to indicate episcleritis, while severe pain and deep-seated signs of inflammation tend to indicate scleritis.
During the examination, the extent and location of the redness, as well as any accompanying changes, are assessed. It is also important to determine whether an underlying condition is present. Therefore, depending on the suspected cause, further evaluation by a physician specializing in internal medicine or rheumatology may be necessary.
Particularly in cases of recurrent or severe inflammation, a purely local assessment is insufficient. It is crucial to reliably rule out other causes of a red eye. Not all redness is harmless; if severe pain, light sensitivity, or vision loss are present, a serious inflammation of the sclera should always be considered.
Treatment
Treatment depends on the type, extent, and cause of the inflammation. In cases of episcleritis, symptomatic therapy is often sufficient, as the condition is usually self-limiting. The primary goal is to alleviate symptoms and monitor the course of the condition. Since the condition can recur, frequent episodes should prompt an investigation into whether there is a connection to underlying inflammatory diseases.
Scleritis usually requires more intensive treatment. The primary focus is on treating the underlying condition, if one is identified. Anti-inflammatory medications are used as an adjunct. In cases of infectious causes, targeted treatment of the pathogen is necessary.
Interdisciplinary care is particularly advisable in cases of chronic and severe disease progression to ensure that both the local inflammation and the systemic cause are treated appropriately.
Course
Episkleritis usually has a favorable course; it often resolves within a limited time and rarely causes complications. However, it can recur at periodic intervals. The symptom-free intervals can be long.
In contrast, scleritis often has a more severe course. It can become chronic, recur, and, in severe cases, lead to tissue destruction. Chronic forms are particularly problematic.
This is another reason why early diagnosis is important; the sooner an underlying cause is identified and treated, the better the prognosis can be managed.
In summary, episcleritis is usually the milder form, while scleritis is the significantly more serious one. Recurring symptoms, severe pain, or vision loss should always be evaluated promptly.
Specialists
The primary points of contact for conditions in this area are ophthalmologists with experience in inflammatory changes affecting the outer layers of the eye. If scleritis or an underlying systemic disease is suspected, collaboration with other medical specialties is often advisable; for example, rheumatology, internal medicine, or infectious diseases.
It is particularly important for affected individuals to see a specialist if their symptoms are severe, recurrent, or if their vision is impaired. This allows for an early distinction between relatively harmless episcleritis and inflammation of the sclera that requires treatment.
Frequently Asked Questions
What is the sclera of the eye?
The sclera is the firm outer layer of the eyeball. It forms the visible white part of the eye and provides stability.
What is the difference between episcleritis and scleritis?
Episkleritis affects the superficial layer between the conjunctiva and the sclera and is usually mild. Scleritis is a deeper inflammation with more severe pain and a higher risk of complications.
What causes inflammation of the sclera?
Possible causes include autoimmune diseases, rheumatic diseases, infections, or other underlying inflammatory conditions. In the case of episcleritis, the cause often remains unclear.
What are the typical symptoms?
Typical symptoms include redness, a sensation of irritation and pressure, and tearing. Scleritis is often accompanied by severe pain, sensitivity to light, and, in some cases, vision loss.
When should a red eye be examined?
A red eye should be examined by a doctor, especially if severe pain, recurrent inflammation, or vision loss occurs.
How are scleral diseases treated?
Treatment depends on the cause and severity. Episcleritis is usually treated symptomatically, whereas scleritis often requires targeted treatment of the underlying condition as well.
Share this article
