
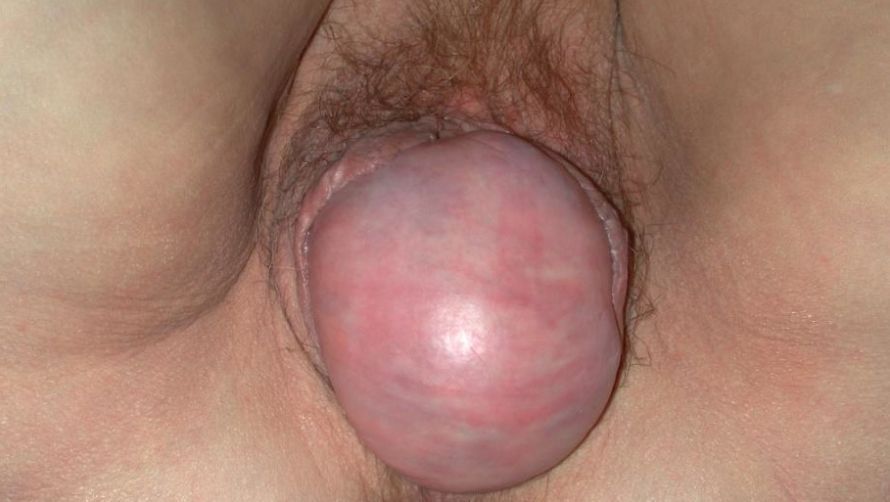
Vaginal prolapse (descent of the vagina) occurs when the vagina can no longer be held in place. This is caused by damage to the supporting structures made of connective tissue and the pelvic floor muscles. Possible effects include problems with bladder function and bowel movements. Pain may also result.
Causes of Vaginal Prolapse
Due to upright posture, the birth canal lies in the pelvis with its opening at the bottom. The bony pelvis is closed off by the pelvic floor muscles (primarily the levator group) and by supportive structures made of connective tissue (ligaments and fascia). The vagina remains as an opening. During childbirth, this opening is stretched significantly to allow the baby to pass through. Damage to the supporting structures and muscles can occur even during childbirth. Tears in the muscles and connective tissue, as well as overstretching of nerves, are possible.
The pelvic floor is subjected to significant strain due to pressure from the abdominal organs and chronic stress over many years. If a woman is predisposed, this can lead to damage. The result is vaginal prolapse and/or uterine prolapse. Since the urethra and bladder lie directly against the anterior wall of the vagina, they also prolapse. The rectum is held in place by the posterior wall of the vagina. If this wall gives way, this portion of the intestine also descends. Being overweight and smoking are additional factors that contribute to vaginal prolapse. Many women do not notice the initial changes until additional symptoms arise.
Symptoms of Vaginal Prolapse
Vaginal prolapse can cause a variety of functional disorders due to the resulting changes in the position of neighboring organs:
- Bladder dysfunction, such as stress urinary incontinence and an increased urge to urinate, frequently occurs with vaginal prolapse.
- However, bladder emptying disorders caused by kinking of the urethra are also possible.
- Bowel movement disorders, fecal smearing, and fecal incontinence can result from the prolapse of the posterior vaginal wall along with the rectum.
- Sexual function is also often impaired by vaginal prolapse.
In severe cases of prolapse, the anterior and posterior vaginal walls or the uterus may protrude in front of the vaginal opening. If vaginal prolapse persists for a long time, ulcerations (open sores) may develop, which may also bleed slightly.
Preventing Vaginal Prolapse
You can prevent vaginal prolapse by taking the following measures:
- Regularly exercising the pelvic floor muscles
- Avoiding unnecessary strain
- Lifting weights correctly
Unfortunately, congenital connective tissue weakness cannot be improved. After menopause, a low-dose vaginal estriol treatment can have a beneficial effect on the tissue.
Diagnosis of Vaginal Prolapse
The gynecologist is usually the first point of contact. They can often detect vaginal prolapse during a routine preventive exam. Women with bladder dysfunction often also consult a urologist.
Conservative treatment—that is, treatment without surgery at first—is often initiated right in the doctor’s office. If the vaginal prolapse or functional disorders are severe, surgery may be necessary. In that case, consult a urogynecological clinic or a pelvic floor center.
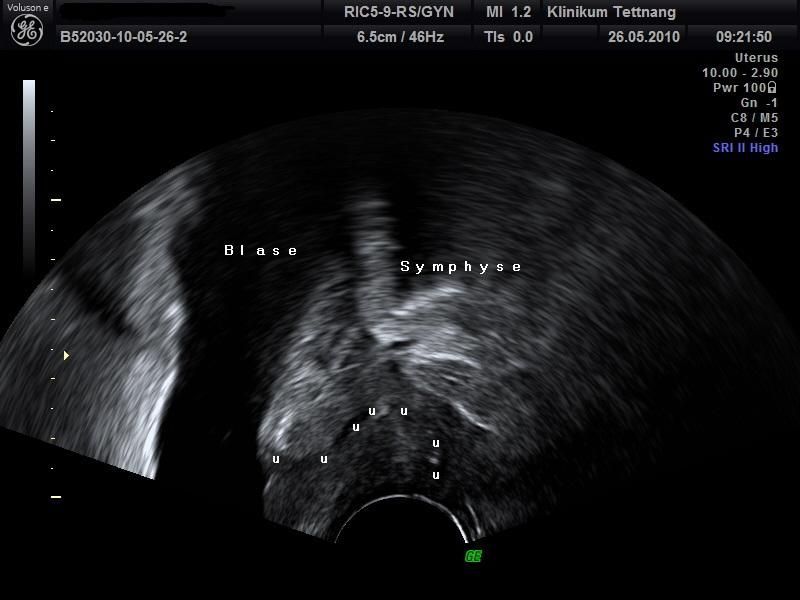
A simple ultrasound exam can provide a more accurate assessment of the positional changes in the urethra, bladder, vagina, uterus, and intestines. Sometimes a urodynamic study is also required. This allows for an assessment of the bladder’s storage function and any incontinence. In complex cases, an X-ray examination of the bowel or bladder or an MRI scan of the pelvis may also be performed.
Treatment of Vaginal Prolapse
Pelvic floor exercises or pessaries
With physiotherapy-supervised pelvic floor exercises—which also include the back and abdominal muscles—it is sometimes possible to stabilize vaginal prolapse. This is especially true when no prolapse has yet occurred. In addition, estrogen is applied vaginally, if possible.
Pessaries (silicone rings, cubes, or cups) can be used to reposition the vagina and stabilize its position. These are used in cases where surgery is not yet necessary or desired. The goal is for the woman to change the pessary regularly. Even if surgery appears too risky for medical reasons, the use of pessaries is still possible.
Plastic Reconstruction of the Pelvic Floor
In cases of severe prolapse, quality of life is significantly impaired by bladder and bowel dysfunction. Surgery can restore the vagina, bladder, and bowel to their original positions.
There are several surgical procedures for pelvic floor reconstruction. The surgery is often performed through the vagina (vaginal procedures). Vaginal prolapse is corrected by tightening the connective tissue and utilizing the existing ligament structures. In some cases, a procedure involving a small abdominal incision or laparoscopy (abdominal endoscopy) is preferred.
Surgical Mesh
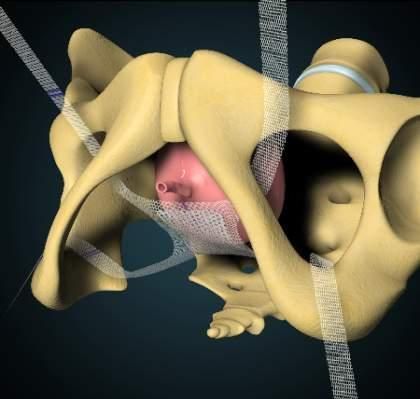
In the past, surgery for vaginal prolapse always involved removal of the uterus. Today, in many cases, the uterus can be left in place. In cases of weak connective tissue or recurrent vaginal prolapse following surgery, it is possible to reinforce the tissue with a synthetic mesh. This results in greater stability.
The specific surgical procedure is selected based on the individual findings regarding the vaginal prolapse and the associated functional disorder. The goal is to achieve the most stable outcome possible and a good restoration of bladder and bowel function. There are clinics that specialize in the diagnosis and treatment of pelvic floor dysfunction and the surgical procedures used to correct it.
Follow-up Care for Vaginal Prolapse
Surgery to treat vaginal prolapse can only restore the position of the organs. However, the function of the pelvic muscles, the bladder, and the bowel requires ongoing attention. The following measures are important for long-term success:
- Muscle training
- Local application of estrogen
- Proper eating and drinking habits
- Proper management of physical exertion
Since it is not possible to reverse the underlying weakness of the supporting tissues, vaginal prolapse may recur later.
Conclusion
The pelvic floor is a vulnerable area of the female body. Exercising the pelvic floor muscles immediately after childbirth can at least delay the onset of vaginal prolapse. If symptoms arise, the gynecologist is the first point of contact. If surgery is unavoidable, it is advisable to seek care at a clinic specializing in urogynecology. Today, various surgical methods are available for treating vaginal prolapse, which are applied on an individual basis depending on the findings and symptoms.
FAQ: Common Questions About Vaginal Prolapse
What symptoms can occur with vaginal prolapse?
Prolapse can make it difficult to empty the bladder or cause constipation. Some patients also report pain during sexual intercourse or a feeling of pressure toward the rectum.
How does a gynecologist diagnose vaginal prolapse?
The diagnosis is usually made during a routine examination, during which the gynecologist assesses the position of the pelvic organs. If a cystocele or vaginal or uterine prolapse is suspected, an ultrasound or further diagnostic procedures may be necessary.
What non-surgical treatment options are available?
Regular pelvic floor muscle exercises are effective for relief, as they help support the pelvic organs. In addition, local estrogen therapy can be helpful, and there are various pessaries available that stabilize the vagina before surgery becomes necessary. These methods can often significantly alleviate symptoms.
When is surgery necessary?
Surgical treatment is primarily considered when daily life is severely restricted or when symptoms worsen despite conservative measures. Surgery is also advisable if heavy lifting, chronic coughing, or infections are causing the condition to deteriorate permanently and other measures are insufficient to prevent the prolapse.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →

