
An acetabular fracture refers to a fracture of the hip socket (acetabulum) and is one of the most complex injuries in orthopedics and trauma surgery. It is usually caused by a severe traumatic event, such as a traffic accident or a fall from a great height. The injury frequently affects the anterior or posterior pillar of the acetabulum (trochanter major); in severe cases, it may even involve both pillars. The Jedet and Letournel classification system, which is commonly used today, distinguishes between simple and associated fracture types and forms the basis for further treatment.
Following a thorough physical examination, X-rays and a CT scan confirm the diagnosis and allow for a precise assessment of the fracture pattern. While stable fractures with minimal displacement can be treated conservatively in select cases, displaced fractures usually require surgical management involving reduction and osteosynthesis. This is followed by rehabilitation to restore hip mobility and muscle strength and to prevent complications.
What is the acetabulum?
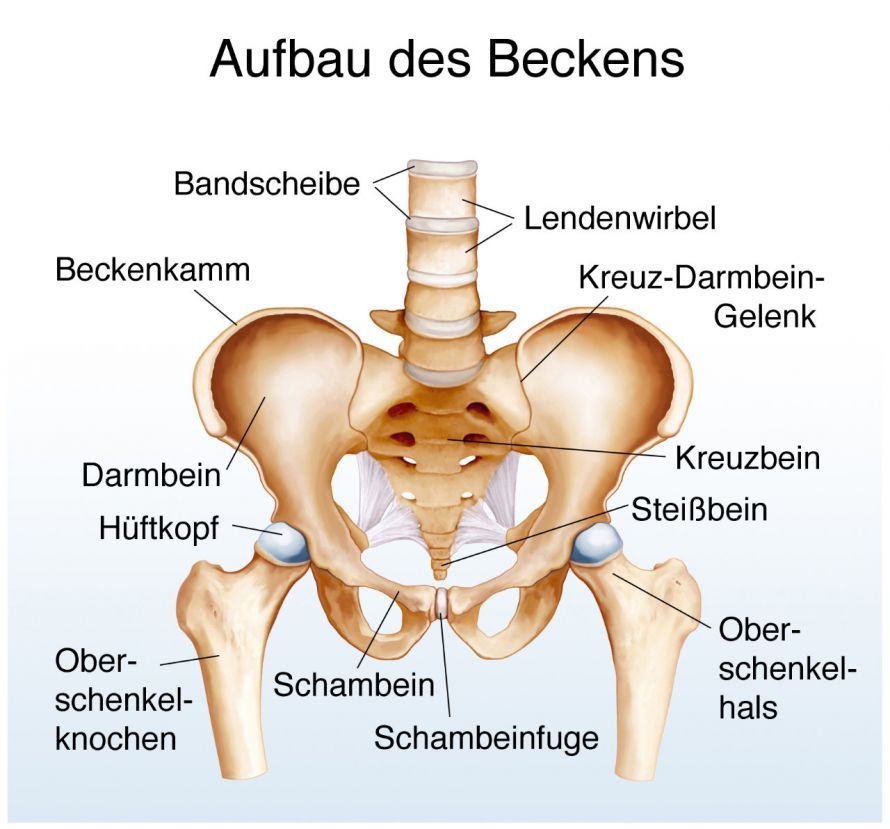
The acetabulum is a part of the pelvic bone and is also known as the hip socket. Viewed from above, it is crescent-shaped and forms the center of the hip joint. All three parts of the pelvic bone—the ischium, pubis, and ilium—meet here and together form the joint surface. The thigh bone (femur) moves within the acetabulum with every movement. Therefore, its integrity is essential for mobility, sports, and even sitting.
The overall incidence of acetabular fractures is low. They primarily affect younger people following high-velocity trauma, as well as older patients following falls, in whom bone quality is already compromised. In addition to classic acetabular fractures, periprosthetic acetabular fractures following hip replacement surgery are becoming increasingly common.
Causes and Risk Factors of Acetabular Fractures—Classification According to Letournel and Judet
An acetabular fracture is a joint fracture that occupies a special category among pelvic fractures. An acetabular fracture is usually the result of severe direct or indirect trauma. This occurs, for example, when falling from a great height and landing on one’s feet. In such cases, the head of the femur is suddenly forced against the acetabulum, which rarely occurs without consequences.
Indirect force can also occur in a rear-end collision when the knee strikes the dashboard. An acetabular fracture often occurs in conjunction with a dislocation of the hip joint. In about 15 percent of cases, there is also an injury to the sciatic nerve (nervus ischiadicus).
Depending on the direction of the force, transverse fractures, injuries to the anterior pillar, fractures of the posterior pillar, fractures of the anterior pillar, or fractures of both pillars may occur. Combined fractures involving other sections of the pelvis also occur.
The Letournel and Judet classification is used internationally to describe the various injury patterns. It distinguishes between simple fractures and associated fracture patterns. Simple injuries include, for example, Type B or Type C, as well as other fracture patterns; treatment depends on the location and extent of the injury and is determined by the fracture pattern.
Hip joint dislocations frequently occur concurrently. The more severe the dislocation of the bone fragments, the more challenging the subsequent reconstruction of the articular surface becomes.
What are the symptoms of an acetabular fracture?
The symptoms of an acetabular fracture are very similar to the general symptoms of a pelvic fracture. They include
- severe pain,
- bruising,
- limited or lost ability to bear weight on the leg,
- swelling, and
- possibly an unstable pelvic bone.
Depending on the extent of the injury, the legs may appear to be different lengths or may be misaligned. Often, the affected leg is turned slightly outward. Mobility of the hip joint is significantly restricted, especially in cases of severe dislocation of the bone fragments.
It is not uncommon for associated injuries to occur. These include injuries to muscles, ligaments, blood vessels, or nerves. If the sciatic nerve is affected, numbness, tingling, or paralysis may occur in the lower leg and foot. Injuries to the bladder, urethra, or internal organs may also be present, particularly if there are additional pelvic injuries.
While injuries in young people are usually caused by severe trauma, injuries in older patients can sometimes result from a fall from a low height. In these cases, symptoms are often less pronounced; nevertheless, an acetabular fracture should still be ruled out.
Diagnosis and Examinations in Orthopedics and Trauma Surgery: Planning for Conservative or Surgical Management of the Fracture
Since acetabular fractures are almost always the result of a severe accident and the patient is unable to walk, the emergency medical services or an emergency physician are usually notified, and further treatment takes place in the hospital. There, the doctors on duty in the emergency room and trauma surgery department determine the next steps. First, detailed questions are asked about the circumstances of the accident and the patient’s medical history (anamnesis):
- How did the accident happen?
- How would you describe the pain?
- Were there any previous symptoms?
- Are there any known pre-existing conditions or previous injuries?
The patient interview is followed by various examinations.
Physical Examination
The physical examination, in particular, is very important and must be conducted thoroughly. During this examination, the following are assessed:
- external injuries,
- bruises, or
- joint misalignments
. A shortened leg on the affected side and outward rotation are also important indicators of a bone injury near the hip.
This is followed by careful palpation of the pelvis to identify tender points and, if necessary, even detect signs of a bone injury (crepitus = crackling). The stability of the pelvis can also be assessed during this process. However, extreme caution is required during the examination, as it is often very painful for the patient and should be avoided if possible.
To rule out internal bleeding, a digital rectal examination is also not uncommon. In addition,
- sensitivity,
- motor function, and
- blood flow
in the legs and feet to ensure that any potential nerve damage is not overlooked.
Imaging Procedures
An ultrasound examination (sonography) can be used to examine the abdominal cavity for possible injuries to the internal organs. In addition, sonography can detect whether there is free fluid—such as blood—in the abdominal cavity. An ultrasound should always be performed in the emergency department (trauma room), especially in cases of severe traffic accidents or falls from a great height. This is part of the initial examination and determines the urgency of further treatment. Injuries to internal organs can be life-threatening and generally require emergency surgery. An isolated acetabular fracture is not usually life-threatening.
To diagnose an acetabular fracture, a pelvic X-ray is essential. This allows the exact location of the fracture to be identified and helps determine whether the fracture is unstable or stable. In addition to a panoramic pelvic X-ray, special projections such as the ala view and other oblique views are often taken for this purpose. In a stable fracture, the bone fragments are barely displaced, whereas in an unstable fracture, there is significant displacement. In the case of minor and non-displaced fractures, they may not be clearly visible on a standard X-ray; however, this does not rule out a bone fracture.
If a bone fracture is suspected based on the patient’s medical history and severe pain, a computed tomography (CT) scan should definitely be performed. This allows for an accurate assessment of the extent of the injury. In addition, a CT scan allows for a better assessment of the condition of the soft tissues. This examination clearly shows the extent to which a hematoma has spread.
The results of the imaging are essential for preoperative planning. The subsequent choice of surgical approach and the surgical procedure depend largely on these findings.
Additional Diagnostic Methods for an Acetabular Fracture
As already described in detail, the most important examination for an acetabular fracture is computed tomography. However, to detect additional injuries to neighboring organs and organ systems, additional specialized examinations may be necessary. Associated injuries may include, for example,
- the bladder,
- the urethra,
- the ureter, as well as
- the rectum or
- a woman’s internal reproductive organs (ovaries and uterus).
Initially, examinations by the appropriate specialists who deal with the respective possible associated injuries are necessary. A urologist is responsible for the bladder, urethra, and ureter; a visceral surgeon for the colon and rectum; and a gynecologist for the reproductive organs. If concomitant injuries are suspected, the responsible specialists will then arrange for further examinations as needed.
For example, if injuries to the urinary tract and kidneys are suspected, a procedure called excretory urography may be ordered. For this purpose, the patient is administered a contrast agent, which is injected into a vein. The body excretes this contrast agent through the kidneys, and it is visible on an X-ray.
The initial examination determines whether immediate treatment is necessary or whether other injuries must be treated first.
Treatment of an Acetabular Fracture
An acetabular fracture is a serious injury that requires surgery in nearly all cases. This is also done with the goal of preventing premature joint wear. After all, the acetabulum plays a central role and bears the brunt of the load when a person walks upright.
The goal of the surgery is to restore the joint surface as anatomically as possible. This is particularly important in cases of displaced fractures, joint steps, unstable injuries, trapped bone fragments, or accompanying dislocations of the hip joint.
For this reason, patients usually have to remain on bed rest for several weeks after surgery. If a multiple pelvic fracture is present in addition to the acetabular fracture, it may take several months before the patient is allowed to bear weight on their legs again.
Surgery on the hip socket following an acetabular fracture is a complex procedure. For this reason, the surgery should be performed at specialized centers. During the surgery, the fractured bone fragments are fixed in place using plates and screws or an external stabilizer. During the acute phase, anesthesia is the primary treatment.
Pain-relieving medications enable the patient to perform physical therapy exercises. Many pain relievers have calming properties, which have a positive effect on patients with an acetabular fracture.
Treatment depends on the extent of the injury, the type of fracture, the patient’s age, and other patient-specific factors. In addition, patient-specific factors such as associated injuries, general health, and the stability of the hip joint play a role.
Primarily conservative treatment of an acetabular fracture is usually insufficient to prevent secondary damage.
Surgical Treatment
Surgical treatment is one of the most challenging procedures in pelvic surgery and should be performed in specialized centers for orthopedics and trauma surgery following detailed preoperative planning.
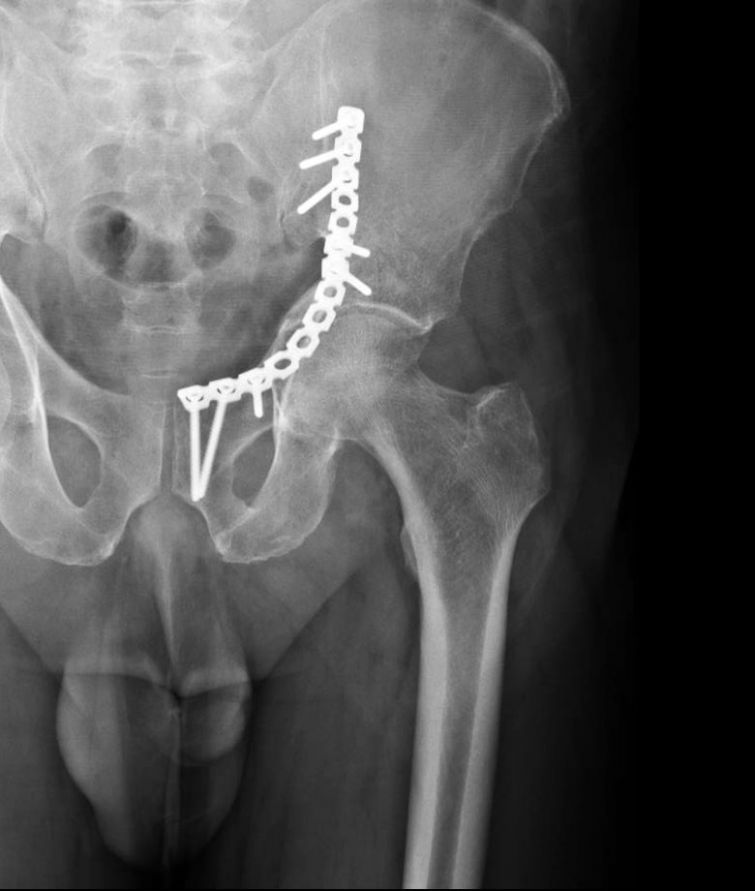
The basic principle of the surgery is open reduction of the bone fragments, followed by realignment and fixation using osteosynthesis. After the fragments have been precisely aligned, they are permanently stabilized with plates and screws. The posterior pillar is often fixed using a reconstruction plate to restore the stability of the hip joint.
The choice of surgical technique depends on the fracture pattern. The location of the injury, associated injuries, and the choice of surgical approach also influence the surgical procedure.
Depending on the fracture, different surgical approaches may be considered:
- the ilioguinial approach,
- the Stoppa approach,
- the modified Stoppa approach, and
- combined surgical techniques.
In particular, the ilioinguinal approach and the modified Stoppa approach provide good visualization of the anterior pillar and the quadrilateral surface. This allows even complex combined fractures to be treated safely.
After successful reduction, the stability of the repair is checked immediately. The goal is to restore the articular surface as anatomically as possible, since even minor irregularities can lead to premature joint wear in the long term.
Complication: Special Fracture Types—Periprosthetic Acetabular Fractures
Periprosthetic fractures become more common with advancing age. In these cases, the injury occurs in the area of an already implanted hip prosthesis.
Such a fracture poses special challenges for surgical planning. Treatment is often guided by the Paprosky and Della Valle classification system, which takes into account both the stability of the prosthesis and the extent of the bone defect.
For example, if a stable prosthesis is present following a fall from standing height, bony reconstruction can often be performed. In more complex cases, the acetabulum must also be replaced.
Scientific case reports describe, among other things, a right-sided periprosthetic posterior pillar acetabular fracture with a stable prosthesis. Such injuries require particularly careful surgical planning and experience in pelvic surgery.
After the surgery is completed, the first postoperative assessment is performed using X-ray or CT. Postoperative imaging following revision—or imaging following revision with osteosynthesis—serves to verify the correct positioning of the implants. If a revision with osteosynthesis of the posterior pillar was performed, the stability of the reconstruction is also assessed.
Rehabilitation After an Acetabular Fracture
An acetabular fracture is a relatively complex fracture that requires a long recovery period. It takes weeks or months before the patient is allowed to bear weight on their legs as usual. However, this extended period is crucial to prevent secondary malalignment or malunion. “Secondary” refers to a good alignment of the fractured bone fragments immediately after surgery that subsequently shifts due to premature weight-bearing.
Nevertheless, even with a pelvic fracture, it is important to begin mobilization early to reduce the risk of thrombosis and prevent muscle atrophy. To avoid the complications mentioned above, this must be done under the guidance of a physical therapist in the case of an acetabular fracture. This allows the extent of the load to be monitored and controlled, and helpful tips and tricks to be provided.
At the beginning of physical therapy, aquatic exercise therapy is ideal for strengthening the muscles and regaining a normal range of motion, even if the leg cannot yet bear full weight during this phase.
The program consists primarily of passive and assisted active mobilization. With the help of the physical therapist, the patient performs isometric exercises. These exercises initially involve tensing the muscles without active movement. Later, concentric exercises are performed—that is, exercises in which the patient contracts the muscles during movement.
As therapy progresses, the patient can
- rehabilitation on an ergometer as well as
- special exercises for the lumbar and sacral regions as well as the hip joint
. Only after consulting with the treating physician should the patient begin light physical activities upon completion of the rehabilitation program.
A follow-up examination 2 years postoperatively often reveals whether the joint surface has remained permanently stable or whether signs of joint wear are developing.
Conclusion on Acetabular Fractures
In summary, an acetabular fracture is rarely a life-threatening injury. However, treatment is usually surgical, and the healing process requires a great deal of patience. Patients should expect several months of rehabilitation and limited ability to work. But in the vast majority of cases, the patience is worth it.
Frequently Asked Questions About Acetabular Fractures
Does every acetabular fracture require surgery?
No. Small, stable, and non-displaced fractures can be treated conservatively in some cases. However, the majority of patients require surgical treatment to restore the joint surface as precisely as possible.
How long does healing take?
Bone healing usually takes several months. Full weight-bearing capacity is gradually reintroduced and depends on the individual healing process as well as follow-up examinations.
When can weight-bearing resume?
In the first few weeks, only partial weight-bearing is usually permitted. The treating physician will determine when the leg can bear full weight again based on X-ray or CT follow-up examinations.
What complications can occur?
Possible complications include infections, nerve injuries, delayed bone healing, or later osteoarthritis of the hip joint. Early treatment and consistent rehabilitation can significantly reduce this risk.
Can I return to sports after an acetabular fracture?
In many cases, yes. This requires complete bone healing and sufficient stability of the hip joint. The treating specialist will determine the appropriate time to resume sports activities on a case-by-case basis.
Share this article

About the medical author
Prof. Dr. med. Susanne Regus
Medical Author
Prof. Dr. med. Susanne Regus – medical author: expert articles, professional insights and medical expertise in the Leading Medicine Guide.
View full expert profile →




















