
Adrenal metastases are secondary tumors (metastases) that originate from malignant tumors in other parts of the body. Cancer cells from lung cancer often spread to the adrenal glands, but other types of cancer can also metastasize to the adrenal glands. Due to their location and rich blood supply, the adrenal glands are most commonly affected by metastasis.
Here you will find further information as well as a selection of specialists and centers for adrenal metastases.
Background Information
The adrenal gland is an organ measuring approximately 3 x 1.5 cm that sits on top of the kidney.
Since humans have two kidneys, there are also two adrenal glands, one on each kidney.
Structurally, the adrenal gland consists of:
- an outer part, the adrenal cortex, and
- an inner region, the adrenal medulla
Both regions produce hormones that are vital to the body, including:
- Cortisol: Affects metabolism and the immune system and is considered an important stress hormone
- Aldosterone: Regulates salt and water balance
- Adrenaline
- Norepinephrine
- Dopamine
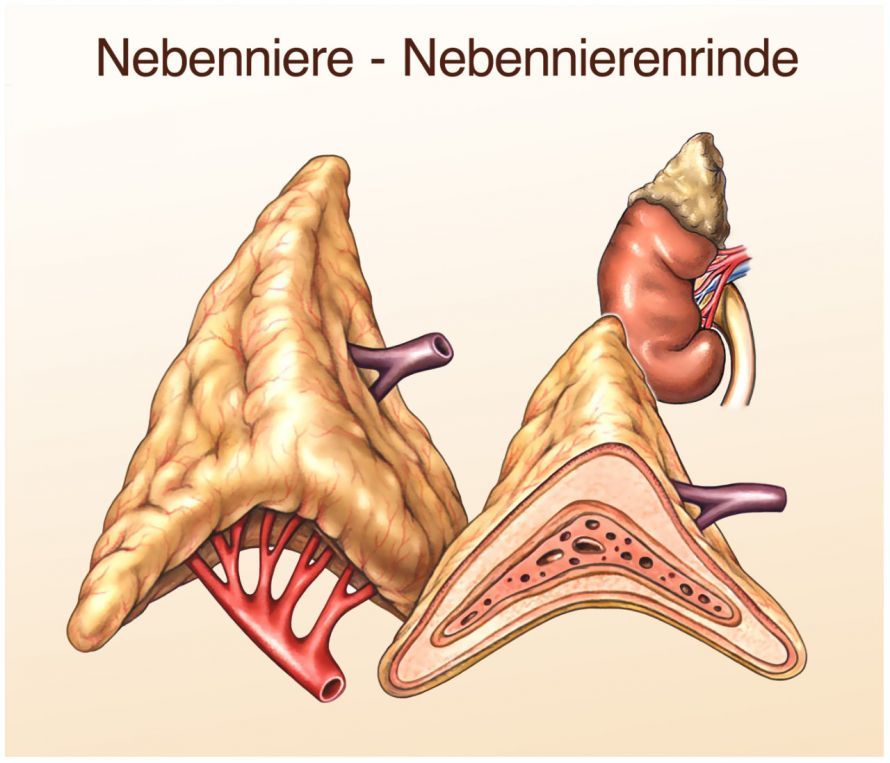
The adrenal gland sits on top of the kidney, as shown in the upper right. Metastases often form in the adrenal gland © Henrie | AdobeStock
Types of Adrenal Tumors
Various tumors or space-occupying lesions can form in the adrenal glands.
Metastases are, for example, secondary tumors that originate from a primary tumor elsewhere in the body. The cancer cells travel to the adrenal gland via the bloodstream or the lymphatic system and form secondary tumors there.
Lung cancer is often the primary tumor. Adrenal metastases are among the most common tumors. About half of all adrenal tumors are metastases.
However, adrenal metastases should not be confused with adrenal cancer (adrenal carcinoma). Unlike metastases, adrenal cancer forms directly in the adrenal glands.
Other space-occupying lesions of the adrenal glands include:
- benign tumors (adrenal adenoma) and
- pheochromocytomas (usually a benign tumor of the adrenal medulla).
Symptoms
The adrenal glands produce important hormones. The growth of a metastasis in the adrenal gland can cause changes in metabolism.
For example, a metastasis in the adrenal cortex displaces the cortisol-producing tissue. As a result, the adrenal gland produces too little cortisol.
This very often leads to adrenal insufficiency, which is called Addison’s syndrome or Addison’s disease.
Symptoms of Addison’s disease include, among others:
- Fatigue
- Weakness and
- Dizziness
Causes and Risk Factors
An adrenal metastasis is always caused by cancer in another organ.
For example, the primary tumors are located in the following organs:
- Lungs (especially in cases of small-cell lung cancer)
- Breast (in breast cancer)
- Kidney (in cases of kidney cancer or renal cell carcinoma)
- Stomach (in cases of stomach cancer)
- Pancreas (also called the pancreas; in pancreatic cancer)
- Ovary (also called the ovary; in ovarian cancer or ovarian carcinoma)
- Large intestine (also called the colon; in colorectal cancer, this usually refers to colon cancer or colon carcinoma)
Whether cancer metastasizes to the adrenal glands depends on the following factors:
- The malignancy of the primary tumor
- The stage at which doctors diagnosed the cancer, and
- The success of cancer treatment
The later doctors detect the cancer, the more likely it is that metastases have formed in other organs, such as the adrenal glands.
For example, at the time of diagnosis of bronchial carcinoma, kidney cancer, or melanoma, about 15 percent of all patients already have adrenal metastases.
Examination and Diagnosis
Doctors typically detect adrenal metastases:
- as part of staging tests—that is, during a targeted search for metastases following a cancer diagnosis—or
- during follow-up examinations of cancer patients who have already undergone treatment
In some cases, adrenal metastases are incidental findings during a computed tomography (CT) scan or an ultrasound examination.
When doctors discover tumors by chance, they are called incidentalomas.
Adrenal metastases are very easily detected on a CT scan. If abnormalities are found in the adrenal gland on a CT scan or ultrasound, doctors check to see if they are metastases.
To do this, they re-examine the adrenal gland using imaging techniques with higher resolution.
The following diagnostic methods are also used:
- Contrast-enhanced CT
- Magnetic resonance imaging (MRI) or
- A combination of positron emission tomography (PET) and CT (known as PET-CT)
In addition, doctors typically order tests to measure cortisol and other laboratory parameters in the blood and/or urine.
Hormone testing can rule out other conditions (such as Cushing’s syndrome or a pheochromocytoma).
If suspicion of an adrenal metastasis increases, doctors will take a tissue sample.
The suspicion is strengthened by:
- the detection of a primary tumor
- the tumor being visualized on a CT scan, and
- the exclusion of a pheochromocytoma through hormonal testing
To obtain the tissue sample, doctors insert a fine needle through the skin into the adrenal gland under CT guidance.
During this fine-needle biopsy, they collect tissue samples, which are then examined histologically under a microscope by a pathologist.
The tissue sample allows for a definitive determination of whether a metastasis or another tumor is present.
General Information on Treatment
Treatment of adrenal metastases is tailored to the patient’s individual situation.
It depends on whether the primary tumor has already been removed or whether it is even removable.
Possible treatment options include:
- Surgical removal of the metastasis along with the adrenal gland (adrenalectomy)
- Chemotherapy
- Local destruction of the tumor using heat generated by high-frequency current (radiofrequency ablation)
- Radiation therapy
If possible, the goal is surgical removal of the metastasis: Doctors can remove smaller metastases during a laparoscopy.
Larger metastases are removed via open abdominal surgery.
If doctors must remove the adrenal gland, the body may still be able to produce hormones via the second adrenal gland. If that is not possible, the patient may need to take cortisol temporarily or permanently.
Course and Prognosis
The prognosis depends largely on:
- the type of cancer underlying the adrenal metastasis,
- how far the cancer has already progressed, and
- whether successful treatment has been administered
However, metastasis always means that the cancer has spread. The primary tumor is therefore already at an advanced stage.
The prognosis—and thus life expectancy—is more favorable if:
- more than two years have elapsed between the diagnosis of the primary tumor and the onset of the adrenal metastasis
- there are no other metastases in other organs, and
- doctors were able to completely remove the cancer
Prevention
You cannot prevent kidney metastases. It is crucial that doctors detect the underlying cancer early to minimize the risk of metastasis.
Therefore, be sure to attend the recommended cancer screening exams regularly.
If you have already had cancer, be sure to keep your follow-up appointments. This is the only way doctors can detect metastases early.
Share this article

About the medical author
Dr. Claus Puhlmann
Medical Author · Medical journalist
Dr. Claus Puhlmann – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.
View full expert profile →Sources
- Chirurgische Arbeitsgemeinschaft Endokrinologie (CAEK) der Deutschen Gesellschaft für Allgemein- und Viszeralchirurgie (DGAV) (2017) S2k-Leitlinie Operative Therapie von Nebennierentumoren. AWMF-Registernummer 088-008. (Download als PDF)
- Fassnacht M, Arlt W, Bancos I et al. Management of adrenal incidentalomas: European Society of Endocrinology Clinical Practice Guideline in collaboration with the European Network for the Study of Adrenal Tumors. Eur J Endocrinol 2016; 175: G1–G34
- Fornara P., Kawan F. (2016) Nebennierenmetastasen. In: Michel M., Thüroff J., Janetschek G., Wirth M. (eds) Die Urologie. Springer Reference Medizin. Springer, Berlin, Heidelberg.
- Deutschbein T, Fassnacht M (2017) Erste Europäische Leitlinie zum Nebennieren-Inzidentalom. Bayerisches Ärzteblatt 4: 144ff.
- Shumarova SY (2016) Management of isolated adrenal metastases. Khirurgiia (Sofiia) 82(2):87-96
- Spartalis E et al. (2019) Metastatic Carcinomas of the Adrenal Glands: From Diagnosis to Treatment. Anticancer Res 39(6):2699-2710. doi: 10.21873/anticanres.13395







