
Surgery for ulcerative colitis usually involves a proctocolectomy, i.e., the removal of the large intestine and rectum. After the proctocolectomy, the surgeon creates a kind of artificial rectum from a section of the small intestine. This is intended to take over the function of the removed rectum. In this way, the patient usually remains continent, thereby avoiding the need for a permanent colostomy.
Here you will find further information as well as a selection of specialists and centers for ulcerative colitis surgery.
The Goal of Ulcerative Colitis Surgery
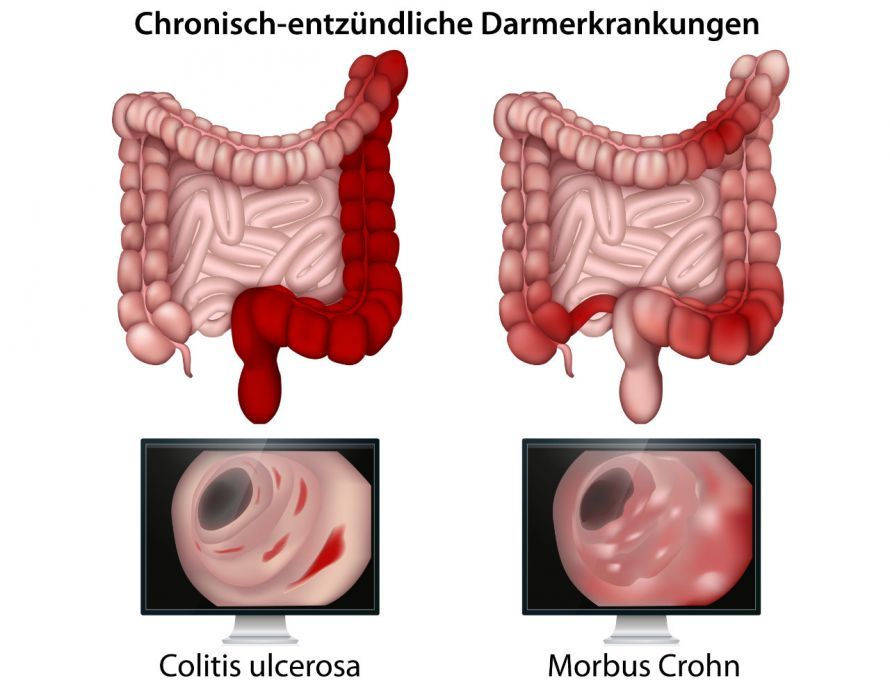
Ulcerative colitis is limited to the large intestine (colon). Therefore, a colectomy (removal of the large intestine) or proctocolectomy can effectively cure the disease.
Surgery for ulcerative colitis can also reduce the risk of colon cancer and prevent toxic megacolon.
Another important goal of the surgery is to preserve sphincter function. For this reason, after the large intestine is removed, the small intestine is connected to the sphincter margin. This often makes it possible to avoid the need for a colostomy.
When is surgery for ulcerative colitis performed?
The following are indications for ulcerative colitis surgery—that is, reasons for performing the procedure:
- The procedure is necessary in cases of colitis-associated carcinoma (colon carcinoma, colon cancer).
- In cases of precancerous lesions (low-grade intraepithelial neoplasia), the procedure may be performed, but alternatives may also be available.
- In cases of toxic megacolon (dilatation of the large intestine with harmful accumulations of intestinal contents), there is an urgent indication for ulcerative colitis surgery.
- In cases of free perforation (a hole in the bowel), there is an emergency indication for ulcerative colitis surgery.
Surgery is also necessary if ulcerative colitis
- does not respond to medical treatment or
- there is a risk of complications, such as severe bleeding.
Surgery may also be considered to prevent colon cancer or to reduce the amount of medication required.
Preparing for Ulcerative Colitis Surgery
Ulcerative colitis surgery—that is, the removal of the large intestine—is a major procedure. To ensure that it proceeds without complications and heals as desired afterward, careful preparation of the patient is necessary.
One general measure is improving heart and lung function. To this end, the patient should perform breathing exercises and refrain from smoking.
No later than the day before ulcerative colitis surgery, the patient must completely empty their bowels. To do this, they are given a laxative solution to drink along with detailed instructions on how to take it and what to eat.
Procedure for Ulcerative Colitis Surgery
During ulcerative colitis surgery, at least the affected sections of the large intestine are removed. In most cases, however, surgeons remove the entire large intestine and the rectum. Only then is the patient cured of the disease.
If the sphincter muscle is still functioning properly, the natural anus can be preserved. This is possible in approximately 90% of cases.
In many cases, ulcerative colitis surgery can be performed using a minimally invasive technique. In such cases, no large incision is necessary.
However, if there are too many adhesions in the abdomen or too many affected sections of the intestine, doctors perform open surgery. In this case, they make a vertical incision in the center of the abdomen.
After removing the large intestine, the bowel passage is reconstructed. To do this, the surgeon extends the small intestine and secures it above the anal sphincter (ileoanal anastomosis).
The surgeon then forms a so-called J-pouch from loops of the small intestine. A pouch is a reservoir designed to replace the function of the rectum—that is, the storage of intestinal contents prior to evacuation. This procedure is known as restorative proctocolectomy.
Artificial Bowel Opening Following Surgery for Ulcerative Colitis
In the past, an artificial small-bowel outlet (ileostomy) was necessary because the large intestine, including the sphincter muscle, was completely removed. With the pouch construction, there is no longer an absolute necessity for a permanent artificial bowel outlet.
However, if the sphincter muscle cannot be preserved, a permanent ileostomy must be created.
Temporary ostomy following ulcerative colitis surgery
In most cases, the surgeon creates a temporary stoma. This protects the fresh intestinal sutures (anastomosis) after surgery.
A temporary ileostomy is also intended to spare the affected sections of the intestine so that they can heal more effectively.
Bowel Movements After Ulcerative Colitis Surgery
Before surgery, a patient with severe ulcerative colitis may have bowel movements up to 30 times a day. After surgery for ulcerative colitis, the frequency of bowel movements ideally decreases to about 5 to 10 times a day.
However, after surgical treatment, the stool will always remain somewhat thinner or mushy.
Complications of ulcerative colitis surgery
Before ulcerative colitis surgery, the doctor discusses the possible complications with the patient. As with all abdominal surgeries, complications such as
- postoperative bleeding,
- wound healing disorders,
- injury to adjacent organs,
- bowel kinks, and
- adhesions
may occur.
In rare cases, surgery for ulcerative colitis can also lead to peritonitis, which may be life-threatening. The risk of this increases significantly if the suture connecting the two remaining ends of the intestine does not heal properly and bacterial-laden intestinal contents leak into the abdominal cavity. To prevent this, the intestinal suture is performed with the utmost precision.
Even though the intestine is thoroughly cleaned, bacteria can still enter the abdominal cavity during ulcerative colitis surgery. For this reason, doctors pay close attention to signs of wound infection after the procedure.
Postoperative Care Following Ulcerative Colitis Surgery
After ulcerative colitis surgery, patients are usually cared for in the surgical intensive care unit for a few days.
During or after surgery, doctors insert several tubes, which are removed as soon as possible. These include:
- an endotracheal tube for mechanical ventilation,
- a drainage tube to remove wound secretions from the abdominal cavity,
- a nasogastric tube to prevent postoperative vomiting,
- a urinary catheter to drain urine from the bladder.
Ideally, the patient will be transferred to the general ward the day after surgery. At this point, the patient may begin consuming small amounts of fluids (e.g., tea and, if appropriate, soup). However, fluid balance must still be maintained through IV fluids. The patient will receive pain medication to manage discomfort.
Afterward, the patient should spend as much time as possible out of bed and walk around.
If recovery proceeds optimally, the patient can be discharged as early as six to seven days after the procedure.
After about three months, the bowel suture is checked via X-ray. If the findings are normal, the doctors can then close the stoma.
Following surgery for ulcerative colitis, lifelong care by an experienced internist is recommended.

About the medical author
Dr. Claus Puhlmann
Medical Author · Medical journalist
Dr. Claus Puhlmann – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.
More about the medical author →




















