
Trabeculectomy is a well-established procedure in glaucoma surgery and is frequently used to treat glaucoma. The goal of this procedure is to reduce elevated intraocular pressure in the eye over the long term. It involves creating an artificial drainage channel for the aqueous humor so that it can drain more effectively. This form of glaucoma treatment is usually used when eye drops or other therapies are not sufficient.
During the surgery, a so-called drainage pocket is created under the conjunctiva. The procedure is performed surgically under anesthesia at a specialized eye clinic. Modern techniques, such as the use of mitomycin C, help reduce scarring. Careful follow-up care is crucial to the success of trabeculectomy.
Background on Glaucoma
The hollowing out of the optic nerve is known as glaucoma. The steadily progressing damage to the optic nerve causes more and more areas of the retina to become inaccessible. These areas then gradually disappear from the visual field and turn black.
Without treatment, the patient will go blind as the disease progresses. Therefore, it is advisable for patients to see a specialist as soon as possible if they suspect they have glaucoma. The specialist can make a diagnosis and initiate treatment.
The exact cause of glaucoma has not yet been conclusively determined. The most common trigger is an increase in intraocular pressure due to an excess of aqueous humor in the eye.
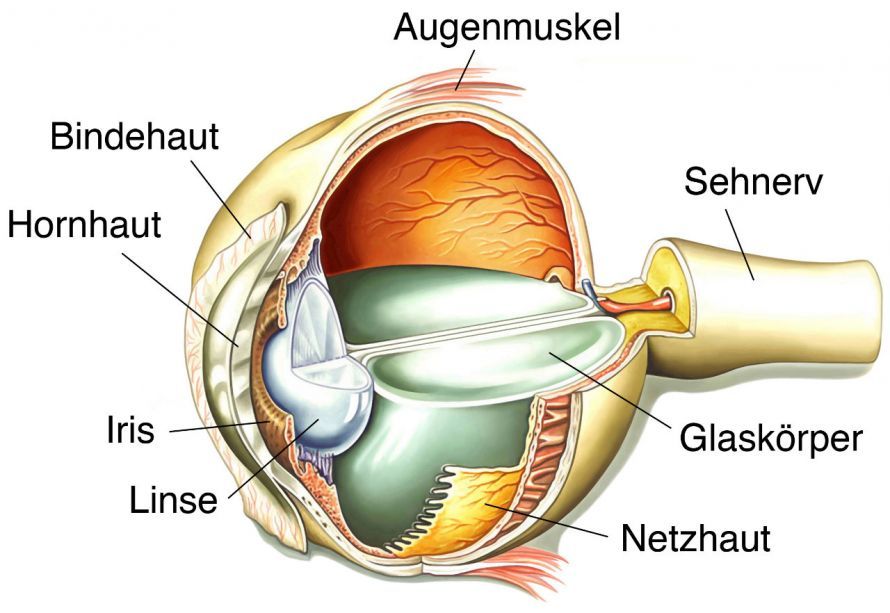
The optic nerve can withstand only a certain level of intraocular pressure without damage. If the pressure rises above this threshold, damage to the nerve tissue will occur without glaucoma surgery. Even a brief but intense surge in pressure can be sufficient to cause this damage.
The optic nerve is particularly at risk; it originates at the retina and exits the eyeball toward the back at the so-called optic disc.
Medication can help reduce the pressure to some extent. However, only a trabeculectomy provides a lasting solution.
Nerve damage caused by glaucoma is irreversible; that is, the damaged areas of the nerve cannot be restored. Therefore, treatment should be initiated as soon as possible. The goal is to prevent further damage to the nerve tissue.
Preliminary Examinations for Trabeculectomy
It should be determined beforehand whether a laser surgical procedure might be a suitable alternative to trabeculectomy. Often, a laser procedure is a suitable option, in which the doctor partially ablates the cells near the ciliary body that are causing the fluid outflow. This results in a decrease in intraocular pressure.
However, depending on the eye’s condition, a conventional trabeculectomy may be a better option. When performed correctly and followed by careful postoperative care, it is a highly effective method for lowering intraocular pressure. If the glaucoma is already at an advanced stage, trabeculectomy is the appropriate treatment in almost all cases.
A trabeculectomy can be performed under either local or general anesthesia. The doctor must carefully weigh the success of the treatment against the risks of general anesthesia.
Local anesthesia avoids the risks of general anesthesia. However, general anesthesia is more comfortable for both the patient and the surgeon and makes the procedure easier. The final decision, however, rests with the patient. To make this decision, the patient needs sufficient information about the advantages and disadvantages of both options.
Procedure for a Trabeculectomy
In a trabeculectomy, a surgical opening is created to allow excess aqueous humor to drain. This creates a kind of pressure valve: when intraocular pressure becomes too high, aqueous humor can drain away, and the pressure drops again before further damage occurs to the optic nerve.
Trabeculectomy is therefore considered the standard procedure for treating glaucoma.
Creating a Valve
During a trabeculectomy, an opening is created in the sclera (the white part of the eye) to allow aqueous humor to drain. The accumulation of aqueous humor under the conjunctiva forms a “drainage pocket.”
This is where the fluid that has drained from the interior of the eye can initially collect. Later, it flows under the connective tissue of the eye and is reabsorbed by the body there.
The surgeon also creates a flap from the underlying sclera beneath the conjunctiva. After the rest of the surgery is successfully completed, the surgeon sutures this flap in such a way that, when intraocular pressure is high, a greater amount of fluid can drain toward the second, deeper opening.
The surgeon creates this second opening in the deeper layer of the eyeball’s skin. The incision required for this is made directly beneath the previously excised scleral flap. The goal here is to create a “drainage channel.” Through this channel, the aqueous humor can drain from the “fluid reservoir” or “drainage cushion.”
The surgeon’s experience and skill are of great importance here. He must assess the necessary degree of laxity of this “pressure valve” and carefully place a suture.
The surgeon must also take wound healing into account. After trabeculectomy, fluid from the eye is intended to enter the “fluid reservoir” created by the proper suturing of the scleral flap. From there, it can drain through the second, deeper opening.
Checking Valve Function
The doctor checks that the scleral valve flap is functioning correctly during the procedure by performing a careful water test.
Aqueous humor that flows over the iris after surgery can restrict the patient’s field of vision. To prevent this, the doctor removes a small portion of the iris. This removal of part of the iris during trabeculectomy is also referred to as an iridectomy.
Trabeculectomy does not always sufficiently lower intraocular pressure. In such cases, a second procedure may be necessary at a later date.
Risks of Trabeculectomy
Many patients report astigmatism after a trabeculectomy. It is caused by the sutures placed during the procedure. Astigmatism is not uncommon and usually improves quickly with successful follow-up care. If the surgeon uses dissolvable sutures, this can pose an additional risk to the patient. If the suture dissolves inside the eye, it can trigger an inflammatory reaction.
A serious complication of trabeculectomy can be the development of cataracts in the treated eye. However, with current medical technology, this can usually be treated without difficulty using standard procedures.
In some cases, a fibrin reaction occurs following glaucoma surgery. Rarer complications, such as
- retinal detachment or
- the onset of double vision
and their causes usually require doctors to investigate them more thoroughly on a case-by-case basis.
The natural healing process leads to scarring of the trabecular meshwork, a condition known as capsular opacification. This capsular opacification often hinders the success of the surgery, as it causes intraocular pressure to rise again. To reduce capsular opacification, a procedure known as needling can be performed.
In this procedure, 5-FU is injected directly into the scarred tissue via syringes. The tissue is loosened through punctures or incisions, allowing the filtration bed to resume its function. It is also possible to treat such encapsulation of the drainage bed using 5-FU alone, without needling.
Encapsulation of the drainage pad following a trabeculectomy is a well-known and widely discussed issue. One possible option would be to support the function of an inadequately functioning drainage bed by administering medication. If the scarring cannot be controlled with postoperative measures, a second trabeculectomy may be necessary.
Monitoring the Success of the Surgery
The goal of the procedure is to achieve long-term regulation of intraocular pressure.
Close monitoring of treatment success after surgery is essential. The permeability of the “drainage cushion” must also be ensured and monitored. These follow-up examinations take place at short intervals after the procedure. The patient should attend these appointments diligently!
A useful test for monitoring intraocular pressure on the day after trabeculectomy is the daily pressure profile (TTP). In most cases, this allows doctors to effectively identify short-term spikes in pressure. Renowned ophthalmologists believe that, in many cases, these spikes in intraocular pressure cause damage to the optic nerve.
Nerve damage that has already occurred due to elevated intraocular pressure cannot be reversed by surgery.
Conclusion
Trabeculectomy is considered the gold standard of glaucoma surgery and is a proven surgical procedure for lowering intraocular pressure in glaucoma. The goal of this surgical method is to create an artificial outflow pathway for the aqueous humor, allowing it to drain from the eye in a controlled manner. During the procedure, an incision is made in the scleral flap in the anterior chamber to reduce drainage resistance in the trabecular meshwork. The aqueous humor is artificially directed outward and collects beneath the conjunctiva in the area of the drainage pad.
The success of the surgery depends largely on good wound healing and controlled scar formation, particularly to prevent scarring of the trabecular meshwork. Medications such as 5-FU are often used to support and guide the healing process. In the days following surgery, closely monitored postoperative care is crucial for maintaining stable intraocular pressure. Regular measurement of intraocular pressure helps monitor the success of treatment and detect potential risks and complications early on.
Alternatives such as canaloplasty or trabeculotomy, as well as minimally invasive procedures like canaloplasty, offer a gentler treatment option in certain cases. Implant surgery or the use of microcatheters may also play a role. Nevertheless, trabeculectomy often remains the most effective option for patients with elevated intraocular pressure to lower intraocular pressure and protect the optic nerve in the long term. In some cases, a portion of the iris is also removed, or aqueous humor production is reduced by sclerotherapy of the ciliary body.
Despite the good results, complications such as infection or excessive scarring can occur, which is why careful management with eye drops and, if necessary, additional medication is required. Overall, this surgical method has proven to be an effective and long-term solution for treating elevated intraocular pressure and preventing subsequent damage to the interior of the eye.
FAQ
What is a trabeculectomy?
A trabeculectomy is a surgical procedure to treat glaucoma in which an artificial drainage channel for aqueous humor is created. This lowers intraocular pressure and reduces the risk of damage to the optic nerve.
When is a trabeculectomy performed?
This procedure is performed when eye drops or other medical treatments are insufficient to lower intraocular pressure. The surgery is particularly beneficial in cases of advanced glaucoma.
How does the surgery work?
During a trabeculectomy, a small incision is made in the sclera so that aqueous humor can drain from the anterior chamber. A drainage pocket forms under the conjunctiva, allowing the fluid to drain.
What are the risks?
Possible risks and complications include scarring, infection, or an insufficient reduction in intraocular pressure. Close follow-up care helps detect these issues early on.
What are the alternatives to trabeculectomy?
Alternatives include minimally invasive procedures such as canaloplasty or trabeculotomy. Implant surgery may also be an option, depending on the severity of the glaucoma.
