
The umbrella term “pulmonary hypertension” (PAH for short) refers to a wide range of different conditions in which the pressure in the pulmonary vessels is too high. As a result of increased vascular resistance, blood pressure in the pulmonary circulation also rises. This leads to complications and disruptions in the exchange of gases between the heart and the lungs. As a result, those affected often feel weak, exhausted, and experience a decline in physical performance. The symptoms of PAH can be confused with many other conditions and are often dismissed by those affected as simply feeling off that day.
Here you will find further information as well as a selection of pulmonary hypertension specialists and centers.
Definition: What is pulmonary hypertension?
The mean arterial blood pressure in the lungs is normally lower than in the rest of the body. It is 15 mmHg compared to 80–100 mmHg in the rest of the body. If this value rises above 20 mmHg, it is referred to as latent PAH. A sustained value above 25 mmHg indicates the clinical picture of manifest pulmonary hypertension.
In most cases, the first signs of organ failure appear when the mean arterial pressure reaches 30 mmHg. At a mean pressure of 50 mmHg or higher, cardiac output decreases noticeably. Physical performance is reduced, and circulatory collapse—potentially leading to cardiac arrest—may occur.
Pulmonary hypertension has a poor prognosis. Therefore, it is important to diagnose and treat it early.
If pulmonary hypertension progresses to a chronic form, the damage to the body becomes irreversible. At that point, only a transplant can prevent a fatal outcome.
That is why it is important not to underestimate the symptoms and to seek medical advice sooner rather than later.
What are the causes of pulmonary hypertension?
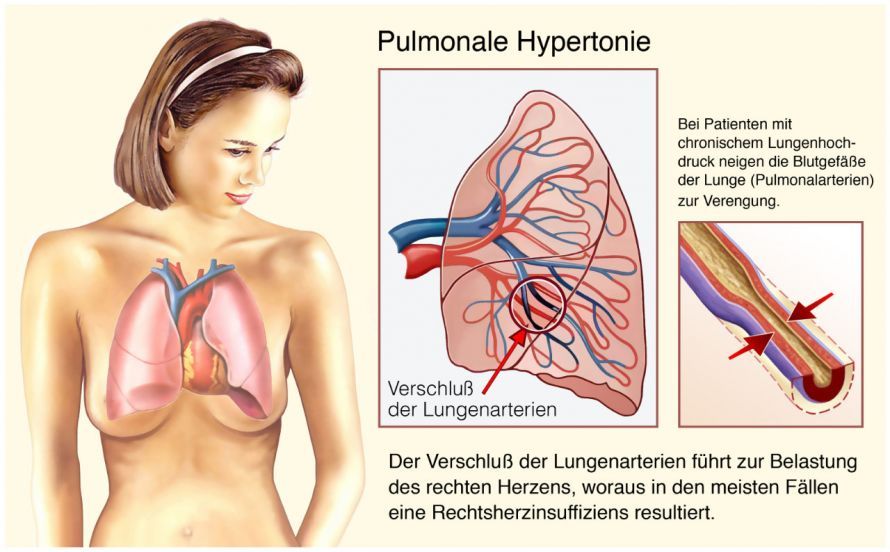
Pulmonary hypertension results from constriction (narrowing) of the blood vessels in the lungs. The blood vessels are constricted by muscle contractions in the vessel walls. This can be caused by
- excessive blood flow in the pulmonary circulation or
- insufficient oxygen supply
.
In addition to acute pulmonary hypertension, there is a chronic form. In the chronic form, the pulmonary blood vessels undergo a structural change. As the vascular muscle tissue increases, connective tissue—which develops from the muscle tissue—gradually grows into the structure of the vessels. This restricts the vessels’ ability to expand and contract. At this stage, pulmonary hypertension is irreversible.
Pulmonary hypertension usually occurs as a secondary condition associated with another medical condition. Left heart failure, in particular, triggers symptoms of PAH. The left side of the heart is then no longer able to perform its pumping function with its usual strength. This causes blood to back up. This backflow then leads to the vascular changes.
Pulmonary hypertension also frequently develops in connection with lung or heart conditions such as thrombosis or pulmonary embolism. Due to fluctuations in blood composition, blood clots can form in the pulmonary vessels and block the bloodstream (pulmonary embolism).
In most cases, a pulmonary embolism resolves without being noticed. In life-threatening cases, however, it causes a blockage in the pulmonary circulation and, due to the blood congestion in the lungs, contributes to pulmonary hypertension.
What are the symptoms of pulmonary hypertension?
Unfortunately, pulmonary hypertension does not present with a uniform set of symptoms. Depending on the severity of the disease, various symptoms may develop. In most cases of PAH, patients experience
- shortness of breath,
- fatigue, and
- fatigue.
Dizziness and heart palpitations are also among the most common physical signs of the disease. In addition, there are a variety of other symptoms that do not necessarily occur together.
The following symptoms often indicate pulmonary hypertension:
- Shortness of breath and difficulty breathing,
- circulatory problems/circulatory collapse,
- sudden loss of consciousness (syncope),
- fatigue and general malaise,
- angina pectoris,
- frequent coughing,
- Raynaud’s syndrome (vascular spasms and poor blood flow in the toes and fingers),
- cyanosis (bluish discoloration of the mucous membranes or skin),
- peripheral edema (fluid retention in the interstitial tissue),
- chest tightness,
- tricuspid valve insufficiency (a heart valve belonging to the group of semilunar valves).
How is pulmonary hypertension treated?
The prognosis for pulmonary hypertension is usually poor. The five-year survival rate for patients with a mean pressure above 30 mmHg is only 30%. When the mean pressure exceeds 50 mmHg, the survival rate is even lower. Treating this condition is difficult.
After an initial visit to the primary care physician, the patient is usually referred to a cardiologist (heart specialist) if pulmonary hypertension is suspected. If the cardiologist determines that the cause lies in complications of the pulmonary circulation, the patient is then referred to a pulmonologist (lung specialist).
Acute pulmonary hypertension should be treated in such a way that it does not progress to a chronic form. In most cases, two treatment methods are combined. One treatment method involves identifying potential causes and addressing them. A second treatment method aims to slow the progression of the disease.
To restore normal blood flow, the resistance in the blood vessels must be reduced. Medications such as
- PDE-5 inhibitors,
- calcium channel blockers, or
- prostacyclin derivatives.
Patients must follow strict guidelines to support the treatment of the disease. They must make lifestyle changes and avoid certain things, including:
- prolonged physical exertion,
- vigorous exercise
- nicotine, and
- alcohol.
Chronic PAH is irreversible, and its symptoms can only be alleviated. Pain relievers and medications to manage symptoms are used for this purpose.
A cure is now only possible through a lung or heart transplant using a donor organ.
Share this article

Sources
- Hoeper MM et al., Pulmonale Hypertonie. Dtsch Arztebl Int 2017; 114(5):73–84; doi:10.3238/arztebl.2016.0073
- Opitz C et al., ESC-Leitlinie 2015: Diagnostik und Therapie der pulmonalen Hypertonie. Dtsch Med Wochenschr 2016; 141:1764–1769
- flexikon.doccheck.com/de/Pulmonale_Hypertonie



