
Chronic inflammatory bowel diseases are long-term intestinal disorders caused by a misdirected immune response that triggers persistent inflammation in the digestive tract. Among the most common forms are Crohn’s disease and ulcerative colitis, which occur in flare-ups and can affect both the intestines and other organ systems. Modern gastroenterological therapies now allow for better control of disease activity and longer periods with fewer symptoms.
Definition of Intestinal Diseases
Chronic inflammatory bowel diseases (IBD) refer to conditions characterized by inflammatory changes in the intestinal mucosa. These conditions result from a severe immune reaction directed against bacterial or other structures. They progress in cycles of remission and flare-ups.
The symptoms include diarrhea—which may sometimes be bloody—and abdominal pain.
The main clinical presentations are:
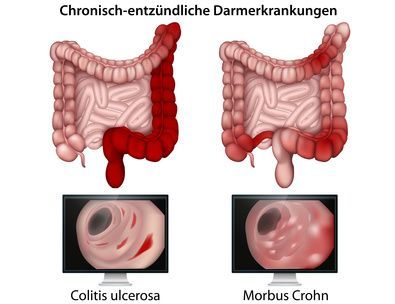
- Crohn’s disease: affects the entire digestive tract in segments, penetrating deep into the mucosa
- Ulcerative colitis: continuous inflammation of the intestinal mucosa of the large intestine
Other variants include colitis indeterminata or, in rare cases, inflammatory bowel processes. If left untreated, these conditions can lead to strictures, fistula formation, complications, or significant weight loss.
In Germany, approximately 360,000 people are affected by IBD. The annual incidence rate is about 10 per 100,000 inhabitants, meaning that approximately 7,600 to 8,400 people are newly diagnosed with IBD each year.
Causes of Inflammatory Bowel Disease
The exact cause of inflammatory bowel disease remains unclear to this day. The interplay of various factors is considered to be multifactorial.
Genetic predisposition: Many patients carry genetically determined risk variants that influence the activity of the immune system and lead to a higher incidence of both diseases within families.
Environmental factors & the microbiome: Changes in gut flora, dietary habits, stress, infections, and other environmental factors can promote inflammatory processes. A bacterial-triggered dysregulation of the immune system also plays a role.
Immunological malfunctions: A misdirected immune response targets structures of the intestinal mucosa, which contributes to long-term tissue damage.
Symptoms and effects of this disease
Common symptoms of chronic inflammatory bowel diseases include severe diarrhea accompanied by cramping, intense abdominal pain. Fever, blood in the stool, and a general feeling of physical weakness may also occur simultaneously. Various factors interact in each patient. As a result, the severity of symptoms varies.
The inflammation in the intestine also affects the entire body and can manifest as conditions affecting the skin, eyes, and joints (extraintestinal manifestations).
The disease has a particularly severe impact when bowel function is no longer fully intact. In such cases, the intestine can no longer adequately absorb and process food.
In this case, the following occur:
- weight loss,
- malnutrition, and
- deficiencies.
IBD can also lead to such malnutrition if large sections of the small intestine are affected. This can be the case with Crohn’s disease.
If a very high loss of protein is no longer compensated for by adequate dietary intake, life-threatening conditions can develop.
Of course, diarrhea can also be caused by other conditions. However, if it persists for more than six weeks, it is rarely due solely to a gastrointestinal infection ( gastroenteritis ). In such cases,
- an IBD,
- a dysfunction of the digestive glands (e.g., the pancreas), or
- a malfunction of the digestive enzymes in the intestinal mucosa
are likely causes.
Diagnosis of IBD | Crohn’s Disease and Ulcerative Colitis
To reliably diagnose inflammatory bowel disease, a comprehensive evaluation by a specialist is of great importance. The doctor reviews the patient’s individual medical history and takes into account all factors that could be triggers. This so-called medical history includes information on any stress the patient may be experiencing, diet, other personal medical conditions, and possible family history of disease.
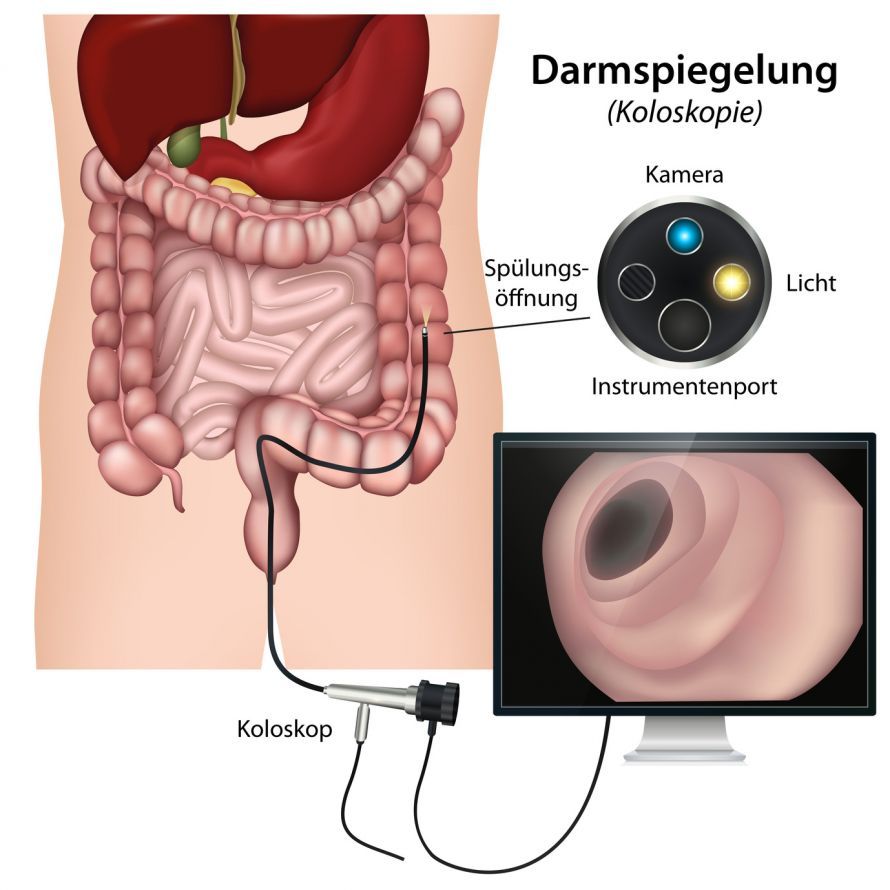
Imaging techniques are used to aid in the diagnosis. An ultrasound examination and a colonoscopy with a tissue sample (biopsy) provide important clues. The colonoscopy can be performed under light anesthesia. Virtual procedures that do not require an endoscope are also possible.
A complete blood count and stool sample are other important methods for diagnosing IBD. If blood values are elevated, the lab results indicate inflammation in the body or the intestines:
- elevated white blood cell count,
- elevated C-reactive protein,
- elevated erythrocyte sedimentation rate.
The stool sample is first examined for an acute bacterial infection. Other markers of inflammatory bowel disease include
- elevated calprotectin, a protein produced by immune system cells, and
- elevated lactoferrin levels.
Lactoferrin is also a protein and indicates an ongoing immune response.
IBD has symptoms similar to those of non-inflammatory bowel diseases (such as irritable bowel syndrome). Therefore, testing for inflammatory markers in the blood and stool is an important diagnostic criterion.
Treatment of Inflammatory Bowel Diseases
Treatment is tailored to the course of the disease—including high disease activity, location, and individual progression—and is usually carried out in collaboration with a university hospital, specialized IBD centers, or experienced gastroenterologists.
The goal of drug therapy is to control inflammation and prolong symptom-free periods. Key active ingredients include corticosteroids for treating acute flare-ups, azathioprine for long-term control, biologics (e.g., monoclonal antibodies), tofacitinib and other JAK inhibitors, as well as anti-inflammatory and immunomodulatory medications.
Depending on the medication, administration is oral, subcutaneous, or intravenous. This medication-based therapy reduces long-term damage and prevents flare-ups.
Surgery becomes necessary if severe complications, uncontrollable inflammatory activity, fistulas, or strictures occur. Visceral surgeons remove affected sections of the intestine while preserving as much tissue as possible and, ideally, maintaining bowel function.
Prognosis
The course of the disease varies greatly from person to person. Many people experience stable remissions, while others go through recurring flare-ups. Modern therapies and care at specialized centers can significantly reduce the burden of the disease. In the long term, early diagnosis, consistent treatment, and regular follow-up examinations improve the prognosis.
Frequently Asked Questions About Multifactorial Inflammation of the Intestine
Are Crohn’s disease and ulcerative colitis curable?
Both conditions are chronic inflammatory bowel diseases and are currently incurable. However, thanks to modern treatments, long periods of remission are possible.
What diet helps with IBD—chronic inflammatory bowel disease?
There is no one-size-fits-all recommendation. Many patients benefit from individually tailored dietary strategies that reduce symptoms and have
a positive effect on disease activity. When is surgery necessary?
Surgery is necessary in cases of fistulas, strictures, treatment-resistant inflammation, or other complications. The procedure is usually performed at centers specializing in visceral surgery.
How do Crohn’s disease and ulcerative colitis differ?
They differ in terms of the extent and depth of inflammation and the regions affected. In Crohn’s disease, the entire digestive tract may be affected, whereas ulcerative colitis is limited to the large intestine. When the diagnosis is unclear, the condition is referred to as colitis indeterminata.
Share this article

About the medical author
Prof. JoergG. Albert
Medical Author
Prof. Dr. med. Jörg G. Albert – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.
View full expert profile →


























