
Surgery on the esophagus is a complex procedure due to its proximity to vital organs and blood vessels. The surgery can be performed as open surgery or using a minimally invasive approach. The minimally invasive approach has several advantages over traditional open surgery. It is therefore considered the gold standard. Furthermore, the success of surgical treatment depends largely on the surgeon’s experience. Esophageal surgery should therefore be performed by experienced experts at specialized centers.
Here you will find further information as well as a selection of specialists and centers for minimally invasive esophageal surgery.
Definition: Minimally Invasive Surgery
Surgical procedures can be classified as open or closed (minimally invasive).
In open surgical procedures, the surgeon makes larger incisions in the skin to expose the surgical site. The procedure is thus performed on the open body.
A minimally invasive procedure, on the other hand, is performed closed. Only small skin incisions are required. Through these, the surgeon inserts miniaturized endoscopic instruments, such as
- forceps,
- scissors,
- irrigation and suction devices,
- suturing instruments, and
- a video camera.
The video system displays an image—in some cases even in three dimensions—on a monitor. This provides a clear view of the surgical site. Minimally invasive, endoscopic procedures in the abdominal cavity are called laparoscopy; those in the chest cavity are called thoracoscopy.
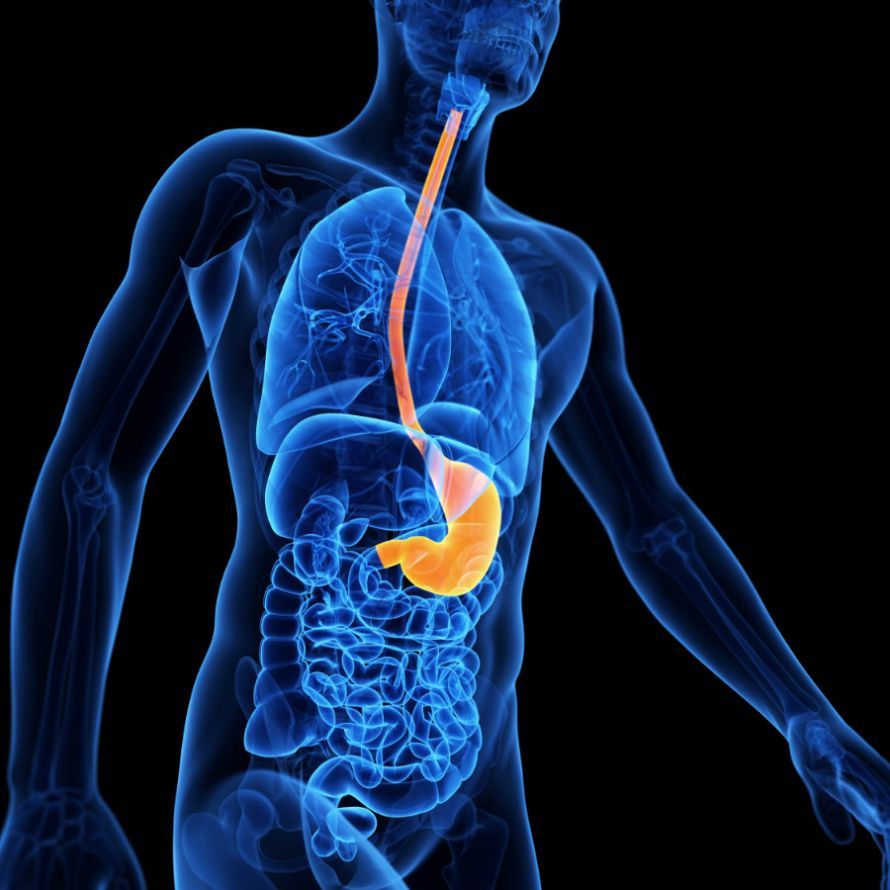
From a functional perspective, the esophagus is a relatively simple organ. It transports food from the mouth to the stomach. However, its location behind the lungs makes it difficult to access surgically. During a procedure, there is a risk of
- the lung,
- the large blood vessels located nearby,
- the spleen, or
- the diaphragm
. For this reason, esophageal surgery presents a complex challenge fraught with complications from a surgical standpoint.
Reasons for Treatment
In minimally invasive surgery, fewer complications occur due to the reduced extent of surgical trauma. For this reason, minimally invasive surgery is now the standard procedure for esophageal conditions.
In addition to the reduced risk of complications, minimally invasive procedures generally offer the following advantages over open surgery:
- Less pain after surgery, allowing the patient to get up and move around sooner. This reduces the risk of thrombosis.
- Earlier discharge from the hospital.
- Better cosmetic results due to smaller scars.
- Fewer wound healing complications occur.
Today, most patients with esophageal conditions can be treated using minimally invasive techniques.
In some cases, however, a minimally invasive procedure is not possible, and the surgery must be performed as an open procedure. The following contraindications preclude minimally invasive surgery:
- Adhesions and scar tissue from previous surgeries
- Infections of the skin or abdominal wall
- Inflammation of the peritoneum (peritonitis) or pleura (pleuritis)
- Uncontrolled bleeding disorders
- Heart or lung diseases associated with a higher risk during anesthesia.
A typical indication for minimally invasive esophageal surgery is the treatment of
- malignant esophageal tumors (esophageal cancer: esophageal carcinoma),
- precancerous lesions, and
- reflux disease (so-called antireflux surgery).
Other applications include, for example:
- esophageal malformations
- Injuries to the esophagus
- Hiatal hernia: Parts of the stomach protrude through the opening in the diaphragm through which the esophagus passes
- Achalasia: the inability of the lower esophageal sphincter to open sufficiently to allow food to pass into the stomach
- Diverticula (outpouchings) of the esophagus
- Benign tumors of the esophageal muscle (leiomyomas)
Minimally invasive esophageal surgery for esophageal cancer
In cases of advanced esophageal cancer, partial or complete removal of the esophagus is usually necessary. This is referred to as esophageal resection or esophagectomy. Often, the lymph nodes in the abdominal and thoracic cavities must also be removed.
The goal is to completely remove the tumor and create a new connection between the mouth and the stomach or intestine.
Possible Procedures
Two methods have become established for this purpose, which
- open surgery,
- fully minimally invasive, or
- partially open and partially minimally invasive (hybrid procedure)
:
- transhiatal esophagectomy (surgery via the abdomen and neck)
- transthoracic esophagectomy (surgery via the abdomen and chest cavity)
Transhiatal esophagectomy is most commonly used in patients with lung damage and is then performed as an open surgical procedure. Even in difficult cases, surgeons may opt for either the hybrid procedure or the completely open surgical approach.
Performing thoracoscopic-laparoscopic esophagectomy
Due to the slightly better survival rate, many centers perform transthoracic esophagectomy using a minimally invasive approach. This is also referred to as thoracoscopic-laparoscopic esophageal resection.
It involves a combination of two endoscopic procedures:
- laparoscopy (endoscopy in the abdominal cavity) and
- a thoracoscopy (endoscopy in the chest cavity).
The procedure begins as a laparoscopy. With the patient lying on their back, the surgeon inserts the endoscopic instruments into the body through five small incisions in the abdomen. The surgeon then exposes the lower esophagus along with the surrounding lymph nodes. Next, the surgeon reshapes the stomach into a tube so that it can later be connected to the portion of the esophagus remaining in the body. Finally, the surgeon removes the instruments from the body and closes the incision sites.
For the subsequent thoracoscopy, the patient is positioned on their side. Here, too, five skin incisions are necessary, this time on the chest. The surgeon then dissects the esophagus—including the lymph nodes—from the surrounding tissue up to just below the neck.
Exposing the esophagus is difficult due to its close connection
- to the aorta,
- the pericardium,
- the main bronchi, and
- the trachea
is very complex. If the tumor is located in the cervical portion of the esophagus, the area around the neck must also be exposed. In most cases, however, the cervical portion of the esophagus can remain inside the body. The procedure is thus limited to the chest cavity.
The surgeon then pulls the gastric tube—which was prepared in the first step—up into the chest cavity. He removes the esophagus, along with the lymph nodes, from the body through a skin incision approximately five centimeters long. He then connects the gastric tube to the remaining esophagus.
After the endoscopic instruments have been removed, the incisions are closed.
Patients with esophageal cancer require special follow-up care to detect any recurrence of the cancer in a timely manner.
Minimally Invasive Esophageal Surgery for Reflux Disease
Minimally invasive reflux treatment, known as antireflux surgery, is also a common procedure.
The cause of reflux is usually a hiatal hernia, in which the upper part of the stomach slides up into the chest cavity next to the esophagus. As a result, the closing mechanism at the junction of the esophagus and stomach no longer functions properly, and acidic stomach contents flow back into the esophagus.
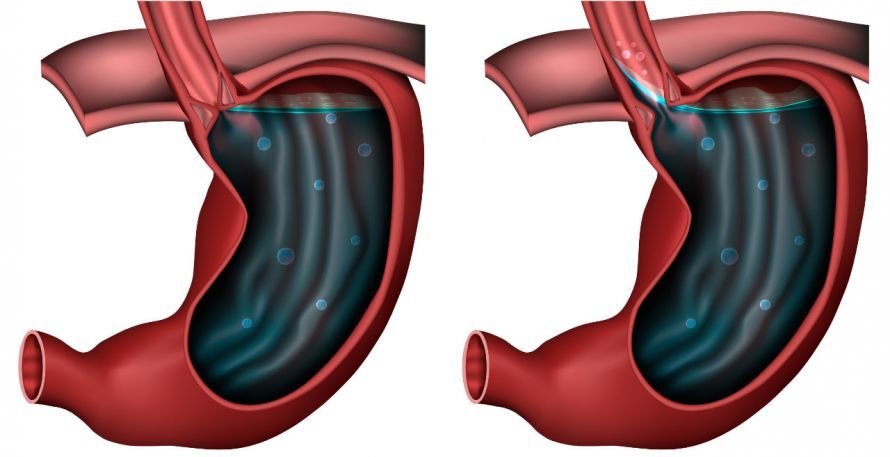
Laparoscopic antireflux surgery (LARO) is recommended for patients
- who respond to treatment with proton pump inhibitors but cannot tolerate them
- who experience reflux symptoms despite treatment with proton pump inhibitors, particularly regurgitation of chyme into the oral cavity
- who, despite treatment with proton pump inhibitors, exhibit atypical reflux symptoms, such as chronic cough, recurrent sinusitis, asthma, sleep-related breathing disorders, hoarseness, tooth erosion, and chest pain.
However, if atypical reflux symptoms are the primary concern, the chances of success with LARO are significantly reduced. LARO is also less effective or, in some cases, unsuitable for patients with
- severe obesity
- irritable stomach
- irritable bowel syndrome
- anxiety disorders and depression
- hypochondria, or mood swings.
After inserting the laparoscopic instruments, the surgeon narrows the widened hiatal opening. A mesh (hiatoplasty) is often used for this purpose.
The surgeon then wraps the gastric dome around the lower end of the esophagus in the form of a cuff (fundoplication). The cuff can be
- be performed completely (laparoscopic Nissen fundoplication)—the most commonly used method—
- partially (laparoscopic Toupet fundoplication) or
- only in the anterior region (laparoscopic fundoplication according to Dor)—the least commonly used variant—
.
Postoperative Care and Follow-Up
After removal of the esophagus, normal oral feeding is initially no longer possible. Instead, nutritional concentrates are administered directly into the intestine, possibly for several months. The patient can prevent malnutrition through the administration of high-energy solutions.
If chyme enters the small intestine too quickly, it can lead to
- an unpleasant feeling of fullness,
- diarrhea,
- pain,
- sweating, and
- tremors
. People affected by this dumping syndrome can prevent it by being mindful of what they eat and drink. It’s important to
- to eat slowly,
- chew thoroughly,
- not to “wash down” food with drinks, and
- avoid liquid foods.
After a fundoplication, patients are usually able to eat a light, bland diet as early as the day after surgery. By the third day, they can usually resume eating normally.
Patients who have undergone a minimally invasive procedure may need to adjust their diet—depending on their condition. For this reason, they are usually provided with nutritional counseling. They may not feel hungry for some time, and they must spread their food and fluid intake over several small, individual portions.
In principle, there is no standard diet; rather, each patient explores what works best for them.
Complications, Risks, and Prognosis
Every surgery carries general risks associated with the procedure. These include, for example,
- infections,
- postoperative bleeding, and
- thrombosis.
In addition, there are specific risks of complications that are due to the unique characteristics of minimally invasive surgery. For example, the insertion of endoscopic instruments can cause bleeding and tears in adjacent tissues.
Since air is insufflated during a minimally invasive procedure, air can accumulate under the skin (cutaneous emphysema). Furthermore, the increase in pressure can lead to complications affecting the heart, lungs, and blood flow.
In rare cases, laparoscopic antireflux surgery can result in
- injuries, particularly to the spleen and other organs,
- the cuff slipping or dissolving into the chest cavity,
- respiratory complications, and
- swallowing difficulties
may occur.
Organ-specific injuries can also occur during esophagectomy. A serious complication arises if the connection between the esophagus and the stomach becomes leaky. This can lead to pneumonia.
Overall, however, the chances of success and the prognosis following minimally invasive procedures on the esophagus are very good. Most patients regain a largely normal quality of life after fundoplication.
The surgery should be performed by experienced surgeons at specialized centers.

About the medical author
Prof. Paul Magnus Schneider
Medical Author · Zurich
Prof. Dr. med. Paul Magnus Schneider – author: Explore expert medical articles in the Leading Medicine Guide.
Sources
- Fein M (2011) Lebensqualität nach Fundoplikatio. Passion Chirurgie 1(2): Artikel 02_01. https://www.bdc.de/lebensqualitaet-nach-fundoplikatio/
- Franzke T, Jähne J (2012) Postoperative Syndrome und Lebensqualität nach Eingriffen am Magen. Allgemein- und Viszeralchirurgie up2date 3. DOI: http://dx.doi.org/10.1055/s-0031-1298551
- „Leitlinienprogramm Onkologie“ der Arbeitsgemeinschaft der Wissenschaftlichen Medizinischen Fachgesellschaften e. V., der Deutschen Krebsgesellschaft e. V. und der Stiftung Deutsche Krebshilfe (2018). Krebs der Speiseröhre. Eine Leitlinie für Patientinnen und Patienten. https://www.awmf.org/uploads/tx_szleitlinien/021-023OLp_S3_Oesophaguskarzinom_2016-09.pdfSchneider PM (2016) Minimalinvasive Chirurgie des Speiseröhrenkrebses. Mittelpunkt 2: 14-15
- Schneider PM (2016) Minimalinvasive Chirurgie des Speiseröhrenkrebses. Mittelpunkt 2: 14-15
- Schneider PM, Grimminger PP (2016) Antirefluxchirurgie bei gastroösophagealer Refluxkrankheit. Gastroenterologe. DOI 10.1007/s11377-016-0052-1















