
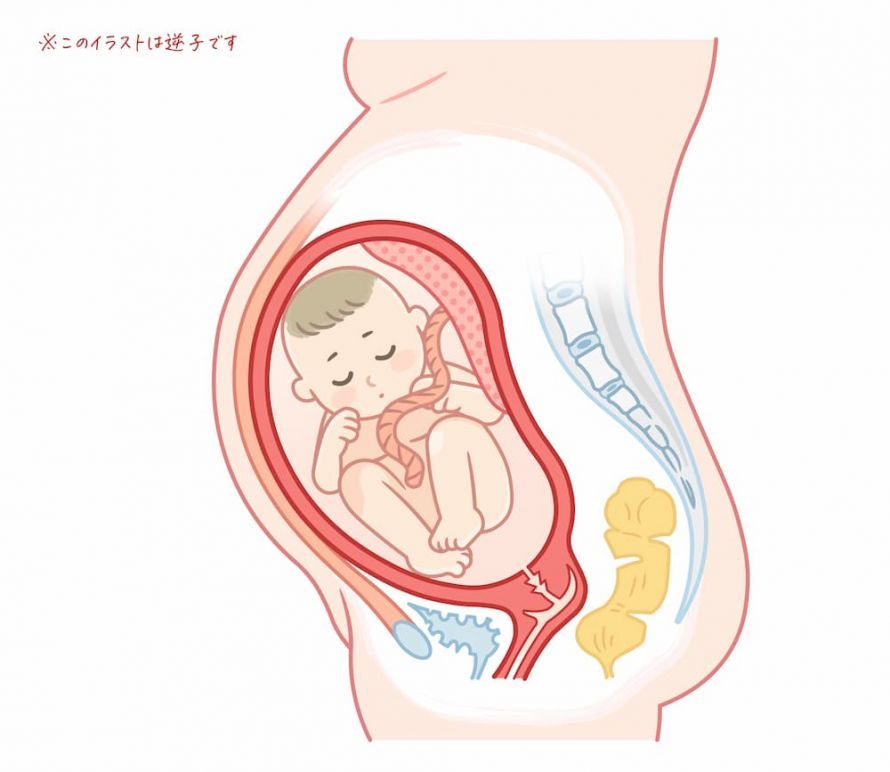
In a breech presentation, the unborn baby lies in the mother’s abdomen with its buttocks facing the pelvic outlet. Normally, by the 32nd week of pregnancy, the baby should have turned so that its head is facing the pelvic outlet. In that case, a natural birth is usually possible.
Below you will find further information as well as a list of selected specialists for breech presentations.
What exactly is a breech presentation?
A breech presentation is one of the so-called presentation abnormalities in which a baby is born head-first.
Doctors also refer to this as a cephalic presentation.
A transverse presentation occurs when the baby is lying across the mother’s abdomen.
If the head is at the top of the uterus and the feet or buttocks are at the bottom, this is a breech presentation.
Depending on the position of the unborn baby, there are different types of breech presentation:
Breech presentation: The baby’s feet are in front of its face or close to its head. In a vaginal birth, the buttocks would therefore emerge first.
Breech-foot presentation: The baby pulls one or both knees toward its abdomen.
Foot presentation: The baby has its legs extended. In this rare form, the baby would be born feet-first.
Knee presentation: In this position, the unborn baby is kneeling.
Causes, Reasons, and Triggers of Breech Presentation
In about half of all cases, no cause for the baby’s abnormal position can be identified.
However, breech presentation is particularly common in women giving birth to their first child.
Studies show that women who were born in a breech position are more likely to give birth to a baby in a breech position.
Many babies do not turn until around the 30th week of pregnancy. Preterm babies born before this time have often not yet turned.
Breech presentations therefore occur with increased frequency in preterm births.
Another risk factor for a breech presentation is a multiple pregnancy.
In such cases, one or both twins or multiples lack the space needed to turn. There is also insufficient space in normal pregnancies with low amniotic fluid (oligohydramnios).
If there is too much amniotic fluid (polyhydramnios), there is too much space. As a result, the baby’s position can often change within a short period of time (changing fetal positions). Thus, the risk of a breech presentation is also increased in this case.
Other causes of a breech presentation include:
- Fetal malformations
- a short umbilical cord or umbilical cord entanglement
- Placental abnormalities (e.g., placenta previa)
- Tumors in the mother’s pelvic region
- maternal pelvic deformities
- Benign tumors (fibroids) of the uterus
- Anatomical abnormalities of the uterus, such as a heart-shaped uterus or a septum within the uterus.
Signs of a breech presentation
Many women do not realize that their baby is in a breech presentation. They may notice the baby kicking more frequently in the lower abdomen.
The feet may cause a stronger urge to urinate when pressure is applied to the bladder. In some cases, the head may also press against the ribs from below. Pregnant women often find this very uncomfortable or painful.
Breech Presentation and Childbirth
Unlike a transverse presentation, a breech presentation does not necessarily require a cesarean section. There are hospitals that support the natural delivery of a baby in a breech position.
Since a breech presentation carries different complications during childbirth than a head-first presentation, experienced midwives and doctors are essential.
With their expertise, the conditions for a complication-free birth are met even in the case of a breech presentation. Nevertheless, a breech presentation is considered a sufficient factor to classify the birth as high-risk.
Impact of a breech presentation on the baby
A breech presentation generally does not affect the development of the unborn child. A breech presentation is only diagnosed if the baby has not turned by the end of the pregnancy.
Fetal abnormalities and malformations occur in the early stages of pregnancy and are not caused by a breech presentation. The supply of nutrients to the unborn child is also not normally compromised by a breech presentation.
Examination and Diagnosis
In most cases, a breech presentation can be diagnosed during routine prenatal care. The obstetrician can use ultrasound to determine exactly how the baby is positioned in the womb.
At each prenatal visit, the treating physician records the baby’s exact position in the prenatal record. The gynecologist diagnoses a breech presentation when the fetus has not yet turned by the 32nd week of pregnancy.
In general, however, the baby can still turn until around the 37th week of pregnancy.

© fotoduets | AdobeStock
Treatment of a breech presentation: wait-and-see approach, external version, or cesarean section
Experienced obstetricians can perform an external version in cases of breech presentation. During this procedure, doctors use careful and precise manual maneuvers from the outside, through the abdominal wall, to turn the baby into a cephalic position. The success rate for this procedure is approximately 50–70%.
Complications occur in less than 3% of all cases.
These include, for example:
- premature placental abruption and
- a drop in the baby’s heart rate
For this reason, a surgical team ready to perform a cesarean section (sectio) should be on standby during every external version.
Perinatal centers care for pregnant women who are giving birth in a breech presentation or who undergo an external version. Obstetricians specialize in the care of premature and newborn infants.
Course and Prognosis of Breech Presentation
An external version performed after the 37th week of pregnancy can reduce the number of cesarean sections. It also increases the likelihood of a vaginal birth.
However, if there are no specific risk factors, pregnant women can also deliver vaginally from a breech presentation.
The delivery can be more strenuous for both the baby and the mother than a delivery from a cephalic presentation.
If the baby’s head is too large for the mother’s pelvis, labor may be prolonged.
For this reason, an ultrasound or MRI is often performed before a breech birth to assess this fit. If abnormalities are detected, a cesarean section may be necessary.
Share this article

Sources
- https://flexikon.doccheck.com/de/Beckenendlage
- https://www.frauenaerzte-im-netz.de/schwangerschaft-geburt/schwangerschaft/schwangerschaftsdrittel/#c73
- https://www.familienplanung.de/schwangerschaft/geburt/komplikationen/beckenendlage/#c3094
- https://deximed.de/home/b/schwangerschaft-geburtshilfe/geburt-wochenbett/geburt/beckenend-und-querlage/
- https://www.cochrane.org/de/CD000084/PREG_aussere-wendung-bei-beckenendlage-vor-dem-geburtstermin



