
Typical symptoms, such as abnormal bleeding, often allow for an early diagnosis, which means that the overall prognosis for uterine cancer is favorable. Nevertheless, the disease requires a thorough gynecological evaluation and a personalized treatment plan.
What is uterine cancer?
The uterus is a hollow organ consisting of the body and the cervix. Uterine cancer develops in the upper part of the uterus, in the body.
At the lower end of the tubular body of the uterus is the cervical os—it forms the opening into the vagina. The endometrium, or uterine lining, completely lines the inside of the uterus and renews itself with each menstrual period.
Unlike many other types of cancer, uterine cancer does not develop from muscle tissue, but rather from the cells of the lining. Medical professionals therefore also refer to the disease as endometrial carcinoma. Other terms for uterine cancer include cancer of the uterine lining, endometrial carcinoma, or corpus carcinoma.
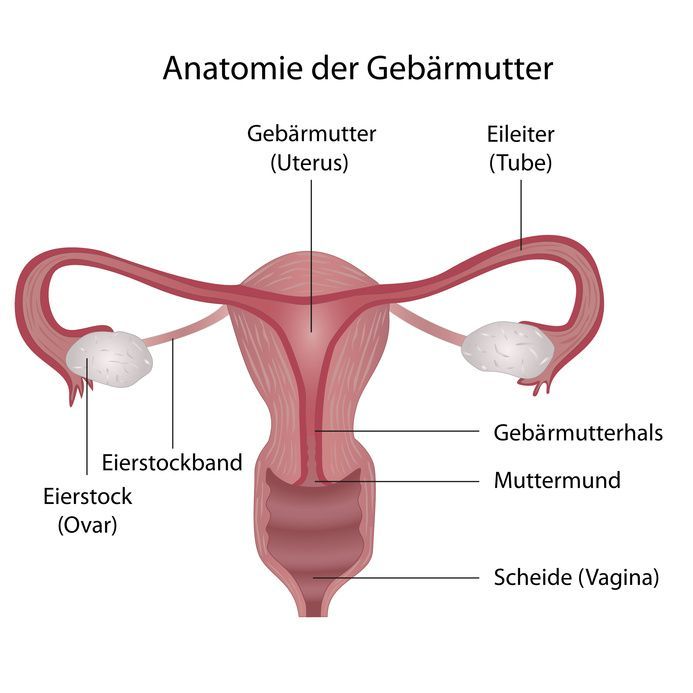
Anatomy of the uterus and surrounding structures © SHOTPRIME STUDIO | AdobeStock
Endometrial carcinoma is the fourth most common cancer in women, following breast, colorectal, and lung cancer. It is the most common malignant disease of the female reproductive tract. According to statistics, approximately 11,000 new cases are diagnosed each year.
This malignant tumor of the uterine body (uterus) occurs primarily in postmenopausal women. The peak incidence is between the ages of 75 and 79. Uterine cancer is extremely rare before the age of 40.
Uterine cancer should not be confused with cervical cancer. The two types of cancer differ significantly in terms of early detection and treatment.
Uterine Cancer: Symptoms, Diagnosis, and Chances of Recovery for Endometrial Cancer—Stages, Risk Factors, Prognosis, and Treatment of Uterine Cancer in Women
What causes uterine cancer?
Various factors interact in the development of the disease, and these are not yet fully understood. What is clear is that the disease is primarily linked to the female sex hormone estrogen and its effect on the uterine lining. The hormone is produced in the ovaries, but also in adipose tissue.
In the female menstrual cycle, both estrogen and the luteal hormone progesterone—which belongs to the progestins—play a crucial role. Both hormones interact with each other:
-
Progesterone is responsible for causing the upper layers of the endometrium to shed during menstruation.
-
Estrogen, on the other hand, ensures that the endometrium rebuilds itself after menstruation.

Uterine cancer usually develops after the hormonal changes of menopause © SHOTPRIME STUDIO | AdobeStock
With the onset of menopause, fundamental hormonal changes occur in a woman’s body. The ovaries cease hormone production—menstrual bleeding stops, and the endometrium no longer renews itself. As a result, the endometrium can thicken excessively, and under certain circumstances, an estrogen-dependent carcinoma (Type I) may develop.
There are also estrogen-independent tumors (Type II). The causes of this type of endometrial carcinoma are largely unknown.
What risk factors contribute to uterine cancer?
Since adipose tissue also produces estrogen, overweight women after menopause are considered to be at particularly high risk. The continued presence of estrogen exerts an additional growth stimulus on the endometrium.
Due to the familial clustering of the disease, scientists and physicians assume that genetic predisposition also plays a role—that is, there is a genetic component.
This is significant, for example, in the case of a genetically determined condition known as Lynch syndrome. With this genetic mutation, patients have an increased risk of developing endometrial and/or colorectal cancer.
Women whose bodies have produced estrogen over a very long period of time are also at risk. This includes women who began menstruating very early and those who entered menopause late.
In contrast, women who have taken the birth control pill for an extended period or who have been pregnant multiple times are at lower risk.
Long-term use of the birth control pill reduces the risk of developing the disease © rosifan19 | AdobeStock
Summary: According to current research, several factors contribute to the development of the tumor—particularly estrogen-dependent carcinoma. These include:
- long-term estrogen therapy during menopause without concurrent progestin therapy
- Being overweight, as fat cells produce estrogen
- PCOS (polycystic ovaries cause hormonal imbalances)
- early onset and late cessation of menstruation
- diabetes mellitus
- High blood pressure
- Inability to conceive
- Breast cancer
- Tamoxifen therapy (post-treatment medication for breast cancer)
- Increased familial risk of colorectal cancer (Lynch syndrome)
- Radiation therapy to the pelvic and/or abdominal area due to another cancer
- Changes in the endometrium (atypical hyperplasia)
Factors that reduce the likelihood of developing uterine cancer include:
- Multiple pregnancies (multiparity)
- Physical activity
- Use of contraceptives (“the pill”)
- A lifelong diet rich in soy (possibly)
What are the symptoms of uterine cancer?
There are no noticeable symptoms in the early stages. For this reason, uterine cancer often goes undetected in its early stages. It is only as the disease progresses that the first signs appear that may indicate cancer.
The main symptom is, above all, unusual bleeding. This can include bleeding outside of the menstrual cycle or after menopause. However, you should also be vigilant if you experience unusually long or heavy bleeding, spotting, or a purulent discharge.
Although these symptoms do not always indicate cancer, it is advisable to have them evaluated by a gynecologist.

If unusual bleeding occurs, it may be a sign of a uterine tumor © Мария Кокулина | AdobeStock
Less commonly, pain in the lower abdomen, back, or pelvic area may also occur. In advanced stages, the vagina, rectum, or bladder are often affected as well. This can lead to symptoms such as bleeding from the bowel or bladder and an increased incidence of urinary tract infections.
Diagnosis and Early Detection of Uterine Cancer
Women at increased risk for uterine cancer should undergo a transvaginal ultrasound once a year. During this procedure, the thickness of the endometrium is measured. If, after menopause, the endometrial thickness is less than 4 mm—even when doubled—endometrial cancer can be virtually ruled out—provided there is no bleeding or any of the listed symptoms.
However, if cancer is suspected, a more detailed examination of the uterine lining must be performed. The most reliable method for this is a hysteroscopy, during which tissue samples are specifically taken from suspicious areas. The doctor then scrapes out the entire endometrium (curettage or abrasion). By combining these two methods, malignant tumors can be diagnosed or ruled out with a high degree of certainty.
If the suspicion of uterine cancer is confirmed, further tests are required. These are used to assess the extent of the tumor’s spread within the uterine wall and any potential involvement of lymph nodes and adjacent organs. These include:
- Laboratory test results
- Ultrasound of all abdominal and pelvic organs
- X-ray examination of the kidneys and urinary tract with contrast dye
- possibly cystoscopy and colonoscopy
Computed tomography (CT) and magnetic resonance imaging (MRI) may also be used to better assess the situation.
Treatment of malignant uterine cancer: A common disease involving tumor formation; curable with early treatment
What treatment options are available?
Modern cancer medicine (oncology), particularly gynecologic oncology, offers various treatment approaches for uterine cancer. Their use depends on the stage of the disease.
Surgery for uterine cancer
Currently, surgery performed as part of oncological surgery is the treatment of choice, as it offers the best chance of a cure.
If the tumor is detected at a very early stage, surgery is usually sufficient as a treatment. The pathologist then assesses the extent to which the uterine wall is affected by the tumor (depth of invasion) and whether lymph nodes are involved. This assessment and the findings determine whether radiation therapy or chemotherapy (which is rather rare) will be required afterward.
In a procedure known as a radical hysterectomy, the surgeon removes the uterus, ovaries, and fallopian tubes.
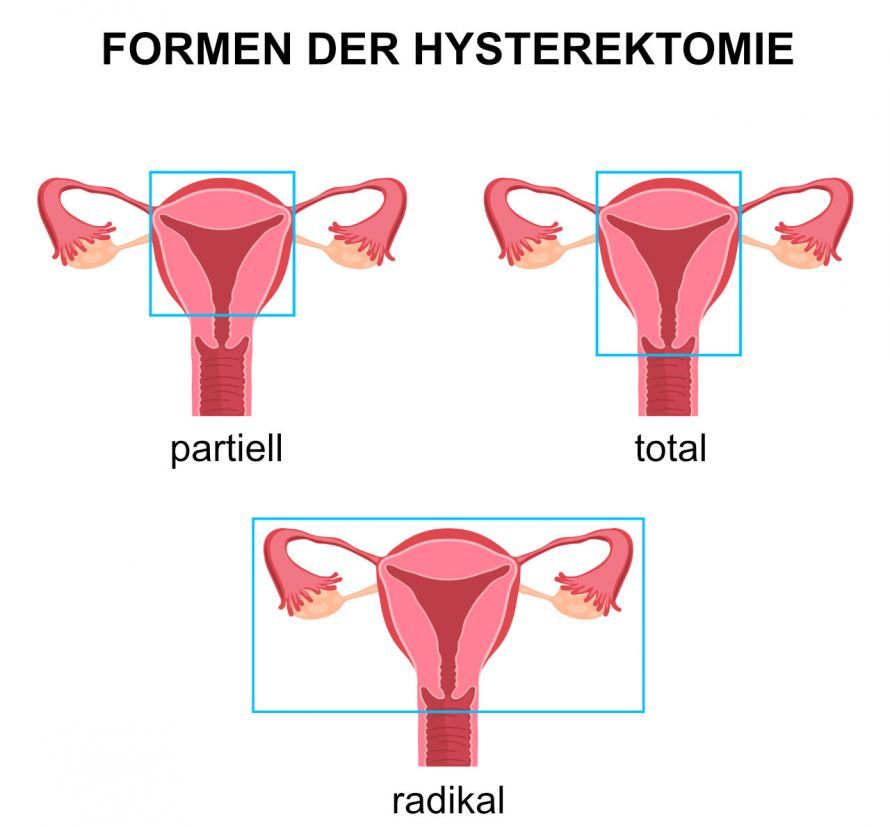
Different types of hysterectomy (removal of the uterus) © fancytapis | AdobeStock
If there is an increased risk of the cancer spreading, or if it turns out that the tumor has grown beyond the boundaries of the uterine body, lymph nodes from the area surrounding the organ (the pelvis) and, in some cases, from behind the abdominal cavity are also removed.
If neighboring organs such as the bladder and rectum are affected, it may be necessary to remove these organs partially or completely as well.
One side effect of the surgery that affects younger patients is the sudden onset of menopause following removal of the ovaries. If the tumor was detected at an early stage, combined estrogen-progestin hormone therapy may be used to alleviate the typical symptoms.

By Ed Uthman from Houston, TX, USA - Endometrial Carcinoma, CC BY 2.0, Link
Radiation Therapy for Uterine Cancer
Radiation therapy is primarily a postoperative measure, meaning it is administered after surgery has been completed. Although radiation therapy can be effective in the early stages, surgery offers a better prognosis. Therefore, radiation therapy is generally most effective when combined with surgery—unless surgical treatment is not possible.
Radiation therapy is primarily aimed at preventing the regrowth of a tumor. However, it is also used when the tumor could not be completely removed or when the vaginal vault has already been affected. In such cases, targeted, locally limited radiation therapy improves the chances of recovery. For uterine cancer, two radiation techniques are commonly used, often in combination.
In what is known as short-distance radiation therapy (brachytherapy), a radiation source is inserted into the vaginal vault several times for short periods. There, it emits high-energy radiation “in situ.” The goal is to prevent a recurrence in the vaginal area.
In contrast, external radiation therapy (also known as external or percutaneous radiation therapy) involves irradiating the entire pelvic cavity. This is intended to prevent a recurrence in this region.
Radiation therapy may be considered as the sole treatment option when surgery is not possible. Reasons for this include, for example, comorbidities or the patient’s poor overall health.
Side effects of radiation therapy may include inflammation of the bladder and bowel, which usually subside after a few weeks. However, they can sometimes lead to chronic symptoms. The vaginal tissue is also more sensitive and susceptible to infections after radiation therapy. These side effects can, however, be alleviated with medication.
Chemotherapy for Uterine Cancer
Treatment approaches using cell-growth-inhibiting drugs (chemotherapy) and inhibitors of the female hormone estrogen (anti-hormone therapy) are primarily used in advanced stages and in cases of recurrence that cannot be treated by other means.
Tumors that are classified as well-differentiated (mature) on histological examination respond better to hormone therapy. Poorly differentiated tumors are better treated with chemotherapy.
In advanced stages, chemotherapy can also be useful for combating secondary tumors (metastases).

Chemotherapy is primarily used in advanced stages © Monkey Business | AdobeStock
Possible side effects of chemotherapy include
- nausea,
- vomiting,
- diarrhea,
- hair loss
as well as an increased susceptibility to infections, some of which—such as vomiting—can be effectively alleviated with medication.
Hormone Therapy for Uterine Cancer
While administering the female sex hormone progestin can slow tumor growth somewhat, hormone therapy does not promise a cure. It can therefore only be considered a complementary measure to other forms of treatment.
In individual cases, hormone therapy is an option for younger women in the early stages of the disease who wish to have children. In most cases, the uterus is then removed after childbirth.
Follow-up Care After Endometrial Cancer Treatment
Regular gynecological examinations are important after uterine cancer treatment to detect possible local recurrences of the disease. Depending on the risk of recurrence, these examinations should be performed every three to six months during the first three years after surgery. Most recurrences and treatment-related complications occur during this period.
About 11 percent of women with early-stage uterine cancer develop local recurrences. With early diagnosis, surgery—and thus a cure—may be possible. Therefore, all affected women should keep in mind: Any unusual changes are a reason to see your doctor immediately, rather than waiting until your next follow-up appointment.
Is it possible to have children despite uterine cancer?
Under certain circumstances, women with uterine cancer can fulfill their desire to have children. This is possible only if the uterine tumor is less aggressive and at a very early stage.
In such cases, doctors temporarily administer hormone therapy with synthetic progestins. While these usually do not permanently inhibit tumor growth, Nevertheless, it is often possible to fulfill the desire to have children during this time. This requires a repeat examination of the uterine cavity (hysteroscopy) and a dilation and curettage (D&C) as a follow-up after progestin therapy (i.e., hormone therapy). The tumor should no longer be detectable to a large extent.

Under certain circumstances, affected women may still be able to fulfill their desire to have children © Dimid | AdobeStock
Following such fertility-preserving therapy, surgical treatment appropriate to the stage of the disease is required.
Is there a way to prevent it?
Unfortunately, there is no preventive treatment that protects against uterine cancer. A preventive vaccine against human papillomavirus, which offers protection against cervical cancer, is ineffective against uterine cancer.
The most important measure against uterine cancer is early detection. That is why specialists recommend regular screening exams with a gynecologist.
What are the chances of recovery from uterine cancer?
If the disease is detected and treated early, the chances of recovery are very good. Statistics cover a five-year period and determine the so-called “five-year survival rate.” The prognosis for uterine cancer is extremely positive. About 80 percent of affected women have overcome the cancer after five years.
The prognosis worsens significantly if secondary tumors (metastases) have already formed. Metastases often settle in the lungs or liver—rarely in the bones—and can only be treated with medication.
FAQ
What is uterine cancer?
Uterine cancer is a malignant cancer of the uterus that usually originates as endometrial carcinoma from the uterine lining. It is one of the most common types of cancer in women.
What are the typical symptoms of uterine cancer?
A common symptom is abnormal bleeding, especially after menopause. Bleeding outside of the menstrual cycle or pain may also occur.
How is uterine cancer diagnosed?
The diagnosis is made through a gynecological examination, ultrasound, hysteroscopy, and a tissue biopsy. Imaging tests help assess the stage of the cancer and determine whether it has spread.
What treatment options are available for uterine cancer?
Uterine cancer is usually treated surgically by removing the uterus, often supplemented by radiation therapy, chemotherapy, or hormone therapy. Treatment depends on the stage of the disease.
What are the chances of recovery from uterine cancer?
If uterine cancer is detected at an early stage, the chances of recovery are very good. The prognosis depends on the tumor stage, the extent of spread, and individual risk factors.
Share this article
Sources
- Krebsinformationsdienst des Deutschen Krebsforschungszentrums (www.krebsinformationsdienst.de/gebaermutterkoerperkrebs)
- Frauenärzte im Netz (https://www.frauenaerzte-im-netz.de/erkrankungen/gebaermutterkoerperkrebs/)

















