
The extent of surgery for pancreatic cancer depends on the location of the tumor. In cases of pancreatic head cancer, doctors remove the head of the pancreas along with the gallbladder, the common bile duct, the duodenum, and the surrounding lymph nodes.
A cure through pancreatic cancer surgery is only possible if doctors are able to remove all of the tumor tissue.
The Pancreas—Anatomy and Function
The pancreas is located in the upper abdomen behind the stomach and is anatomically divided from right to left into the following structures:
- Head
- Body, and
- Tail
The head of the pancreas is situated in the curve of the duodenum, into which the bile duct and the pancreatic duct drain. Both ducts pass through the head of the gland, where they join and empty into the duodenum via the papilla.
The body of the gland lies in front of the aorta, near the blood vessels supplying the upper abdominal organs and the intestine.
The tail of the gland extends toward the spleen and shares blood vessels with it.
A dense network of lymphatic vessels runs through the posterior abdominal cavity, where tumor cells can spread widely. The gland is very well supplied with blood from multiple directions. The insulin-producing cells are particularly concentrated in the tail.
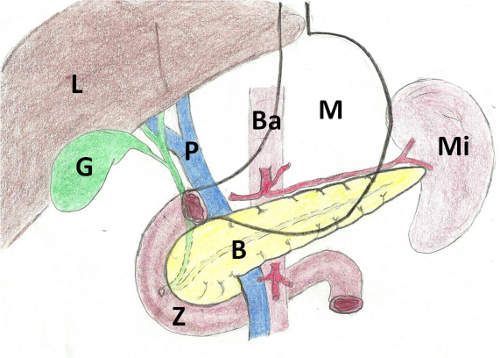
Fig. 1: Schematic anatomy of the pancreas. The stomach, located in front of the pancreas, is shown as a silhouette. L=Liver, G=Gallbladder and bile ducts, M=Stomach, B=Pancreas, Mi=Spleen, Z=Duodenum, Ba=Abdominal aorta, P=Portal vein.
Since nature designs organs with generous margins and builds in reserves, a 50% loss of the gland may have no negative effects.
This does not apply to people with diabetes, whose insulin production was already insufficient beforehand. Digestive enzymes and insulin administration can compensate for the pancreas’s deficiency.
The pancreas has a dual function:
It is the primary producer of digestive enzymes and facilitates the absorption of fats from food. A deficiency of these enzymes causes greasy, foul-smelling stools and gradual weight loss.
It produces insulin and is therefore a key organ in regulating blood sugar. A lack of insulin leads to insulin-dependent diabetes mellitus.
Definition and Tumor Biology: Pancreatic Cancer
Pancreatic cancer is a malignant tumor that can originate from any cell population within the gland. However, the most common type arises from the ductal system (ductal carcinoma, accounting for 95% of cases).
Pancreatic cancer is aggressive and is characterized by uncontrolled growth and early metastasis (spread). Even when only a few centimeters in size, it reaches the organ capsule, which, being a thin membrane, does not constitute a true barrier. Behind it lie vital structures that become infiltrated once the tumor breaks through.
Early on, tumor cells enter the dense network of lymph nodes via the lymphatic system. This is not a multi-stage filtration system like the one we see in colorectal cancer. Therefore, lymph node involvement is usually an indicator of widespread cancer spread.
This metastasis occurs primarily via the dense bloodstream to distant organs. First and foremost to the liver, where liver metastases then develop.
Finally, the cancer can also enter the abdominal cavity directly through the shedding of superficial tumor cells. There, metastases can lead to intestinal obstruction.
Diagnosis of Pancreatic Cancer
With 15,000 new cases, pancreatic cancer is the eighth most common cancer in Germany.
Little is known about its causes. Nicotine, alcohol, and diabetes mellitus are minor risk factors. A familial cluster of cases is observed in a small number of patients. To date, there is no clearly definable risk group.
It is likely that some carcinomas develop from polyp-like precancerous lesions in the duct system. There is no endoscopic screening for the duct system.
Furthermore, early detection via ultrasound of this organ, which is located deep within the abdomen, is impossible. For this reason, doctors typically first detect most pancreatic tumors radiologically via computed tomography (CT) or magnetic resonance imaging (MRI). The new PET-CT scan does not yet play a role in routine clinical practice.
Consequently, doctors usually do not diagnose cancer until symptoms appear.
Symptoms of Pancreatic Cancer
The symptoms of the tumor are nonspecific and typically indicate advanced disease:
- Pressure in the upper abdomen
- Pain radiating to the back
- newly diagnosed diabetes mellitus
- Soft, greasy-smelling stools
It is not surprising that valuable months can pass between the onset of initial symptoms and diagnosis. When tumors encroach on the papilla (the opening of the bile and pancreatic ducts), they obstruct the flow of bile into the intestine. This causes jaundice. This painless jaundice is considered the key symptom of tumors of the pancreatic head.
The rule of thumb is: the closer the tumor is to the papilla, the earlier the typical jaundice and tumor diagnosis occur. The farther the cancer is from the papilla, the later the symptoms and diagnosis occur.
Procedure for Pancreatic Cancer Surgery
If tumors are confined to the pancreas, doctors can remove them through radical surgery. Preoperative oncological treatment with chemotherapy or radiation therapy is not standard practice for pancreatic cancer.
Radiological staging (particularly CT) determines whether the tumor is operable. This localizes the tumor and identifies whether adjacent structures, lymph nodes, and other organs—such as the liver—are involved.
Generally, only locally confined cancer is treated surgically. To date, there is no effective oncological therapy for advanced carcinoma; only symptom-management chemotherapy is available.
Pancreatic Cancer Surgery for Cancer of the Pancreatic Head
The extent of pancreatic cancer surgery depends on the tumor’s location.
Cancer of the pancreatic head requires the removal of:
- the head of the pancreas, along with the gallbladder and the common bile duct
- The duodenum and the surrounding lymph nodes
This pancreatic cancer surgery is called a pylorus-preserving duodenopancreatectomy according to Traverso-Longmire (Fig. 2).
Over the past twenty years, it has replaced the classic Kausch-Whipple resection with partial gastrectomy as the gold standard.
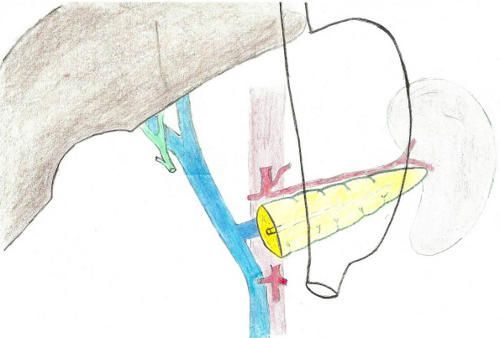
Fig. 2: Extent of resection in pancreatic head cancer
In the second part of this complex, multi-hour pancreatic cancer surgery, surgeons must reconstruct the continuity of the digestive tract. This means connecting the pancreas, bile duct, and stomach to the small intestine (Fig. 3).
Occasionally, they also divert the remaining portion of the pancreas into the stomach.
Only a few specialists are capable of performing this complex pancreatic cancer surgery. Worldwide, it is performed almost exclusively using the traditional open technique.
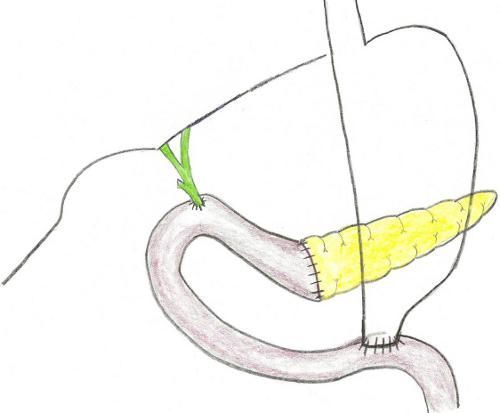
Fig. 3: Reconstruction with the small intestine elevated, to which the remnant of the pancreas, the bile ducts, and the stomach are connected.
Pancreatic Cancer Surgery for Tumors in the Pancreatic Body
Tumors in the body of the pancreas rarely require surgery. They invade neighboring vessels at an early stage and are no longer operable.
In rare cases of operable corpus carcinoma, surgeons remove the corpus along with the surrounding lymphatic vessels. They can suture the gland toward the head. However, they must connect the pancreatic tail to a bypassed loop of the intestine.
Pancreatic Cancer Surgery for Cancer in the Pancreatic Tail
Doctors rarely detect cancer in the pancreatic tail early enough. Therefore, it is rarely operable.
Yet radical tail resection is relatively simple (Fig. 4). Doctors separate the tail from the body of the pancreas and, due to their shared blood supply, remove it together with the spleen. Complex reconstruction is not necessary.
Pancreatic resections are often performed using minimally invasive techniques (keyhole surgery or laparoscopy).
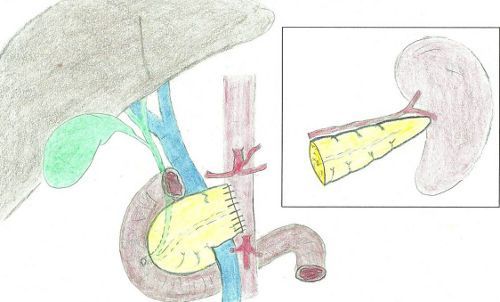
Fig. 4: Extent of pancreatic tail resection. The end of the remaining gland is closed off.
Other Pancreatic Cancer Surgeries
Surgeries for pancreatic cancer, such as the partial removal of affected neighboring organs like the colon, stomach, or liver, are performed only very rarely.
Total pancreatectomy is also not a standard oncological treatment, but rather part of managing complications in cases of severe inflammation.
The situation is different, however, when the portal vein is involved, as in cases where the cancer has infiltrated the head of this vessel, which is essential for blood flow to the liver. An experienced pancreatic surgeon can reconstruct the vessel in this particularly challenging situation.
Prognosis and Follow-Up Care After Pancreatic Cancer Surgery
A cure is only achieved if the pancreatic cancer surgery is able to remove all of the tumor tissue.
Once the body has recovered and adapted to the newly reconstructed upper abdominal anatomy, a normal life without restrictions is possible. This adaptation can take several months.
If the tumor has spread (metastases), a cure is not possible. However, this can often only be determined after pancreatic cancer surgery. During this process, the pathologist examines the lymph nodes under a microscope using a special stain.
If the pathologist finds microscopic clusters of tumor cells there, the prognosis is poor. This is because the cancer usually returns within two years—either as a local recurrence at the same site in the posterior abdomen or as distant metastases in the liver, lungs, or bones.
In this situation, there is no specific treatment. Instead, care is tailored to the patient’s individual symptoms, such as pain, ability to eat, and jaundice.
For this reason, there is also no meaningful standardized oncological follow-up care after pancreatic cancer surgery. Instead, medical and nursing care is primarily palliative in nature.
Outcomes of Pancreatic Cancer Surgery
Pancreatic cancer surgeries are complex, challenging specialized procedures. Surgical outcomes have steadily improved over the past few decades; nevertheless, pancreatic cancer surgeries remain a significant burden for patients.
After pancreatic resections, doctors should assess the function of the remaining pancreas. If necessary, the patient receives pancreatic enzymes as a dietary supplement and insulin.
Medications as an Alternative to Pancreatic Cancer Surgery
To date, there is no effective non-surgical treatment. Chemotherapy and radiation therapy cannot cure the disease, nor can they even significantly prolong life.
Tumor treatment therefore focuses on managing symptoms and supporting the patient during the few remaining months of life.
About the medical author
Herr Prof. Dr. Dr. h.c. Norbert Runkel
Medical writer



















