
Spondylolysis refers to a gap between the upper and lower articular processes of the vertebral arch (processus articularis superior and inferior). This condition is usually congenital and most commonly occurs in the fifth lumbar vertebra. Approximately 6% of the population is affected by spondylolysis. The resulting instability of the vertebra usually leads to spondylolisthesis. The vertebral body then slips forward and can cause symptoms. However, spondylolisthesis is not always painful.
Here you will find all the information and a selection of specialists for the treatment of spondylolysis.
Causes of Spondylolysis and Spondylolisthesis
Spondylolysis (ICD code: M43.0) results from a small crack in the vertebral arch (usually in the area of the pars interarticularis) and is hereditary in most cases. This causes the vertebra to become unstable. In some cases, the vertebra slips forward—a condition known as spondylolisthesis or vertebral slippage. Spondylolysis usually develops during childhood and adolescence, affecting children between the ages of 12 and 17.
Main Causes | Types of Spondylolisthesis:
- Congenital: very rare, present even in newborns.
- Isthmic spondylolisthesis: typical in children and adolescents, often caused by overexertion during sports (e.g., artistic gymnastics, apparatus gymnastics, or weightlifting).
- Degenerative spondylolisthesis: usually occurs in older age, when intervertebral discs and facet joints wear down.
- Other causes: rarely due to bone fractures or spina bifida.
Patients who develop spondylolysis at a young age are at particularly high risk of later developing more severe spondylolisthesis in the lumbar spine.
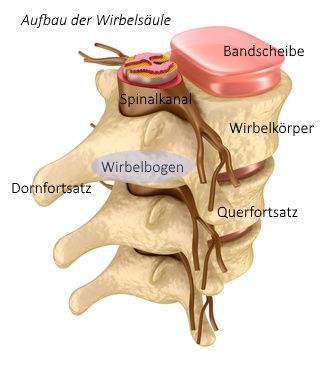
This leads to poor posture and uneven wear and tear on the vertebral joints, making spondylolisthesis more likely. Spondylolisthesis can also be caused by accidents or bone diseases such as osteoporosis or degenerative changes.
In extremely rare cases, tumors or inflammation may be the cause.
Symptoms of Spondylolysis
The condition primarily affects the lumbar spine (LS) and, rarely, the cervical spine (CS). Spondylolysis is classified into severity grades I through IV. Grade IV refers to the complete tilting (forward slippage) of a vertebral body, which is, however, very rare. A variant of this condition is the displacement of a vertebral body without the formation of a gap (pseudospondylolisthesis).
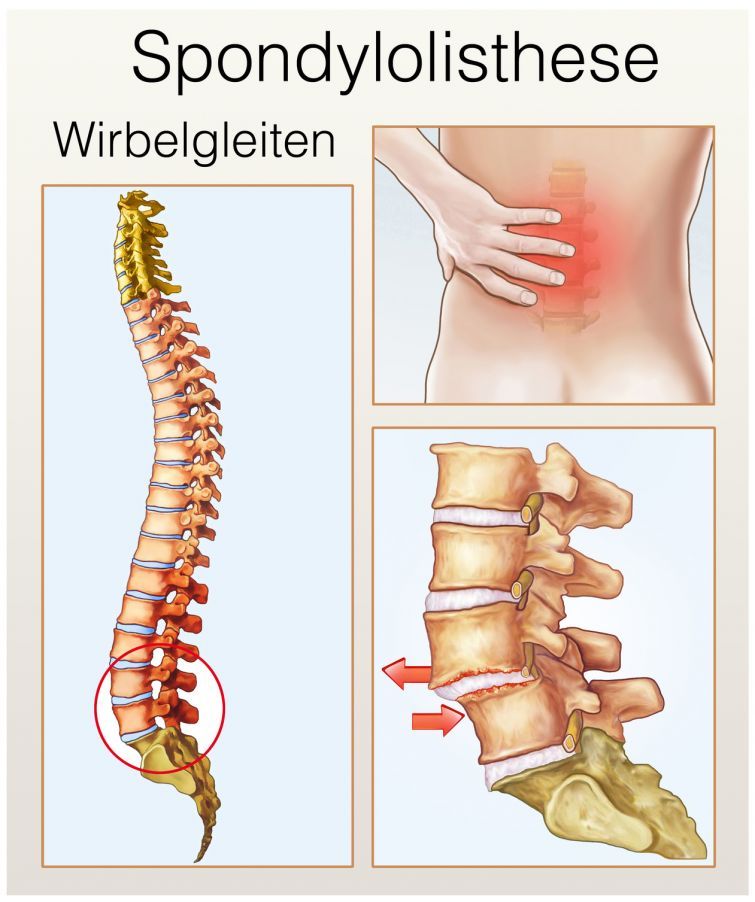
The following symptoms occur with spondylolisthesis:
- Back pain during physical activity that radiates into the buttocks and thighs.
- The pain increases when the patient extends (bends backward): This movement narrows the spinal canal, putting pressure on the surrounding tissue and causing the bony processes to come into contact with one another.
- When bending forward, the pain lessens: the flexion relieves pressure because it slightly widens the spinal canal, allowing the bony processes to move apart.
However, the condition can also be completely painless—a rare form of spondylolysis. The diagnosis of asymptomatic spondylolysis is usually an incidental finding. It is often discovered by chance during an X-ray examination. If the muscles and ligaments surrounding the spine provide compensatory stability, spondylolysis does not necessarily cause symptoms.
Spondylolysis should not be confused with a herniated disc, even though the symptoms may be similar in some cases. The diagnosis can be made with a lateral X-ray of the spine. An MRI also reveals possible damage to the spinal cord and nervous system—and thus a potential herniated disc—making this diagnostic method preferable to a simple X-ray.
Treatment of Spondylolysis
For Grade I and II cases, conservative treatment is sufficient. It should not be based solely on the X-ray image but primarily on the patient’s functional symptoms.
In most cases, physical therapy is prescribed, which is very effective. It aims to strengthen the abdominal and back muscles, as well as the core and lower back. Ideally, treatment takes a holistic approach. Massage, muscle-relaxing medications, and electrotherapy have also been shown to be effective.
However, if neurological deficits such as leg paralysis are already present, surgical treatment may be considered. In this procedure, the slipped vertebra that has slipped forward is repositioned and stabilized (spondylodesis with reduction). Following surgery, a stay of several weeks in a rehabilitation clinic is required.

Is it possible to prevent vertebral slippage conservatively and thereby alleviate symptoms?
Prevention is not possible in cases of genetically caused spondylolysis. However, something can be done in cases of wear-and-tear-related spondylolisthesis.
Since pseudospondylolisthesis can be halted or prevented through spinal exercises, targeted muscle strengthening is necessary. All muscles that support the skeleton should be strengthened.
The muscles located ventrally (toward the back) are also trained. Pilates and yoga, in combination with a targeted strengthening program using equipment such as the MedX, are also beneficial. This cannot restore the vertebrae to their original position. However, further deterioration is usually prevented or at least delayed.
Strong muscles stabilize the entire skeleton and generally help prevent back pain. Strong muscles can also help prevent age-related back problems.
Frequently Asked Questions from Patients
Is spondylolysis curable?
Spondylolysis cannot always be completely cured, as the gap in the vertebral arch (pars interarticularis) often remains. However, many patients with spondylolysis are asymptomatic and have no symptoms. In cases of symptomatic spondylolysis, conservative treatments such as physical therapy, muscle strengthening, and rest usually help to stabilize the spine. Surgical treatment is rarely necessary—for example, in cases of severe spondylolisthesis with pressure on the nerve roots.
What should you avoid doing if you have spondylolisthesis?
In cases of spondylolisthesis, strenuous activities should be avoided. These include sports that involve frequent hyperextension of the back, such as artistic gymnastics, weightlifting, or extreme back training. These movements can further narrow the spinal canal and worsen symptoms. Instead, functional exercises, physical therapy, or low-impact sports such as swimming, Pilates, or yoga—which help stabilize the lumbar spine—are recommended.
What is the difference between spondylolysis and spondylolisthesis?
Spondylolysis refers to a fracture in the pars interarticularis of the vertebral arch. If the affected vertebral body becomes unstable and slips forward, spondylolisthesis (also known as vertebral slippage) occurs. There are different forms, such as isthmic spondylolisthesis (most commonly in adolescents due to overuse) and degenerative spondylolisthesis (frequently in older adults due to wear and tear of the intervertebral discs and facet joints).
How dangerous is spondylolisthesis?
Spondylolisthesis (spinal slippage) is usually not life-threatening. Many people affected experience only mild back pain or even asymptomatic spondylolysis without any symptoms. It only becomes dangerous in cases of severe spondylolisthesis, when the vertebral body slips significantly forward and compresses the nerve roots. This can lead to numbness or paralysis—in such cases, surgical treatment is often necessary.
How is spondylolysis diagnosed?
Spondylolysis is diagnosed using X-rays, MRI, or CT scans. An X-ray usually reveals a gap in the pars interarticularis. An MRI also allows for the assessment of intervertebral discs, nerve roots, and the stability of the spine. Many asymptomatic patients first learn of their condition through these tests.
Share this article












