
Pulmonary fibrosis is not a disease in its own right, but rather a symptom of numerous conditions. These conditions are classified as interstitial lung diseases. In pulmonary fibrosis, the amount of connective tissue between the alveoli in the lungs increases.
Below you will find further information as well as a selection of pulmonary fibrosis specialists.
Idiopathic pulmonary fibrosis (with no known cause) is the most common form of the disease. Between 14 and 42 people per 100,000 residents are affected. Men are more likely than women to develop pulmonary fibrosis. Pulmonary fibrosis is rarely diagnosed in people under the age of 50.
The Symptoms of Pulmonary Fibrosis
The connective tissue changes in the lungs often go unnoticed for many years. The disease only becomes apparent once a large portion of the lung tissue has been affected by fibrosis.
Those affected notice that their physical performance is declining and that they are no longer as resilient as before. Even during simple everyday activities, they become short of breath and also suffer from a dry, irritating cough without phlegm. Inhaling is particularly difficult, so patients often experience a sudden pause in breathing while inhaling.
As the disease progresses, shortness of breath eventually occurs even when no physical exertion is involved.
To compensate for the decreasing oxygen levels in the blood, the body increases the respiratory rate. As a result, breathing generally becomes shallower and faster. This is also referred to as gasping for breath.
A prolonged lack of oxygen manifests itself through the following symptoms:
- Blue discoloration of the skin (cyanosis)
- Round and swollen fingertips (clubbing)
- Noticeably bulging fingernails (watchglass nails)
The Causes of Pulmonary Fibrosis
In fibrosis, connective tissue fibers proliferate within the lungs. This excess connective tissue eventually forms scar tissue and damages the surface of the delicate alveoli. As a result, the lungs’ elasticity decreases and gas exchange within the lungs is impaired.
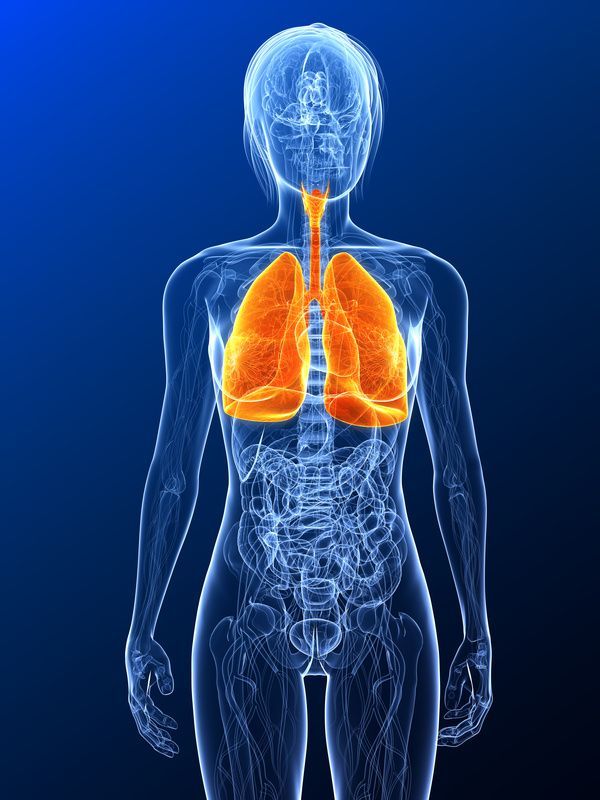
Generally, pulmonary fibrosis can be divided into two groups based on its cause:
- pulmonary fibrosis with a known cause and
- idiopathic fibrosis, in which no trigger can be identified.
Pulmonary fibrosis can be caused by viruses or parasites and by exposure to harmful substances.
Inhaling harmful substances can cause diseases or allergic reactions, as well as fibrosis later on, e.g.,
- asbestos or coal dust (which can lead to pneumoconiosis with fibrosis),
- cigarette smoke,
- various allergens such as bird droppings or fungal spores,
- gases such as sulfur dioxide or ammonia, as well as
- vapors and aerosols.
All of these can contribute to fibrotic changes in lung tissue.
In addition, there are medications that can lead to pulmonary fibrosis if taken regularly. For example,
- bleomycin,
- carbamazepine, and
- floxuridine
cause changes to the lung structure and significantly increase the risk of fibrosis.
Damage to lung tissue can also result from radiation therapy for cancer. In this case, the condition is referred to as radiation fibrosis.
Certain rheumatic diseases, such as
are also associated with connective tissue remodeling in the lungs.
Diagnosis of Pulmonary Fibrosis
First, the doctor discusses the symptoms with the patient and takes a medical history. If the doctor suspects pulmonary fibrosis, he or she performs various physical examinations.
First, they listen to the lungs with a stethoscope (auscultation). In pulmonary fibrosis, a so-called crackling sound can be heard at the end of the inhalation phase. This crackling sound is caused by fluid accumulation in the lung tissue. Occasionally, a squeaking sound can also be heard.
Due to fibrosis, the lungs can no longer expand properly. When the lungs are tapped (percussion), elevated diaphragmatic borders are therefore noticeable.
To better assess the properties of the lung tissue and gas exchange, the doctor performs pulmonary function tests. Using a device called a spirometer, the doctor measures how quickly exhaled air is expelled and how much air can be mobilized in the lungs.
Typically, spirometry and blood tests reveal the following findings:
- a decrease in lung tissue function
- reduced elasticity of the lung tissue
- impaired gas exchange between the blood and the lungs
- reduced oxygen saturation in the blood (hypoxemia)
An X-ray examination is necessary to definitively assess the extent of the disease. This typically reveals increased pulmonary vascular markings and a high-riding diaphragm.
The lung structure can also be assessed using high-resolution computed tomography.
Pulmonary Fibrosis – Treatment
Since pulmonary fibrosis is only a symptom, treatment depends on the underlying condition.
If the fibrosis is caused by exposure to harmful substances, these must be strictly avoided.
Inflammatory lung diseases, on the other hand, are treated with corticosteroids. These not only combat inflammation but also have anti-allergic effects. The patient receives them
- in the form of tablets,
- as an inhaled spray, or
- intravenously.
To widen the narrowed airways, patients are also given so-called bronchodilators. These medications relax the small muscles of the bronchi and make breathing easier.
If pulmonary fibrosis is caused by a bacterial infection, it is treated with antibiotics such as
- macrolides,
- quinolones, or
- cephalosporins
.
Active participation in a pulmonary rehabilitation program can improve the physical fitness of patients with pulmonary fibrosis. Under professional guidance, patients perform targeted muscle and endurance training.
Severe cases of the disease, in which the lungs can no longer adequately facilitate gas exchange, require a lung transplant. However, patients must be younger than 60 years old and consistently abstain from smoking.
Transplantation generally improves quality of life. However, it does not prolong life expectancy.
The Prognosis for Pulmonary Fibrosis
The prognosis depends on various factors. These include not only the timing of treatment initiation but also the success of treatment and the extent of lung damage.
Fundamentally, pulmonary fibrosis is a severe form of organ damage. It cannot be cured and leads to death in many patients. Idiopathic pulmonary fibrosis has an extremely poor prognosis: 70 percent of all patients die from this form of fibrosis.
The average survival time after diagnosis is three years. After five years, only 20 to 40 percent of those affected are still alive.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →


