
Sarcoidosis—also known as Boeck’s disease or granulomatosis—is a rare inflammatory disease. It can cause clusters of small granulomas to form in any organ of the body. The granulomas consist of a granular form of connective tissue known as granulation tissue. This tissue is normally formed as part of the wound-healing process.
Here you will find all the important information as well as highly qualified sarcoidosis specialists.
What is sarcoidosis?
Generally, a distinction is made between the acute and chronic forms of sarcoidosis. Most people affected—about 95% of cases—have the chronic form. The acute form, also known as Löfgren’s syndrome, primarily affects young women.
The disease is caused by a dysregulation of the immune system or an exaggerated immune response to inflammatory processes. This subsequently leads to the formation of granulomas. For this reason, sarcoidosis is classified as a granulomatous autoimmune disease.
The causes of the heightened immune response remain unclear. Based on observed familial clustering, a genetic predisposition is assumed. When certain environmental factors are present, the immune system is activated, triggering granuloma formation.
Risk factors under discussion include, among others, inhaled pollutants such as
- chemicals or fine particulate matter,
- pathogens, and
- allergenic substances.
Furthermore, for reasons that are still unclear, sarcoidosis occurs more frequently among nursing staff.
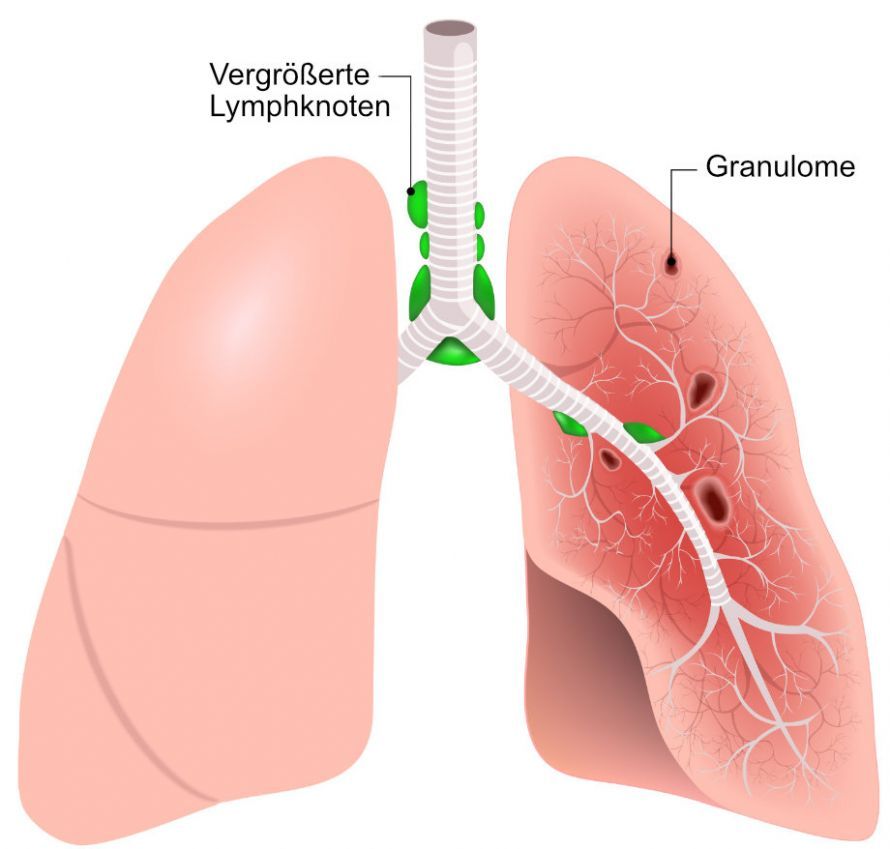
Sarcoidosis usually manifests between the ages of 20 and 40. In rare cases, children and infants may also develop the disease (early-onset sarcoidosis). Early-onset sarcoidosis (also known as Blau syndrome) appears before the age of 5. It is caused by a genetic defect.
Boeck’s disease can, in principle, affect any organ, as it is a systemic disease. However, in 95% of cases, nodular growths manifest in the lungs (pulmonary manifestation).
In addition, sarcoidosis frequently affects the following organs outside the lungs (extrapulmonary manifestations):
- the skin (15.9 percent),
- the eyes (11.8 percent),
- the liver (11.5 percent),
- the spleen (6.7 percent),
- the nervous system (4.9 percent),
- (parotid) salivary glands (3.9 percent),
- Bone marrow (3.9 percent),
- Throat, nose, ears (3.0 percent),
- heart (2.3 percent),
- Kidneys, bones, muscles (0.4 to 0.7 percent).
What are the symptoms of sarcoidosis?
In general, the typical general symptoms associated with inflammatory diseases, such as
- a general feeling of illness,
- fatigue,
- fever,
- limb pain, and
- joint inflammation
. In addition, the symptoms associated with the disease vary widely. They depend on the specific patterns of involvement and types of the disease.
Acute sarcoidosis
Acute sarcoidosis is characterized by the typical triad of symptoms consisting of
- arthritis,
- erythema nodosum, and
- bilateral lymphadenopathy
.
Erythema nodosum is characterized by painful, inflammatory changes in the subcutaneous fatty tissue. It presents as reddish-bluish papules. The affected skin areas are very tender. Typically, erythema nodosum manifests on the extensor surfaces of the lower legs.
Arthritis is the inflammation of one or more joints (polyarthritis). In many cases of acute sarcoidosis, the ankle joint is affected. Ankle arthritis, in turn, causes pain when walking.
Bihilar lymphadenopathy is characterized by swelling of the lymph nodes on both sides of the pulmonary hilum. The pulmonary hilum refers to the area of the large pulmonary vessels and main bronchi (where the trachea branches). Other symptoms of acute sarcoidosis include fever and cough.
Chronic sarcoidosis
At the onset of the disease, chronic sarcoidosis is asymptomatic in 50 percent of cases. The diagnosis is therefore often made incidentally during a chest X-ray examination.
A characteristic feature is the discrepancy between the patient’s relatively good subjective well-being and the pronounced objective findings, such as those seen on a chest X-ray.
In 95 percent of cases, chronic sarcoidosis manifests in the lungs and the lymph nodes in the chest area. In cases of pulmonary involvement, a dry cough and exertional dyspnea (shortness of breath upon exertion) may develop later in the course of the disease.
General signs of the disease, such as
- mild fever,
- weight loss,
- fatigue, and
- arthritis
are additional signs of chronic sarcoidosis.
The chronic form is classified into stages (Type 0 to IV) based on chest X-ray findings, which provide information about the pattern of involvement:
- Type 0: There are signs of the disease outside the chest, with no visible lung involvement
- Type I: bilateral hilar lymphadenopathy (= enlarged lymph nodes on both sides of the pulmonary hilum) without visible lung involvement
- Type II: Bihilar lymphadenopathy with lung involvement
- Type III: Lung involvement without bilateral hilar lymphadenopathy
- Type IV: Pulmonary fibrosis (= conversion of lung tissue into connective tissue) with irreversible impairment of lung function
Early-Onset Sarcoidosis (EOS)
EOS typically manifests before the age of 5, usually presenting as involvement of
- joints (arthritis),
- the middle layer of the eye (uveitis), and
- the skin (rash).
Other symptoms include
- fatigue,
- anorexia (loss of appetite),
- fever, and
- enlargement of the liver and spleen.
Extrapulmonary manifestations of Boeck’s disease
If sarcoidosis does not occur in the lungs, it is referred to as an extrapulmonary manifestation. These include, among others,
1. The skin:
- characterized by reddish-brown papules of varying sizes,
- extensive livid discoloration of the skin on the cheeks and nose (lupus pernio),
- yellowish-brown plaques in the area of existing scars (scar sarcoidosis),
- subcutaneous blue-reddish nodules on the extensor surfaces of the lower legs that are tender to pressure (erythema nodosum).
2. The eyes:
- inflammation of the iris and the ciliary body attached to the lens (iridocyclitis),
- inflammation of the middle layer of the eye’s vascular membrane, known as the uvea (uveitis),
- calcium deposits in the sclera and cornea,
- due to involvement of the lacrimal glands.
3. The parotid gland:
- Inflammation of the parotid gland (parotitis) in combination with uveitis and facial nerve palsy in Heerfordt syndrome.
4. The bones:
- due to cystic changes in the phalanges of the fingers (ostitis multiplex cystoides or Jüngling syndrome).
5. The nervous system (neurosarcoidosis):
- caused by facial nerve palsy,
- diabetes insipidus (associated with greatly increased urine output and a sensation of thirst),
- anterior pituitary insufficiency (loss of endocrine function in part of the pituitary gland),
- granulomatous meningitis (inflammation of the meninges).
6. The heart (cardiac sarcoidosis):
- asymptomatic in mild cases,
- by arrhythmias, left heart failure, and pericardial effusion (fluid accumulation in the pericardium) in cases of severe involvement.

By NHLBI authors. - National Heart, Lung, and Blood Institute: DCI Home: Lung Diseases: Sarcoidosis: Signs & Symptoms Retrieved on May 9, 2009., Public Domain, https://commons.wikimedia.org/w/index.php?curid=6737947
How is sarcoidosis treated?
Treatment depends on the specific type of the disease and the pattern of involvement.
Sarcoidosis is typically treated with corticosteroids (cortisone). These are associated with quite significant side effects. Therefore, such treatment is avoided for types of sarcoidosis that have a high rate of spontaneous remission. These include, for example, acute sarcoidosis and chronic sarcoidosis types 0 and I.
Treatment with corticosteroids is recommended for Type II and higher when lung function is impaired. Elevated calcium levels increase the risk of developing kidney stones. Therefore, this treatment is also used in cases of hypercalcemia. Kidney stones can cause kidney damage.
In addition, corticosteroids are indicated for use when the
- the eyes,
- liver,
- the nervous system,
- the myocardium (heart muscle), and
- skin, as well as
- in cases of severe systemic symptoms associated with acute sarcoidosis.
If corticosteroids are not sufficiently effective, a combination of prednisolone and immunosuppressants is indicated. In addition to systemic corticosteroids, local steroid therapy is recommended for uveitis and skin lesions.
Arthritic pain in acute sarcoidosis can be treated with NSAIDs (nonsteroidal anti-inflammatory drugs) such as ibuprofen.
Depending on possible further organ involvement, additional therapeutic measures may be indicated. For example, in cases of cardiac sarcoidosis, a pacemaker or defibrillator may be required as needed.
In cases of advanced organ involvement, transplantation of the affected organ is indicated as a last resort in the end stage.
What are the chances of recovery from sarcoidosis?
In 95 percent of cases, acute sarcoidosis resolves spontaneously within 2 years. It therefore has a very good prognosis.
In chronic sarcoidosis, the chances of recovery and the prognosis depend on the current stage of the disease. Type I sarcoidosis still has a spontaneous remission rate of 70 percent within 1 to 3 years. For Type II, this rate is about 50 percent, and for Type III, about 20 percent.
About one-fifth of patients experience permanent impairment of lung function. The mortality rate is 5 percent.
Sarcoidosis Specialists – Education and Continuing Medical Education
If you have lung problems, a pulmonologist is the right specialist for you.
After completing medical school, this specialist has undergone training to become a board-certified physician in internal medicine and pulmonology. This training lasts a total of 72 months and covers all relevant diagnostic and therapeutic procedures for the treatment of lung diseases.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →



