
Carotid surgery encompasses all surgical procedures on the carotid artery intended to treat pathological changes or narrowing (stenosis) caused by atherosclerosis. A narrowed or calcified carotid artery can significantly impair blood flow to the brain, thereby substantially increasing the risk of stroke. If plaques, blood clots, or narrowings are not removed in a timely manner, they can become dislodged and trigger a transient or permanent cerebral infarction. Diagnosis and treatment are now typically performed using ultrasound, supplemented by additional examination methods to assess the vessel diameter and the degree of narrowing according to NASCET or ECST. Modern carotid surgeries—including carotid endarterectomy, eversion endarterectomy, or stenting—are performed by experienced vascular surgeons, angiologists, and neurologists and aim to achieve a significant reduction in the risk of stroke. Depending on the patient’s anatomy, symptoms, and risk profile, the procedure is performed under general anesthesia or under local anesthesia with the patient awake.
What is carotid surgery?
Carotid surgery is a procedure performed on the carotid artery (medical term: arteria carotis) to correct a narrowing of the vessel. The goal is to prevent strokes caused by accelerated and turbulent blood flow through the narrowed section.
The carotid artery carries oxygen-rich blood from the heart to the brain. If fat, calcium, or blood clots build up on the vessel wall over the years—known as plaques—this can lead to a narrowing (stenosis). In severe cases, there is a risk of stroke if parts of these deposits break off and travel to the brain.
Carotid surgery is a subspecialty of vascular surgery, which is the specialized surgery of blood vessels.
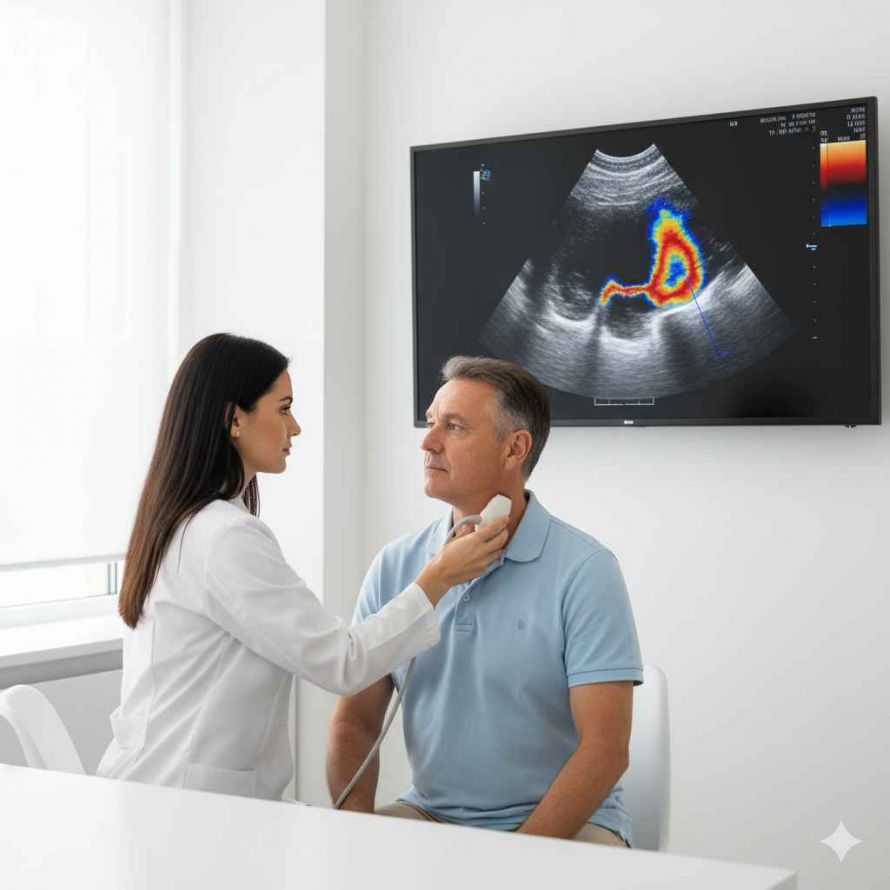
Early detection via ultrasound: Duplex ultrasound of the carotid artery is the most important non-invasive method for detecting narrowings (carotid stenoses) in a timely manner and thus minimizing the risk of stroke.
Why is carotid surgery necessary?
Carotid stenosis—the narrowing of the carotid artery—often goes unnoticed for a long time. Many people affected have no symptoms—yet their risk of stroke is significantly increased. Treatment is recommended above all:
- if a stroke has already occurred
- If warning signs of a stroke, known as a TIA (transient ischemic attack), occur
- if the carotid artery is narrowed by more than 70%, even if no symptoms are present yet
- if the patient has other risk factors such as high blood pressure, diabetes, or smoking
The goal of carotid surgery is to significantly reduce the risk of a recurrent or first stroke and to permanently ensure blood flow to the brain.
What surgical procedures are available?
Carotid surgery can be performed in two ways:
1. Open surgery (thrombendarterectomy)
In this procedure, the carotid artery is surgically opened. The surgeon removes the deposits (plaques) from the vessel wall. The vessel is then closed using a fine suture or a patch (a vascular prosthesis made of plastic or the patient’s own tissue).
Alternatively, the plaques are removed by separating the internal carotid artery from the common carotid artery, scraping out the plaque with a special instrument, and then reattaching the internal carotid artery to the common carotid artery with a suture.
2. Endovascular Treatment—Stent Implantation (Carotid Stenting)
In this method, a metal mesh (stent) is inserted into the narrowed vessel. It keeps the artery open from the inside. The procedure is minimally invasive, usually performed through an incision in the groin.
Important to know:
- Surgical treatment is still considered the gold standard for treating patients with carotid stenosis.
- Stenting is primarily an option for patients for whom surgery would be too risky—due to previous surgeries or radiation therapy in the neck area.
Open surgical treatment is usually performed under general anesthesia, but can also be performed under local anesthesia at the patient’s request. Carotid stenting is performed via the femoral artery under local anesthesia. Both procedures take about one to two hours.
What happens after the procedure?
After surgical or endovascular carotid treatment, the patient usually stays in a monitoring unit for 1 day. Full discharge typically occurs after 2 to 5 days.
Important for follow-up care:
- Regular ultrasound checkups of the carotid artery
- blood-thinning medications (e.g., acetylsalicylic acid) to prevent new blockages
- a healthy lifestyle, such as not smoking, exercising, and eating a healthy diet
- Maintaining proper blood pressure and cholesterol levels
The success of the treatment depends largely on how consistently these recommendations are followed.
What are the risks and complications?
As with any surgical procedure, there are potential risks associated with the treatment of carotid stenosis. The most common are:
- Postoperative bleeding (within the first few hours after the procedure)
- Nerve irritation (e.g., temporary numbness in the face or neck)
- Stroke during or after surgery—the risk is approximately 1–3% (according to the literature, slightly higher for carotid stenting, especially in cases of soft plaque and when the patient is already experiencing symptoms)
Given these risks—which, although rare, are not impossible—the decision to perform surgery or stenting (determination of indications) is clearly guided by the recommendations of European and German professional societies. In any case, the risk of stroke from the treatment should be lower than the risk of stroke with medication alone. Especially in patients who have already had a stroke, surgery significantly reduces the risk of another stroke.
What are the chances of success for carotid surgery?
The long-term prognosis after carotid surgery is very good for most patients. Studies show that the procedure can reduce the risk of stroke by up to 60%. The best results are achieved by patients who consistently manage their risk factors and follow their doctor’s recommendations for follow-up care.
Conclusion: Carotid surgery can save lives
If a narrowing of the carotid artery is detected, carotid surgery can be an important measure to prevent a stroke. The procedure is now safe and effective, especially when diagnosed early. It is important to consult an experienced vascular surgeon and take the recommended follow-up care seriously. This can significantly reduce the risk of serious complications.
Stent: A small metal mesh that keeps a blood vessel open
A stent is a fine metal mesh that is inserted into a narrowed blood vessel to keep it permanently open and ensure blood flow. In carotid surgery, this procedure is primarily used when open surgery is not possible or carries an increased risk. The stent is advanced into the narrowed carotid artery via a catheter using an endovascular procedure and then deployed there. It presses the plaques against the vessel wall, stabilizes the narrowing, and immediately restores blood flow to the brain. A stent can be a valuable alternative, particularly for soft or poorly located stenoses; however, it requires careful follow-up care, as clots or new narrowings may form.
FAQs on Carotid Surgery
Why does a narrowing of the carotid artery occur in the first place?
A narrowing of the carotid artery (carotid stenosis) is usually caused by atherosclerosis—that is, calcification and the buildup of plaque on the vessel wall. This pathological narrowing can promote the formation of thrombi and clots, which can disrupt blood flow to the brain or become dislodged. In rare cases, anatomical abnormalities, inflammatory processes, or changes in the external carotid artery may also play a role.
When is carotid surgery medically necessary?
Surgery is recommended if the degree of narrowing exceeds 70 percent or if neurological symptoms such as visual disturbances, paralysis, or transient ischemic attacks occur. If such symptoms are present, the risk of stroke increases significantly, as clots can enter the bloodstream and cause a temporary or permanent cerebral infarction. The decision is based on guidelines, ultrasound findings, the NASCET or ECST score, and individual risk factors.
What surgical procedures are available in carotid surgery?
The most important treatment methods include classic thrombendarterectomy, eversion endarterectomy—in which the vessel is peeled back and then repositioned—and endovascular stenting. All procedures aim to reliably remove narrowings, restore blood flow, and keep the carotid arteries permanently open. Depending on the situation, the surgery is performed under general or local anesthesia.
What does the diagnostic process involve before carotid surgery?
The first diagnostic method is almost always a carotid ultrasound, which can be used to assess the vessel diameter, the presence of plaques, and the degree of stenosis. In addition, neurological tests, imaging, or measurement methods may be used to determine whether brain damage has already occurred or whether clots are present in the bloodstream. Diagnosis and treatment are conducted on an interdisciplinary basis, often with the involvement of a neurologist.
How high is the risk of complications from carotid surgery?
The overall complication rate for carotid surgery is low, particularly in specialized centers. Nevertheless, complications such as postoperative bleeding, temporary nerve irritation, or, rarely, a stroke may occur during the procedure. These may be caused by unstable plaques, blood clots, or anatomical abnormalities that alter blood flow. Postoperatively, short-term neurological symptoms may occasionally occur, but they usually resolve quickly.
What is particularly important after the procedure?
After surgery, close monitoring via ultrasound is performed to assess the outcome. Patients should consistently manage risk factors such as high blood pressure or atherosclerosis, take blood-thinning medications, and make lifestyle adjustments. The goal is to prevent the recurrence of stenoses and to maintain a stable blood flow over the long term. In anatomically complex cases, shunts, stents, or surgical revisions may be necessary.

About the medical author
assoc. Prof. PD Dr. Markus Klinger MBA, FEBVS
Vienna
More about the medical author →







