
A hip replacement may be necessary for various reasons. Replacing a hip prosthesis is more complex and demanding than the initial implantation. Here you will find further information as well as a selection of specialists and centers that perform hip replacement surgeries.
Reasons for Hip Replacement Revision Surgery
Various reasons may make it necessary to replace an artificial hip joint. Most commonly, replacement surgery is required due to prosthesis loosening. A distinction is made between aseptic (non-infectious) loosening and septic (infectious) loosening.
Other reasons for a revision surgery include
- fractures of the pelvis or femur that lead to implant loosening,
- wear and tear on prostheses that have been in place for a very long time, such as wear through of the polyethylene, or
- the fracture of ceramic components.
Septic Prosthesis Loosening
Septic prosthetic loosening of the hip, which results from a bacterial infection of the hip prosthesis, is less common.
An early infection can occur due to contamination during or shortly after the initial implantation. This may be caused by skin bacteria entering through the wound; direct contamination during the initial surgery is also possible.
Bacterial colonization via the bloodstream is more common, particularly in patients with serious pre-existing conditions, such as diabetes.
Late-stage infections of a hip replacement, which are more common, usually result from bacterial colonization of the implant via the bloodstream. Even hip replacements that have been in place for a long time and have been functioning well can suddenly become loose due to a bacterial infection.
New diagnostic methods indicate an increase in the proportion of septic-related loosening of endoprostheses. For this purpose, removed prostheses are examined using ultrasound, for example.
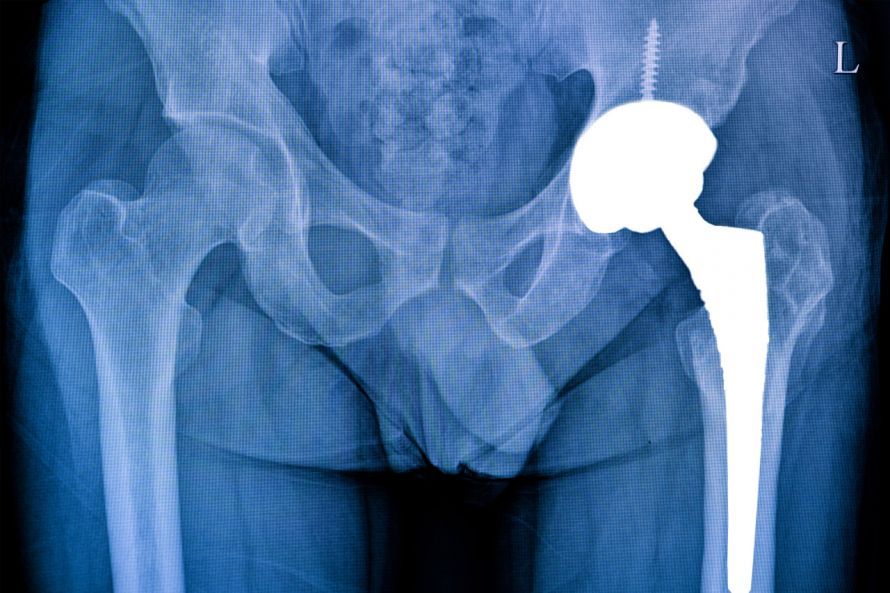
Aseptic loosening of the hip prosthesis
Aseptic loosening of the hip prosthesis is more common. Sooner or later, it affects every hip prosthesis, regardless of where it was implanted. It is facilitated by
- aging,
- wear and tear of the prosthesis materials, and
- reactions in the surrounding tissue.
Over the years, tiny particles of wear debris accumulate between the artificial joint head and the acetabular cup. These particles can cause inflammation in the tissue and, as a result, loosening of the hip prosthesis.
Improper use of the artificial hip joint is rarely the sole cause of hip prosthesis loosening. Nevertheless, heavy stress on the joint (including that caused by excess weight) should be avoided after the initial implantation. Regular monitoring of the prosthesis via X-ray examinations is also recommended.
Hip Replacement Revision for Prosthetic Infections
Patients who
- diabetes mellitus,
- rheumatoid arthritis,
- psoriasis,
- obesity, or
- a history of previous hip surgery on the same side
in their medical history. Bacterial infection sites pose a high risk of implant infection. These include, among others,
- dental abscesses,
- chronic urinary tract infections, or
- pneumonia.
For this reason, early antibiotic therapy is now recommended for patients with implanted hip prostheses who have a bacterial infection.
The symptoms of an acute hip prosthesis infection are
- pain,
- limited range of motion, and
- often significant redness, warmth, and swelling of the joint.
These symptoms may be absent in a late-onset infection. In most cases, an infection is accompanied by elevated inflammatory markers in the blood (leukocytosis, C-reactive protein, erythrocyte sedimentation rate).
Further diagnostic evaluation involves
- advanced imaging (X-ray, CT, MRI, or scintigraphy) and
- joint aspiration or biopsy followed by microbiological examination.
The treatment strategy depends on the type, duration, and severity of the infection, as well as the patient’s physical condition. It may include various measures, such as
- joint lavage with head and liner replacement (for early infections < 6 weeks),
- a one-stage prosthesis replacement (monoinfections, gram-positive bacterial spectrum, good bone stock),
- a two-stage replacement (temporary placement of an antibiotic-impregnated space maintainer made of bone cement).
The surgical technique depends on
- the timing of the infection,
- the bacterial species and their antibiotic resistance, as well as
- the patient’s general condition.
Hip Prosthesis Replacement Due to Prosthesis Instability
Instability present since the initial surgery is usually due to wear and tear of the components or hip impingement. Hip impingement refers to the repeated contact of prosthesis components with each other or with the bone.
General risk factors for instability and dislocations include
- spinal disorders with nerve and muscle dysfunction,
- previous revision surgeries,
- lack of patient cooperation,
- excessive alcohol consumption, and
- neurological diseases.
The majority of cases of joint instability require surgical hip replacement. The goal of the surgery is to restore soft tissue tension. Additional stability can be achieved through the use of appropriate prosthetic components, such as
- larger head diameters and head lengths,
- covered inlays,
- modular stem systems, or
- coupled inserts.
Hip Replacement for Fractures
Periprosthetic fractures (bone fractures in the prosthesis region) can
- result from accidents involving external force,
- in cases of aseptic loosening due to increased local bone resorption, as well as
- occur directly during surgery
.
When treating a fracture, the goal is to restore anatomical alignment and bony continuity.
If the prosthesis is firmly anchored and the situation allows, this can be achieved through osteosynthesis techniques (plates or wires). Unstable prostheses often require hip replacement with a different system that bridges the fracture and allows force transmission beyond the fracture site.
Occasionally, in cases of extensive bone injuries, replacing the prosthesis alone is not sufficient. In such cases, additional plates or wire bands must be applied.
Lifespan of Revision Prostheses
Over the course of a long life, multiple revision surgeries on the same hip prosthesis may be necessary.
The lifespan of revision hip prostheses is shorter than that of primary implants. With each revision surgery, it becomes more difficult to securely anchor the artificial hip joint.
Hip endoprostheses are classified according to
- model,
- bone condition,
- age, and
- the patient’s comorbidities, as well as
- individual stress
with a lifespan of 15 to 30 years.
Hip replacement revision surgery
Before hip replacement surgery
If the patient experiences symptoms such as groin, thigh, or knee pain, the treating physician will determine whether these are actually related to the endoprosthesis or are caused by other conditions. Other possible causes of these symptoms include:
- knee osteoarthritis,
- degenerative spinal disorders,
- neurological disorders.
To make a diagnosis, a clinical examination by the doctor, as well as laboratory and X-ray tests, are necessary. Occasionally, to confirm the diagnosis,
- a computed tomography (CT) scan,
- a magnetic resonance imaging (MRI) scan, or
- a scintigraphy
be required.
The doctor must assess the condition of the hip prosthesis fixation. In doing so, he or she checks whether the cup, the stem, or both components are loose. It must also be determined whether an infection is present and whether the stem or the cup has migrated.
In rare cases, a definitive assessment is only possible during surgery, when the prosthesis’s fixation can be examined in situ.
Various procedures are available for hip replacement surgery.
As part of the replacement surgery,
- the sliding components,
- only the cup,
- just the stem, or
- both components
be replaced.

In the event of an infection, the artificial hip joint can be replaced in one or two sessions.
If a two-stage replacement is planned, several weeks or even years may elapse between the two procedures. During the first procedure, the prosthesis infected with bacteria is removed, the tissue is cleaned, and a temporary prosthesis or antibiotic carrier is inserted.
This is replaced with the final hip prosthesis during the second surgery.
Procedure for Hip Prosthesis Replacement
A hip prosthesis replacement surgery is not always necessary. Some symptoms can (initially) be treated conservatively.
Once the decision to replace the artificial hip joint has been made, the surgical procedure must be determined. This depends, for example, on
- the type of loosening,
- the condition of the surrounding bone and soft tissue structures,
- the functional goals of the procedure (e.g., ability to participate in sports),
- the patient’s overall health,
- and, in the case of an infection, its duration and the type of pathogen.
In addition to the revision procedure, the timing of the hip prosthesis replacement surgery must be carefully considered. In cases of acute infection or dislocation of the prosthesis, surgery should be performed very soon.
The approach to hip prosthesis replacement surgery also depends on how the initial implant was inserted. If the initial hip prosthesis was cemented, the cement often must be completely removed.
In this case—and generally when removing the hip prosthesis from the bone—it is important to preserve as much intact tissue and bone material as possible.
Due to bone destruction caused by the loose prosthesis and cement, the risk of bone fractures during a revision surgery is significantly higher than during the initial implantation.
The surgeon decides on a case-by-case basis whether the new hip prosthesis will be cemented or cementless.
Duration of the Revision Surgery
Hip replacement revision surgery takes longer than the initial implantation of an artificial hip joint.
It is also more complicated, as there is, among other things, more extensive damage to the bone structure. Bone defects must be treated using the patient’s own bone or donor bone, along with special implants.
Preventing Infections of the Hip Prosthesis
The current standard in endoprosthetics includes
- the combination of cleanroom technology and antibiotic prophylaxis, as well as
- a careful and tissue-preserving surgical approach.
As a result, the infection rate associated with hip replacement surgery has dropped significantly over the past few decades. If an infection does occur, however, the prognosis is better than it was several decades ago.
Which specialist performs hip replacement revision surgery?
Hip replacement revision surgery is performed by a specialist in orthopedics and trauma surgery or a specialist in orthopedics.
A comprehensive joint replacement center typically specializes in such surgeries.

About the medical author
Dr. med. Matthias Pothmann
Sources
- Prothesenwechsel am Hüftgelenk. Leitlinien der Deutschen Gesellschaft für Unfallchirurgie. AWMF-Leitlinien-Register: Nr. 012/007. Entwicklungsstufe: 1. URL: http://www.awmf.org/uploads/tx_szleitlinien/012-007l_S1_Prothesenwechsel_am_Hueftgelenk_2008.pdf
- Tschauner, Christian (Hrsg.) (2004): Becken, Hüfte. Stuttgart: Georg Thieme Verlag.
- Ficklscherer, Andreas (2008): BASICS Orthopädie und Traumatologie. 2. Aufl. München: Urban & Fischer Verlag.
- Hermichen, Honke G. / Kistermann, Sibylle (2001): Gut leben mit dem neuen Hüftgelenk. Stuttgart: Georg Thieme Verlag. Endoprothese bei Koxarthrose. Leitlinien der Deutschen Gesellschaft für Unfallchirurgie. AWMF-Leitlinien-Register: Nr. 012/006. Entwicklungsstufe: 1. URL: http://www.awmf.org/uploads/tx_szleitlinien/012-006l_S1_Endoprothese_bei_Koxarthrose_2008.pdf



































