
In the past, hip surgery often involved a long incision and a recovery period lasting several weeks. Today, much has changed in orthopedics: Minimally invasive hip surgery, often referred to as the “keyhole” technique, allows for the implantation of a hip prosthesis in a way that is particularly gentle on the surrounding tissues. In this surgical procedure, muscles are generally no longer cut; instead, the natural gap between the muscles is used. This approach to the hip joint spares nerves, blood vessels, and soft tissue, resulting in less pain and faster wound healing. Whether an anterior approach (from the front) or a lateral approach (from the side) is chosen depends on the surgeon and the patient’s individual anatomy.
What is minimally invasive surgery?
Until a few years ago, hip surgeries were traditionally performed through fairly large incisions on the side or back of the hip joint. The major drawback of these techniques is the need to cut through or damage soft tissue structures and muscles. Bleeding or impaired wound healing in the surgical area was not uncommon.
Minimally invasive hip surgery has evolved steadily over the past ten years and is characterized in particular by small incisions and the complete preservation of these vital muscle structures.
The most commonly used minimally invasive technique for the hip joint is hip arthroscopy. This is also referred to as a “keyhole” technique using a camera. Through a small incision in the skin, surgeons insert endoscopic probes and surgical instruments. A light source is located at the tip of the endoscope. The camera’s image is transmitted live and magnified to a monitor.
This allows, for example, the removal of excess bone or the treatment of injuries to the labrum. However, the insertion of an artificial hip joint is not possible using the keyhole technique alone. Nevertheless, modern endoprosthetics has also seen the development of procedures that are particularly gentle on soft tissues.
Unlike in the past, minimally invasive approaches for hip joint replacement are now mostly performed from the front (AMIS) or from the front-lateral side (ALMIS). These areas feature so-called muscle gaps or intervals. The muscles are no longer cut or damaged to gain access to and a clear view of the joint; instead, special hooks are used to push the muscles aside. This allows for tissue-sparing surgery through a small skin incision and without muscle trauma.
The advantage of this method is that it eliminates the need for a large incision, resulting in a significantly smaller surgical wound. The muscles are not damaged. This means
- less pain for the patient,
- faster healing, and
- a lower risk of infection.
After minimally invasive surgery, the patient can usually be mobilized immediately following the procedure, get up on their own early on, and begin physical therapy quickly.
Minimally invasive surgery is particularly suitable for
- younger patients who are still working and
- older adults who want to regain mobility more quickly.
Surgeons specializing in these techniques now perform surgery on nearly all patients using minimally invasive approaches.
Minimally Invasive Surgery and Access in Hip Surgery: Rapid Mobilization After Hip Surgery Through Minimally Invasive Procedures
What are the general reasons for hip surgery?
The most common cause of damage to the hip joint is age-related wear and tear: Starting around age 30, the hip joint begins to wear down more and more. In so-called hip osteoarthritis (coxarthrosis), the thin layers of articular cartilage in the hip joint undergo severe wear and tear.
This wear-and-tear process is accelerated by
- sports injuries,
- accidents,
- postural problems, and
- excessive strain on the joints.
This degenerative process ultimately leads to severe pain during movement and increasing limitations in mobility.
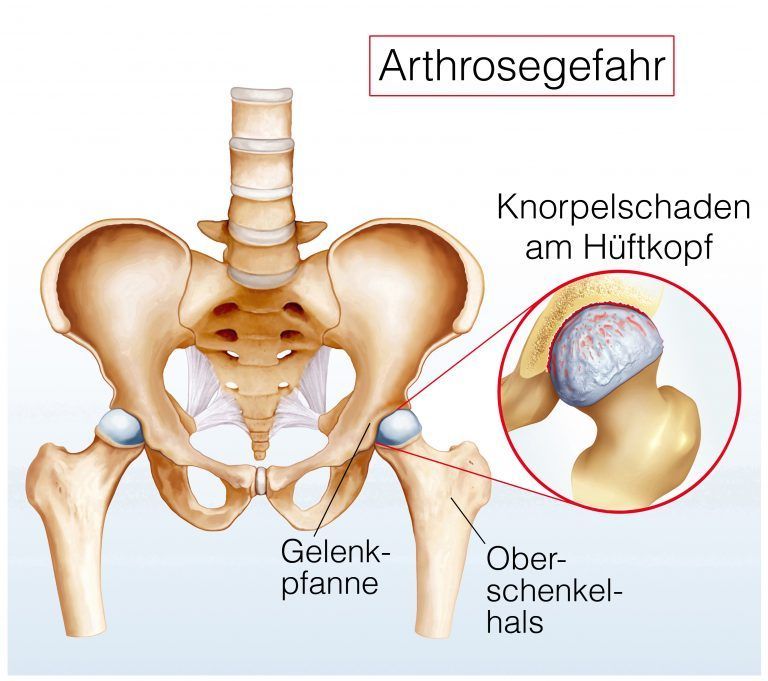
Severe hip pain can usually be managed for a time with pain-relieving medications. Physical therapy and alternative treatments, such as acupuncture, also primarily help to relieve pain.
However, when such conservative treatments are no longer effective, patients’ suffering increases. At that point, the use of an artificial hip joint (hip endoprosthesis, hip TEP) should be considered.
Who is a good candidate for an artificial hip joint?
According to current guidelines, you are a candidate for hip replacement surgery if:
- there is significant structural damage to the hip joint (coxarthrosis at least Kellgren/Lawrence Grade 3 or avascular necrosis of the femoral head at least ARCO III c),
- conservative treatment attempts (pain medication, physical therapy, weight loss) have not led to sufficient improvement after a period of at least three months,
- despite conservative treatment measures, you experience significant suffering manifested by hip-related symptoms, limited mobility, and a reduced health-related quality of life.
Contraindications—that is, reasons that preclude surgery—are, according to guidelines:
- active infections and inflammation,
- acute or chronic comorbidities associated with an increased risk of mortality,
- and a body mass index (BMI) of > 40.
These factors are associated with an increased risk of wound healing disorders and postoperative complications. In such cases, doctors may initially decline to perform surgery and advise on weight loss. The same applies to the minimally invasive method.
In recent years, minimally invasive hip surgery has gained popularity among patients and is increasingly in demand.
However, minimally invasive hip replacement surgery is not suitable for every patient. Whether minimally invasive hip surgery is an option depends
- the patient’s health status,
- the method of anchoring the prosthesis in the bone, and
- the extent of the damage to the hip joint
.
Minimally invasive hip surgery is particularly less suitable for patients with
- a history of hip surgery,
- bone deformities,
- scarring in the surgical area,
- or extreme obesity.
What is minimally invasive hip surgery?
Traditionally, hip surgery involved fairly large skin incisions that required the muscles to be detached. Minimally invasive hip surgery, on the other hand, is characterized by maximum preservation of soft tissue. Access to the hip joint is gained through natural gaps in the muscles. This means that the surgeon holds the muscle groups aside using special hooks instead of cutting through them. This muscle-sparing approach keeps the muscles and tendons essential for stability intact. The incision is often only a few centimeters long, which reduces scarring and promotes wound healing. This preservation of tissue is the main reason why patients experience less pain after surgery and can often leave the hospital sooner.
What are the different approaches to the hip joint?
In modern orthopedics and trauma surgery, various minimally invasive approaches have become established. The anterior approach utilizes a natural gap at the front of the thigh. The AMIS method is well known in this context. This approach is considered particularly gentle, as no muscles need to be detached from the bone. Alternatives include the anterolateral approach—from the front and side—or the purely lateral approach from the side. The choice of approach to the hip joint often depends on the surgeon’s experience and the patient’s individual anatomy. Specialists such as Nogler and Thaler have played a key role in further developing these surgical techniques to make hip replacement as safe as possible.
Implantation of a Minimally Invasive Hip Prosthesis: Hip Treatment at the Clinic
Procedure: How is the minimally invasive procedure performed?
The procedure is usually performed under general anesthesia or spinal anesthesia. After making the skin incision, the surgeon creates a path to the acetabulum through the muscle gaps. The femoral head, which has been damaged by osteoarthritis, is removed, and the acetabulum is prepared to receive the artificial hip cup. Next, the stem of the hip prosthesis is inserted into the femur. Because the soft tissues are preserved, the view of the joint is often limited, which is why this surgical technique requires a great deal of experience. After the prosthetic head is positioned and the joint is repositioned, the incision is closed with skin sutures. The surgery typically lasts between 45 and 90 minutes.
Advantages: Less pain and faster mobilization
The greatest advantage of minimally invasive hip surgery is significantly faster rehabilitation. Since the stabilizing muscles remain intact, patients can often get out of bed and bear weight on their leg as early as the day of surgery. This promotes rapid and uncomplicated healing and reduces the risk of blood clots. In addition, blood loss is lower, which reduces the strain on the circulatory system. Patients report less postoperative pain and require smaller amounts of pain medication. The recovery time is often shortened by weeks compared to patients who undergo conventional surgery. The cosmetic outcome is also often better due to the small skin incision and reduced scarring.
Preparation and Anesthesia: The Path to the Operating Room
Before the actual procedure, precise planning takes place at the clinic. Using digital X-rays, the surgeon determines the size and position of the planned hip prosthesis in advance. Minimally invasive hip surgery can be performed under various forms of anesthesia. General anesthesia is often chosen, but spinal anesthesia is also an option; with this method, the patient remains awake but feels no pain from the waist down. The patient’s positioning on the operating table is crucial. Depending on the surgical technique chosen—such as the anterior approach—the patient lies on their back on a special extension table that allows the leg to be moved during surgery in a way that provides optimal access to the joint without stretching or tearing muscles.
The Approach: Why the Muscle Gap Is Crucial
The key term “minimally invasive” refers not only to the length of the skin incision but primarily to how the muscles beneath the skin are handled. With conventional methods, parts of the gluteal muscles often had to be detached to reach the joint. With the minimally invasive technique, the surgeon looks for a natural gap between the muscles. With the anterior approach, for example, this gap is located between the tensor fasciae latae muscle and the sartorius muscle. Special hooks and retractors are inserted through this gap to gently hold the tissue aside. This creates a tunnel leading directly to the joint capsule. Since no muscles are cut, there is no need for a complex tendon suture at the end of the surgery, and the leg’s strength is immediately preserved postoperatively.
Detailed Procedure
The actual surgical procedure typically lasts between 45 and 90 minutes and follows a standardized protocol:
1. Incision and Exposure The surgeon makes an incision approximately 6 to 10 centimeters long, usually on the front or side of the thigh. After dissecting through the subcutaneous tissue and the fascia, the muscles are bluntly pushed aside to expose the joint capsule.
2. Removal of the femoral head The joint capsule is opened. To make room for the prosthesis, the femoral head—which has been worn down by osteoarthritis—is cut off at the femoral neck using an electric saw and removed. This is often the most difficult part, as space is limited.
3. Preparation of the acetabulum The surgeon now has a clear view of the acetabulum in the pelvic bone. Remnants of cartilage and degenerative tissue are removed. Using special drills, the acetabulum is shaped into a hemispherical form until the bone is healthy and well-vascularized. This ensures that the artificial hip socket will integrate properly later on.
4. Implantation of the Components The artificial acetabulum, usually made of titanium, is pressed into the prepared socket (press-fit procedure) or, less commonly, screwed in. An inlay made of ceramic or highly cross-linked polyethylene is inserted into this metal shell to serve as a sliding surface. Next, the femur is prepared. Using rasps, the medullary canal of the femur is shaped so that it can accommodate the prosthetic stem. The stem is driven into place and fitted with a matching prosthetic head.
5. Repositioning and Functional Testing Before closing the incision, the surgeon reduces the joint (repositioning) and checks its stability and range of motion. Leg length is also checked and, if necessary, corrected by adjusting the size of the head. Only when the joint is stable in all positions and does not dislocate is the definitive prosthesis permanently fixed in place.
6. Wound Closure Since no muscles need to be sutured, only the fascial sheath and subcutaneous fat tissue are sutured. The skin is usually closed with an absorbable suture or skin staples. Drainage is often omitted to minimize blood loss.
Implants and Materials
Minimally invasive hip surgery utilizes modern, high-performance materials. The implant is usually cementless; the rough surface of the titanium implants fuses with the bone like Velcro. In older patients with poor bone quality (osteoporosis), the stem may also be cemented to ensure immediate stability. The bearing pair—that is, the connection between the head and the cup—is now often made of ceramic-on-ceramic or ceramic-on-polyethylene, as these materials are extremely wear-resistant and durable.
Postoperative Care and Rehabilitation
The major advantage of this tissue-sparing method becomes apparent during postoperative care. Since the joint’s muscular guidance remains intact, patients are generally able to get out of bed (bearing full weight) immediately after waking from anesthesia or that same evening. The first steps are practiced under the guidance of a physical therapist. Climbing stairs is often possible after just a few days. The hospital stay is usually only 3 to 5 days. Subsequent rehabilitation, whether outpatient or inpatient, strengthens muscle development and optimizes gait. Since the incision is small, wound healing is usually uncomplicated, and the sutures can be removed after about 12 to 14 days.
FAQ: The 8 Most Important Questions About Minimally Invasive Hip Surgery
What does “minimally invasive” mean in hip surgery?
In hip surgery, “minimally invasive” means that access to the hip joint is chosen in a way that minimizes damage to the soft tissues. The incision, at approximately 8 to 10 cm, is significantly smaller than with traditional methods. More importantly, however, the surgeon utilizes a natural gap between the muscle groups. This means that no muscle needs to be cut or detached from the bone, which preserves the hip’s postoperative stability and strength.
What are the advantages of the minimally invasive technique?
The advantages are numerous: Because the tissue is spared, patients experience less pain after surgery and require fewer pain medications. Blood loss is reduced, and scarring is less noticeable. Since the muscles remain intact, rehabilitation can proceed more quickly. Many patients can put their full weight on the leg as early as the day of surgery and often leave the hospital after just a few days. The risk of the prosthesis dislocating is also reduced.
What surgical approaches are available?
There are various minimally invasive surgical techniques. The most common is the anterior approach (Direct Anterior Approach, DAA), in which the incision is made on the front of the thigh. A variation is the AMIS method (Anterior Minimally Invasive Surgery). The anterolateral (anterior-lateral) approach is also possible. The choice of approach depends on the surgeon’s experience and the patient’s anatomical characteristics. Pioneers such as Nogler and Thaler have played a key role in further developing these techniques.
How long does recovery take?
Thanks to the tissue-sparing surgical technique (Tissue Sparing Arthroplasty), the recovery time is usually significantly shorter. Mobilization often begins just a few hours after the procedure under the guidance of a physical therapist. Most patients can walk again without walking aids after about 3 to 6 weeks. It usually takes 3 to 6 months to return to full athletic activity, depending on the individual’s healing process.
Who is this procedure suitable for?
In general, minimally invasive hip surgery is suitable for almost all patients with hip osteoarthritis who require a hip replacement. There may be limitations for severely obese or very muscular patients, as visibility of the joint can be compromised in these cases. The orthopedic surgeon may also sometimes resort to conventional approaches for complex revision surgeries or severe deformities to ensure safe implant placement.
How is the surgery performed?
The procedure is usually performed under general anesthesia or spinal anesthesia. After making the skin incision, the surgeon creates a path to the acetabulum through the muscle gaps. The diseased femoral head is removed, the acetabulum is reamed, and the new acetabular cup is inserted. The stem is then inserted into the femur, and the prosthetic head is attached. After checking mobility and leg length, the skin is sutured.
Are there any risks associated with this procedure?
As with any surgical procedure, there are general risks such as infection, thrombosis, or bleeding. Specific to the minimally invasive anterior approach is the risk of irritation to the cutaneous nerve in the thigh, which can lead to numbness but usually resolves on its own. Soft tissue damage to blood vessels and nerves is rare, as the surgery is performed with particular care. An experienced team at a specialized clinic for orthopedics and trauma surgery minimizes these risks.
What should you keep in mind after surgery?
In the initial period following hip surgery, extreme movements should be avoided to ensure that the hip prosthesis heals properly. Subsequent rehabilitation, whether on an outpatient or inpatient basis, helps rebuild muscle strength and restore a normal gait. Regular follow-up visits with a specialist ensure a good long-term outcome of the surgery.

About the medical author
Prof. Dr. med. Karl Philipp Kutzner
Medical Editor · Mainz
Prof. Dr. med. Karl Philipp Kutzner – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.
Sources
- bvou.net/leitlinie-unterstuetzt-bei-indikationsstellung-zur-hueft-endoprothese
- deutsches-zentrum-fuer-orthopaedie.de/huefte/minimal-invasive-operationsmethoden
- internisten-im-netz.de/aktuelle-meldungen/aktuell/hueftprothese-minimalinvasiv-oder-klassisch-implantieren.html
- S3-Leitlinie „Evidenz- und konsensbasierte Indikationskriterien zur Hüfttotalendoprothese bei Coxarthrose“, AWMF-Register-Nr. 187-001, Version: 1.0 (24.03.2021)
























