
Medical professionals distinguish between a unilateral (unicondylar) and a bicondylar sliding prosthesis of the knee joint—the largest joint in the human body. It is considered a proven treatment for unilateral osteoarthritis of the knee joint. A unilateral sliding prosthesis involves a partial replacement of the knee joint (partial knee replacement), whereas a bicondylar sliding prosthesis involves a complete surface replacement of the knee joint. The unilateral sliding prosthesis has several advantages over the bicondylar sliding prosthesis.
Here you will find further information as well as a selection of sliding prosthesis specialists and centers.
Historical Background of the Sliding Prosthesis in the Knee Joint
The first attempts at total knee arthroplasty date back to 1890 and were conducted by the Berlin surgeon Gluck. The implant used at that time was a hinged joint made of ivory. It was anchored using nickel-plated screws and a plaster-rosin cement. Septic complications (inflammation and sepsis) occurred in all 14 patients.
The unilateral sled prosthesis was designed to treat unicompartmental medial or lateral knee osteoarthritis. In 1952, McKeever and Alliot developed a unicondylar metal tibial plateau prosthesis with a tibial anchoring groove.
In 1954, McIntosh of Toronto created an implant made of Vitallium, which was available in various thicknesses. Here, too, the procedure involved only the replacement of the tibial defect. The main problem was the implant’s tendency to dislocate.
In 1968, Gunston introduced a two-component sled prosthesis (metal–plastic), the Polycentric Knee. In this sled prosthesis, which operated on the low-friction principle, a semicircular metal disc was implanted in the area of the femoral condyle. It moved within a correspondingly grooved tibial polyethylene block. Anchoring was achieved using bone cement. However, the results were unsatisfactory.
The principle of rail guidance was abandoned following Englbrecht’s further development in 1969. He developed a metal sled that was implanted in the region of the femoral condyle. The sled made point contact with a tibial polyethylene block.
This was a model with three degrees of freedom, without forced guidance, and with minimal form-fit of the contact surfaces. Since the tibial component was available in only one size and thickness, extensive bone resection was often required on the tibia. This subsequently led to an increase in stress fractures.
This weakness of the first model of the St. Georg prosthesis was partially addressed by a further development by Marmor in 1972. He developed a modular system with a true polycentric design and various tibial implants. Due to material limitations, problems arose primarily with the thinner tibial implants.
In the years that followed, the St. Georg and Marmor prostheses underwent constant further development.

Knee pain, such as that caused by osteoarthritis, affects many older adults. A knee replacement is often necessary © Prostock-studio | AdobeStock
Current Models and Concepts
There are currently a wide variety of different unicondylar prosthesis models on the joint replacement market. With one exception—the Oxford knee—the femoral bearing surface corresponds to an idealized condylar shape.
Differences are evident in part in
- the anchoring elements on the femoral component and tibial plateau,
- the shape of the tibial bearing surface (flat, curved, or mobile),
- the implantation technique for the tibial component (inlay or onlay technique, or “metal-backed”), and
- the surgical approaches (conventional, minimally invasive).
Unicompartmental knee replacement has the advantage over bicondylar replacement in that
- the mechanics of the joint remain virtually unchanged from those of the original knee,
- patients recover more quickly,
- postoperative scores are better, and
- patients are able to resume more normal activities.
The disadvantage lies in a more demanding surgical technique, which may be associated with a higher revision rate.
The unicondylar sliding prosthesis is considered a reliable treatment option for medial or lateral knee osteoarthritis.
Thanks to continuous improvements in materials and surgical techniques, prostheses are remaining in the body for longer and longer periods. Consequently, the indication for implanting a unicondylar knee prosthesis is increasingly being discussed even for young patients.
In addition to technical improvements, the surgeon’s experience has a decisive impact on the outcome. Here, the learning curve is relatively flat. This is due, among other things, to the limited visibility during implantation, which is usually performed using minimally invasive techniques.
Most of the sliding prostheses used today have the following characteristics:
- an idealized condylar shape of the femoral component, with anchoring methods that sometimes vary significantly
- and a tibial component with a plastic bearing surface, either made entirely of polyethylene or with a metal backing, known as a “metal-back” implant.
Femoral anchoring is typically achieved via one or more pins. Depending on the implant, implantation is either cemented or cementless. There are also cemented and cementless variants for the tibial component.
Metal-back implants also typically require an anchoring fin. Pure polyethylene components, on the other hand, are cemented using the so-called onlay technique. In the onlay technique, the tibial component is cemented directly onto the tibial tuberosity.
With regard to the materials used, the greatest advances in development have been in the area of
- manufacturing,
- processing, and
- sterilization
of polyethylene.
Indications: When is the implantation of a unicondylar sled prosthesis appropriate?
An indication for a unicondylar sled prosthesis is
- gonarthrosis, i.e., osteoarthritis of the knee joint
- unicompartmental, posttraumatic, or degenerative osteoarthritis, as well as
- osteonecrosis (Ahlbäck’s disease)
. The ligamentous apparatus—particularly the cruciate ligaments—must be intact. The sled prosthesis is implanted when there is unilateral wear in the knee joint. It is particularly suitable when only one compartment of the knee is damaged. A current X-ray of the knee joint is always taken before the decision to operate is made.
Contraindications for the implantation of a unicondylar knee prosthesis include:
- Severe obesity (BMI > 35)
- Acute or chronic infection, local or systemic (or a history of such an infection)
- Insufficiency of the anterior or posterior cruciate ligament
- A previous realignment osteotomy
- Extension deficit of more than 10°
- Clinical varus/valgus deformity of more than 10°
- Advanced involvement of the other compartments
- Rheumatoid arthritis
- Symptomatic retropatellar osteoarthritis (behind the kneecap)
- A significantly altered leg axis with varus or valgus deformity > 10° is a contraindication
Postoperative care and rehabilitation following sled prosthesis surgery
The procedure is typically performed on an inpatient basis, requiring a short hospital stay. Mobilization begins on the very first day after surgery with physical therapy. Once the drain has been removed, patients are allowed to bear weight up to their pain threshold. They receive physical therapy and use a continuous passive motion (CPM) device. In addition to the CPM device, physical therapy plays an important role.
Depending on their age and overall health, patients are able to walk without crutches after 2 to 4 weeks. Many patients who have undergone the surgery report a significant reduction in pain early on.
Summary: Advantages and Potential Disadvantages of a Partial Knee Replacement
The unicondylar knee prosthesis is a type of artificial knee joint that is only partially implanted. The advantages of the minimally invasive implantation of a unicondylar knee replacement lie in the fact that it does not interfere with the extensor mechanism. Postoperative pain is reduced, as are the formation of adhesions and the infection rate. In addition to improved cosmetic results, the range of motion is also better than with the conventional procedure.
The disadvantages of a sled prosthesis include the potential for misalignment of the components and the technically demanding surgical procedure. These disadvantages can be mitigated through the use of navigation systems and robotic technology, which have been available to us for some time.
Contraindications for the implantation of a unicompartmental knee prosthesis include
- osteoarthritis of the contralateral compartment,
- rheumatoid arthritis,
- a varus-valgus deformity of more than 10°,
- a flexion deficit of more than 10°, and
- cruciate ligament insufficiency, particularly for mobile prosthetic knees (increased risk of dislocation).
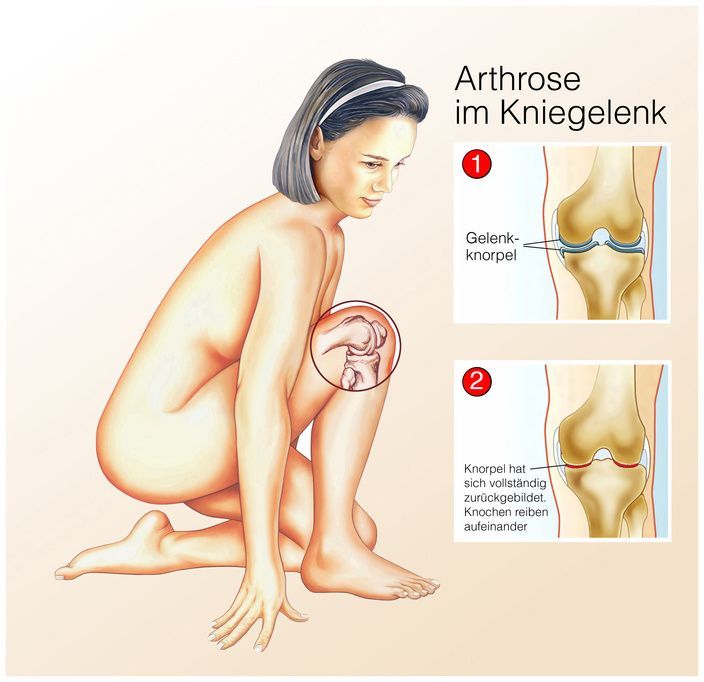
Under certain conditions, osteoarthritis may be a contraindication for unicompartmental knee replacement © henrie | AdobeStock
Additional advantages of unicompartmental knee replacement compared to bicondylar replacement include
- the preservation of both cruciate ligaments,
- preservation of the original biomechanics, and
- the preservation of bone in the unaffected compartment and in the femoropatellar joint.
Patients with unicompartmental knee replacement have lower perioperative morbidity and improved mobility compared to patients who have undergone bicondylar prosthesis implantation.
Based on our mid-term results, it can be concluded that the use of a ligament tensioner results in stable knee joints in both flexion and extension with correct alignment. The joint plane is restored, and the surgical technique is reliable.
Due to the prosthesis’s anatomical design and the minimally invasive implantation technique, postoperative morbidity is lower. Only time will tell whether this procedure is also suitable for younger and active patients.
FAQ
When is a sled prosthesis in the knee joint recommended?
A sled prosthesis is primarily recommended for osteoarthritis when only one segment of the knee joint is affected. Typical indications include unilateral knee osteoarthritis (medial or lateral) or osteonecrosis, provided the cruciate ligaments are intact.
How long does a knee replacement last?
The longevity of modern prostheses has increased significantly thanks to improved materials and surgical techniques. Studies show that many implants remain functional for 15 years or longer, depending on the patient’s load, age, and activity level.
What are the advantages of a partial knee replacement over a total knee replacement?
Compared to total knee replacement (TKR), a partial knee replacement preserves more healthy joint structures, is less invasive, and allows for faster rehabilitation. Patients often report more natural mobility and less pain after surgery.
What does postoperative care involve?
Postoperative care includes physical therapy, continuous passive motion (CPM) devices, and early weight-bearing within pain tolerance limits. Typically, patients can walk without crutches after 2 to 4 weeks and gradually return to normal daily activities.












































