
Reflux—medically known as gastroesophageal reflux disease (GERD)—is one of the most common disorders of the digestive tract. About 20% of the population suffers from it; reflux and heartburn are therefore among the most common complaints.
When acidic stomach contents flow back—that is, when stomach contents enter the esophagus—it causes the typical burning sensation behind the breastbone (heartburn). This acute heartburn can occur as a single episode or recur. In this overview of symptoms and treatment, you’ll learn how reflux develops, which warning signs to watch for, and which therapies can help.
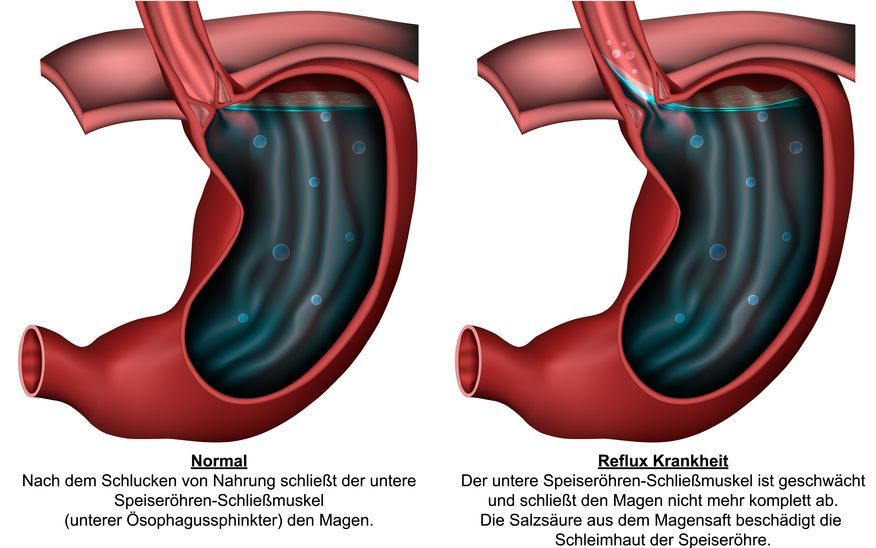
Reflux disease refers to symptoms that occur when acidic stomach contents flow back into the esophagus. This is usually triggered by a malfunctioning sphincter between the esophagus and the stomach; GERD can cause heartburn—ranging from occasional heartburn to chronic reflux disease.
What are the causes and risk factors for reflux disease?
In reflux disease, the barrier at the entrance to the stomach—the sphincter at the lower end of the esophagus and the opening through the diaphragm—fails. If this area becomes too weak or is displaced (e.g., due to diaphragmatic problems), stomach contents can flow back: Stomach contents enter the esophagus, stomach acid rises into the esophagus, and the reflux flows back, potentially irritating the mucous membrane—leading to symptoms such as coughing, hoarseness, or laryngitis. This explains why reflux can cause symptoms such as belching and heartburn. (Synonyms: GERD, gastroesophageal reflux disease; also frequently searched for as “gastroesophageal reflux disease.”)
Common risk factors that contribute to reflux disease include, among others:
- Being overweight and increased abdominal pressure (tight clothing, heavy lifting, straining).
- Pregnancy (hormone-induced weakening of the lower esophageal sphincter, increased abdominal pressure).
- Nicotine and alcohol (reduce sphincter tone and irritate the mucous membrane).
- Various medications (e.g., certain pain relievers, sedatives, blood pressure medications).
- Late, large meals; high-fat foods; excessive coffee or chocolate; and heavily spiced foods.
Two main causes are of primary importance:
-
Inadequate function of the sphincter at the entrance to the stomach (weak barrier or valve);
-
Reduced motility of the esophagus (impaired clearance), causing refluxed stomach contents to remain in the esophagus for longer periods.
Both triggers can be primary (without an identifiable underlying condition) or secondary to other disorders—such as anatomical changes in the diaphragm or chronic gastric emptying disorders. Reflux can occur in all of these situations; it typically causes a burning sensation behind the breastbone and other symptoms.
What symptoms does reflux cause?
Reflux symptoms: The main symptom is heartburn—a burning sensation behind the breastbone that sometimes radiates from the breastbone up to the throat. Belching and heartburn often occur together, frequently accompanied by a sour taste in the mouth.
Other symptoms may include:
- Nausea, occasionally vomiting
- frequent coughing fits, the urge to clear one’s throat
- Inflammation in the larynx or throat, hoarseness
- Difficulty swallowing
- Pain in the upper abdomen
When stomach acid enters the esophagus, it can irritate the esophageal lining and worsen symptoms. So-called “silent reflux” can manifest primarily as coughing, a hoarse voice, or a scratchy throat—with little or no classic heartburn.
Typical triggers that exacerbate symptoms include:
- shortly after eating or after large meals
- after drinking alcohol or eating very fatty or sweet foods
- while lying down (e.g., at night) or when bending over or straining (increased abdominal pressure)
How is reflux disease diagnosed?
First step: Doctors take a medical history (symptoms, lifestyle habits, comorbid conditions) and perform a physical examination. If gastroesophageal reflux disease (GERD) is suspected, specific tests will follow.
Endoscopy / Gastroscopy (ÖGD)
During a gastroscopy, a flexible endoscope is inserted through the mouth and throat to directly examine the lining of the esophagus and stomach. This allows for the detection of irritation caused by stomach acid in the esophagus, erosions (erosive reflux disease), or Barrett’s esophagus. If necessary, a tissue sample is taken and analyzed in the laboratory. A hiatal hernia at the entrance to the stomach may also be visible—a common anatomical cause that can contribute to reflux disease.
pH monitoring / impedance pH monitoring
A thin probe is inserted through the nose into the lower part of the esophagus (near the sphincter). Over a 24-hour period, it measures how often and for how long stomach contents enter the esophagus—that is, the reflux of stomach contents (acidic and, if applicable, non-acidic). The test objectively shows when reflux occurs and how severe it is (e.g., at night while lying down), and documents whether reflux reaches as high as the throat.
Additional diagnostic procedures
- Barium swallow X-ray: Assessment of the swallowing process and detection of a hiatal hernia; it shows whether the junction between the esophagus and the stomach (at the diaphragm) is correctly positioned or has shifted into the abdominal cavity.
- ENT evaluation: In cases of cough, hoarseness, or laryngitis (suspected “silent” reflux), an ENT specialist examines the upper respiratory tract.
- Manometry (optional): Measures pressure and motility in the esophagus and the lower esophageal sphincter.
Goal of the diagnostic evaluation: To determine how often stomach contents flow back into the esophagus, whether this irritates the mucous membrane, and whether factors such as a diaphragmatic or hiatal hernia at the entrance to the stomach are present. This allows for precise planning of diagnosis and treatment.
Self-Care for Reflux Disease
Diet
- Eat protein-rich and light meals: Proteins stimulate gastrin production and can improve the tone of the esophageal sphincter—allowing it to close more reliably at the entrance to the stomach.
- Small meals instead of large portions: Large, heavy meals increase pressure in the abdominal cavity and can lead to reflux.
- Choose low-fat and low-carbohydrate foods; eat slowly and chew thoroughly.
- Do not eat anything 3–4 hours before bedtime: Reflux occurs more easily when lying down; this way, less stomach acid enters the esophagus at night and the mucous membrane is less irritated.
- Avoid/identify triggers: Very fatty, heavily spiced, or overly sweet foods can cause belching and worsen heartburn, and may contribute to reflux disease. A food diary can help you identify your personal triggers.
Stimulants
- Avoid alcohol as much as possible: It irritates the lining and weakens the lower esophageal sphincter—making it easier for stomach contents to flow back up.
- Avoid nicotine: It promotes the production of stomach acid and makes symptoms more likely.
- Test coffee on an individual basis: Caffeine can increase acid production, though for some people it may actually help by increasing gastrin levels—try small amounts with meals.
Daily Life & Body Position
- Raise the head of the bed (10–15 cm): This reduces the likelihood of stomach contents entering the esophagus at night.
- Wear loose-fitting clothing: Belts or pants that press on the stomach or diaphragm can contribute to reflux.
- Stay upright after eating (at least 30–60 minutes) and avoid bending over heavily.
- Maintain a healthy weight: Being overweight increases pressure on the lower part of the esophagus and causes more frequent reflux.
- Diaphragmatic breathing and moderate exercise (such as walks after meals) help keep the valve between the esophagus and stomach closed.
If symptoms persist, occur very frequently, or if there are signs of “silent” reflux (e.g., chronic cough/hoarseness, laryngitis), a medical evaluation is necessary—especially in cases of GERD (gastroesophageal reflux disease).
Medical Treatment for Reflux
A stepwise approach: First, lifestyle measures, supplemented—if necessary—by medication. Surgical procedures may be considered in cases of persistent symptoms or complications.
Medication
- Proton pump inhibitors (PPIs): The first-line treatment; they inhibit the production of stomach acid and thereby reduce irritation caused by gastric juices. Guidelines recommend a time-limited course of treatment followed by a dose review.
- H2 blockers/antacids/alginates: As an alternative or adjunct, e.g., for nighttime symptoms; well-suited for on-demand therapy.
- Prokinetics: In selected cases to improve gastric emptying.
- Important: Regularly assess whether medication can be reduced or discontinued.
When to perform surgery?
- Insufficient response despite adequate PPI therapy.
- Frequent/erosive forms, complications (e.g., Barrett’s esophagus).
- Large diaphragmatic hernia (hiatal hernia) requiring anatomical correction at the junction.
- Long-term need for medication in younger patients.
Surgical options
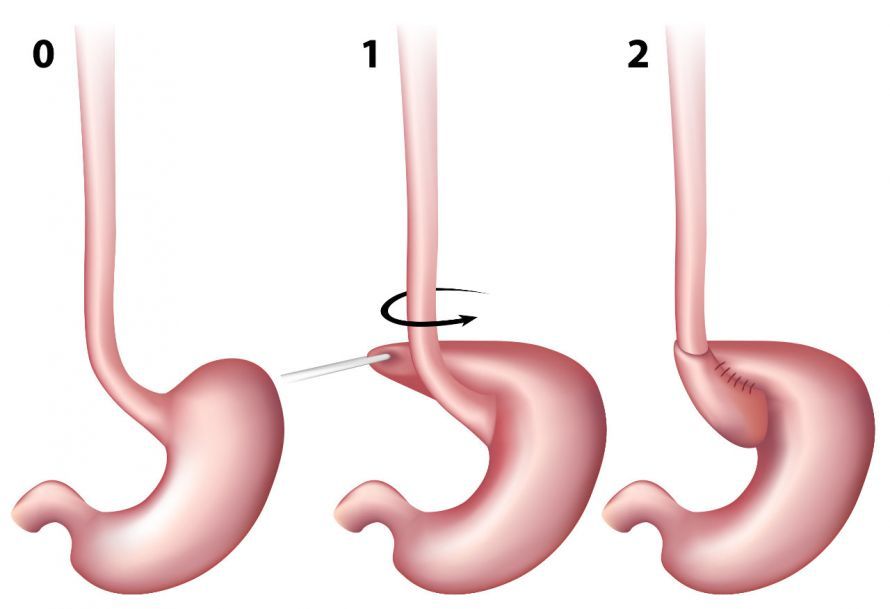
- Laparoscopic fundoplication: The upper part of the stomach is wrapped around the junction in a cuff-like manner to increase the closure pressure; any existing hiatal hernia is also repaired at the diaphragm. Goal: improved function at the junction without the need for long-term medication.
- Magnetic ring system (LINX): A chain of magnetic beads stabilizes the valve; advantages typically include a shorter surgery time and the ability to belch and vomit.
- Both procedures are generally minimally invasive and are selected on a case-by-case basis depending on the findings.
Notes on a “silent” course
If coughing, hoarseness, or laryngitis occur despite few typical symptoms, a “silent” course may be present; in such cases, an ENT evaluation and a trial of PPI therapy are often advisable.
Magnetic Ring Surgery (LINX)
Magnetic ring surgery is a gentle, minimally invasive procedure for antireflux repair. During the procedure, a flexible chain of magnetic beads is placed at the entrance to the stomach. The beads attract each other and stabilize the closure mechanism; when swallowing, they briefly move apart to allow food and drink to pass through.
Advantages:
- Belching and vomiting are generally still possible.
- Often results in fewer gas-related symptoms and a reduced feeling of fullness.
- Laparoscopic access via small incisions in the abdomen; the surgery is usually brief.
- There is minimal additional irritation to the surrounding tissue.
Which medical specialists treat reflux?
Symptoms of reflux disease usually lead patients to see their primary care physician first. In severe cases, internists and gastroenterologists supplement the individual reflux treatment.
These specialists in internal medicine and gastroenterology are experts in the treatment of reflux disease. After completing their medical training, they undergo several years of specialized residency training to focus on the comprehensive diagnosis and treatment of diseases of the internal organs, particularly those of the digestive system.
Conclusion
Reflux disease is common but easily treatable. Lifestyle changes and medication (e.g., PPIs) help many patients; for persistent symptoms, effective, minimally invasive options such as fundoplication or a magnetic ring are available. The best way to determine which strategy is right for you is to consult with a specialist—based on your test results and preferences.
Share this article

About the medical author
Prof. JoergG. Albert
Medical Author
Prof. Dr. med. Jörg G. Albert – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.
View full expert profile →



























