
A total knee replacement (TKR) involves the complete replacement of the cartilage surface of the knee joint, which has been severely damaged by wear and tear. Advanced osteoarthritis typically causes significant discomfort in the knee joint and can no longer be adequately treated with conservative measures. Depending on the extent of wear and tear in the knee joint or the presence of accompanying conditions such as instability or misalignment, various types of total knee replacements are available. These can generally be categorized as uncoupled, partially coupled, and coupled total knee replacements.
Here you will find further information as well as a selection of total knee replacement specialists and centers.
Knee Replacement Surgery: Knee Prosthesis, Artificial Knee Joint & Implantation
Joint wear (osteoarthritis) caused by chronic improper use and excessive strain destroys the physiological (healthy) function of the joint. Joint wear refers to the gradual wearing down of the cartilage surfaces on the bony joint surfaces over time. This leads to the breakdown of cartilage cells and inflammatory reactions, resulting in pain.
The video shows the progression of osteoarthritis and its effects on the joint:
When the disease is far advanced and can no longer be satisfactorily treated with conservative therapies, the only effective solution is usually the implantation of an artificial knee joint—a knee endoprosthesis. In this way, physicians can effectively counteract pain and limited mobility.
Types of Knee Replacements: What Knee Replacement Systems Are Available?
The type of knee replacement used for a knee joint affected by osteoarthritis depends on the severity of the condition and the specific areas of the knee joint involved. A total knee replacement is not always necessary. Often, it is sufficient to replace only certain parts of the joint.
One of the following prosthetic systems is used as a knee replacement:
- Sliding prosthesis: For isolated damage to the inner (common) or outer (rare) part of the knee joint.
- Patellar retropatellar surface replacement: For isolated retropatellar osteoarthritis (wear and tear beneath the patella)
- Total Knee Arthroplasty (TKA) (complete surface replacement)
- Uncoupled total knee arthroplasty (surface replacement): Complete replacement of all joint components. Used when multiple areas of the knee joint are worn but the ligamentous apparatus of the knee remains intact.
- Partially Coupled Total Knee Arthroplasty: Total knee replacement for malalignments with moderate ligamentous imbalance or cruciate ligament damage. The prosthesis simultaneously provides some of the ligament’s function. Only partial stabilization of the joint and support for the existing collateral ligament structures.
- Coupled Knee TEP: Total knee replacement for severe ligament instability and significant axial misalignment. In this type of prosthesis, the tibial plateau (shinbone) and femoral component (thigh bone) are firmly connected to each other via a coupling mechanism.
The individual knee replacement models also differ in a variety of other parameters, such as:
- Material (titanium and its alloys, cobalt-based alloys, steel)
- Coating (titanium/aluminum and ceramic oxide)
- Surface structure (micro-/macrostructuring)
- Cemented vs. cementless
- Shafted vs. non-shafted
The video demonstrates the principle of knee joint endoprostheses:
Knee Replacement Surgery: Cementless and Cemented Implantation Techniques
A total knee replacement (TKR) can be implanted using either a cementless or cemented technique. However, the vast majority of knee replacement surgeries are performed using the cemented technique. Cemented implantation refers to the use of an additional anchoring material—a synthetic substance called bone cement—which firmly anchors the new joint components within the bone.
Cementless Total Knee Replacement
In a cementless total knee replacement (TKR) procedure, the prosthetic component is secured in the bone using a press fit or form fit. This “locking” of the knee prosthesis provides primary stability. Subsequently, secondary ingrowth of cancellous bone structures is possible. However, immediate weight-bearing on the knee prosthesis is generally still possible.
With this type of fixation, a healthy bone matrix is a prerequisite for good long-term results. Therefore, osteoporosis and bone metabolism disorders of any kind are considered contraindications. This means that in these cases, the artificial prosthesis cannot be implanted cementlessly.
One advantage of the cementless knee prosthesis may be the easier removal of the endoprosthesis, should this be necessary for a prosthesis replacement. Less bone substance is lost during removal.
Nevertheless, changes in load-bearing conditions can lead to the breakdown of bone matrix (lysis). The area of the femur located below the implant is particularly affected by this.
Cemented Total Knee Replacement
Here, a plastic material (polymethyl methacrylate) serves as the interface between the bone matrix and the prosthesis. This implantation technique is widely used. It can also be used in patients for whom a cementless total knee replacement is not possible due to reduced bone quality or density.
After surgery, the total knee replacement can always bear full weight.
Hybrid Knee Replacement
This approach combines the advantages of both implantation techniques. In most cases, the tibial component (shinbone) is cemented, while the femoral component (thighbone) is implanted cement-free.
Full weight-bearing is also possible here after surgery.
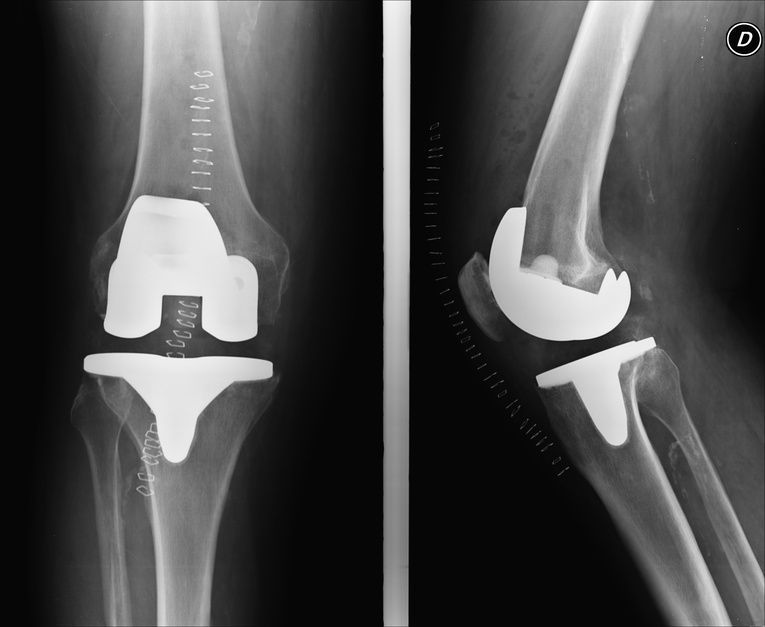
Procedure for Knee Replacement Surgery
There are several standard approaches to accessing the knee joint. During the procedure, the patient lies on their back.
The skin incision is usually made anteromedially (i.e., from the front toward the inner side of the leg) above the kneecap (patella). The knee joint capsule can be opened in various standard ways.
The parapatellar (next to the kneecap) approach provides an excellent surgical view of all three compartments.
A disadvantage of this approach is that the incision disrupts the vastus medialis muscle. The procedure may therefore result in weakening of the muscle.
The so-called midvastus approach offers a view that is nearly as good. However, the incision in the area of the vastus medialis may lead to bleeding and hematomas.
With the subvastus approach, the vastus medialis is not traumatized, or only minimally so. However, this limits the view of the surgical site during the procedure.
Minimally invasive implantation procedures, similar to those used in hip arthroplasty, are also possible for the knee joint. They primarily spare soft tissue structures such as the vastus medialis muscle and the tendon of the quadriceps femoris muscle. These techniques are routinely used, particularly in partial knee replacement.
As a result, they play a crucial role in helping patients regain mobility more quickly after surgery and in preventing muscle weakness.
Prosthesis Replacement and Treatment of Complications Following Total Knee Arthroplasty
About 7 percent of all patients undergo repeat surgery within the first ten years after receiving a knee replacement.
The causes of revision surgery following a total knee replacement are varied. Sometimes infections or malfunctions of the artificial joint become apparent. If the joint surface continues to be painful long-term after the implantation of a knee prosthesis, the causes must be carefully investigated.
A cause cannot always be identified. One such cause is “arthrofibrosis”—a painful thickening and shrinkage of the joint capsule. This is believed to result from excessive scar tissue formation within the joint capsule, leading to permanent functional impairment of the joint. The reasons for this complication remain largely unclear to this day.
Signs of wear on the artificial joint and prosthesis loosening usually do not occur until much later after the initial surgery. They can generally be diagnosed.
Planning a Knee Replacement Revision Surgery
First, a thorough clinical examination is performed. The following are assessed:
- joint function,
- ligament stability,
- muscle function,
- the condition of the scar tissue, and the
- tendency to swell.
X-rays are used to check the fit of the knee joint prosthesis. The position of the prosthesis can also be assessed using specialized imaging.
It is crucial to rule out an infection in the knee. In addition to blood tests, joint aspirations are essential for diagnosis. Sometimes, tissue biopsies are also necessary.
Revision surgery should not be performed until the causes have been clarified. Furthermore, a revision strategy should be established. Here are three typical examples for replacing a knee prosthesis:
- Replacement of the polyethylene liner (the joint’s bearing surface) due to wear and tear or mild instability
- Replacement of the posterior surface of the patella as a second procedure due to persistent anterior knee pain
- Replacement of the artificial joint due to infection or uncontrollable dysfunction/ligament instability, loosening, or malpositioning (single-stage or two-stage)
Prosthesis Models for Knee Revision Surgery
Revision endoprostheses are usually modular in design. They consist of a large number of individual components that can be combined in a wide variety of ways. This allows them to be tailored very well to the patient’s individual situation.
The experience of the clinic and the surgeon is of great importance for a successful revision. Preoperative planning is essential, and potential complications must also be considered.
Specialized orthopedic clinics or joint replacement centers have the necessary experience and the appropriate specialized instruments.
Postoperative Care Following Knee Prosthesis Replacement Surgery
The goal of revision surgery is to enable the patient to quickly resume full weight-bearing and movement of the joint. Only in exceptional cases must the patient adhere to certain restrictions in this regard for a specific period of time.
A personalized pain management plan enables gentle and rapid mobilization.
Close, interdisciplinary collaboration between physical therapists, anesthesiologists, and the surgeon is crucial to the success of the surgery. Overall, a follow-up care plan similar to that used for the initial surgery is followed.
Outcomes of Revision Knee Surgery
Before revision surgery, the specific problem should be discussed in detail with each patient, and the goals and expectations should be aligned. The risk of complications increases with each revision procedure. The decision to perform knee revision surgery should therefore be made with great care.
It is recommended to consult an experienced joint replacement specialist for this purpose.
Follow-up Care and Rehabilitation After Total Knee Replacement: Regaining Mobility
After the implantation of a knee replacement, the important phase of rehabilitation begins. The goal is to strengthen the muscles around the knee joint, prevent misalignment, and ensure long-term mobility. Just a few days after surgery, physical therapists help patients carefully bend and straighten the joint.
It is essential to engage in joint-friendly exercise that protects the joint surfaces and surrounding tissue. This includes special exercises as well as joint-friendly sports such as swimming or cycling.
In addition to inpatient treatment, outpatient therapy is often an option. This helps patients gradually put weight on the knee and regain mobility in daily life. Regular follow-up visits with the surgeon ensure that no infections or loosening of the prosthesis occur and that the implant’s durability is not compromised.

About the medical author
Prof. Dr. med. Karl Philipp Kutzner
Medical Editor · Mainz
Prof. Dr. med. Karl Philipp Kutzner – medical author: expert articles, professional insights and medical knowledge in the Leading Medicine Guide.











































