
Thoracic outlet syndrome is a condition in which nerves or blood vessels are compressed in the area of the upper thoracic aperture. The arm and upper extremity are frequently affected, as the brachial plexus, arteries, and veins run through that area.
Thoracic outlet syndrome, often referred to as TOS, can have various causes, such as bony narrowing, a cervical rib, or muscular changes. Depending on the affected structure, a distinction is made between neurogenic, venous, or arterial thoracic outlet syndrome. Typical symptoms result from pressure on the nerves or impaired blood flow.
Symptoms may worsen with certain arm positions. A thorough diagnosis is crucial for initiating the appropriate treatment for thoracic outlet syndrome.
What is the thoracic outlet?
“Thorax” means “chest,” and “outlet” means “opening.” The term “thoracic outlet” therefore refers to the upper opening of the chest, around which the first rib runs. It originates on the side of the first thoracic vertebra.
Many patients have an additional rib extending from the 7th cervical vertebra. This rib is called the “cervical rib.” It can be stub-like or long and may extend to further encircle the upper thoracic opening.
Nerves, called “nerve roots,” emerge laterally from the bony cervical spine through specific bony openings. The 5th through 8th cervical nerve roots are responsible for the motor and sensory innervation of the arm and hand.
After emerging laterally from the cervical spine, these nerves follow a very complex anatomical path. The nerve structures branch out in a plexus-like pattern, which is why this nerve region is also called the “brachial plexus” (“arm nerve plexus”).
The parts of this plexus that emerge low in the cervical spine are responsible for
- the small muscles in the hand as well as
- sensation, pain, and temperature perception on the little-finger side of the hand.
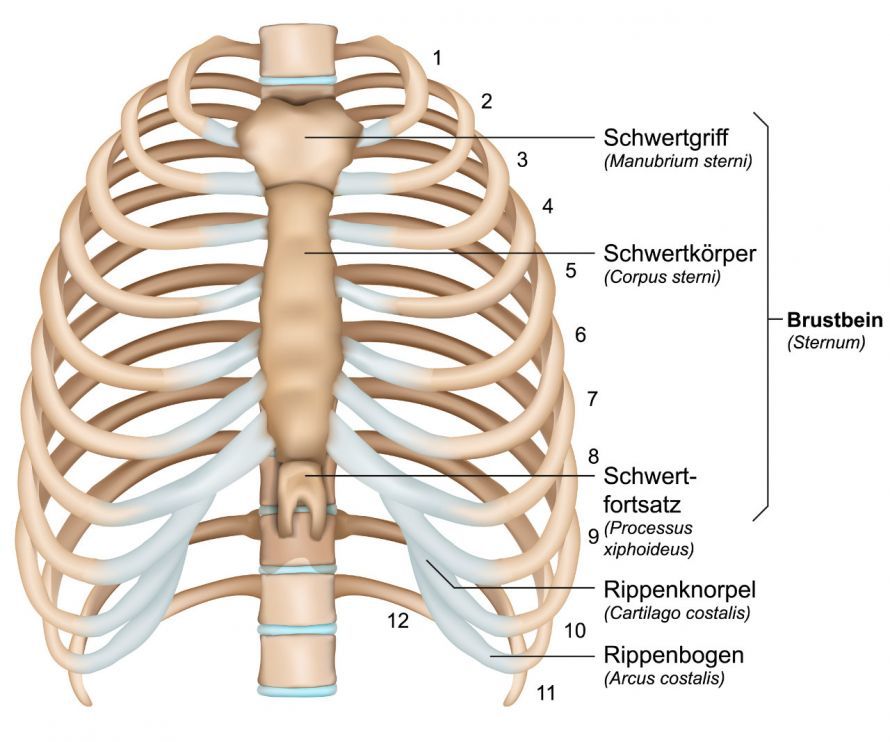
The ribs in the human chest © bilderzwerg | AdobeStock
Causes and Symptoms of Thoracic Outlet Syndrome
It is precisely these nerves that can be irritated by anatomical structures at the thoracic outlet. Although these structures are present from birth, they may eventually prove to be problematic over the course of a person’s life. Why and how this condition develops is not known.
People with a very narrow chest and a long, slender neck are more prone to developing thoracic outlet syndrome. It is believed that the particularly steep trajectory of the nerves in such cases contributes to the condition.
Vascular impairment—either isolated or combined with neurological symptoms—is also possible in thoracic outlet syndrome. Arterial constriction caused by arm positioning can lead to the formation of clots and trigger embolisms in the arteries of the fingers.
In very rare cases, the blood supply to the brain is compromised. This can lead to episodes of dizziness or fainting. Clots in the arm veins are even more dangerous.
The nerve symptoms associated with thoracic outlet syndrome are usually described as an electric-shock-like sensation. They radiate toward the little finger side of the hand and can be extremely unpleasant.
Many patients feel misunderstood by their doctors. Medical professionals often diagnose psychological problems as the cause of the symptoms. This leads to a long and painful ordeal.
There is no drug therapy available. According to affected patients, painkillers of any kind have virtually never been effective.
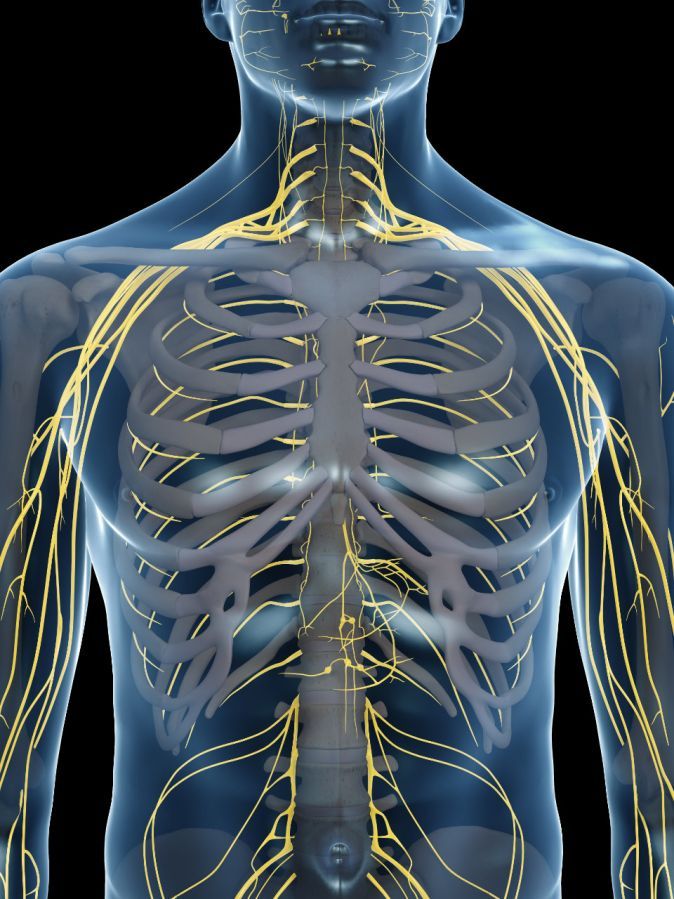
Nerves in the chest area © SciePro | AdobeStock
Treatment of Thoracic Outlet Syndrome
Once the symptoms of thoracic outlet syndrome have appeared, physical therapy is virtually ineffective.
If the symptoms are purely neurological, changing one’s posture may be helpful. This allows the patient to try to reposition the structures located in the upper thoracic outlet so that they are no longer irritated.
However, in cases of recurrent circulatory symptoms, surgery for thoracic outlet syndrome is absolutely necessary.
Examination and Diagnosis of Thoracic Outlet Syndrome
Very few physicians even address the clinical presentation of thoracic outlet syndrome. Opinions vary widely regarding which examination methods provide conclusive evidence for diagnosis. There are no general rules for diagnosing thoracic outlet syndrome that can be found in the literature. Therefore, the consulting physician must rely largely on personal experience. For the patient, however, this is unsatisfactory.
Performing specific provocation maneuvers as part of a clinical examination is almost the most important diagnostic method. In this procedure, the examiner applies pressure with their fingers to the patient’s supraclavicular fossa.
If this triggers the typical symptoms, it is the most compelling indication of thoracic outlet syndrome. Complex electrophysiological examinations performed by a neurologist for thoracic outlet syndrome are very extensive and time-consuming. They therefore serve only a supplementary purpose.
In cases where symptoms are exclusively neurological, magnetic resonance imaging (MRI) serves only to rule out a possible tumor. A herniated disc in the cervical spine may produce symptoms similar to those of thoracic outlet syndrome. This condition must be ruled out during the diagnostic process.
An X-ray is used to determine the presence of a cervical rib. Currently, sonography (ultrasound) is gaining in importance because it can be performed while the arm is in different positions.
However, none of these imaging tests provide conclusive evidence of nerve irritation in the thoracic outlet region.
In cases of vascular symptoms, examinations of the arm’s arteries and veins are absolutely essential: Using magnetic resonance angiography and vascular ultrasound with the arm in various positions, these tests look for narrowings or obstructions to blood flow.
Thoracic Outlet Syndrome Surgery
If physical therapy attempts prove ineffective, treatment of thoracic outlet syndrome can only be performed surgically. In cases of concerning vascular symptoms, surgical treatment is even unavoidable.
Such surgery is preceded by in-depth consultations with the patient. During these consultations, the doctor thoroughly explains to the patient all uncertainties regarding the surgery, as well as the risks of delaying treatment in the presence of vascular symptoms.
Thoracic outlet syndrome is very rare, and the surgery involves various specialists, including
As a result, there are widely differing views on the surgical procedure and the choice of surgical approach.
If the brachial artery and vein are patent, a procedure via the supraclavicular fossa using a relatively small incision has proven effective.
The surgeon must identify all the nerves of the arm, as well as the brachial artery and vein, together. Then he can locate the structure responsible for irritating the lower cervical nerve root. This may be
- tendinous structures pulling vertically downward within the neck extensor muscles,
- a sharp inner edge of the first rib, or
- a possible stub-like cervical rib.
The surgeon decides, based on the individual situation, what needs to be removed or partially removed.
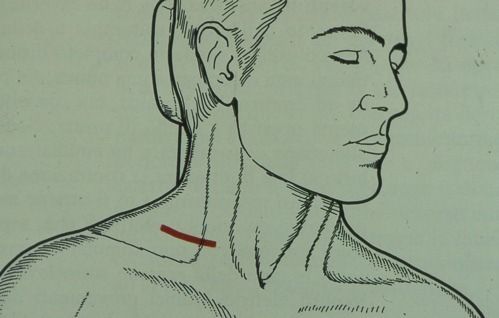
There is no general rule for how thoracic outlet syndrome surgery must be performed. Naturally, requests for a keyhole technique carry far too great a risk of injury.
Healing of the wound site in the supraclavicular fossa should be ensured with a suction drain for 2 to 3 days. The small fat pocket revealed after skin incision contains a network of small lymphatic vessels; if these are torn, fluid may leak from the tissue. Suction drainage
- ensures adequate adhesion of the surgical site and
- prevents an unwanted accumulation of wound fluid.
Therefore, inpatient follow-up should be arranged.
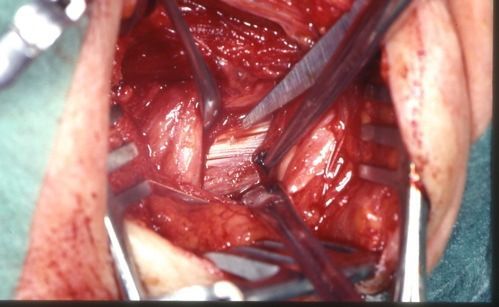
When vascular symptoms are the primary concern, thoracic surgeons choose an axillary approach. They then aim for total removal of the first rib to ensure unobstructed blood flow in the vessels.
Our own experience with the surgical approach above the clavicle has shown that this method also achieves the desired outcome without the need for rib resection. However, opinions on this matter remain divided, and there are valid arguments supporting each viewpoint.
Postoperative Care Following Thoracic Outlet Syndrome Surgery
There is no need for any follow-up treatment after thoracic outlet syndrome surgery. The patient will notice immediately the next day whether the procedure was successful. Physical therapy exercises are not necessary, as there were usually no serious neurological deficits even before the surgery.
Local wound treatments such as massages and similar procedures should be strictly avoided. These could cause new irritation during the scar formation process.
Possible Complications and Risks of Thoracic Outlet Syndrome Surgery
Due to uncertainties in diagnosis and determining the indication for surgery, there is always a risk that the procedure will not be successful. Thoracic outlet syndrome surgery must not cause any additional nerve damage.
No surgeon can guarantee this; nevertheless, the requirements for the surgeon’s diligence and patience are very high. Damage can only be avoided if the surgeon keeps all nerve and vascular structures in view at all times during the surgical procedure.
The literature mentions the risk to the phrenic nerve in cases where the approach is made above the clavicle. This nerve provides unilateral motor innervation to the diaphragm. The procedure extends to the apex of the lung.
Both the lung is surrounded by a membrane (internal pleura) and the inner surface of the chest wall (external pleura). If the outer pleural layer is injured, air can enter the space between the lung and the inner chest wall through the surgical field (“pneumothorax”).
The patient notices this as difficulty breathing, and an X-ray can confirm the diagnosis. A suction drain placed intraoperatively toward the apex of the lung prevents the accumulation of air in the chest cavity.
The axillary approach also carries these potential complications. Additionally, there is a risk of damage to the lower brachial plexus. Ultimately, everything depends on the care taken during the operation.
Findings from Thoracic Outlet Syndrome Surgery
Reliable statistical data on the effectiveness of such thoracic outlet syndrome surgeries are scarce. The few surgeons who deal with these conditions can only draw on their personal experience.
A relationship of trust must develop following extensive discussions between the patient and the physician. This allows both parties to make a judgment call.
Conclusion
Thoracic outlet syndrome is a syndrome caused by irritation of
- nerves (neurogenic TOS) or
- the arm artery and vein (vascular TOS)
above the upper thoracic outlet.
In the former, the nerves supplying the little-finger side of the hand are always affected. In the latter, complex circulatory disorders develop.
The cause is minor anatomical anomalies present from birth. The resulting symptoms can largely be treated only surgically, even though
- diagnosis,
- determining the need for surgery, and
- performing thoracic outlet syndrome surgery
are associated with unavoidable uncertainties.
FAQ
What is thoracic outlet syndrome (TOS)?
Thoracic outlet syndrome is a condition in which nerves or blood vessels are compressed in the area of the upper thoracic aperture. These constrictions often occur between the first rib, the clavicle, and the surrounding muscles. The arm is particularly affected, as it is supplied by blood vessels and nerves in that area.
What are the symptoms of thoracic outlet syndrome?
Typical symptoms include pain, numbness, or weakness in the arm. In neurogenic thoracic outlet syndrome, neurological symptoms caused by compression of the brachial plexus are the primary concern. In vascular forms, swelling, circulatory problems, or discoloration may occur.
How is thoracic outlet syndrome diagnosed?
Diagnosis of thoracic outlet syndrome begins with a clinical examination and medical history. Provocation maneuvers such as the Adson test can provide clues. In addition, imaging techniques such as X-rays, ultrasound, or other imaging methods are used to identify bony or anatomical causes.
What treatment options are available for TOS?
Treatment for thoracic outlet syndrome depends on the cause and severity. Conservative therapy—including physical therapy, posture training, and muscle strengthening—is often recommended initially. The goal is to reduce compression and alleviate symptoms.
When is surgery necessary for thoracic outlet syndrome?
Surgical treatment is indicated when conservative measures are insufficient or when blood vessels are severely compromised. The goal of surgical treatment is to eliminate the narrowings, for example, by removing the first rib or a cervical rib. The decision is made on a case-by-case basis for patients with thoracic outlet syndrome.
Share this article







































