
General Information
Endocrine surgery involves both conventional surgical techniques and minimally invasive procedures. Doctors from various specialties work together in this field. Most often, these are
- endocrine surgeons,
- endocrinologists (internists),
- radiologists, and
- nuclear medicine specialists.
Pathologists are sometimes involved as well. They are consulted for cancer diagnosis—that is, when tissue must be examined for possible malignancy (malignant tumors).
Especially in cases of malignant diseases, follow-up treatment specific to the tumor is usually necessary after endocrine surgery.
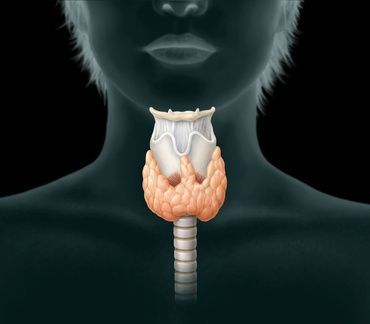
Overview of the Thyroid Gland
In the field of endocrine surgery, thyroid surgeries are primarily performed for
- benign thyroid nodules (nodular goiter, adenomas),
- thyroid tumors (thyroid carcinomas), or
- autoimmune thyroid diseases (Graves’ disease)
.
In Germany, one in two people over the age of 45 suffers from an enlarged thyroid gland (commonly referred to as a goiter) or a nodule. If medication is not sufficient for treatment, endocrine surgery is used.
Surgical options in endocrine surgery include total thyroidectomy and partial thyroidectomy. In addition, it may be necessary to remove lymph nodes as well in cases of thyroid carcinoma.
Overview of the Parathyroid Glands
Endocrine surgery on the parathyroid glands is generally performed for
- very rare parathyroid tumors
- hyperparathyroidism, or
- damage to the parathyroid glands resulting from thyroid surgery
.
Surgeons assess the success of the procedure during the operation itself. To do this, the tissue is examined under a microscope (histological examination). The hormones secreted by the parathyroid gland can also be measured intraoperatively (known as intraoperative parathyroid hormone measurement). Whenever possible, the diseased parathyroid gland is removed through a targeted procedure using open or video-assisted endocrine surgery.
Overview of the Adrenal Glands
Endocrine surgery on the adrenal glands plays a particularly important role in the treatment of adrenal tumors. The adrenal glands consist of the adrenal cortex and the adrenal medulla. Tumors can develop in both of these structures.
One form of this is known as Cushing’s syndrome. In this condition, the hormone cortisol is produced in excess. This leads to
- high blood pressure,
- diabetes,
- muscle weakness, and
- in women, male-pattern hair growth.
Typical features also include the so-called “moon face” and central obesity. This refers to an abnormal distribution of body fat that results in thin arms and legs and an accumulation of fat around the trunk.
If a tumor in the adrenal cortex produces excess aldosterone, this results in Conn’s syndrome. Typical symptoms include high blood pressure combined with a markedly low potassium level in the blood.
The most common tumor of the adrenal medulla is a pheochromocytoma. This condition causes an overproduction of the hormones adrenaline and norepinephrine. These hormones lead to high blood pressure accompanied by
- headaches,
- palpitations or a racing heart, and
- profuse sweating.
Overview of the Pancreas
The best-known function of the endocrine portion of the pancreas is the regulation of blood sugar levels. It secretes the hormones insulin and glucagon.
Tumors that originate in the endocrine parts of the gland can be benign or malignant. A sign of a pancreatic tumor may be a yellowing of the skin (jaundice), which is usually painless. Affected individuals sometimes complain of abdominal or back pain and experience unintentional weight loss within a few months.
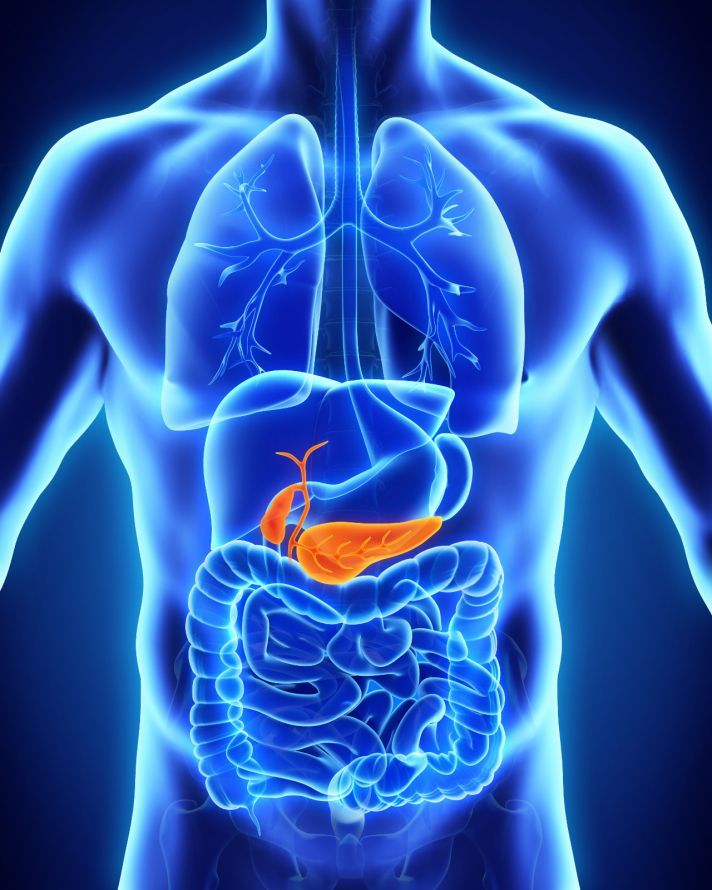
The location of the pancreas (center of the image) © nerthuz | AdobeStock
An ultrasound examination is usually performed prior to endocrine surgery. This allows other conditions that also cause yellowing of the skin or abdominal pain to be identified or ruled out.
Tumors of the pancreas can also be detected using computed tomography (CT) and magnetic resonance imaging (MRI). Sometimes a gastroscopy with intubation and X-ray imaging of the pancreatic duct is necessary. However, distinguishing between a malignant tumor and chronic inflammation of the pancreas is very difficult. Often, this can only be assessed during surgery.
Overview of Neuroendocrine Cells
Among diseases of neuroendocrine cells, neuroendocrine tumors (NETs) play a particularly important role. They occur primarily in the gastrointestinal tract. Based on their ability to secrete hormones, they can be classified as functional or non-functional tumors.
They require an endocrine surgical approach tailored to the site of origin and the type of hormone production. In addition to the primary tumor, neuroendocrine tumors can metastasize to other organs. These metastases must then also be treated.
Endocrine Surgery: Thyroid Surgery
Endocrine surgery can be used to remove tumors and nodular changes in the thyroid gland and to treat hyperthyroidism.
Thyroid surgery has now become a routine procedure within the field of endocrine surgery. In Germany, approximately 80,000 to 100,000 thyroid surgeries are performed each year.
Reasons for Thyroid Surgery
Thyroid surgery is particularly indicated when an enlarged thyroid gland is compressing other organs. For example, compression of the trachea or esophagus can lead to difficulty swallowing or breathing, or a feeling of pressure in the throat.
Other reasons for endocrine surgery include:
- Suspected or confirmed malignant disease
- Cold nodules that are bothersome due to their size, are growing rapidly, or suggest malignancy
- Hot nodules that cause hyperthyroidism and cannot be adequately treated with medication or radioiodine therapy
- Graves’ disease, provided that radioiodine therapy is not appropriate or is not desired
Preoperative evaluations for thyroid surgery
Specifically, the endocrine surgeon will perform various tests:
- A blood test to determine the levels of thyroid hormones in the blood over the past few weeks,
- a recent ultrasound examination of the thyroid gland to assess its location, size, and tissue pattern,
- a thyroid scintigraphy, which provides information on thyroid function (including any possible thyroid nodules), and
- a general laboratory workup, as well as
- an electrocardiogram (ECG).
In some cases, an ear, nose, and throat (ENT) specialist may be consulted prior to endocrine surgery to assess the function of the vocal cords. This decision is made on a case-by-case basis.
Procedure for Thyroid Surgery
Most thyroid surgeries are performed under general anesthesia and last about one to two hours. Thyroid hormone levels, which are measured via a blood test, should be within the normal range at the time of endocrine surgery. This means that any existing dysfunction (especially hyperthyroidism) should be treated with medication prior to endocrine surgery.
Thyroid surgery is performed through a small incision (4–5 cm) below the neck (known as a “collar incision”). The endocrine surgeon exposes the thyroid gland and removes diseased tissue.
The amount of tissue removed depends on
- whether it is a single nodule or
- how large a potentially malignant tumor is.
Occasionally, an entire thyroid lobe or the entire thyroid gland must be removed. In cases of thyroid cancer, the entire thyroid gland, including the surrounding lymph nodes, is usually removed. If it is unclear whether the tumor is malignant, the removed tissue is examined during the thyroid surgery (frozen section analysis).
Before the wound is closed, a small drainage tube is inserted to allow blood and secretions to drain. The wound is usually closed with dissolvable sutures.
Postoperative Care Following Thyroid Surgery
The hospital stay for thyroid surgery is usually two to three days. Patients can get out of bed and are allowed to eat and drink as early as the day after surgery.
The wound drains are removed on the first or second day. The skin sutures are removed on the fifth to seventh day, unless dissolvable sutures were used. In most cases, an ear, nose, and throat (ENT) specialist also checks vocal cord function.
About seven days after discharge from the hospital, patients can usually resume all their normal activities.
Four to six weeks after the surgery, metabolic status is monitored via a blood test. A decision is then made as to whether and in what dosage thyroid hormones should be administered.
Endocrine Surgery: Parathyroid Surgery
Management of Parathyroid Injuries Resulting from a Previous Thyroid Surgery
In rare cases, the parathyroid glands may be injured or inadvertently removed during thyroid surgery. They can then be reimplanted in another location (forearm, neck muscles). They usually resume function after a few days.
However, reimplanting the parathyroid glands in a different location is not always possible. In such cases, the resulting calcium deficiency can be treated with a daily calcium supplement. Vitamin D may also be prescribed as needed.
Endocrine Surgery for Primary Hyperparathyroidism
Primary hyperparathyroidism is also known as parathyroid adenoma or parathyroid hyperplasia. It is treated by surgically removing the enlarged parathyroid gland through endocrine surgery.
The endocrine procedure should be performed once the condition has been confirmed by elevated calcium levels or elevated parathyroid hormone levels.
Occasionally, the location of the enlarged parathyroid gland cannot be precisely identified prior to surgery. There may also be suspicion that more than one parathyroid gland is affected. In both cases, all potential sites must be surgically exposed.
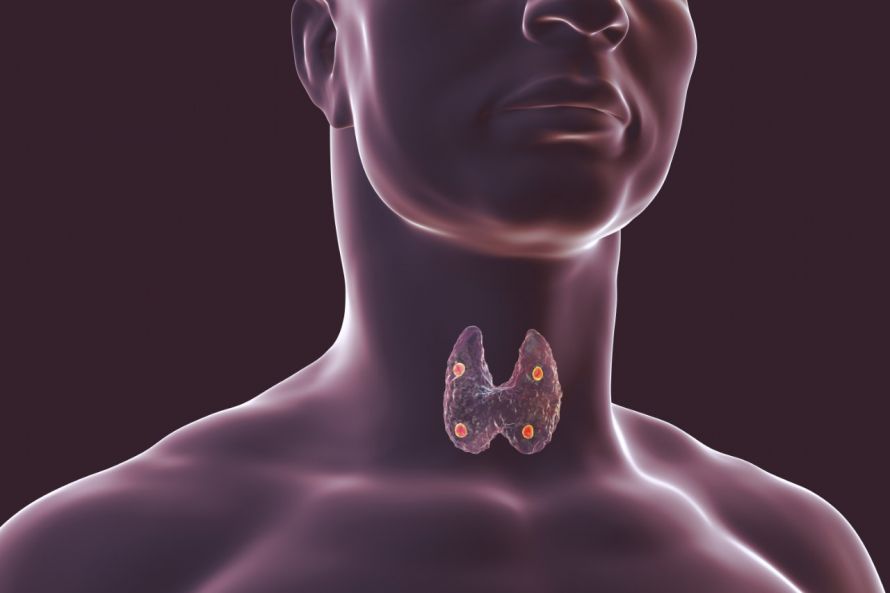
The removed tissue is examined histologically during the operation (frozen section analysis). This verifies whether the parathyroid adenoma has been successfully removed and rules out any potential malignancy.
If all four parathyroid glands are pathologically enlarged, three and a half parathyroid glands are removed, and one-half of a well-perfused parathyroid gland is left in place. This is common in cases of familial primary hyperparathyroidism.
Alternatively, all four enlarged parathyroid glands can be removed, and small particles of parathyroid tissue can be reimplanted.
Endocrine Surgery for Parathyroid Carcinoma
The malignant transformation of a parathyroid adenoma is usually first detected during histological examination of the parathyroid tissue. In endocrine surgery, an adenoma is considered suspicious if it is difficult to dissect from its surrounding tissue during surgery.
Extensive surgery must be performed when there is strong suspicion of—or confirmation of—a malignant tumor. This means that even the smallest tumor remnants must be removed to prevent the tumor from recurring.
The thyroid gland on the same side is completely removed. This also includes the lymphatic tissue along the blood vessel sheaths as well as the lymph nodes affected by tumor tissue.
Follow-up Care After Parathyroid Surgery
After the removal of overactive parathyroid gland(s), the bones are accustomed to high calcium levels in the blood. Following the procedure, there may be a temporary drop in calcium levels below the normal range.
This can be treated by regularly taking calcium effervescent tablets, possibly in combination with vitamin D. However, the achieved calcium level should not exceed the lower limit of the normal range. This allows the parathyroid glands to resume their function and also helps prevent the formation of calcium-containing kidney stones or renal calcification.
Endocrine Surgery: Adrenal Gland Surgery
Surgery for Adrenal Cortex Tumors
For adrenal cortical tumors that cause Cushing’s syndrome or Conn’s syndrome, treatment involves the surgical removal of the tumor or the entire adrenal gland (known as an adrenalectomy).
In the majority of cases, this procedure is performed using the keyhole technique (minimally invasive laparoscopic technique). Adrenocortical carcinoma, a malignant tumor of the adrenal cortex, must also be removed via endocrine surgery. In addition, medication and chemotherapy are required.
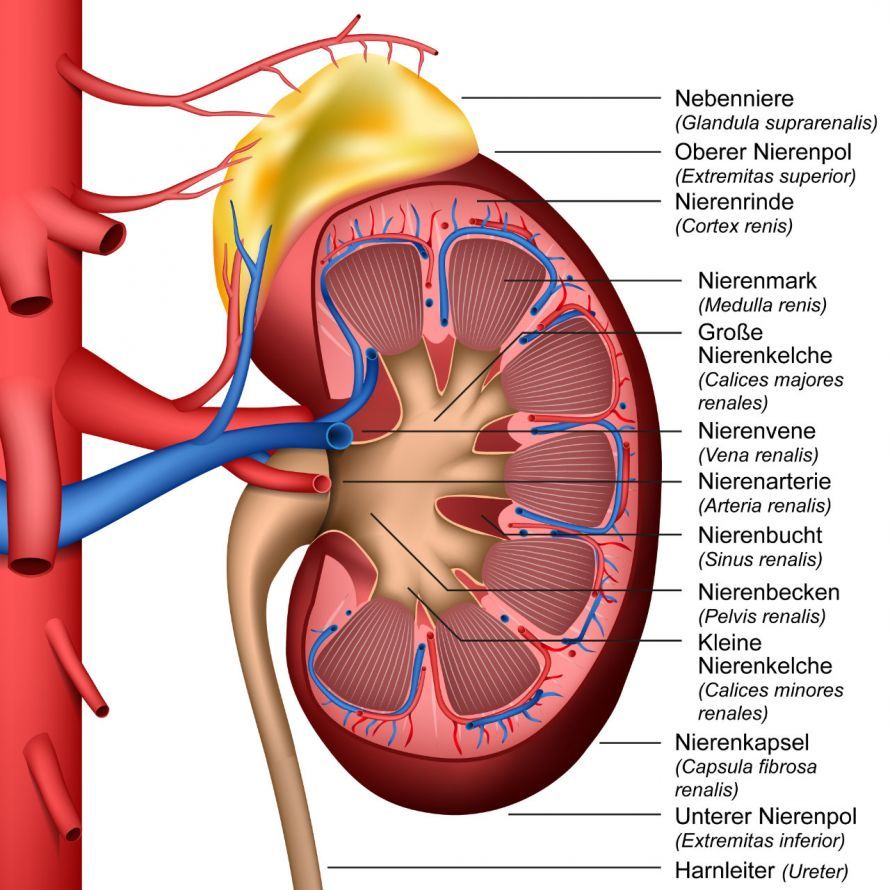
The standard procedure for adrenal tumors that are smaller than 6 cm and show no signs of malignancy is laparoscopic adrenalectomy, or the laparoscopic removal of the affected portion of the adrenal gland.
To perform this procedure, instruments are inserted through three incisions, each approximately 2–3 cm in size, in the right or left flank.
Surgery for Adrenal Tumors
Pheochromocytoma is also treated using endocrine surgery. For tumors up to approximately 6 cm in size, this procedure can be performed using a keyhole technique.
Larger tumors carry a certain risk of malignancy. Therefore, in these cases, conventional surgery via a flank or abdominal incision should be performed to ensure that no tumor tissue is left behind.
Before surgery for a pheochromocytoma, patients are treated with a special medication. It counteracts the effects of epinephrine and norepinephrine on the blood vessels, thereby helping to prevent complications during surgery.
Regular follow-up examinations are necessary for pheochromocytomas and malignant adrenal tumors.
Endocrine Surgery: Pancreatic Surgeries
Procedure for Pancreatic Surgery
Before surgery, efforts should be made to significantly improve any pre-existing conditions affecting other organs. Pancreatic activity is reduced with medication prior to surgery.
On the day before surgery, the bowel is completely emptied. To avoid major, stressful surgeries, a so-called diagnostic laparoscopy is performed at the beginning of the procedure in most cases. During this procedure, the pancreas is examined using a special ultrasound device.
If complete removal of the tumor appears feasible at this stage, the surgery continues via a standard abdominal incision; otherwise, it is terminated.
In principle, for many pancreatic tumors, a chance of cure exists only if the entire tumor can be removed. To achieve this, adjacent organs—such as the duodenum or the bile duct—often must also be removed.
Risks, Complications, and Postoperative Care Following Pancreatic Surgery
Pancreatic surgery carries the general risks and complications associated with all surgical procedures. In addition, care must be taken after pancreatic surgery to monitor for inflammation of the remaining pancreatic tissue.
The histological examination of the pancreatic tissue removed during surgery takes about one week. Based on these results, it is determined whether further medical treatment of the disease is necessary to increase the chances of a permanent cure.
Endocrine Surgery: Surgery for Neuroendocrine Tumors
Endocrine surgery is the primary treatment for gastrointestinal neuroendocrine tumors.
Even very large or metastatic tumors are surgically removed to
- reduce the tumor burden (debulking) and
- prevent complications that may be caused by the primary tumor invading surrounding tissues (e.g., bowel obstruction or bleeding).
This depends on the tumor’s location and stage. In addition, it is possible to alleviate symptoms resulting from the tumor’s hormone production with medication. A combination of chemotherapy drugs is also used. Radiation therapy for neuroendocrine tumors, however, is not a treatment option.
FAQ
What is endocrine surgery?
Endocrine surgery is a subspecialty of visceral surgery that focuses on the surgical treatment of diseases of the endocrine organs. These include, in particular, the thyroid, parathyroid, and adrenal glands, as well as the pancreas in certain cases. Endocrine surgeons treat both benign and malignant conditions.
What conditions are treated in endocrine surgery?
The most common disorders of the thyroid gland include thyroid nodules, thyroid cancer, and hormonal dysfunction. In addition, disorders of the parathyroid glands, hormone-producing adrenal glands, and neuroendocrine tumors are treated. Benign or malignant changes in the endocrine organs may also require surgical treatment.
When is thyroid surgery necessary?
Thyroid surgery is recommended when thyroid nodules cause symptoms, a tumor is suspected, or malignant conditions are present. Prior to the procedure, diagnostic tests, an ultrasound, and often an interdisciplinary evaluation by endocrinologists, nuclear medicine specialists, and a radiologist are performed. The decision to proceed with surgery is made on a case-by-case basis.
What role do specialists in endocrine surgery play?
Specialists in endocrine surgery have specific expertise in procedures involving the thyroid, parathyroid glands, and adrenal glands. Risks can be reduced through modern surgical techniques, intraoperative monitoring of the recurrent laryngeal nerve, and neuromonitoring. Treatment at an endocrine center is particularly advisable for complex or malignant conditions.
What does follow-up care involve after surgery?
After surgery, structured follow-up care is provided by the endocrine surgery department. During this process, hormone levels are checked and the function of the remaining gland is monitored. Outpatient clinic visits also serve to provide long-term care for patients. If necessary, further treatment is provided through an interdisciplinary approach involving endocrinology, the Department of Nuclear Medicine, and other specialists.

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
More about the medical author →

























