
Kyphoplasty is a minimally invasive procedure used to treat painful vertebral fractures, particularly those associated with osteoporosis. The goal of kyphoplasty is to stabilize fractured vertebrae, relieve pain, and quickly improve patients’ mobility.
Unlike vertebroplasty, kyphoplasty involves inserting a balloon into the vertebral body to first straighten it and create a cavity. Bone cement is then injected into the vertebral body to achieve permanent stabilization. The procedure is typically minimally invasive and can often be performed in a short amount of time.
What is kyphoplasty?
If a compression fracture occurs in the spine that causes severe pain, kyphoplasty may be a suitable treatment option.
This is a minimally invasive procedure for pain management. During the procedure, doctors inject bone cement into the fractured vertebral body.
What is a compression fracture?
The spine primarily serves to support the body, but it also plays a role in movement. As a result, the individual segments of the spine are constantly under stress. In older age, changes due to wear and tear often occur.
In some cases, constant stress on the spine can also lead to such changes at an early age. Additionally, there is often a reduction in bone mass (known as osteoporosis). As a result, fractures in the vertebral body can occur even with minor stress or accidents.
These fractures typically occur in the lumbar and thoracic spine. This results in compression of the vertebral body and a loss of vertebral height. This loss of height, also known as compression, gives rise to the term “compression fracture.”
The loss of height is usually more pronounced in the anterior portion of the vertebral body, resulting in a wedge-shaped vertebra.
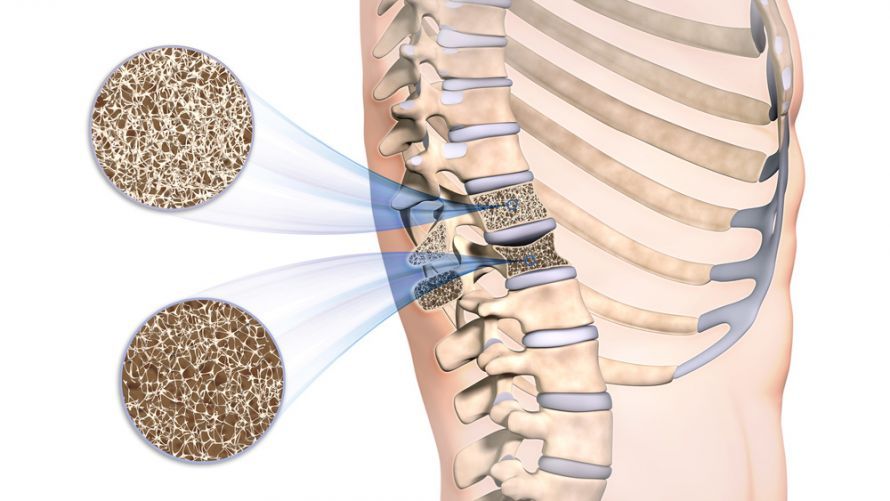
If the bone tissue in the vertebral body is unstable due to osteoporosis, even harmless everyday situations can lead to a vertebral body fracture @ Sagittaria /AdobeStock
Symptoms of a compression fracture
Symptoms occur suddenly following a minor movement, straining, or a fall. They are described as severe back pain, sometimes radiating to adjacent areas of the body. In some cases, the symptoms are so unbearable that they result in immobility.
If a portion of the bone shifts toward the nerve structures, it can lead to paralysis and sensory disturbances. In these cases, immediate medical attention is required.
Treatment Options for a Compression Fracture
Treatment begins with the diagnosis of the vertebral fracture. To do this, the doctor first performs an X-ray examination. If further differentiation is necessary, a CT scan and/or MRI is then performed.
Treatment initially focuses on managing acute pain. A brace (corset) is used to immobilize the fractured vertebra.
If there is no improvement in symptoms despite these measures, you should consider kyphoplasty.
 An anatomically shaped back brace makes it easier to maintain an upright posture @ chayantorn /AdobeStock
Surgical treatment via kyphoplasty should be performed in the following cases:
- If there is a risk of further vertebral collapse with damage to nerve structures
- When pain cannot be controlled with medication
Which specialists perform kyphoplasty?
Spinal surgery is part of the field of orthopedics and trauma surgery. Specialists in orthopedics and trauma surgery focus on the diagnosis and treatment of specific spinal conditions.
In specialized spinal centers, physicians from various disciplines work together in an interdisciplinary manner to provide the best possible care for patients with spinal conditions. Neurosurgeons and radiologists are also involved.
The Kyphoplasty Procedure
Kyphoplasty is typically performed under general anesthesia with the patient lying on their stomach. The procedure takes about 30 minutes. Under X-ray guidance, doctors insert two needles into the fractured vertebral body. They then create a cavity using a small, fluid-filled balloon.
They then inject bone cement through the needles. This is a fast-setting, viscous plastic that mechanically resembles healthy bone. By the end of the kyphoplasty procedure, this cement has completely hardened and can bear weight.
The patient is usually mobilized on the same day as the surgery. Bed rest is not required after a kyphoplasty.
Follow-up Care After Kyphoplasty
After being discharged from the hospital, the patient can resume their daily activities. If there is an underlying condition, such as osteoporosis, treatment is long-term.
The 10 Back Care Rules:
- Stay active!
- Keep your back straight!
- Squat down when bending over!
- If possible, avoid lifting heavy objects!
- Distribute the weight and carry loads close to your body!
- Don’t stand with your knees locked!
- When lying down, bend your knees!
- When sitting, keep your knees lower than your hips!
- Exercise your back muscles daily!
- Exercise regularly! If possible: backstroke, cycling, running on soft ground
Possible Complications of Kyphoplasty
Despite the utmost care, complications can occur during and after kyphoplasty. During the procedure, cement may leak from the vertebral body. Since the procedure is performed under X-ray guidance, any leakage can be detected immediately.
In the past, there were several instances of cement leakage into blood vessels. For this reason, the composition of the bone cement was modified. This type of complication is now very rare in kyphoplasty.
Furthermore, nerve injuries can occur during the puncture of the vertebral body as part of a kyphoplasty procedure. This complication is also very rare.
Conclusion
Kyphoplasty is considered a modern, minimally invasive procedure for treating vertebral fractures associated with osteoporotic conditions and is frequently discussed in the context of vertebroplasty. In cases of osteoporotic vertebral compression fractures, two cannulas are specifically used to insert a balloon into the fractured vertebra, inflate it, and then inject bone cement to restore stability to the vertebral body.
The goal of kyphoplasty is to realign fractured vertebral bodies, relieve severe pain, and improve the structural integrity of the spine in the long term; the choice between kyphoplasty and vertebroplasty depends on the specific findings. Compared to vertebroplasty, “balloon kyphoplasty” often offers an advantage in terms of realignment, which is particularly relevant in the treatment of vertebral fractures and other spinal fractures.
Kyphoplasty is typically performed with the patient in the prone position under local anesthesia and, depending on the technique used, is considered a safe procedure for treating patients with osteoporotic vertebral fractures. Bed rest is generally not required; however, short-term use of a back brace is recommended to support rehabilitation and stabilize the vertebral bodies. Overall, it is evident that vertebroplasty and kyphoplasty—as minimally invasive therapeutic procedures—are effective in relieving pain, maintaining spinal stability, and restoring mobility to patients with osteoporotic vertebral bodies.
FAQ
What is the difference between kyphoplasty and vertebroplasty?
In kyphoplasty, a balloon is inflated before bone cement is injected to straighten the vertebral body. Vertebroplasty omits this step and stabilizes the vertebral body directly with cement.
For which patients is kyphoplasty suitable?
Kyphoplasty is primarily suitable for patients with osteoporotic vertebral fractures and severe back pain. The indication is determined through clinical and imaging evaluations.
How is the procedure performed?
Kyphoplasty is a minimally invasive procedure and is usually performed with the patient lying on their stomach under general or local anesthesia. The balloon is inserted through cannulas, inflated, and then bone cement is injected.
What are the benefits of kyphoplasty?
Kyphoplasty can realign vertebral bodies, improve spinal stability, and significantly relieve pain. Patients often experience improved mobility shortly after the procedure.
Are there any risks or complications?
As with any surgical procedure, complications can occur, such as cement leakage or infections. Overall, however, kyphoplasty is considered a safe and well-established procedure.

About the medical author
Dr. med. Erik Fritzsche
Medical writer





































