
An acoustic neuroma is a benign tumor in the inner ear. This type of tumor is rare. It is located in the temporal bone within the inner ear and originates from the vestibular nerve. Acoustic neuromas grow very slowly and usually occur on only one side.
Here you will find all the important information as well as a selection of acoustic neuroma specialists.
What is an acoustic neuroma?
Acoustic neuromas are located at the point where the vestibular nerve enters the cranial cavity in the internal auditory canal. The cerebellopontine angle is affected later on, and only once the tumor has grown larger. The cerebellopontine angle is the niche between the cerebellum and the brainstem.
People between the ages of 30 and 50 have an increased risk of developing an acoustic neuroma. However, this brain tumor most commonly occurs in patients between the ages of 50 and 60.
How does an acoustic neuroma develop?
This benign brain tumor develops from Schwann cells. In the brain, this type of cell insulates the cranial nerves from the outside environment. In doing so, the cells accelerate the transmission of information between nerve cells.
In patients with an acoustic neuroma, Schwann cells grow rapidly and uncontrollably. In the process, they encase themselves in a capsule of connective tissue, thereby separating themselves from the surrounding tissues.
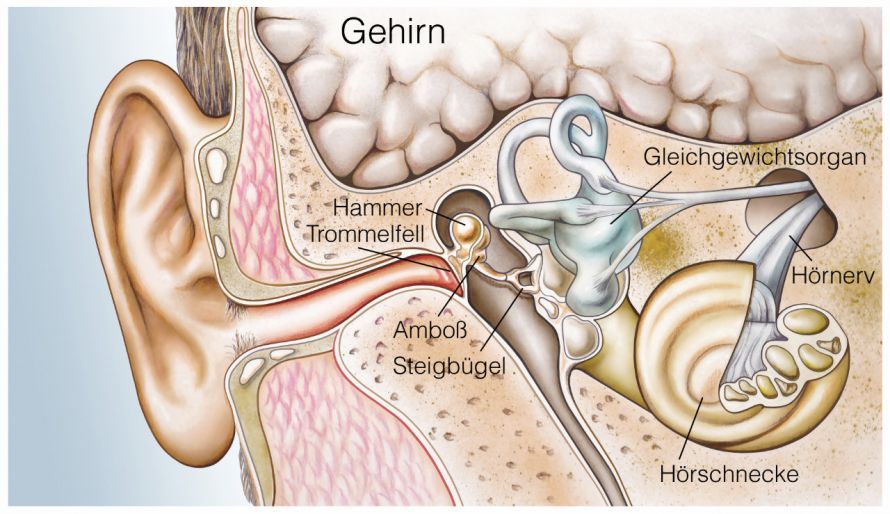
The neuroma originates from the vestibular nerve (nervus vestibularis). Therefore, it is more correctly referred to as a vestibular schwannoma. This vestibular nerve transmits information from the vestibular system in the inner ear to the brain. The exact cause of the tissue overgrowth remains unclear.
The auditory nerve runs in close proximity to the vestibular nerve. It is very often damaged as well, resulting in a sudden loss of hearing. Hearing loss is usually the first symptom of an acoustic neuroma.
The loss of the sense of balance occurs very slowly and therefore usually goes unnoticed. For this reason, the tumor was formerly referred to as an acoustic neuroma based on its association with the auditory nerve (nervus acusticus).
In rare cases, this excessive tissue growth is a symptom of hereditary type 2 neurofibromatosis. In such cases, it can even occur on both sides. Neurofibromatosis is a condition in which benign tumors
- on the skin’s surface,
- in the brain, and
- in the nerve fibers
.
What are the symptoms of this tissue overgrowth?
Acoustic neuroma usually manifests as sudden hearing loss. Since the tumor grows slowly, other symptoms typically do not appear until several months later. Some of the symptoms occur only on the side of the body where the tumor is located.
This benign tumor can be identified by the following symptoms:
- Sensorineural hearing loss
- Sudden hearing loss
- Tinnitus
- Vertigo
- Nausea and vomiting
- Headaches
- Facial nerve paralysis (nervus facialis)
- Sensory disturbances in the face
- Stiff neck
- Impaired vision (double vision)
Initially, hearing and the sense of balance are affected. Patients notice that their hearing is impaired in one ear. A hearing test reveals the hearing loss as sensorineural hearing loss (inner ear hearing loss). This primarily affects high frequencies above 1,000 hertz. High-pitched sounds are no longer audible at all or are perceived differently.
In addition, an acoustic neuroma can cause sudden hearing loss: The patient suddenly hears nothing at all or very little in one ear. Tinnitus may also occur. These ringing sounds consist of high-pitched tones (ringing, hissing) and are very distressing. The external auditory canal feels numb because its sensitivity is reduced.
If the vestibular nerve is also affected, the patient feels nauseous. This leads to episodes of dizziness. The patient suddenly begins to sway (swaying vertigo). Less commonly, there is a sensation that everything is spinning around them (rotatory vertigo). Their gait becomes unsteady.
Their eyes move—as is typical with vertigo—quickly in one direction and slowly back (nystagmus). This usually occurs when the acoustic neuroma patient makes a rapid head movement or when it is dark and rapid eye fixation is therefore absent.
Larger acoustic neuromas also affect the facial nerve, since it also runs through the internal auditory canal. The patient’s facial expressions are restricted on one side. If the neurinoma presses on the trigeminal nerve, sensation in the facial skin is also reduced (numbness).
In the worst-case scenario, the tumor prevents cerebrospinal fluid (CSF) from draining adequately through the brainstem. The accumulated fluid and the resulting increased intracranial pressure often cause nausea and vomiting.
The patient complains of headaches and feels as though they can no longer move their neck properly (stiff neck). In addition, their vision is affected: for example, they may see double.
Anyone who notices these symptoms should consult a specialist (an ENT doctor or neurologist) as soon as possible.
Diagnosis of an acoustic neuroma
The ear, nose, and throat (ENT) specialist examines the patient’s external auditory canal and eardrum. If the patient has only nonspecific symptoms such as dizziness and headaches, further tests are conducted. These are used to differentiate the condition from other diseases with similar symptoms through differential diagnosis.
Acoustic neuroma is diagnosed using
- a hearing test (tone, speech, and brainstem audiometry)
- a balance test, and
- magnetic resonance imaging (MRI; with contrast agent)
If a diagnosis is suspected, the patient listens to specific words and tones through headphones at the ENT doctor’s office and must repeat them.
Brainstem audiometry (BERA) is used to assess the function of the auditory nerves. The patient hears clicking sounds. An electrode placed behind the ear records the extent to which the ear transmits acoustic stimuli to the brain without obstruction.
A balance test using hot and cold water is also part of the diagnosis. The doctor irrigates the external auditory canal with warm water and measures eye movements (nystagmus). If the reactions are not symmetrical on both sides, this indicates hypofunction of a vestibular organ.
Magnetic resonance imaging (MRI) provides definitive confirmation if it detects contrast enhancement in the inner ear canal in the area of the vestibular nerve.
Treatment of Acoustic Neuroma
Smaller tumors, no larger than 3 centimeters, are surgically removed via the middle cranial fossa (by an ENT specialist). Larger tumors, on the other hand, are approached from the back (suboccipital approach by a neurosurgeon).
Due to the tumor’s location, surgeons must proceed with great care. It is essential to avoid damage to
- nerves,
- blood vessels, and
- intact tissue
. It is essential to preserve the facial nerve and, in a high percentage of cases, the auditory nerve as well. Once completely removed, the neurinoma usually does not recur.
Smaller growths are treated with radiation therapy. Other physicians, on the other hand, regularly monitor tumor growth using magnetic resonance imaging (MRI).
In some cases, it is sufficient to adopt a “wait-and-see” approach and monitor the tumor regularly. This is the method of choice when
- the patient has no symptoms at all,
- the tumor is not growing any further, or
- the tumor is shrinking (which is often the case in older people).
For inoperable tumors, the schwannoma is destroyed or its growth is inhibited using radiation therapy. In this method, the tumor is irradiated with a high dose of radiation.
Share this article

About the medical author
Sabine Schneider
Editor-in-Chief
Sabine Schneider – medical author: Explore expert articles and medical expertise in the Leading Medicine Guide.
View full expert profile →

















