
Nerve tumors are predominantly benign. They grow very slowly. Doctors usually detect them late, when the first symptoms of pain and impairments in motor and sensory functions appear. Surgical removal of the nerve tumor is performed using a surgical microscope.
The procedure requires a great deal of time and care to prevent or minimize potential damage to the affected nerve fibers. If functional impairments occur in the affected limbs following nerve tumor surgery, physical therapy and rehabilitation can help.
Here you will find further information as well as a selection of nerve cancer specialists and centers.
What are nerve fibers?
Tumors of the peripheral nerves in a limb are predominantly benign. Nevertheless, such nerve tumors pose a challenge for the surgeon.
The nerve cells of the spinal cord, through intense activity, form cylindrical nerve extensions up to 2 meters long. Thousands of these are then found in specific clusters within the peripheral nerves of the arm or leg.
These nerve extensions, or nerve fibers, conduct the electrically generated impulses that we need for the proper functioning of our arms and legs.
There are two distinct types of nerve fiber functions:
- Nerve fibers along which electrical impulses travel to the spinal cord and brain. They transmit sensory functions such as sensation, pain, and temperature perception.
- Nerve fibers through which electrical impulses travel from the spinal cord to the periphery, for example, to a muscle. These fibers control motor functions.
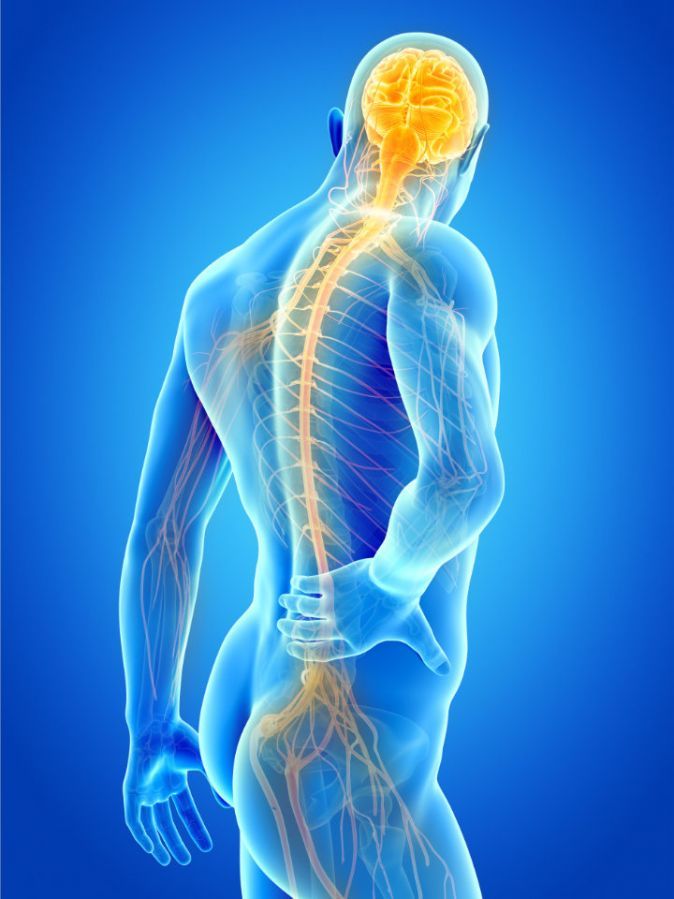
The Nervous System © SciePro | AdobeStock
What types of nerve tumors are there?
Each of the thousands of nerve fibers is surrounded by a layer of cells that acts as insulation.
This is comparable to the rubber coating around a copper wire. The cells that form this fatty insulating layer are called “Schwann cells.”
Unfortunately, however, they can also develop into benign nerve tumors when they multiply abnormally. Such tumors are then called nerve sheath tumors.
These include, for example:
- Schwannoma
- the neurinoma, and
- neurofibroma
The causes of their development are unknown. Nerve sheath tumors grow slowly and are often not detected until years later, when they begin to cause symptoms.
Individual patients with Recklinghausen neurofibromatosis are prone to a marked increase in the number of nerve tumors. This is caused by genetic mutations.
The second most common type of nerve tumor that can form within a peripheral nerve is benign. These so-called cysts are filled with a viscous, transparent substance. Histologically, they resemble cysts in tendon sheaths, formerly known as “ganglions.”
Cysts can lie on the outside of a nerve, but they can also form inside the nerve. Inside the nerve, they can even occur in multiple, long-extending clusters.
There is always a tiny connection between an adjacent joint and such cysts. This connection follows the course of the nerve branch supplying the respective joint.
As a result, the cystic mass on or within the nerve represents an external manifestation of the interior of the joint.
There are histological similarities between:
- the mucous membrane of the joint cavity
- the mucous membrane of the tendon sheaths, and
- the membrane of extra- or intraneural cysts
Simply put, nothing more is known.
Very rarely, other nerve tumors originate from blood vessels within a nerve.
These include:
- cavernomas
- Hemangiomas and
- Hemangioblastomas
These nerve tumors are so rare that we will not discuss them further here.
How and when do doctors detect a nerve tumor?
Each major nerve in the arm or leg has motor functions that affect a group of muscles associated with that specific nerve.
In addition, there are sensory functions in which very specific areas of skin are associated with the following regions:
- Sense of touch
- Pain sensation
- Temperature sensation, etc.
Nerve tumors, which are predominantly benign, grow very slowly. The impairment of the functions described above develops just as slowly.
This is why it often takes many years before a nerve impairment is even suspected. It takes even longer for doctors to actually detect a nerve tumor.
Symptoms of a nerve tumor
For the person affected, the primary symptom over a long period of time is usually pain, which they only perceive under certain circumstances—for example, when an external force strikes the arm or leg where the tumor is growing.
The pain is comparable to the well-known phenomenon of “musician’s bone.” This is a specific type of pain that occurs when one bumps the elbow area; it radiates like an electric shock into the little finger.
The origin and cause of this pain, which can be triggered by mechanical irritation, cannot be precisely determined.
Motor or sensory deficits do not occur until very late in the course of a nerve tumor.
Examination and Diagnosis of a Nerve Tumor
The diagnosis of “nerve tumor” is not immediately obvious to many doctors when examining a patient. Without this suspicion, no targeted examinations can be performed.
However, if nerve cancer is suspected, imaging techniques help establish the definitive diagnosis.
These include:
- ultrasound (sonography) and
- magnetic resonance imaging (MRI)
In contrast, instrumental examinations play a minor role in establishing the diagnosis.
These include:
- measurements of nerve conduction velocity and
- recording of electrical potentials from specific muscle groups that may be affected
It is crucial to believe the patient’s description of the pain. Depending on the area of radiation, mechanically produced pain can be attributed to a specific main nerve. Doctors can verify this using imaging techniques.
Surgery on a nerve tumor using a surgical microscope
The surgical treatment of a nerve tumor poses a major challenge for the surgeon.
The goal of the surgery is to preserve as many functional nerve fibers in the affected group as possible. When removing the nerve tumor, the surgeon should damage as few nerve fibers as possible.
This is possible with a surgical microscope. Microinstruments and microscopic magnification of the surgical field are standard for such procedures.
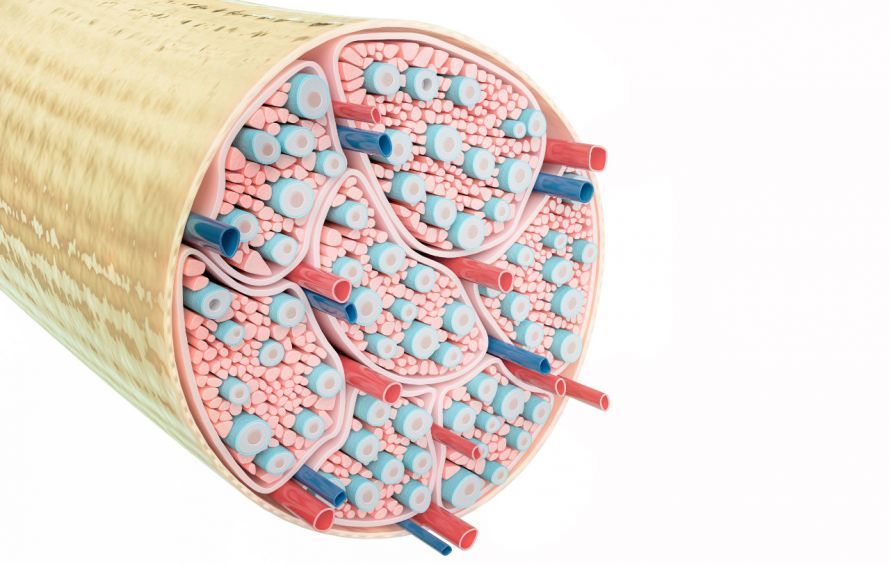
Each peripheral nerve is surrounded by an outer connective tissue sheath (epineurium). Inside, the nerve fibers are grouped into individual smaller bundles by thin connective tissue sheaths (perineurium). Between the fiber bundles is loose connective tissue containing small blood vessels.
Using small instruments and the surgical microscope, surgeons can penetrate between these subgroups of nerve fibers without disrupting the continuity of the nerve fibers.
When performing surgery on a nerve tumor, it is important to be aware of this possibility. This allows doctors to locate the fan-shaped nerve fibers on the nerve tumor. They use microsurgery to detach these fibers from the nerve tumor while preserving their anatomical and functional integrity.
A schwannoma (neurinoma) originates only from the Schwann cells of a small group of nerve fibers. The surgeon identifies these using microsurgery and completely severs them both above and below the nerve tumor. This ensures the complete removal of the nerve tumor.
In the case of a neurofibroma (which differs only slightly from a schwannoma at the histological level), the group of nerve fibers that must be sacrificed is somewhat larger.
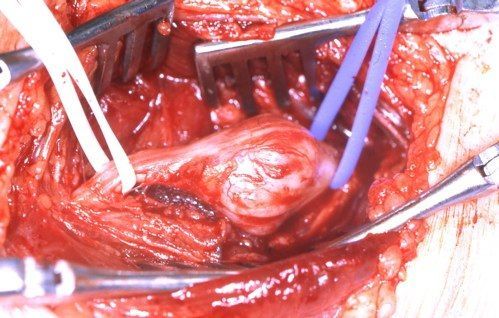
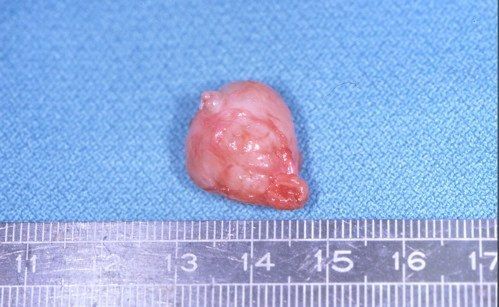
The procedure is different in cases of neurofibromatosis. Neurofibromatosis refers to a genetic predisposition to the development of numerous neurofibromas throughout the body (Recklinghausen’s disease).
Due to the large number of neurofibromas, all of which originate from different groups of nerve fibers, doctors may decide to leave the neurofibromas in place. This allows them to avoid a total loss of function in the affected main nerve.
The decision-making process in these cases is very complex and must be based on individual consultations between the patient and the doctor.
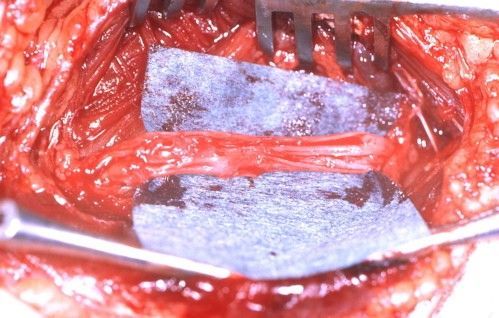
“Ganglia” and “pseudoganglia” are cysts filled with gelatinous fluid. The standard microsurgical approach is also used for these, particularly when the cysts are located inside the nerves—that is, intraneurally.
Here, too, it is necessary to identify the fibers located inside the nerve. The surgeon then carefully and gently separates the fiber bundles from one another. Afterward, dissection can proceed toward the cysts.
The surgeon drains the viscous contents of the cysts. However, he must not completely remove the outer membranes of these cysts. The cyst walls and the tissue surrounding the nerve fibers are so closely connected that doing so would also result in the removal of the nerve fibers.
Cysts that are attached only to the outside of the nerve are easier to remove.
During the preoperative consultation, the patient should be informed that a cyst can reform even after a successful operation.
This is particularly the case when there is a connection to the interior of a neighboring joint. In such cases, it is not possible to identify the connecting passage. Doctors are therefore unable to block it.
Medications for the Treatment of Nerve Tumors
Medications cannot influence the growth of a benign tumor. Therefore, surgical removal of the nerve tumor is the only option.
The situation is different with neurofibromatosis (Recklinghausen’s disease), a definable genetic disorder. In this case, it is possible that, in a few decades, treatment options based on human genetics may become available.
Possible Complications and Risks Associated with Nerve Tumor Surgery
Due to the complexity of the procedure, nerve damage may occur during surgery. The risk of this cannot be predicted in advance. The outcome may range from a minor loss of function to permanent functional impairment.
The extent of potential damage depends largely on the following factors:
- The surgeon’s experience
- Available microsurgical instruments, as well as
- the care and time taken during the surgical procedure
If the nerve tumor is successfully removed under the following conditions, only a temporary functional impairment will result:
- For intraneural cysts without sacrifice of nerve fibers,
- For schwannomas (neurinomas) involving the sacrifice of only a single fiber group, and
- In the case of neurofibromas, with sacrifice of at most one-quarter of all fiber groups
Any resulting motor impairments can be almost completely resolved through follow-up physical therapy.
Persistent nerve pain is very rare, but certain localized sensory disturbances are fairly common.
Neurofibromatosis, however, presents a completely different situation. If doctors unexpectedly discover it during the procedure, it may be necessary to terminate the surgery. To prevent severe damage to nerve function, certain conditions must be met, which are not always the case.
Follow-up Care After the Removal of a Nerve Tumor
If no complications—or only very minor ones—occurred during surgery, no follow-up physical therapy is required.
As a rule, the patient can recover from minor functional impairments through their own efforts. Sensory deficits, if they have occurred, are of course untreatable.
If a more severe and primarily motor functional deficit has occurred, follow-up physical therapy is required. Occupational therapy may also be necessary.
Experience shows that nerve fibers preserved after tumor surgery compensate for (or replace) the initial damage.
If multiple neurofibromas are present, genetic testing should be considered to determine the risk of inheritance.
Findings on Nerve Tumors
Nerve tumors are so rare compared to nerve injuries that no relevant statistical data is available.
There are only a few centers specializing in the treatment of nerve tumors that have compiled scientific findings.
These include, for example, the center in New Orleans led by David Kline. Medical researchers have found that neurinomas and neurofibromas in the extremities are more likely to develop closer to the trunk than farther away.
This finding has implications only for the surgeon: The internal structure of the nerve differs near the trunk compared to further away. The microsurgeon must take this into account.

Conclusion
Nerve tumors are predominantly benign and grow very slowly.
In the case of neurinomas and neurofibromas, they grow as solid masses originating from the Schwann cells of the nerve sheath.
In the case of cysts or pseudocysts, the encapsulated structures simply fill with fluid over time.
Despite these positive findings, the surgical treatment of a nerve tumor poses a challenge for the surgeon. It requires time, care, and microsurgical instruments.
Under these conditions, surgical removal of nerve tumors or cysts in peripheral nerves is always indicated. A “wait-and-see” approach would significantly reduce the chances of a successful outcome.
The larger a nerve tumor is, the less microsurgery can ensure the function of all nerve fibers within the affected nerve. There is therefore no reason to repeatedly justify a “wait-and-see” approach.
Share this article































