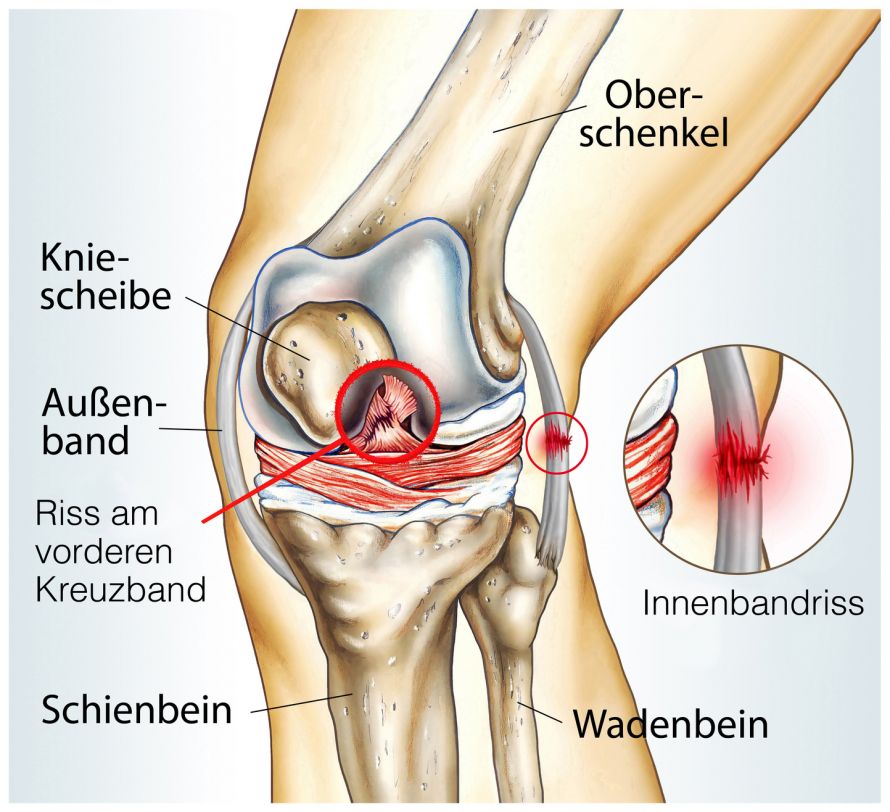
A cruciate ligament tear (ICD code: S83) is a partial or complete tear of a cruciate ligament in the knee joint. Either the anterior or posterior cruciate ligament may be affected. A distinction is therefore made between an anterior and a posterior cruciate ligament tear. In rare cases, both cruciate ligaments in the knee may be affected.
According to the Federal Statistical Office, 35,000 cases of an anterior cruciate ligament tear are diagnosed in Germany each year. This makes this injury one of the most common and, at the same time, one of the most serious injuries to the knee joint. In most cases, a cruciate ligament tear occurs suddenly, often during sports activities involving rapid changes in direction.
The cruciate ligament is one of the two main stabilizers of the joint. The anterior and posterior cruciate ligaments are located at the center of the knee joint. They stabilize the joint and support nearly the entire range of motion during running, walking, and jumping. Together with other ligaments in the knee, they ensure stability and proper guidance of the joint.
When the cruciate ligament fails, it leads to increased forward movement of the lower leg. The remaining structures inside the knee must then take over the stabilizing function. This often results in further damage to the meniscus, ligaments, and articular cartilage.
In the video below, you can view the anatomy of the knee joint:
People between the ages of 15 and 30 are most commonly affected, as this age group is very active in sports. Women have an injury rate up to eight times higher than men. Possible causes for this include, among others,
- hormonal influences,
- anatomical differences, and
- differences in training routines
. One in three cruciate ligament tears occurs alongside a meniscus injury. Concurrent injuries to ligaments and articular cartilage are also common.
In most cases, a cruciate ligament tear is the result of a sports-related injury, particularly in sports such as
- soccer,
- handball, and
- skiing.
However, workplace and traffic accidents are also common causes of cruciate ligament tears. Injuries to the anterior cruciate ligament often occur without any direct external force (>70% of injuries).
Typically, a cruciate ligament tear is caused by unexpected changes in direction. High acceleration forces—e.g., while skiing—cause the lower leg to rotate outward at the bent knee joint and, at the same time, cause the joint to open on its inner side (so-called valgus stress). The otherwise stable ligament is ultimately unable to withstand the forces acting upon it. A posterior cruciate ligament tear is usually caused by a direct force applied to the lower leg, such as in a car accident.
Also,
- inward rotations combined with outward tilting (so-called varus stress) as well as
- forceful extension and flexion movements
can lead to a cruciate ligament tear.
© Henrie / Fotolia
The classic mechanism of injury is a sudden and unexpected change in direction accompanied by twisting of the body while simultaneously coming to a stop at walking speed. The foot remains fixed to the ground during this movement. Contact with an opponent is not required. This is referred to as a “standing twist injury.”
A cruciate ligament tear is characterized by
- with severe pain as well as
- a tearing or shifting sensation in the knee, which can be heard as a popping sound.
A bruise forms quickly: a feeling of tightness and pain on weight-bearing develops.
Without immediate ice and compression treatment, the knee swells rapidly. The causes are
- hemarthrosis caused by a rupture of the arterial supply to the anterior cruciate ligament and
- bleeding into the peripheral soft tissues due to capsular injuries.
Knee effusion (joint effusion) may also occur.
In most cases, those affected are then unable to continue their athletic activities.
These acute symptoms of an anterior cruciate ligament tear usually subside within 10 to 14 days. The joint can then initially bear weight normally again. As time goes on, the patient often experiences a feeling of uncertainty and instability in the knee joint. If the knee becomes unstable, this can lead to further damage to the meniscus or cartilage. The joint’s ability to bear weight also gradually decreases in everyday life. Characteristic symptoms include:
- Unsteadiness when walking,
- spontaneous buckling of the knee joint,
- pain that worsens with weight-bearing, and
- difficulty extending and bending the knee.
Eventually, the persistent instability leads to secondary damage to the meniscus and articular cartilage. Up to 80 percent of those affected suffer a meniscus tear five to ten years after their cruciate ligament tear. This results in damage to another stabilizing structure of the joint. This increasing instability in the knee often leads to osteoarthritis later on.
Before a cruciate ligament tear is diagnosed, the first step is to take a medical history, which involves a consultation with the doctor. Since cruciate ligament tears are among the most common knee injuries, the focus is on a detailed analysis of how the injury occurred.
Medical History Interview
As part of the medical history interview, the treating doctor asks the patient the following questions:
- Is the current knee injury actually the result of a first-time accident, or was it preceded by a previous injury?
- Did the knee swell after previous twisting injuries, did it ever make a popping sound, or did the patient have to stop participating in sports due to an acute injury to the same knee joint?
- Was a puncture performed to drain blood?
- Was the injured person placed in a cast or given a bandage?
- Was the knee subsequently less stable than the healthy knee?
- Did swelling recur later on with even slight twisting?
The 5 most important questions about the symptoms:
- Severe pain deep within the joint?
- A popping sound (a very reliable sign if present, but may occasionally go unnoticed)?
- Swelling, effusion (1–24 hours after the injury)?
- Interruption of play or sports activity (skiers may occasionally still be able to complete runs due to the cooling effect of the cold)?
A positive answer to some of these questions suggests a previous anterior cruciate ligament tear. A feeling of instability with a tendency toward subluxation is indicative of chronic anterior cruciate ligament insufficiency.
© westfotos.de / Fotolia
Clinical Examination of the Knee Joint
The physician will thoroughly inspect and palpate the patient’s injured knee. Fresh skin changes provide clues as to the nature and severity of the injury. At the very latest, the detection of injury and surgical scars should prompt the examiner to inquire about the patient’s medical history.
Misalignment of the leg axes is of great prognostic significance. For example, varus deformities combined with posterolateral capsuloligamentous injuries lead to instability, resulting in a significant disability for the patient.
Active and passive range-of-motion tests complete the physical examination. During this process, the physician uses palpation and specific movement patterns to examine
- to identify tender points around the knee joint and
- the function of the ligaments.
Imaging Techniques
Imaging techniques, such as X-rays and magnetic resonance imaging (MRI), are usually used as a supplement. In particular, an anterior cruciate ligament tear can be reliably diagnosed using MRI images. There are limitations for patients who have previously undergone knee surgery involving metal implants.
Standard X-rays, ideally with a comparison to the uninjured side, can suggest a previous cruciate ligament injury based on
- osteophytes,
- early condylar flattening,
- narrowing of the joint space, and/or
- clumping of the cruciate ligament tubercles
.
Another radiological examination is scintigraphy. In recent years, it has gained importance for detecting “active” cartilage/bone lesions in the knee joint. “Hot spots,” for example, indicate active chondromalacia lesions with cell death.
Chondromalacia refers to cartilage damage in the joints. Unstable knee joints with hot spots should be stabilized whenever possible to slow the progression of these cartilage-related processes.
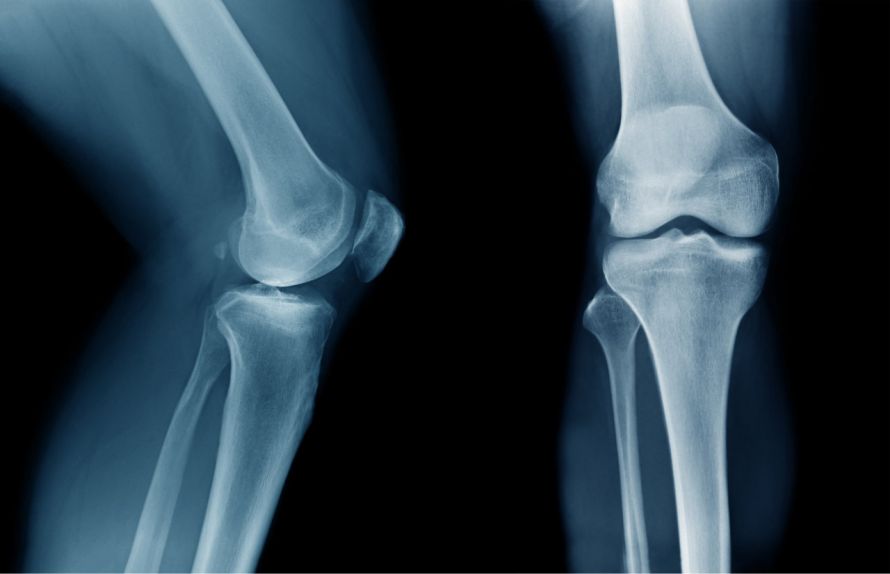
An X-ray can determine whether the bony structures have sustained damage following a cruciate ligament tear © angkhan | AdobeStock
The diagnosis and treatment of a cruciate ligament tear can generally be approached either conservatively or surgically.
Conservative treatment methods include, among other things,
- physical therapy to stabilize the knee joint and build muscle, as well as
- pain management, and
- cold therapy.
Patients—who are usually younger—very often wish to remain physically active. In principle, this is possible even without a functional anterior cruciate ligament, provided the knee joint has good muscle support.
But don’t be misled: Due to potential long-term complications, only about half of those affected are actually able to participate in sports without restrictions five years after an ACL tear. Furthermore, the long-term—and often decades-long—intensive muscle-building process is rather unlikely.
The anterior cruciate ligament should therefore be stabilized surgically as part of ACL reconstruction following a tear. Incidentally, this applies not only to young adults but also to children and older adults.
Modern arthroscopic techniques have completely replaced the older method, which required opening the entire joint. Techniques in which the torn cruciate ligaments were sutured back together are also outdated today.
Instead, the injured cruciate ligament is replaced with a tendon from the patient’s own body. You can see the cruciate ligament reconstruction procedure in the video:
When should surgery for a cruciate ligament tear be performed?
The ideal timing for surgical treatment following an anterior cruciate ligament tear is a matter of debate. To avoid complications during surgery, many surgeons wait at least four to six weeks for isolated cruciate ligament injuries.
If the body’s natural healing process in the injured joint has not yet begun, the procedure can also be performed immediately after the cruciate ligament tear.
Concomitant injuries also often determine the right timing. Meniscus injuries, in particular, are common and should be sutured promptly, provided it is technically feasible.
What material is used during the surgery?
The patellar tendon and the semitendinosus tendon are the primary materials considered for reconstruction following a cruciate ligament tear. The use of the patellar tendon is the gold standard. Various surgeons also primarily use the quadriceps tendon.
All grafts can present challenges during surgery. What is truly crucial is the correct placement of the replacement tendon within the knee joint. It must be positioned as precisely as possible in the exact same location as the original cruciate ligament. Only in this way can the knee joint regain nearly full load-bearing capacity and range of motion after a cruciate ligament tear. Correct placement is technically challenging for the orthopedic surgeon.
How is surgery performed for a cruciate ligament tear?
In most cases, a single tendon strand is inserted into the knee joint as a graft. This is referred to as the “single-bundle technique.”
However, this does not correspond to the anatomical structure: the cruciate ligament actually consists of three individual main fiber bundles. These are twisted together in a helical pattern. Biomechanical studies suggest that the anteromedial and posteromedial bundles provide the primary stability.
Consequently, an advanced surgical technique has been developed over the past few years that no longer involves the use of a single bundle. Instead, two slightly narrower grafts are used, which are positioned more closely to the original course of the two fiber bundles.
This modern double-bundle technique is primarily intended to prevent the unpleasant postoperative rotational instability that can occasionally persist after conventional surgery.
However, this advantage—which has not yet been definitively verified—is offset by
- greater surgical complexity,
- procedure-related complications,
- higher costs, and
- greater effort in the event of revision
.
This technique is currently still the subject of scientific debate and is not yet a routine procedure. Nevertheless, this therapeutic approach is extremely promising and represents a serious alternative in modern cruciate ligament surgery.
The severity of the knee injury also becomes apparent during follow-up care after a cruciate ligament tear. Rehabilitation is considered the most important measure for ensuring the long-term success of the surgery.
Follow-up care after cruciate ligament tear surgery must involve early functional rehabilitation. The goal is to achieve the fastest possible and complete extension of the knee joint up to 120° while the knee is flexed.
The ability to work—at least in an office setting—is typically restored after 14 days. Proper and time-intensive rehabilitation, however, takes considerably longer. It may not be completed until eight to ten weeks later, or even later.
This is almost always followed by further individualized progressive training. Full range of motion in the knee joint after a cruciate ligament tear is gradually restored through targeted rehabilitation exercises. As a result, light running training is usually only possible after three months. It is recommended to wait at least half a year before resuming sports that place stress on the knee.
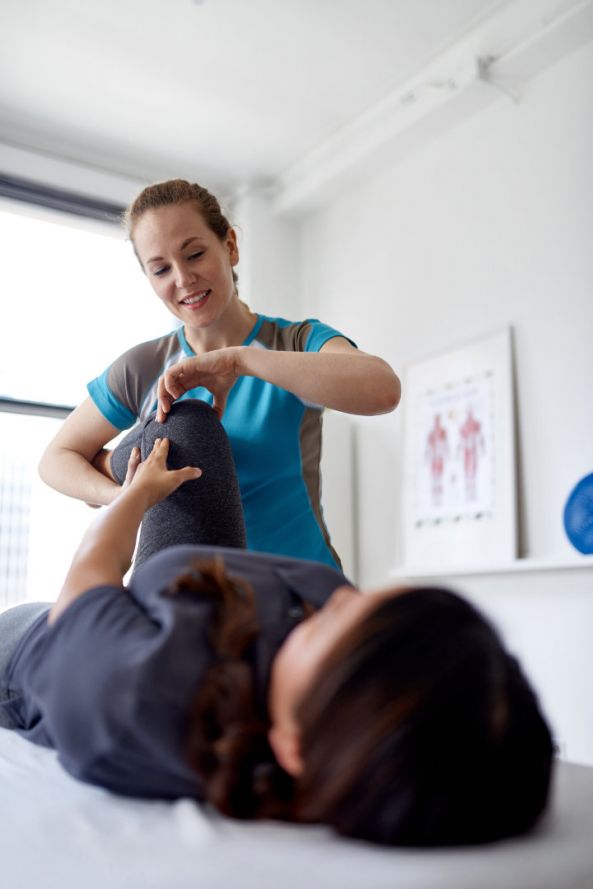
Rehabilitation is important for achieving good results after cruciate ligament tear treatment © AYAimages | AdobeStock
The long-term prognosis for a properly performed cruciate ligament replacement surgery is generally good: joint stability is ensured for years to come.
However, the development of osteoarthritis in the injured joint cannot always be prevented. Despite a successful surgery, it depends largely on pre-existing damage or accompanying meniscus injuries.
But: Only a stabilized joint has a chance of being truly protected against it.
The risk of suffering a cruciate ligament tear can be reduced through
- strength,
- proprioception, and
- coordination training
. This helps optimize movement patterns specific to daily life or a particular sport when faced with unfamiliar stress situations.
Training protective reflexes through balance exercises to maintain stability in extreme situations is very helpful. These include unforeseen events such as tripping or high demands on muscular coordination, such as during a skiing fall.
The trained muscles surrounding the knee joint are capable of absorbing significant stress when they are activated in a timely and properly coordinated manner. In the event of excessive stress or sudden forces, the stress is transferred directly to the knee ligaments. Gaining a moment’s time—which gives the muscles a chance to intervene—is the most important protective factor in this phase for counteracting trauma-induced overload and injuries such as a cruciate ligament tear.
In addition to preventive training, the use of a prophylactic knee brace to prevent a cruciate ligament tear is also worth considering. For a prophylactic orthosis (brace) to be designed and used effectively, it must be tailored to the specific sport being played. Movement patterns and injury mechanisms can vary greatly across different sports.
For example, sports like soccer or American football cannot be compared to ice hockey. Soccer and American football require the leg to be more firmly anchored to the ground (cleats). In ice hockey, on the other hand, the goal is to minimize friction and reduce fixation to the surface (ice).
To date, as part of our 10-year prospective study, more than 100 prophylactic braces have been fitted for ice hockey players. They have consistently yielded positive results. Based on our experience with the national ice hockey team, the use of orthoses as a preventive measure against cruciate ligament tears and other injuries in this sport is recommended.
1. How does a cruciate ligament tear occur in the knee joint?
It usually occurs during sudden changes in direction, jumps, or rotational movements of the knee joint—often during sports such as soccer, handball, or skiing. These movements cause the anterior or posterior cruciate ligament to be overstretched, which can result in a partial or complete tear.
2. What symptoms indicate a cruciate ligament tear?
Typical symptoms include severe pain, an audible popping sound at the moment of injury, swelling, bruising, and instability in the knee. Those affected often feel as though the knee “gives way” or buckles when walking.
3. How is a cruciate ligament tear diagnosed?
The diagnosis is made through a thorough examination of the knee joint, including range-of-motion tests, as well as imaging procedures such as X-rays and MRI. These show whether the anterior or posterior cruciate ligament is affected and whether there are any associated injuries, such as meniscus or cartilage damage.
4. How is it treated—conservatively or surgically?
Depending on the severity of the injury and the patient’s activity level, a cruciate ligament tear can be treated conservatively with physical therapy, muscle strengthening, and pain management, or surgically through cruciate ligament reconstruction. For people who are active in sports, surgery is usually recommended to restore the stability of the knee joint.
5. How long does recovery take after surgery?
Rehabilitation after surgery takes several months. Light weight-bearing is often possible after about two weeks, but sports activities should not be resumed until about six months later. Consistent follow-up treatment with physical therapy and rehabilitation exercises is crucial for success.




































